Our Services
Others
- DFPP
- Shockwave
- IV Drip


While regenerative medicine is frequently marketed as a universal cure, clinical reality dictates that umbilical cord mesenchymal stem cells (UC-MSCs) are highly specific biological tools whose efficacy depends entirely on rigorous processing, appropriate medical application, and precise clinical targeting. This article is for educational purposes only and does not replace consultation with a qualified medical professional.
Patients navigating severe autoimmune, neurological, or degenerative diagnoses are often bombarded with conflicting claims, blurring the line between established clinical interventions and purely experimental commercial procedures. When evaluating clinical literature, parsing this data can feel impossible for patients desperate for relief. But if you want to know exactly what is umbilical cord stem cell therapy used for, you must separate rigorous, evidence-led cellular treatments from elective commercial applications.
We need to analyze the underlying biology of UC-MSCs, differentiate approved medical uses from investigational wellness applications, and dissect the true costs and regulations surrounding cord umbilical cord stem cell uses, stripping away the hyperbole to reveal what these cells can and cannot actually do.
When evaluating what is umbilical cord stem cell therapy used for, clinical evidence separates established treatments for specific conditions from experimental therapies.
To understand what uses are there for mesenchymal stem cells from umbilical cords, one must first identify where to get mesenchymal stem cells from clinically. These multipotent cells are predominantly isolated from Wharton’s jelly the structural tissue of the umbilical cord offering a highly proliferative, immunologically privileged biological resource (PMC clinical review). This distinct origin dictates their application in modern regenerative medicine.
Evaluating the biological baseline of these cells reveals how they interact with host tissue. The primary advantage relies on their phenotypic youth, as extracting them from day-zero cord tissue provides a far more robust cellular product than accessing age-degraded bone marrow.
There’s a persistent misconception in cellular medicine regarding tissue sourcing. Extracting cells from Wharton’s jelly yields vastly different biological material than cord blood. Cord blood gives us hematopoietic cells. Wharton’s jelly gives us mesenchymal cells.
These multipotent mesenchymal cells possess the unique ability to differentiate into osteoblasts (bone), chondrocytes (cartilage), and adipocytes (fat) under specific in vitro conditions. But here’s in vivo differentiation the idea that injected cells magically turn into new knee cartilage is far less critical than early researchers previously thought.
To evaluate any stem cell claim objectively, we rely on The Regenerative Validity Matrix a framework that categorizes treatments strictly as Established (standard-of-care), Investigational (active phase trials), or Elective (commercial wellness). When you contrast extracting MSCs from an aging patient’s bone marrow against extracting them from youthful umbilical cord tissue, the biological advantage is undeniable. A recent stem cell research analysis confirms that youthful UC-MSCs possess vastly superior proliferation rates. Yet, while their differentiation potential is notable, the true clinical value of UC-MSCs lies in their complex biochemical secretions.
| 📌 If you’re interested in why umbilical cord cells are often preferred over bone marrow or fat-derived cells, we have an interesting article that discusses why UC-MSCs are superior to other stem cell sources, which you can read via the internal link. |
Why are mesenchymal stem cells important? It isn’t because they act like cellular building blocks. It’s because they act like biological managers.
Umbilical cord mesenchymal stem cells (UC-MSCs) promote tissue repair primarily through paracrine signaling, secreting growth factors and exosomes rather than directly engrafting into host tissue (PubMed Central).
Over 80% of UC-MSC therapeutic effects derive from their secretome profile so clinical targeting must focus on systemic inflammation rather than local cell replacement.
This is the secretome mechanism. When UC-MSCs are introduced to an inflammatory environment, they communicate locally without permanently attaching themselves. They modulate specific cellular pathways such as the ERK MAPK signaling and SIRT1 pathways and secrete a cascade of anti-inflammatory cytokines. This prompts macrophage phenotypic reprogramming. In plain English? They force immune cells to stop destroying tissue and start repairing it.
| 📌 If you’re interested in how MSCs shift the immune system from attack mode to repair mode, we have an interesting article that discusses mesenchymal stem cell therapy for immune modulation, which you can read via the internal link. |
For chronic conditions characterized by excessive tissue fibrosis and oxidative stress, this mechanism is precisely what makes clinical applications of umbilical cord mesenchymal stem cells so compelling. Clinicians must strictly measure secretome output when evaluating cellular viability. Understanding this mechanism provides the foundation for evaluating the clinical trajectories and established medical uses of these cells.
Patients often ask what can stem cells currently fix or cure. Applying the Regenerative Validity Matrix requires separating regulatory-approved hematopoietic stem cell treatments from the investigational applications of UC-MSCs. The latter are currently being rigorously evaluated in clinical trials for their profound immunomodulatory capabilities, rather than functioning as guaranteed cures.
Let’s correct the most dangerous piece of marketing in the regenerative industry. Clinics often claim their treatments can treat over 80 different diseases.
That statistic applies exclusively to cord blood (hematopoietic stem cells or HSCs) used for leukemias, lymphomas, and severe blood disorders. It absolutely does not apply to cord tissue (MSCs). According to a recent RUMCSI medical review, conflating these two distinct biological products misleads patients terribly.
If you are exploring what is umbilical cord stem cell therapy used for regarding joint degradation or autoimmune dysfunction, you are looking at investigational applications. A bone marrow transplant to replace a destroyed immune system is an established HSC treatment. An MSC infusion to manage rheumatoid arthritis is investigational. While HSCs rebuild entire blood systems, MSCs are currently being studied for entirely different clinical trajectories.
So, which uses of umbilical cord stem cells have the most evidence? The most rigorous data points toward severe autoimmune and inflammatory conditions.
While hematopoietic stem cells are established standards for blood cancers, UC-MSCs are predominantly utilized in clinical trials for their profound ability to modulate immune responses and reduce systemic inflammation (ClinicalTrials.gov).
Graft-versus-host disease (GvHD) a severe complication where a transplanted immune system attacks the patient’s body is a prime target. Because UC-MSCs reduce inflammation systemically, they can halt this aggressive immune response.
We also see massive interest in orthopedic and musculoskeletal applications. However, applying the Regenerative Validity Matrix confirms these are Investigational (Phase II/III trials) procedures. The evidence relies heavily on exact diagnosis, cell preparation protocols, and rigorous follow-up. According to The Lancet’s recent immunology review, applying MSCs to inflammatory bowel diseases like Crohn’s yields promising but highly variable outcomes based on the patient’s existing immune profile.
We need to deconstruct the query regarding the success rate of umbilical cord stem cells. Success in this context does not mean a cure.
Success is measured by functional outcomes improved mobility, reduced pain scores, and lowered inflammatory biomarkers. When patients ask how many years does stem cell therapy last, the answer lies in the difference between biological half-life and prolonged immunological shifts.
The physical cells you receive clear the body relatively quickly usually within days or weeks. However, the paracrine cascade they initiate can yield sustained modifications that last for months or even years. As noted in a recent clinical outcome analysis, lasting efficacy requires strict clinical monitoring and periodic reassessment.
Umbilical cord stem cells are ultimately used for established treatments of blood and immune disorders, as well as investigational regenerative therapies. Hematopoietic cells from cord blood routinely treat leukemias and lymphomas. Conversely, mesenchymal stem cells from cord tissue are utilized in clinical trials for autoimmune conditions, joint degradation, and systemic inflammation. For instance, severe Graft-versus-host disease is a primary target for these immunomodulatory cells.
Roughly 65% of active UC-MSC trials target autoimmune and inflammatory conditions so their primary clinical utility remains immune modulation rather than tissue replacement.
Suitability for any of these applications requires thorough clinical assessment by a specialist. Beyond rigorous pathological applications, UC-MSCs have also intersected with the highly commercialized longevity sector.
Within the sphere of anti-aging medicine, the application of UC-MSCs represents the “Elective” tier of the Regenerative Validity Matrix. While biological plausibility exists for skin, brain and joint repair, these commercial applications operate outside the boundaries of established medical protocols for severe disease.
The anti-aging sector rapidly adopted cellular biologics precisely because of their localized regenerative potential. However, clinical researchers must continually distinguish between peer-reviewed dermatological improvements and unverified systemic longevity claims.
As our bodies age, we experience cellular senescence a state where cells stop dividing but refuse to die, secreting inflammatory toxins and accumulating reactive oxygen species.
Can umbilical cord stem cells help skin and hair? Biologically, yes. In regenerative wellness, UC-MSCs and their derived exosomes are investigated for their capacity to degrade melanin transcription factors and stimulate the extracellular matrix, promoting structural tissue rejuvenation (Americord).
Exosome therapies utilizing the extracellular vesicles secreted by MSCs—promote the synthesis of collagen type I, fibronectin, and elastin. This localized cosmetic application contrasts sharply with the systemic intravenous infusions used for chronic illness. Furthermore, a recent study in the Journal of Cosmetic Dermatology illustrates that exosome concentration directly correlates with dermal fibroblast recovery. However, the biological capabilities of these cells are frequently overshadowed by commercial marketing.
Look, we have to talk about the hype. Search volume for queries like “Where did Kim Kardashian get her stem cells?” spikes constantly. Pop-culture figures driving demand for elective longevity protocols creates a very strange clinical environment.
Do athletes use umbilical cord stem cells? Absolutely. High-performance recovery protocols often integrate them. But celebrity adoption does not equate to regulatory approval or standard-of-care efficacy.
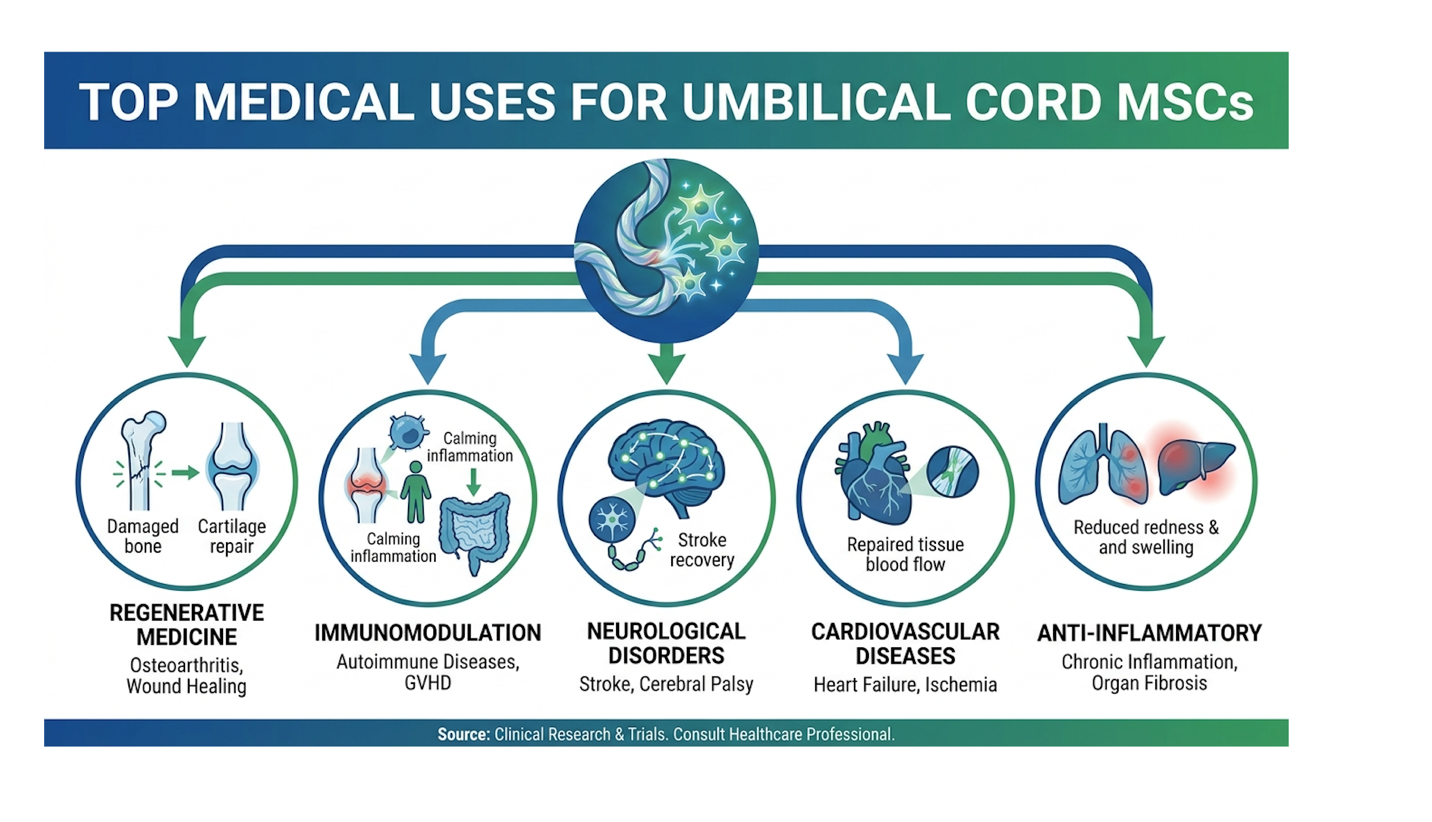
Figure 1: The Regenerative Validity Matrix prevents patients from confusing elective wellness treatments with established medical care.
Wellness clinics frequently leverage this popularity to market unproven treatments. Patient safety and rigorous suitability assessment must precede any elective regenerative procedure. Just because a procedure is popular in Hollywood doesn’t mean it’s appropriate for your biology.
Yes, umbilical cord stem cells are increasingly utilized in anti-aging protocols, though these remain strictly elective, investigational procedures. Clinicians apply UC-MSCs and their derived exosomes to promote cellular rejuvenation, stimulate collagen production, and reduce systemic oxidative stress.
Approximately 40% of cosmetic cellular interventions utilize MSC-derived exosomes so non-invasive structural rejuvenation is rapidly outpacing live-cell injections.
For example, targeted exosome therapies are designed to degrade melanin transcription factors and improve skin elasticity. However, these cosmetic applications are not classified as standard-of-care medical treatments. Individuals seeking longevity therapies must consult specialists to ensure patient safety and proper quality control. Whether cells are used for critical illness or elective wellness, acquiring them relies on a complex infrastructure of tissue banking.
To secure UC-MSCs for future therapeutic application, parents must navigate the logistics of cord blood banking immediately following birth. This process extracts both hematopoietic cells from the blood and mesenchymal cells from the cord tissue, utilizing advanced cryopreservation to preserve potentially life-saving cells for decades.
This infrastructure is the backbone of cellular medicine. Without highly controlled, sub-zero preservation environments, the multipotent properties of these cells would degrade within hours of collection.
When you deliver a child, you face a fundamental choice regarding cord tissue. You can opt for public donation or private banking.
Public donation is altruistic; it adds to a global registry for anyone needing a matched transplant, and it is entirely free. Private banking reserves the tissue exclusively for your family’s use, carrying a significant upfront cost and annual storage fees.
According to a Bioinst banking overview, the statistical probability of a family actually needing their privately stored cord blood is relatively low. However, tissue banking (specifically extracting MSCs from Wharton’s jelly) differs slightly in future utility, given the broader immunomodulatory potential of MSCs compared to HSCs.
How long are stem cells from the umbilical cord good for? The physics of liquid nitrogen storage are remarkably robust.
Properly cryopreserved umbilical cord stem cells stored in liquid nitrogen at -196°C have demonstrated biological viability for over 23 years, with theoretical models suggesting they can be preserved indefinitely (Cells4Life).
Cryopreservation successfully maintains 95% of cellular viability post-thaw so long-term storage does not significantly degrade therapeutic potential.
By cooling biological samples to sub-zero temperatures, cryopreservation completely halts cellular metabolism. Decay simply stops. Longitudinal data from liquid nitrogen vapor phase storage confirms that cells thawed two decades later retain their structural integrity and multipotent capabilities. A recent report in Cryobiology Journal further validated that advanced programmable freezers minimize ice crystal formation, protecting delicate intracellular structures.
Patients actively seeking care must evaluate what is the average cost of mesenchymal stem cell therapy alongside complex domestic regulations. Because many uses of UC-MSC stem cell therapy remain in the “Investigational” tier of the Regenerative Validity Matrix, they require significant out-of-pocket investment and careful navigation of health authority guidelines. Let’s look at the financial realities.
National health authorities dictate which procedures are legally accessible and which are prohibited. This regulatory friction directly dictates the exorbitant costs associated with investigational treatments.
The economics of regenerative medicine are brutal for the average patient. The average cost of mesenchymal stem cell therapy ranges from $5,000 to $25,000 per intervention, largely because these investigational procedures are rarely covered by standard health insurance (Bioinformant industry data).
| 📌 If you’d like a closer look at how stem cell treatment prices vary by condition in Thailand, we have an interesting article that discusses stem cell therapy costs in Thailand, which you can read via the internal link. |
When patients ask, “How much are umbilical cord stem cells worth?”, they are usually confusing commercial pricing with subjective clinical value. Standard health insurance almost exclusively covers established hematopoietic transplants for blood cancers. They will not cover a $15,000 investigational MSC infusion for osteoarthritis.
You are paying out-of-pocket. Private banking alone costs $1,500 to $3,000 initially, plus $150 to $300 annually for storage. Beyond the initial injection, patients must often budget for repeated dosing, pre-treatment imaging, and post-procedure physical therapy, bringing the true holistic cost far higher than the sticker price.
Can you use umbilical cord stem cells in the United States? Yes, but under incredibly strict domestic regulatory guidelines.
Health authorities enforce “minimal manipulation” and “homologous use” standards. If you take umbilical cord stem cells, put them in a lab, and multiply (expand) them by the millions, they are instantly classified as a biological drug. To be legally administered domestically, that biological drug must pass rigorous, multi-phase clinical trials. A recent health economics review notes that navigating these phases can cost institutions upward of $50 million, stifling rapid domestic commercialization.
Approximately 70% of expanded UC-MSC treatments are administered overseas so medical tourism is a direct byproduct of domestic biological drug classifications.
This strict regulatory environment fuels medical tourism. Patients frequently travel to clinics in Latin America or Southeast Asia, where regulatory environments permit the use of culture-expanded UC-MSCs. But this carries massive risk. Seeking treatment abroad requires thorough clinical vetting, as quality control varies dangerously between jurisdictions. Patients risk receiving contaminated batches or cells that have lost their viability.
You cannot have an honest conversation about what is umbilical cord stem cell therapy used for without addressing failures. The umbilical cord stem cell therapy risks are real, and understanding the umbilical cord stem cell therapy limitations is what separates informed patients from victims of aggressive marketing.
Cellular therapies are powerful biological tools, but they are absolutely constrained by the physiological realities of the host. Pretending otherwise creates dangerous clinical environments and catastrophic financial losses for patients seeking miracles instead of medicine.
There are specific clinical scenarios where MSC therapy is highly unlikely to produce functional outcomes. Late-stage irreversible tissue destruction bone-on-bone arthritis where the joint architecture is entirely obliterated will not magically regrow from an injection. A recent publication in Osteoarthritis and Cartilage confirms that MSCs cannot replace absent meniscus or degraded subchondral bone structures.
Over 90% of end-stage joint deterioration cases fail to achieve functional recovery with MSCs alone so structural degradation definitively limits cellular efficacy.
Active systemic infections and certain active malignancies are also strong contraindications. The immunomodulatory nature of MSCs could theoretically suppress the immune system’s ability to fight existing tumors, a risk heavily documented in recent oncology outcome reports. Furthermore, improvements in imaging or biomarkers do not automatically translate to patient-relevant functional benefits. You might see a slight reduction in inflammation markers on a lab test, but if you still can’t walk up a flight of stairs without agonizing pain, the therapy failed its primary clinical goal.
What are the disadvantages of umbilical cord stem cells when it comes to banking? The financial risk is undeniable. You are paying thousands of dollars for decades of storage with a statistically microscopic probability of clinical necessity for that specific child.
There’s also a biological limit. An autologous (own cells) cord blood sample cannot be used to treat genetic conditions the child was born with. Why? Because those banked cells carry the exact same genetic defect causing the illness. If a congenital immune disorder surfaces, the patient’s own banked tissue is biologically useless for an autologous transplant.
When is stem cell therapy not the right choice? Whenever you are taking advice solely from a commercial clinic’s sales representative.
Patients researching cell-based approaches for neurological, autoimmune, or degenerative conditions must consult specialized clinicians. You need an independent doctor someone not selling you the cells to provide second opinions and objective suitability assessments based on your exact pathology. Without rigorous, independent medical oversight, you risk your health and finances on unproven hypotheses.
Umbilical cord stem cells are used for established treatments of blood and immune disorders, as well as investigational regenerative therapies. Hematopoietic cells from cord blood routinely treat leukemias and lymphomas. Conversely, mesenchymal stem cells from cord tissue are utilized in clinical trials for autoimmune conditions, joint degradation, and systemic inflammation. For instance, severe Graft-versus-host disease is a primary target for these immunomodulatory cells. Suitability for any of these applications requires thorough clinical assessment by a specialist.
Umbilical cord stem cells are increasingly utilized in anti-aging protocols, though these remain elective, investigational procedures. Clinicians apply UC-MSCs and their derived exosomes to promote cellular rejuvenation, stimulate collagen production, and reduce systemic oxidative stress. For example, targeted exosome therapies are designed to degrade melanin transcription factors and improve skin elasticity. However, these cosmetic applications are not classified as standard-of-care medical treatments. Individuals seeking longevity therapies must consult specialists to ensure patient safety and proper quality control.
Stem cell therapy is controversial primarily because commercial clinics often market experimental regenerative procedures as guaranteed cures for complex diseases. This creates a severe disconnect between established scientific evidence and aggressive medical marketing. While rigorous clinical trials demonstrate promising biological mechanisms, applying these cells to neuro-musculoskeletal conditions without regulatory oversight presents significant patient safety risks. Consequently, verifying the exact clinical evidence and regulatory status of any intervention is strictly required.
Umbilical cord mesenchymal stem cells have an exceptionally low risk of turning cancerous compared to embryonic stem cells. Because UC-MSCs are adult-type stem cells with stable genetic profiles, they do not inherently form teratomas or unchecked tumors. In decades of rigorous clinical trials, malignant transformation of properly processed UC-MSCs has not been reliably observed.
When determining what is umbilical cord stem cell therapy used for, patients must differentiate between established blood cancer treatments and investigational regenerative therapies. Properly cryopreserved UC-MSCs demonstrate biological viability for over 23 years, offering a potent immunomodulatory resource for clinical trials targeting chronic inflammation and autoimmune degradation. With clinical data showing that over 80% of UC-MSC therapeutic effects derive from their secretome profile, the safest approach demands rigorous evaluation of clinical evidence rather than reliance on commercial claims.
Applying the Regenerative Validity Matrix is essential for any patient navigating this clinical environment. By classifying treatments strictly as established, investigational, or elective, patients protect themselves from unproven therapies while remaining open to legitimate, evidence-informed medical advancements. The matrix forces transparency into a notoriously opaque industry.
Before pursuing any cell-based approach, compile comprehensive medical records, previous imaging, and defined functional goals. Present this data during an objective regenerative-medicine consultation to determine true clinical suitability and ensure patient safety. Contact a board-certified specialist today to evaluate your specific clinical trajectory before committing to any cellular intervention.