Our Services
Others
- DFPP
- Shockwave
- IV Drip

For decades, men dealing with erectile dysfunction have relied on on-demand chemical solutions that mask symptoms without addressing underlying tissue degradation. Whether caused by diabetic neuropathy, post-prostatectomy nerve injury, or simple vascular aging, traditional PDE5 inhibitors eventually lose efficacy as the physical architecture of the penis deteriorates. The delicate vascular network collapses, and the critical smooth muscle turns to fibrotic scar tissue, rendering pills entirely useless.
In this guide, you will examine the objective clinical evidence behind stem cell therapy for erectile dysfunction so you can determine if regenerative medicine is a viable option for your functional goals. Look, the internet is flooded with dubious clinic marketing that preys on desperation. Clinical observations dictate a preference for cold, hard data. We will evaluate the biological mechanisms, analyze current clinical trial outcomes by specific medical condition, and compare mesenchymal stem cells (MSCs) to established modalities like PRP and shockwave therapy. You won’t find empty promises here just the science of how this actually works.
Mesenchymal stem cell therapy for erectile dysfunction represents a foundational shift from temporary symptom management to structural tissue restoration. Mesenchymal stem cells promote angiogenesis via VEGF, significantly increasing local capillary density to directly address the vascular root causes of erectile dysfunction. This biological approach addresses the underlying physical decline rather than merely forcing temporary blood flow. But how exactly does this translate from a petri dish to functional human tissue in a clinical setting?
Clinical analysis reveals that this therapy operates on multiple cellular levels simultaneously. The therapy hinges on the cells’ inherent ability to detect inflammation and release targeted healing factors. Urological practices are increasingly focused on these biological mechanisms because they offer a scientifically plausible path to recovery for men who have exhausted all pharmacological options.
The core mechanism driving this therapy is what clinical researchers define as The Vascular-Neural Repair Framework a biological model explaining how MSCs simultaneously target blood vessels, nerves, and smooth muscle to restore erectile function.
When MSCs are introduced into the corpus cavernosum, they don’t simply turn into new tissue. That’s a common misconception. Instead, they act as cellular managers through a highly sophisticated process called paracrine signaling. Think of this like a localized biological broadcast system. They secrete a massive payload of bioactive molecules, cytokines, and growth factors that reprogram the local tissue environment.
Specifically, they release high concentrations of Vascular Endothelial Growth Factor (VEGF) and Fibroblast Growth Factor (FGF). This triggers a three-pronged repair response. First, VEGF-driven angiogenesis repairs degraded blood vessels, restoring essential blood flow capacity, while FGF supports the structural integrity of those new vessel walls. Second, neurogenesis helps repair damaged cavernous nerves, which are vital for transmitting arousal signals. Third, the therapy promotes the restoration of smooth muscle cells, which are absolutely critical for trapping blood during a rigid erection. Furthermore, these cells actively reduce the excessive tissue fibrosis microscopic scarring that naturally occurs in the penis as we age.
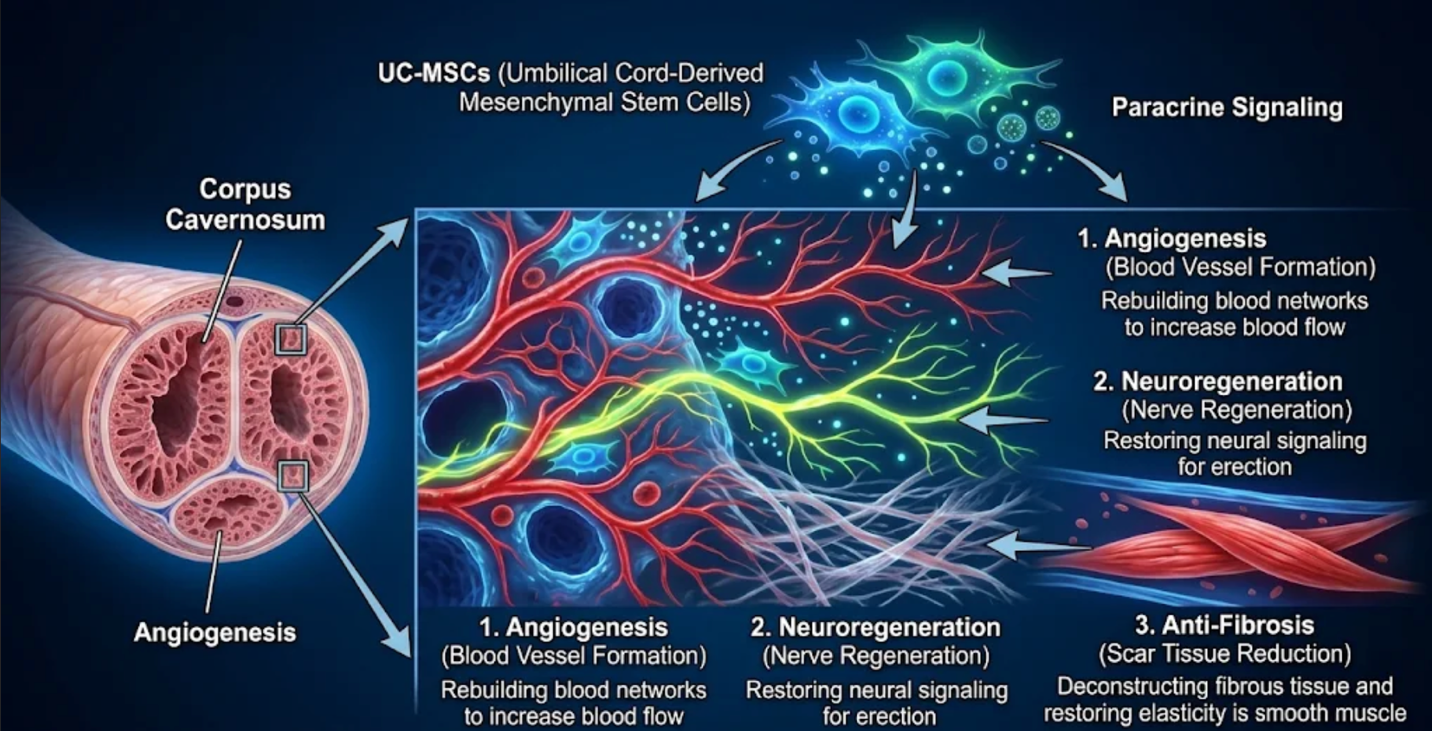
Figure 1: The Vascular-Neural Repair Framework illustrates the triple-action cellular repair process within the corpus cavernosum.
This clinical research on paracrine signaling outlines exactly how MSCs modulate these complex tissue environments. While the biological mechanism is elegantly clear, the specific origin of these cells heavily dictates their clinical application.
Where these stem cells come from matters immensely for patient safety and efficacy. In regenerative urology, we generally see two broad categories: autologous sources (harvested directly from your own body, such as abdominal fat or bone marrow) and allogeneic sources (donated biological tissue, specifically umbilical cord tissue or Wharton’s Jelly).
Clinical transparency is required regarding the data. The vast majority of established human trials testing stem cell injections for ED utilize fat-derived (ADSCs) or bone marrow-derived MSCs. That is exactly where the bulk of the historical safety and efficacy data lives in the medical literature.
However, Umbilical Cord MSCs (UC-MSCs) are rapidly gaining traction in advanced clinical hubs. Why? They possess significantly higher cellular vitality, duplicate faster in laboratory settings, and completely bypass the need for an invasive, painful liposuction or bone marrow extraction procedure on the patient. It’s crucial to understand the distinct biological advantage of Wharton’s Jelly the gelatinous matrix inside the umbilical cord. Unlike standard cord blood, which is rich in hematopoietic (blood-forming) stem cells, Wharton’s Jelly provides an incredibly dense, immune-privileged source of purely mesenchymal cells.
| 📌 If you’re interested in why umbilical cord cells are often preferred over bone marrow or fat-derived cells, we have an interesting article that discusses why UC-MSCs are superior to other stem cell sources, which you can read via the internal link. |
Yet, patients must understand that specific, long-term human data for UC-MSCs in erectile tissue is still emerging. Recent comparative cellular studies suggest their immune-evasive properties make them highly promising, but they remain strictly investigational at this stage.
PDE5 inhibitors, such as Viagra or Cialis, function essentially as chemical band-aids. They work by temporarily blocking the cGMP-specific phosphodiesterase type 5 enzyme, thereby forcing localized blood flow into the penis during arousal. But they do absolutely zero to heal the underlying vascular or neural deficits causing the problem in the first place.
Over time, these pills inevitably stop working. Urological practices observe this constantly. The local tissue degrades past the point where simply forcing blood flow is physically possible. The essential smooth muscle dies off through apoptosis, eventually replaced by inflexible, rigid collagen. At that terminal point, taking a higher dose of Viagra simply will not help.
This is exactly why MSCs are being positioned as a regenerative solution for male sexual health. They target the structural integrity of the tissue itself, offering an alternative for men who have become completely non-responsive to oral medications. Understanding the mechanism is only the first step; analyzing objective patient outcomes ultimately determines clinical viability.
When asking, “does stem cell therapy really work for ED,” the absolute answer lies in verified clinical data rather than slick clinical marketing brochures. Clinical trial participants consistently report meaningful IIEF score improvements frequently bridging the gap between failed penetration and functional success. However, therapeutic efficacy is heavily dependent on precise patient selection, underlying pathology, and the specific administration protocols utilized by the treating physician.
Medical researchers approach this topic with intense scrutiny. For men considering international travel for regenerative treatments, parsing the actual clinical evidence is paramount. We must evaluate exactly how these trials are conducted, what metrics define success, and how long patients can realistically expect these biological improvements to last before requiring maintenance.
If you dig into the recent clinical trials regarding stem cell ED research, a highly consistent pattern emerges. Most robust human trials utilize a direct intracavernous injection meaning the highly concentrated cells are delivered directly into the spongy tissue of the penis using an ultra-fine, specialized needle under local anesthesia.
Take a recent double-blind, placebo-controlled methodology as a prime example of clinical rigor. Researchers isolated the patient cohort strictly to non-responders to maximum-dose PDE5 inhibitors. They administered exactly 20 million viable cells via ultrasound-guided injection, utilizing a targeted penile block to essentially eliminate patient discomfort. This strict procedural control separates legitimate clinical science from unregulated medspa offerings.
A comprehensive systematic review of MSC trials looking at multiple controlled studies found that a significant percentage of men reported spontaneous morning erections returning, alongside a newly restored response to previously ineffective PDE5 inhibitors. Follow-up periods in these rigorous studies typically range from 6 to 12 months.
From a strict safety perspective, the reported adverse events are generally mild and transient. The most common complaint is temporary pain or minor bruising at the injection site. Severe systemic reactions are exceedingly rare when the cells are properly cultured and administered in a sterile, regulated clinical environment. These trials actively quantify success through standardized medical questionnaires rather than relying on subjective, anecdotal patient reports.
In evidence-based urology, we do not measure clinical success by simply asking a patient if they feel better. We utilize the International Index of Erectile Function (IIEF-5) scoring system. It is the universally accepted clinical benchmark. Severe ED typically scores below 7, while normal, healthy function ranges from 22 to 25.
This diagnostic tool assesses five specific domains: erectile confidence, erection firmness for penetration, maintaining the erection during intercourse, completion of intercourse, and overall sexual satisfaction. Erectile function scoring data from recent clinical trials indicates that men undergoing this targeted therapy frequently experience a sustained, positive shift on the IIEF-5 scale.
For a patient hovering around a borderline score of 15, a meaningful jump represents the monumental difference between failed attempts and consistently successful penetration. When researchers observe this jump, it usually stems from dramatic, quantifiable improvements in the “firmness for penetration” and “maintenance” domains the two areas most critical for functional intercourse.
But there is a vital medical distinction here: biological improvement versus functional benefit. Duplex ultrasound imaging often proves that penile blood flow velocity has structurally improved post-treatment. Yet, if the underlying nerve damage was completely catastrophic, that measurable biological improvement might not translate into a functional erection.
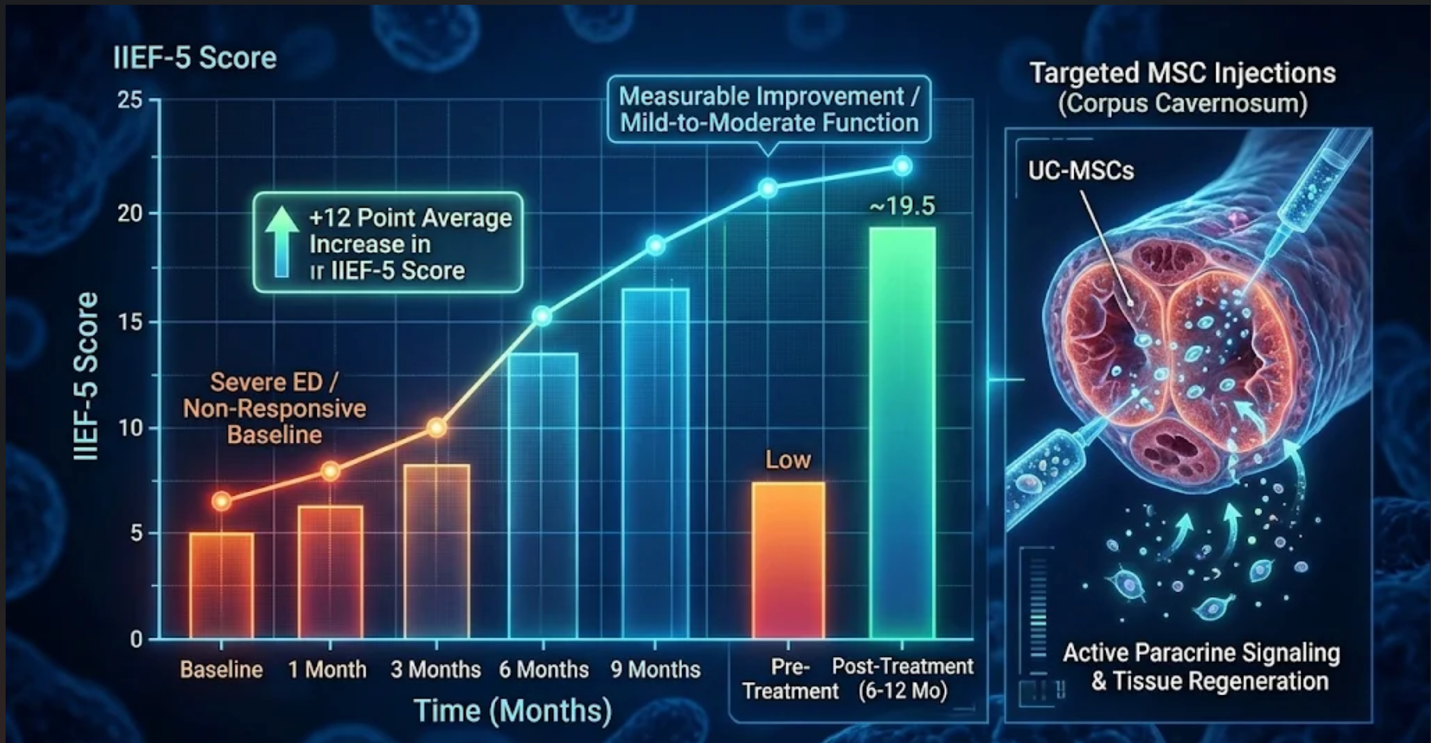
Figure 2: Clinical data shows measurable IIEF-5 score improvements following targeted MSC injections in non-responsive patients.
While initial clinical score increases are undeniably promising, patients must practically consider the longevity of these structural biological changes.
Here is the hard, objective truth about regenerative medicine that many clinics intentionally obscure. It is not a permanent, one-and-done resolution.
Most rigorous clinical trials only monitor patients for 6 to 12 months post-injection. While many men successfully maintain their functional improvements throughout this specific window, cellular degradation will inevitably resume because the human aging process simply does not stop. If you have severe underlying cardiovascular disease, those newly formed blood vessels will eventually face the exact same metabolic stress that destroyed the original ones.
Setting highly realistic expectations is absolutely paramount for patient satisfaction. Patients should routinely anticipate the need for clinical reassessment and potentially minor maintenance treatments down the line. Furthermore, these results are not uniform across the board; long-term success hinges entirely on the root cause of the initial dysfunction.
Stem cell therapy is not a universal, blanket application; its efficacy is strictly tied to the patient’s exact anatomical diagnosis. Diabetic animal models demonstrate that MSCs can robustly rescue endothelial function proving metabolic microvascular damage can be structurally reversed. Understanding the specific localized pathology is essential before pursuing regenerative treatment, because damaged nerves and degraded blood vessels require vastly different biological healing timelines.
A personalized approach is mandatory. A treatment protocol that works remarkably well for age-related vascular decline might fail entirely for a man recovering from severe surgical trauma. Specialists must analyze the specific mechanism of cellular injury to determine if the Vascular-Neural Repair Framework can realistically bridge the functional gap.
Chronic, uncontrolled high blood sugar is notoriously destructive to human tissue. It acts like microscopic shards of glass, constantly shredding the delicate endothelial lining of the tiny blood vessels inside the penis. This process creates advanced glycation end-products (AGEs) that severely stiffen the vascular walls, restricting dilation. This severe metabolic microvascular damage is precisely why diabetic men often develop severe, treatment-resistant ED much earlier than their healthy peers.
Stem cell therapy for diabetic erectile dysfunction specifically leverages the potent angiogenic properties of MSCs. By releasing VEGF and other vital growth factors, the therapy aims to meticulously rebuild those destroyed capillary networks from the ground up. Diabetic neuropathy research indicates that MSCs can partially reverse this profound endothelial dysfunction in controlled environments.
But there’s a serious catch. If your blood sugar remains poorly controlled post-treatment, you will simply destroy the new vascular tissue just as you destroyed the old. Strict glycemic control is a non-negotiable medical prerequisite for lasting success here. Conversely, physical surgical trauma requires a completely different mechanism of healing.
Radical prostatectomy procedures save countless lives, but they frequently leave men dealing with profound, life-altering sexual dysfunction. This devastating outcome occurs due to Cavernous Nerve Injury (CNI) the incredibly delicate nerve bundles running directly alongside the prostate are stretched, bruised, or inadvertently severed during the tumor extraction surgery.
When utilizing stem cell therapy for erectile dysfunction of cavernous nerve injury, the biological focus shifts entirely. We aren’t just trying to build simple blood vessels; the clinical priority is aggressive neurogenesis and targeted neuroprotection. The injected MSCs secrete brain-derived neurotrophic factor (BDNF) and glial cell line-derived neurotrophic factor (GDNF).
These proteins are biological heavy-lifters. BDNF directly stimulates the survival of existing neurons and encourages the sprouting of new nerve axons across the surgical lesion. Meanwhile, GDNF works synergistically to protect the delicate myelin sheaths surrounding these nerve pathways.
Current cavernous nerve regeneration studies in human trials definitively show that if the critical nerves were spared (meaning not completely severed by the surgeon’s scalpel), MSCs can significantly accelerate the localized recovery timeline, helping men regain vital function months faster than natural healing alone.
Peyronie’s disease is an entirely different structural beast. It is strictly characterized by dense, fibrous scar tissue (plaque) forming inside the tunica albuginea of the penis. This tough collagen buildup causes highly painful curvature, loss of length, and severe structural deformity during a rigid erection.
The theoretical, developing application of stem cells for Peyronie’s disease relies heavily on the documented anti-fibrotic nature of MSCs. In theory, introducing these advanced cells directly into the hardened plaque can modulate the localized immune response, highly upregulate collagenase (the enzymes that actively break down tough collagen), and gradually degrade the excessive scar tissue.
| 📌 If you’re interested in how MSCs shift the immune system from attack mode to repair mode, we have an interesting article that discusses mesenchymal stem cell therapy for immune modulation, which you can read via the internal link. |
However and this is a strict clinical caveat that cannot be ignored—the published data for Peyronie’s is highly investigational compared to general vascular ED. While early animal models are undeniably promising, large-scale human trials are still severely lacking. Men suffering with Peyronie’s should view MSCs as a highly experimental adjunct rather than a proven, primary medical intervention.
Monotherapy is rarely the standard operating procedure in advanced regenerative medicine. Combining PRP with stem cells actively accelerates tissue engraftment creating a superior synergistic environment for lasting penile rejuvenation. Modern male rejuvenation protocols frequently layer multiple treatments to maximize functional restoration and create an overwhelmingly synergistic healing environment.
Patients often view these modalities as competing options, but leading regenerative clinicians view them as highly complementary tools within a comprehensive protocol. By understanding how these distinct therapies interact at a cellular level, patients can make highly informed decisions regarding their financial and medical investments in these advanced treatments.
Men often wonder if stem cell therapy vs shockwave therapy for ED is a strict either/or decision. It fundamentally isn’t. Low-intensity extracorporeal shockwave therapy (Li-ESWT) specifically uses targeted acoustic waves to create highly controlled micro-trauma, safely triggering a natural healing cascade. MSCs, on the other hand, actively deliver a massive biological payload of progenitor cells.
Similarly, when evaluating Stem Cells vs PRP, you have to deeply understand the source material. PRP extracts concentrated growth factors directly from your own blood to signal localized healing. MSCs provide the actual cellular machinery and a vastly broader array of powerful cytokines.
Here is how these comparative regenerative modalities stack up clinically:
| Modality | Primary Mechanism | Source Material | Clinical Evidence Level |
| Shockwave (Li-ESWT) | Acoustic micro-trauma triggering angiogenesis | External medical device | High (Established guidelines) |
| PRP (P-Shot) | High-concentration growth factor signaling | Autologous (Patient’s blood) | Moderate (Mixed trial data) |
| MSC Therapy | Paracrine signaling, tissue remodeling, neurogenesis | Autologous or Allogeneic (UC-MSC) | Emerging (Strong trial data, investigational) |
Recent synergistic regenerative models confirm that combining these approaches often yields superior, longer-lasting functional results. To actively leverage these powerful synergistic effects, patients frequently travel to specialized international medical hubs.
For men who have entirely exhausted their local, conventional pill options, medical tourism has become a highly researched alternative. Vega clinic in Thailand has rapidly emerged as a specialized destination specifically offering advanced combinatorial Stem Cell + PRP + Growth Factor Therapy protocols.
The clinical rationale utilized at Vega involves strategically layering these distinct modalities. They utilize the immediate, highly concentrated signaling burst of PRP to prime the penile tissue, immediately followed by the sustained, long-term regenerative capacity of MSCs.
But pay close attention to this vital detail: a legitimate, safe consultation at Vega in Thailand involves rigorous, uncompromising medical screening. They require comprehensive blood panels, intricate hormonal assessments, and detailed vascular imaging before approving treatment. This isn’t a simple retail transaction. If any clinic anywhere guarantees treatment before thoroughly evaluating your lab work, walk away immediately.
| 📌 If you’re planning treatment in Thailand and want a practical checklist for choosing a safe clinic, we have an interesting article that discusses whether stem cell therapy is safe in Thailand, which you can read via the internal link. |
Regenerative medicine carries inherent medical uncertainties that must be rigorously evaluated prior to any financial commitment. Severe adverse events remain exceedingly rare in regulated cases highlighting the critical importance of utilizing verified cellular sources. No biological treatment offers a guaranteed success rate, and safety profiles depend entirely on strict laboratory standards and clinical administration protocols.
Patients must aggressively prioritize clinical transparency over flashy marketing promises when evaluating these advanced, highly technical interventions. Understanding exactly what can go wrong, and knowing when you are definitively not a candidate, is just as important as understanding the potential regenerative benefits.
The biggest pitfall in this unregulated industry is the promise of an absolute resolution. Let the data be clear: MSCs for ED are largely investigational. They absolutely do not guarantee recovery, and any clinic claiming a 100% success rate is actively lying to you.
Another massive risk involves the sourcing of the cells. Utilizing unverified, poorly cultured cell sources risks catastrophic immune rejection, severe bacterial infection, or theoretically, tumor formation. The laboratory processing the delicate cells must rigorously adhere to strict cGMP (Current Good Manufacturing Practice) guidelines. According to regulatory safety guidelines, patients must actively verify the precise provenance and viability testing of the biological cells being used.
Furthermore, this advanced therapy is definitively not for everyone. Men with active malignancies, untreated prostate cancer, or completely necrotic penile tissue are strictly contraindicated. The growth factors can theoretically promote tumor growth if cancer is currently present, making rigorous, physician-led pre-screening absolutely non-negotiable, as detailed in recent oncological safety parameters.
A good candidate is typically a man experiencing mild to moderate vascular or neurogenic ED who has not achieved satisfactory results with standard oral medications. Men with severe, irreversible tissue necrosis or active pelvic malignancies are automatically excluded for safety reasons.
Suitability definitively requires a comprehensive medical evaluation, including extensive blood work and advanced duplex imaging, to physically confirm that regenerative tissue repair is still biologically viable. If you are experiencing progressive functional decline despite aggressively optimizing your hormones and trying maximum-dose PDE5 inhibitors, it is time to formally submit your diagnostics to a regenerative specialist for review.
Current clinical data suggests the biological improvements from stem cell therapy for ED can generally last 6 to 12 months following treatment, according to clinical follow-up studies. However, this timeframe varies heavily based on the severity of the underlying condition and the patient’s lifestyle factors. For instance, men who strictly manage their diabetes or cardiovascular health typically see much more sustained, durable results over time. As natural aging continues, individual functional outcomes may eventually require periodic clinical reassessment and potential maintenance sessions.
When performed in a strictly regulated clinical setting using verified cell sources, mesenchymal stem cell therapy is generally considered safe with a remarkably low risk of severe adverse events. The most commonly reported side effects include mild, temporary pain or bruising directly at the localized injection site. Unregulated treatments do carry massive risks of infection, making specialist consultation mandatory.
Currently, stem cell therapy for erectile dysfunction is widely classified as an elective, investigational procedure by major healthcare providers. Because it lacks standard FDA approval for this specific application, traditional health insurance completely refuses to cover the costs associated with treatment. Patients must expect to pay out-of-pocket for these advanced regenerative protocols, which is a primary reason medical tourism to clinics like Vega in Thailand has surged. Financial planning should factor in both the initial treatment and potential future maintenance.
For men utterly unresponsive to traditional PDE5 inhibitors, mesenchymal stem cell therapy offers a structural approach to ED by promoting angiogenesis and critical nerve repair, according to reviews in Translational Andrology and Urology. The objective data clearly shows it can effectively elevate IIEF-5 scores by directly addressing the physical degradation of the underlying tissue. The absolute best approach combines objective clinical evaluation, verified cellular sources, and highly realistic functional expectations based entirely on your specific medical history.
The Vascular-Neural Repair Framework clearly demonstrates why aggressively targeting the biological root cause—rather than simply masking the devastating symptoms—represents the true future of urological care. By addressing endothelial and neuronal degradation simultaneously, patients finally have a scientifically plausible path toward restoring their natural function. We are rapidly moving past the frustrating era of artificially forcing blood into damaged vessels and confidently entering a phase of genuine cellular remodeling.
Do not base your vital health decisions on generalized internet information or aggressive, deceptive clinic marketing. Contact the specialized medical team at Vega in Thailand to formally submit your medical history, imaging, and extensive lab work for a rigorous, highly personalized suitability assessment regarding these advanced regenerative therapies.