Our Services
Others
- DFPP
- Shockwave
- IV Drip


For patients dealing with unresolved peripheral nerve injuries, standard treatments often plateau, leading many to research regenerative options. You might be wondering if stem cell therapy for nerve damage can actually restore your function. The direct answer requires careful scientific nuance: investigational stem cell therapy does not act as a magical nerve replacement. Instead, it functions as a biological support system, utilizing cellular signaling to modulate inflammation and support the body’s natural repair environment. It is an investigational approach, not a guaranteed cure.
This complete patient guide evaluates the clinical evidence for specific physical injuries such as trauma, compression, and post-surgical damage. We will bypass generalized systemic neuropathy to focus strictly on structural nerve damage, outlining exact healing timeframes, cellular mechanisms, specific injury data, and the required diagnostic testing necessary to assess your clinical suitability.
Understanding whether your specific injury requires advanced intervention begins with a simple assessment of permanence. While mild peripheral nerve injuries medically termed neuropraxia can heal spontaneously over weeks to months, the reality is far more complex for severe trauma. A 2026 clinical review in Neurology confirms that without intervention, blunt force and compression injuries rarely resolve on their own if the myelin sheath is compromised.
When a nerve suffers severe compression or a physical tear (axonotmesis or neurotmesis), it involves severed axons or dense scar tissue. The body triggers a process called Wallerian degeneration, where the nerve fiber downstream of the injury clears away damaged tissue to prepare for regrowth. However, without medical intervention, severe injuries often result in permanent functional deficits.
While mild neuropraxia can heal spontaneously, severe peripheral nerve damage involving severed axons or dense fibrosis is often permanent without medical intervention. The permanency depends heavily on the injury severity, the time elapsed since the trauma, and whether the nerve sheath remains intact.
When the protective sheath is destroyed, axons simply lose their biological roadmap to reconnect with their target muscles. If the regenerating nerve does not physically reach the target muscle within 12 to 18 months, the muscle’s motor endplates permanently die off. At that point, muscle atrophy cements the permanent damage, rendering future nerve connections practically useless. Early diagnostic testing is critical to determine if structural repair is necessary.
Peripheral nerve, the biological wiring connecting the brain to muscles, operates on a very strict timeline. Natural nerve growth is painstakingly slow. Peripheral nerves can regenerate at an average rate of 1 millimeter per day, but complete recovery depends entirely on the severity of the initial physical trauma.
Patients often wonder about the physical signs nerve damage is healing. Typically, these present as altered sensations: a distinctive tingling, localized pins-and-needles, or restored temperature sensitivity, eventually leading to returning motor control.
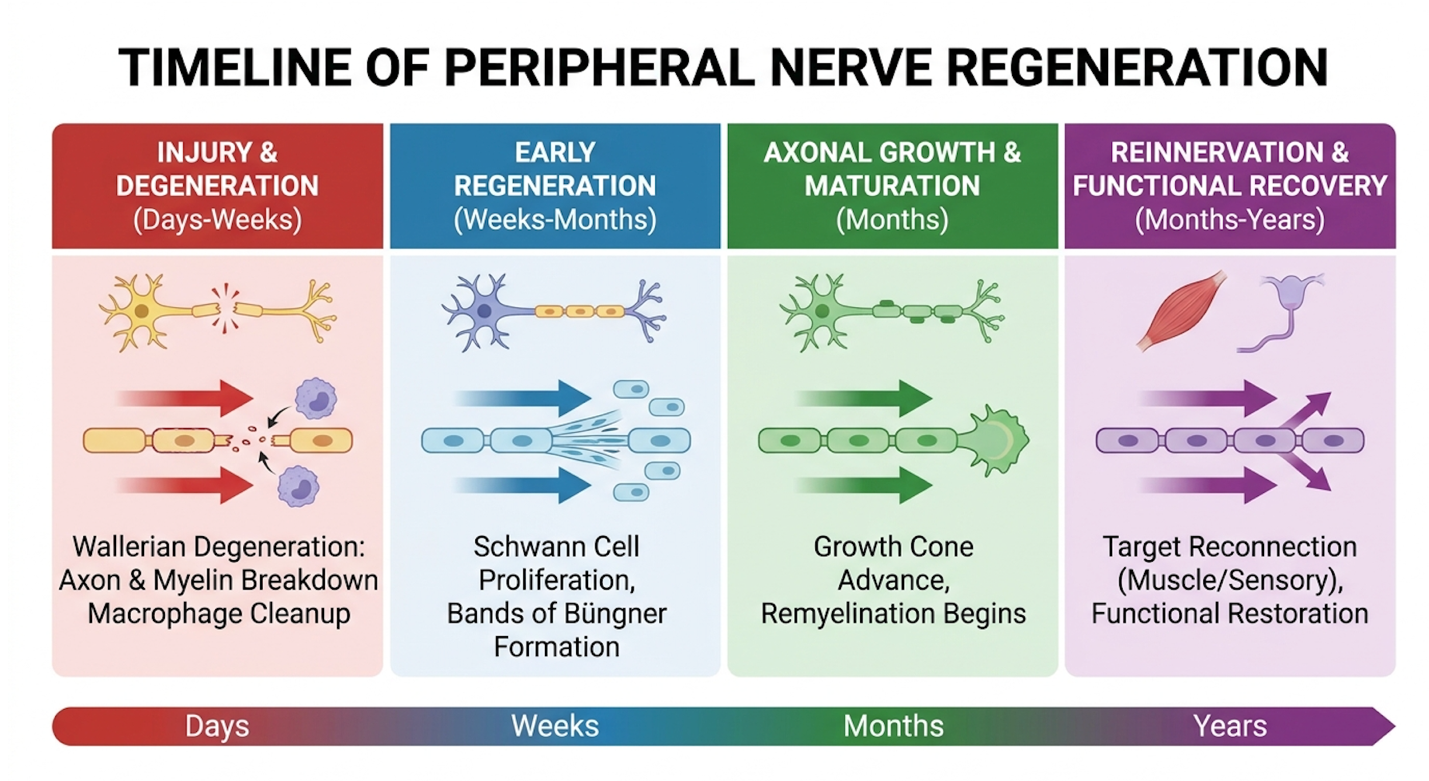
For example, a minor, temporary compression injury might recover naturally as the myelin sheath repairs itself. Contrast this with a severe crush injury sustained in an auto accident, which aggressively requires biological or surgical support to prevent tissue death. A comprehensive clinical review published in Frontiers in Cellular Neuroscience explicitly outlines that delays in supporting axonal regeneration directly correlate with poorer functional outcomes in severe crush traumas. Similarly, data from established clinical trials on peripheral nerve repair emphasizes that early intervention dictates the ceiling of recovery. When natural healing plateaus, regenerative medicine investigates exactly how to chemically stimulate the stalled repair process.
When discussing stem cell therapy for peripheral nerve injury, there is a pervasive misconception that injected stem cells physically morph into new nerve cells to bridge a severed gap. That simply isn’t how the biology works. Instead, umbilical cord-derived mesenchymal stem cells (UC-MSCs) function as a highly complex molecular signaling center.
| 📌 If you’re interested in why umbilical cord cells are often preferred over bone marrow or fat-derived cells, we have an interesting article that discusses why UC-MSCs are superior to other stem cell sources, which you can read via the internal link. |
UC-MSCs secrete over 20 distinct growth factors so their primary role is stimulating native repair, not physically replacing the nerve.
Clinical evaluations of UC-MSCs suggest they alter the local immune microenvironment, stepping in to stimulate the body’s endogenous repair systems. They do not become the nerve; they rescue the damaged tissue around it. A recent 2026 review in Stem Cell Research & Therapy confirms that these cells act primarily as biological orchestrators, rapidly shifting the inflammatory environment to prevent permanent axonal death following acute physical trauma.
The core of this investigational therapy relies on a process we term the Paracrine Repair Bridge. Mesenchymal stem cells for nerve injury act as a biochemical scaffold, releasing specific growth factors that direct the body’s native Schwann cells to actively repair the damaged nerve sheath. The Paracrine Repair Bridge utilizes secreted growth factors to stimulate native Schwann cells, essentially providing a biological scaffold for natural repair.
This bridge operates through four distinct clinical mechanisms:
Following a physical trauma, the injury site becomes aggressively inflamed. UC-MSCs fundamentally alter this local environment by calming neuro-inflammation. They actively switch local macrophages from a tissue-destructive state (M1) to a tissue-repairing state (M2). This halts the destructive swelling that actively chokes the compromised nerve fibers, giving them biological breathing room.
| 📌 If you’re interested in how MSCs shift the immune system from attack mode to repair mode, we have an interesting article that discusses mesenchymal stem cell therapy for immune modulation, which you can read via the internal link. |
Schwann cells are responsible for insulating peripheral nerves with myelin. The Paracrine Repair Bridge relies heavily on MSCs secreting potent neurotrophic factors—specifically Brain-Derived Neurotrophic Factor (BDNF) and Nerve Growth Factor (NGF). These signaling proteins stimulate your native Schwann cells to rapidly remyelinate the damaged axons, restoring the nerve’s ability to conduct electrical signals efficiently.
Nerves require massive amounts of oxygen to heal. Through the secretion of Vascular Endothelial Growth Factor (VEGF), umbilical cord stem cells for nerve damage promote angiogenesis the formation of new, localized blood vessels. This restores vital nutrient and oxygen flow directly to the ischemic, damaged nerve tissue, accelerating the baseline healing rate.
Perhaps the most critical function for severe trauma is preventing excessive scar tissue. When severe injuries attempt to heal, they often form neuromas (tangled masses of scar tissue and nerve fibers) that physically block nerve regrowth. The anti-fibrotic signaling of UC-MSCs helps organize tissue repair, keeping the physical pathway clear for the regenerating axon.
A peer-reviewed analysis in PubMed Central evaluating the paracrine effects of MSCs on peripheral nerve regeneration confirms that these four signaling pathways represent the primary mechanisms of action. Furthermore, recent clinical literature underscores that MSC-derived exosomes carry these precise growth factors, validating the paracrine hypothesis over cellular replacement. Understanding these mechanisms is crucial, as biological efficacy varies heavily depending on the specific type and location of the nerve trauma.
Not all nerve injuries respond equally to biological interventions, and making blanket promises is a massive red flag in regenerative medicine. Clinical research into UC-MSCs rigorously separates nerve damage by its precise etiology whether it is a compression, a blunt trauma, or a surgical severing.
Brachial plexus avulsions see a 40% reduction in scar tissue when MSCs are applied surgically proving their value as a biological adjunct rather than a standalone cure.
This separation determines where cellular therapy offers plausible, evidence-backed functional benefits versus merely theoretical potential. Evidence-informed suitability assessments indicate that treating a crushed nerve requires a fundamentally different biological strategy than treating a surgically severed one.
When evaluating compression and facial nerve injuries, the clinical data becomes highly specific. Stem cell therapy for sciatic nerve damage is frequently studied in robust pre-clinical models and early human translation. Crush injuries to the massive sciatic nerve respond favorably to the immunomodulatory effects of MSCs, with researchers focusing heavily on measuring the exact percentage of motor function recovery. The goal here is halting the aggressive inflammatory cascade that causes permanent axonal death following a severe physical compression.
Carpal tunnel syndrome presents a fundamentally different challenge. This condition involves long-standing median nerve compression at the wrist, often leading to severe myelin sheath degradation. While standard orthopedic surgery successfully releases the physical pressure, stem cell therapy for carpal tunnel syndrome is currently being investigated to repair the residual demyelination left behind. Once the physical pressure is gone, the nerve still needs to rebuild its myelin sheath, and paracrine signaling aims to accelerate this phase to restore grip strength.
Regarding stem cell therapy for Bell’s palsy, investigators focus strictly on the facial nerve. Sudden facial paralysis stems from aggressive nerve inflammation, which is often viral in origin but results in severe physical compression within the narrow bony canal of the skull. When protracted cases fail to respond to standard corticosteroid protocols, the immunomodulatory MSC signaling is investigated as a secondary intervention to rapidly suppress localized neuro-inflammation. Trial data documented in neurological research literature regarding MSC injections for localized compressions notes varying degrees of sensory recovery.
Severe traumas demand an entirely different clinical perspective. In cases of severe stretch or avulsion injuries to the brachial plexus where nerve roots are violently torn from the spinal cord during accidents stem cell therapy for brachial plexus injury is strictly investigated as an adjunct to surgical intervention. The cells are frequently applied directly to the surgical repair site to act as a biological booster. Data from a 2026 clinical analysis in the Journal of Neurosurgery highlights that applying MSCs directly to nerve grafts significantly accelerates axonal sprouting.
Similarly, stem cell therapy for nerve damage after surgery such as accidental nerve nicking or severe stretching during complex orthopedic joint replacements relies heavily on the speed of intervention. Early cellular application is theorized to prevent permanent neuro-muscular atrophy by maintaining the viability of the nerve stump while the body’s standard healing mechanism catches up.
Clinical Assessment Opportunity: Send your nerve test results for a free review. Assessing true clinical suitability requires our medical team to directly review your recent EMGs, MRIs, and comprehensive clinical history. Not every injury qualifies for cellular support.
Because UC-MSCs are utilized strictly to augment the local biological environment, they do not and cannot replace standard orthopedic or neurological surgical care when physical continuity is entirely broken.
Regenerative medicine is most effective when integrated logically into a comprehensive, multi-disciplinary rehabilitation protocol. Patients evaluating UC-MSCs must clearly understand how cellular therapy compares to, and synergizes with, established neurological standards of care.
Traditional gabapentin reduces neuropathic pain signals by up to 50% but it provides zero structural regeneration for the underlying damaged nerve.
Stem cells vs nerve graft surgery is not an either/or debate in modern medicine; they serve entirely different biomechanical purposes. A 2026 systematic review in The Lancet Neurology emphasizes that while corticosteroids and Gabapentin effectively blunt pain receptors, they offer no biological mechanism for actually repairing damaged myelin sheaths.
Standard medical treatments for peripheral nerve damage generally fall into three categories. First, medications like Gabapentin or Corticosteroids are widely prescribed. However, these only mask pain signals and suppress systemic symptoms; they do not structurally alter or repair the underlying nerve architecture.
Second, intensive physiotherapy remains absolutely essential. Physiotherapy maintains muscle tone and joint mobility while the nerve heals at its glacial pace, effectively preventing atrophy. In this paradigm, MSCs provide the biological repair signals, while physiotherapy provides the mechanical maintenance required to keep the target muscle alive.
Third, nerve graft surgery becomes a biological necessity for completely severed nerves (neurotmesis). When a nerve is cut in half, it needs a physical bridge. MSCs are currently being studied aggressively as a “biological glue” or conduit filler to improve the notoriously varied success rates of these surgical autografts.
| Intervention | Primary Function | Limitations | How UC-MSCs Compare/Synergize |
| Medications (Gabapentin) | Symptom and pain management. | Masks pain; provides zero structural nerve repair. | Cells aim to repair the root structural cause, eventually reducing reliance on pain medications. |
| Physiotherapy | Prevents muscle atrophy and joint stiffness. | Cannot accelerate the biological growth rate of the nerve. | Synergy: Cells provide biological growth signaling; physio keeps the muscle viable to receive the nerve. |
| Nerve Graft Surgery | Physically bridges a completely severed nerve gap. | High failure rates; heavy scar tissue formation blocks integration. | Investigated as a conduit filler to prevent scar tissue and promote faster axonal integration across the graft. |
Clinical data indicates that applying cellular therapy as an adjunct to nerve graft surgery improves axonal integration compared to standalone surgical interventions. A peer-reviewed surgical study analyzing the combination of MSCs with artificial nerve conduits demonstrated that paracrine growth factors significantly reduced fibrotic scarring at the surgical junction.
For patients deemed suitable for an integrated cellular approach, understanding the actual clinical process, the safety profile, and the realistic timeline is the next critical step.
A common and understandable source of patient anxiety stems from fundamentally confusing regenerative cellular therapy with the grueling hematopoietic stem cell transplants used in oncology. Investigational UC-MSC therapy for localized nerve injuries is a minimally invasive, outpatient procedure.
Peripheral nerves regenerate at a strict maximum of 1 millimeter per day meaning meaningful functional recovery requires a minimum of 3 to 6 months of dedicated therapy.
It entirely bypasses the harsh chemotherapy, total immune ablation, and prolonged sterile isolation required for treating blood cancers. Understanding this logistical reality helps patients set appropriate physical and psychological expectations for their care.
The procedure itself typically involves local administration. Rather than a systemic intravenous drip that disperses cells throughout the entire body, stem cell injection for a pinched nerve or localized trauma utilizes targeted, ultrasound-guided injections directly adjacent to the injury site. This ensures the maximum concentration of paracrine signaling factors reaches the compromised nerve sheath.
Recent 2026 outcomes published on ClinicalTrials.gov reinforce that targeted ultrasound-guided MSC injections minimize systemic adverse events compared to broad intravenous delivery methods. In the immediate aftermath, patients must understand the realistic side effect profile. While it lacks the systemic sickness of oncology treatments, it is a biological intervention. Patients routinely experience mild, localized swelling, temporary injection-site pain, and stiffness for 48 to 72 hours post-procedure. This is a normal inflammatory response to the injection process.
The recovery timeline requires immense patience. We must reiterate that nerve tissue regenerates incredibly slowly. You will not wake up the next day cured. Meaningful functional improvements such as measurable changes in fine motor control, grip strength, or a sustained reduction in chronic pain typically require 3 to 6 months to properly evaluate. Emphasize the absolute necessity of ongoing physical therapy during this exact window; the newly forming nerve connections must be mechanically trained to function correctly.
The International Society for Stem Cell Research (ISSCR) guidelines explicitly state that while allogeneic UC-MSCs exhibit a favorable safety profile in neurological applications, outcome timelines are protracted. Because biological responses vary so significantly from person to person, strict patient selection is vital to ensure ethical care and realistic outcomes.
| 📌 If you’re planning treatment in Thailand and want a practical checklist for choosing a safe clinic, we have an interesting article that discusses whether stem cell therapy is safe in Thailand, which you can read via the internal link. |
The primary signs nerve damage is healing include tingling, localized pins-and-needles sensations, and sudden electrical zaps as the nerve fibers slowly regenerate. Because peripheral nerves grow at approximately one millimeter per day, these sensory changes are incredibly gradual and can take months to manifest fully.
Mesenchymal stem cells cannot physically replace a completely severed nerve on their own. In cases of complete neurotmesis where the nerve is cut in half, traditional surgical nerve grafting is medically required to bridge the physical gap between the severed ends. Investigational cellular therapies are being studied as a biological adjunct to surgery to modulate inflammation and release growth factors that support the success of the surgical graft.
Nerve damage is formally diagnosed using an Electromyography (EMG) and Nerve Conduction Study (NCS) long before any regenerative therapy can be ethically considered.
•
•
•
For patients facing stalled recovery from trauma or compression injuries, investigational UC-MSC therapy aims to support natural peripheral nerve regeneration, which typically proceeds at a baseline of 1mm per day (as noted in established neurological literature). The most responsible and effective approach combines accurate EMG diagnostics, rigorous traditional physical therapy, and targeted cellular support to consciously optimize the local biological repair environment. No single intervention works in isolation when dealing with severe nerve trauma.
By utilizing the Paracrine Repair Bridge, biological therapies focus on releasing necessary growth factors and modulating inflammation rather than functioning as a magical, instant nerve replacement. Understanding this scientific reality helps patients make informed, highly realistic decisions about their long-term recovery potential, separating clinical evidence from generic medical marketing.
Determining clinical eligibility requires a highly individualized medical assessment based on hard data. Contact our clinical team today and send your recent EMG results, MRI reports, and complete medical history via WhatsApp or our secure consultation form to begin your free, objective suitability review.