Our Services
Others
- DFPP
- Shockwave
- IV Drip

For patients navigating androgenetic alopecia, the gap between commercial marketing claims and peer-reviewed regenerative medicine is vast; true hair follicle regeneration relies on precise paracrine signaling, not “miracle” cell transformations. Clinical researchers reviewing hundreds of case studies frequently note a frustrating reality: relying on clinics that promise stem cells will somehow “create new hair follicles” out of thin air almost always leads to profound disappointment and wasted financial resources.
Stem cells don’t magically morph into hair. By the end of this evidence-informed guide, you’ll understand the exact biological mechanisms that reactivate dormant follicles, allowing you to make clinical decisions based on objective data rather than slick marketing. We’ll examine the dermal papilla’s crucial role in the growth cycle, compare stem cell efficacy directly against PRP and surgical transplants, and clarify FDA regulatory standards for autologous treatments. If you’re serious about salvaging your hair, you need to understand the science first.
Stem cell therapy for hair loss does not create new follicles; rather, it reactivates existing miniature structures. By delivering concentrated growth factors directly to the dermal papilla, stem cells interrupt the balding process and trigger the anagen (growth) phase. This evidence-informed approach distinguishes legitimate regenerative medicine from commercial pseudoscience. Understanding the cellular communication pathways requires abandoning the idea of cellular shape-shifting and focusing entirely on biological signaling.
Adipose-derived stem cells secrete specific paracrine factors that increase density by up to 29%, pushing follicles back into the active anagen phase.
It is entirely a game of biological signaling. If a clinic fails to mention the dermal papilla during your consultation, they likely don’t understand the underlying science at a fundamental level. Cellular rescue requires targeting the exact anatomical structures that govern human hair cycling.
Let’s strip away the complex biology for a second. Your hair operates on a continuous loop: anagen (active growth), catagen (transition), and telogen (resting/shedding). Androgenetic alopecia pattern baldness essentially hijacks this cycle. It dramatically shortens the anagen phase while extending the telogen phase. Over time, the hair shaft becomes thinner and shorter, a process known as follicle miniaturization.
The control center for all of this is the dermal papilla, a highly specialized cluster of fibroblasts at the base of the follicle. When these cells are suppressed by genetics or DHT (dihydrotestosterone), hair growth grinds to a halt. When DHT binds to androgen receptors in the dermal papilla, it triggers a cascade that prematurely ends the active growth cycle.
This brings us to a critical concept in regenerative medicine for hair: The Anagen-Induction Threshold. This is the precise concentration of paracrine growth factors required to switch a dormant dermal papilla from the resting phase back into active growth. According to research on follicular signaling pathways, crossing this biological tipping point requires an intense localized cellular intervention. If a treatment can’t deliver a dense enough molecular payload to cross this threshold, you won’t see results.
Yes, damaged or miniaturized hair follicles can absolutely be repaired, provided they are still structurally intact beneath the scalp. Conditions like androgenetic alopecia cause follicles to shrink and go dormant rather than dying completely right away. The follicular unit is a resilient organ, and miniaturization is a gradual decline, not an instant death sentence.
Regenerative therapies introduce concentrated growth factors that stimulate the dermal papilla, pushing the follicle back into the active growth phase. Studies clearly show substantial density increases when treating these dormant follicles early enough in the hair loss progression. However, if a follicle is entirely scarred and dead, it cannot be revived.
A common clinical question is how stem cells regrow hair if the balding areas already look bare in the mirror. The answer hinges entirely on whether the follicle is dormant or dead.
Stem cell therapy only works by rescuing dormant follicles. A dormant follicle is severely miniaturized and might only produce microscopic, colorless vellus hairs, but it is structurally intact. The dermal papilla is still physically there, waiting for a signal.
A dead follicle, conversely, has undergone complete fibrosis. It is scarred over, sealed, and devoid of cellular activity. The skin feels slick and smooth. If you inject stem cells into a dead zone, absolutely nothing happens. The anatomical structure simply doesn’t exist anymore. This harsh biological boundary is exactly why meticulous clinical suitability assessments are mandatory before proceeding with any regenerative treatment.
So, if they don’t turn into hair, what do these cells actually do? The secret lies in paracrine signaling. Think of it as a localized chemical broadcast system that overrides the body’s balding instructions.
Using adipose derived stem cells hair restoration protocols essentially floods the scalp with a molecular payload. When Umbilical Cord Mesenchymal Stem Cells (UC-MSCs) or autologous cells are injected, they act like biological factories. They begin secreting massive amounts of bioactive molecules, primarily Vascular Endothelial Growth Factor (VEGF) and Hepatocyte Growth Factor (HGF).
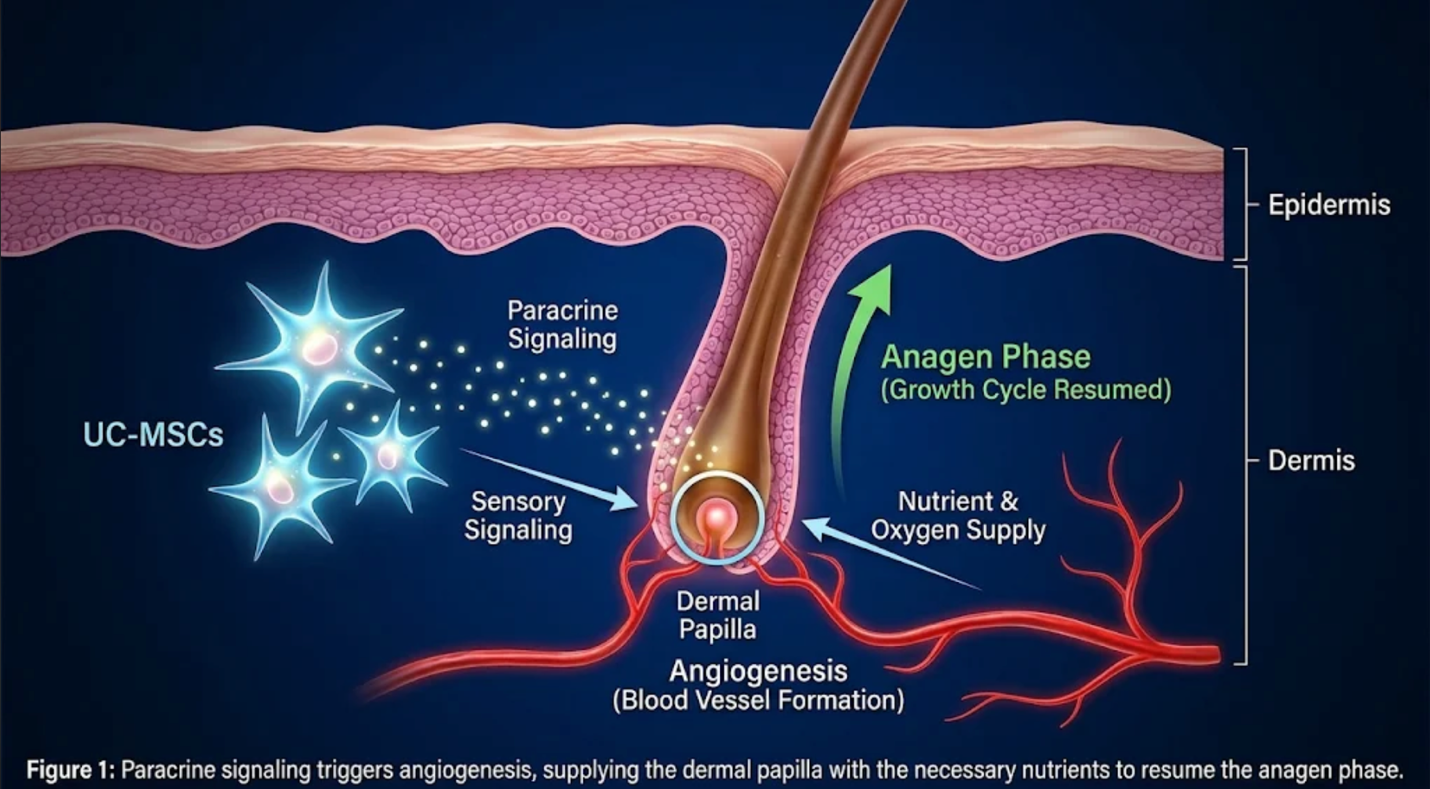
Figure 1: Paracrine signaling triggers angiogenesis, supplying the dermal papilla with the necessary nutrients to resume the anagen phase.
These specific growth factors that reverse follicle miniaturization trigger angiogenesis the formation of new blood vessels via the ERK MAPK signaling pathway. This influx of fresh blood circulation floods the dermal papilla with oxygen and nutrients, pushing the follicle over the Anagen-Induction Threshold. But where stem cell therapy excels at molecular reactivation, other clinical interventions take vastly different approaches to this exact same problem.
When evaluating stem cell vs prp for hair restoration, clinical data consistently favors stem cell interventions for severe follicle miniaturization. While PRP relies heavily on a patient’s existing baseline blood platelet quality, targeted cellular therapies provide vastly superior regenerative payloads. Understanding the physiological limits of each modality dictates long-term clinical success.
Stem cell therapy provides a 24% density increase compared to PRP’s 16%, offering superior reactivation for severely miniaturized follicles.
Unfortunately, many patients waste thousands of dollars on the wrong modality simply because they didn’t understand what these treatments actually do. Selecting the right intervention requires matching the treatment mechanism directly to the severity of your follicle degradation.
| 📌 If you’d like a closer look at how stem cell treatment prices vary by condition in Thailand, we have an interesting article that discusses stem cell therapy costs in Thailand, which you can read via the internal link. |
Patients frequently experience confusion about the exact difference between stem cells and Platelet-Rich Plasma (PRP) therapy. Both are injectables, both are regenerative, but they really aren’t in the same league.
PRP involves spinning your own blood to isolate platelets. The problem? PRP is entirely dependent on the patient’s age, systemic health, and baseline platelet count. If your body is already struggling with inflammation or advancing age, your PRP won’t be particularly potent.
Mesenchymal stem cells, particularly UC-MSCs, bring a vastly higher concentration of fresh, youthful growth factors independent of the patient’s aging biology. A pivotal study comparing stem cells to PRP demonstrated the clear superiority of the MSC approach.
| 📌 If you’re interested in why umbilical cord cells are often preferred over bone marrow or fat-derived cells, we have an interesting article that discusses why UC-MSCs are superior to other stem cell sources, which you can read via the internal link. |
To make the clinical trade-offs clear, here is how the best regenerative hair treatment options stack up against surgical intervention:
| Modality | Mechanism of Action | Clinical Efficacy (Density) | Downtime | Best For |
| UC-MSC Therapy | Paracrine growth factor secretion | ~24-29% increase | 48 hours | Severe thinning, diffuse loss |
| PRP Therapy | Autologous platelet activation | ~16% increase | 24 hours | Early-stage thinning, maintenance |
| FUE Transplant | Surgical follicle relocation | Permanent (relocated hair) | 7-14 days | Receded hairlines, dead follicles |
While injections can revitalize struggling follicles, completely barren scalp tissue requires a structural, surgical approach.
Let’s address the elephant in the room regarding stem cell therapy vs hair transplant surgery. If your scalp is slick bald and the follicles are entirely dead, no amount of liquid stem cells will regenerate that hair. That is the exclusive domain of Follicular Unit Extraction (FUE) transplants.
Transplants don’t grow new hair either; they simply harvest healthy, DHT-resistant follicles from the back of your head and surgically implant them into the dead zones.
Interestingly, these two treatments aren’t mutually exclusive. Recent clinical observations demonstrate that the most advanced surgeons now use stem cell therapy in conjunction with transplants. By injecting MSCs into the recipient site, they drastically improve overall graft survival rates and accelerate tissue healing. For those who do meet the clinical criteria for cellular reactivation, understanding the biological timeline of results is the next vital step.
Stem cell hair growth results are dictated by the natural biological cycles of the human body, not overnight miracles. Achieving the Anagen-Induction Threshold requires immense patience, as cellular repair works invisibly for weeks before surface results ever appear. The timeline is fixed by human biology.
Clinical data demonstrates a 29% density increase over 24 weeks, requiring significant patience as microscopic cellular repair precedes visible growth.
If a clinic tells you you’ll have a thick head of hair in four weeks, run the other way. Unrealistic timelines are the hallmark of predatory marketing in the regenerative aesthetic space.
Expectations must be grounded in statistical realities. The success rate of stem cell hair therapy is highly encouraging, but it requires accurate interpretation.
When we look at the data, clinical trial data demonstrating density increases tells us that while the treatment is remarkably effective, it isn’t an absolute reversal of baldness. Why? Because of The Anagen-Induction Threshold. Not every dormant follicle on your head is healthy enough to cross that threshold, even with a massive influx of growth factors.
Some follicles are just too far gone. This is exactly why density increases are measured in realistic percentages usually between 24% and 30% rather than total restoration. Understanding this statistical probability of success allows patients to map those expectations onto a physical, realistic timeline without getting discouraged.
The biological timeline for stem cell hair growth cannot be rushed. Hair only grows about half an inch per month under the absolute best circumstances. Here is the chronological progression you can actually expect:
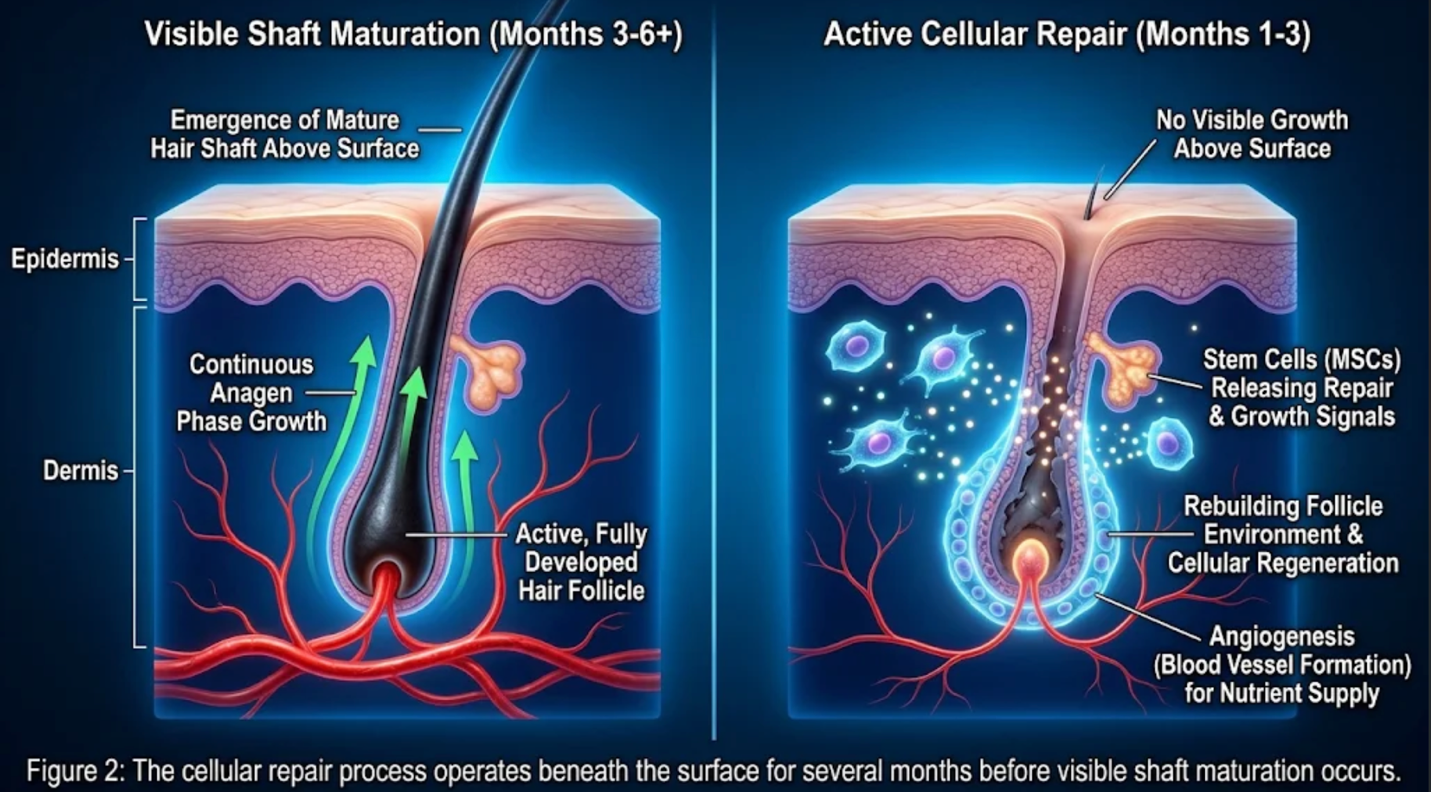
Figure 2: The cellular repair process operates beneath the surface for several months before visible shaft maturation occurs.
Before this biological timeline can even begin, patients must undergo the physical extraction and injection process in a highly controlled clinical setting.
When assessing if stem cell hair growth is safe, the primary factor is the sterile clinical extraction and processing of autologous tissues. Because the procedure often utilizes the patient’s own biological material (or stringently screened immune-privileged UC-MSCs), the risk of systemic rejection is effectively eliminated, making side effect mitigation highly predictable, with clinical trial data confirming high safety profiles and no serious adverse events across treated groups.
Autologous stem cell extractions demonstrate an incredibly high safety profile regarding immune rejection, with minor localized swelling typically resolving within 48 hours.
Despite the intimidating terminology, the actual patient experience is surprisingly straightforward. Many patients express shock at how quickly they are in and out of the clinic door.
The stem cell hair procedure steps are highly standardized in reputable clinics, beginning with meticulous preparation. When utilizing autologous adipose-derived cells, the clinician first selects a donor site usually the abdomen or flanks. According to standardized lipo-aspiration protocols, this minimally invasive harvesting technique maintains an exceptionally low complication rate when performed under sterile conditions.
The area is prepped and heavily numbed with a tumescent local anesthesia. This is a critical step because it ensures the actual extraction is virtually painless. You remain completely awake during this phase, able to converse with the medical team. The anxiety leading up to this moment is almost always worse than the procedure itself.
Once numb, the physician performs a mini-liposuction. It takes about 20 minutes to harvest the necessary 50-100cc of fat tissue.
Let’s talk about the reality of stem cell hair treatment side effects. Because the materials are autologous or highly processed UC-MSCs, severe systemic reactions are exceedingly rare. Your body recognizes its own cells.
You will likely experience mild, localized swelling and tenderness at both the abdominal extraction site and the scalp. Some patients report a feeling of “tightness” or a mild tension headache for the first 24 hours as the fluid disperses.
The recovery time for stem cell hair procedures is remarkably brief. You’re looking at a strict 48-hour window where you need to avoid strenuous cardiovascular exercise, keep direct sunlight off the scalp, and avoid any harsh chemical shampoos or styling products. You also need to sleep with your head slightly elevated to minimize swelling. After that initial two-day period, you can generally resume normal daily life. This clinical rigor directly influences how regulatory bodies classify these treatments and, subsequently, their cost.
Assessing clinical suitability is the absolute most critical step in regenerative medicine; failing to identify irreversible scarring will result in a total treatment failure. Before investing thousands of dollars, patients must navigate the common pitfalls of the aesthetic industry and recognize when alternative medical interventions are the only viable path forward.
Injecting regenerative cells into completely dead, scarred tissue yields a 100% failure rate, making pre-procedure microscopic trichoscopy assessments absolutely mandatory.
Clinical specialists cannot stress this enough: accurate diagnostics prevent expensive mistakes. The underlying cause of your follicle miniaturization determines whether regenerative medicine will be a breakthrough or a disappointment.
The biggest pitfall in this industry is treating the wrong patient. If a clinician agrees to inject stem cells into a completely slick bald area with dead follicles, they are committing you to failure. This is why understanding the biological limitations of regenerative medicine is vital to protecting your investment.
Another massive red flag? Trusting clinics that promise a “100% cure” or explicitly claim they can “create new follicles.” No current peer-reviewed science supports the de novo creation of hair follicles in humans. When faced with these claims, demand to see peer-reviewed evidence and ask for realistic, percentage-based density estimates. If they can’t provide them, walk away.
| 📌 If you’re planning treatment in Thailand and want a practical checklist for choosing a safe clinic, we have an interesting article that discusses whether stem cell therapy is safe in Thailand, which you can read via the internal link. |
No, completely dead and scarred hair follicles cannot be revived by any current non-surgical medical treatment. According to dermatological guidelines on scarring alopecias, once a follicle has undergone complete fibrosis (scarring) and the scalp appears entirely smooth, the biological structure ceases to exist.
Stem cell therapies and medications only work on miniaturized, dormant follicles that are still anatomically present beneath the skin. For areas with completely dead follicles, surgical hair transplantation is the only medical option.
You cannot accurately diagnose the microscopic status of your follicles in a bathroom mirror. Differentiating between a severely miniaturized, dormant follicle and a fibrotic, dead follicle requires high-magnification trichoscopy, a recognized diagnostic standard.
If you are experiencing rapid shedding, patchy hair loss, or suspect you might have a scarring alopecia rather than standard pattern baldness, you must seek professional evaluation. A thorough clinical assessment will accurately determine your ratio of dormant to dead follicles, ensuring you don’t waste time and money on a cellular therapy your scalp cannot biologically support.
Dermal papilla cells act as the biological control center for the hair follicle’s growth cycle. Located at the base of the hair follicle, these specialized mesenchymal cells send molecular signals that determine hair shaft thickness, growth duration, and follicle cycling. When affected by genetics or DHT, dermal papilla cells reduce their signaling, leading to progressive hair thinning. Delivering targeted growth factors to these cells is the primary mechanism of regenerative medicine.
You can force dormant hair follicles back into the anagen (growth) phase by applying concentrated paracrine growth factors directly to the scalp. This is clinically achieved through therapies like mesenchymal stem cell injections or Platelet-Rich Plasma (PRP) therapy. These biological treatments flood the dermal papilla with vascular endothelial growth factor (VEGF), triggering cellular repair and new blood vessel formation. A professional trichoscopy assessment is required to confirm if your specific follicles are viable for reactivation.
Stem cell hair therapy results are long-lasting, but they are not universally permanent. Because androgenetic alopecia is a progressive genetic condition, DHT will eventually begin to miniaturize the rescued follicles again over time. Most patients require maintenance treatments or adjunctive therapies like finasteride to sustain their density improvements over multiple years. Think of it as turning back the biological clock rather than freezing it forever.
Yes, stem cell therapy is often highly effective for female pattern hair loss. Unlike men who frequently develop slick bald spots with dead follicles, women typically experience diffuse thinning where the follicles remain dormant but structurally intact. This makes women exceptional candidates for cellular reactivation therapies. Studies show up to a 29% increase in density when treating dormant follicles, because women naturally possess a higher ratio of salvageable structures.
For individuals suffering from androgenetic alopecia, evidence-led hair follicle regeneration delivers measurable increases in hair density by rescuing dormant structures. Clinical data demonstrates significant improvement rates in patients when cellular therapies are applied correctly. The most effective clinical approach combines proper patient selection, targeted extraction of mesenchymal stem cells, and precision injection to maximize paracrine signaling and scalp blood circulation.
Success ultimately relies on surpassing The Anagen-Induction Threshold. By understanding that stem cells do not magically create new hair out of scarred tissue, but rather provide the specific molecular payload required to wake up resting dermal papilla cells, patients can set realistic clinical expectations and avoid predatory marketing.
The only way to determine if your hair loss is driven by salvageable dormant follicles or irreversible dead follicles is through a microscopic scalp evaluation. Schedule a free clinical hair assessment with a regenerative medicine specialist today to evaluate your unique scalp biology and determine if cellular therapy is appropriate for your condition.