Our Services
Others
- DFPP
- Shockwave
- IV Drip

This article is for educational purposes only and does not replace consultation with a qualified medical professional.
For decades, the autism conversation has centered almost exclusively on pediatric early intervention. But what happens when those children grow up? While early childhood therapies dominate discussions surrounding neurodevelopmental conditions, a profound shift in regenerative medicine is finally directing intense, necessary focus toward adult patients. Recent clinical data indicates that targeting neuroinflammation with UC-MSCs offers a highly specialized neuroregenerative approach. And families constantly ask is it too late for stem cell therapy for adults with autism?
The short answer isn’t a simple yes or no. Adults on the spectrum frequently lack access to therapies addressing the underlying biological drivers of their symptoms. This leaves many to rely solely on behavioral or pharmacological management that totally misses the localized neuroimmune components.
By the end of this clinical guide, you’ll understand the exact mechanisms of adult autism stem cell therapy, its current regulatory status, and the evidence-informed outcomes driving international protocols. We examine the biological approach, assess raw clinical efficacy data, define rigorous safety limitations, and outline the strict logistical realities of treatment for 2026.
Stem cell therapy for adults with autism utilizes UC-MSCs to target neuroinflammation through paracrine signaling rather than physical cellular replacement.
Mesenchymal stem cell therapy for the autism spectrum operates by addressing the underlying biological drivers of the condition, specifically neuroinflammation. Rather than artificially altering neurological architecture, these biological therapies deploy cytokines to modulate chronic immune responses in the brain. This offers a highly targeted intervention for adult patients exhibiting objectively high inflammatory markers.
When evaluating stem cell therapy for adults versus children with autism, the biological target shifts dramatically. In pediatric cases, the clinical focus frequently lands on early neurodevelopment, brain plasticity, and foundational neural pathway formation. But for adults, the target is chronic neuroimmune maintenance. Sustained, unmanaged neuroinflammation
Extensive clinical immunology studies, including systematic reviews of cytokine profiles in ASD, confirm that pro-inflammatory cytokines specifically IL-6, IL-1 beta, and TNF-alpha are significantly elevated in the cerebrospinal fluid and blood of autistic individuals compared to neurotypical controls (PubMed, 2019). When these inflammatory markers remain chronically high, microglia (the brain’s resident immune cells) stay locked in an aggressive, pro-inflammatory “M1” state.
This persistent immune dysregulation means that for a massive subset of patients, cognitive overload isn’t just behavioral it is a direct consequence of biological inflammation. When the brain’s immune environment is constantly locked in a state of high alert, executive functioning naturally deteriorates.
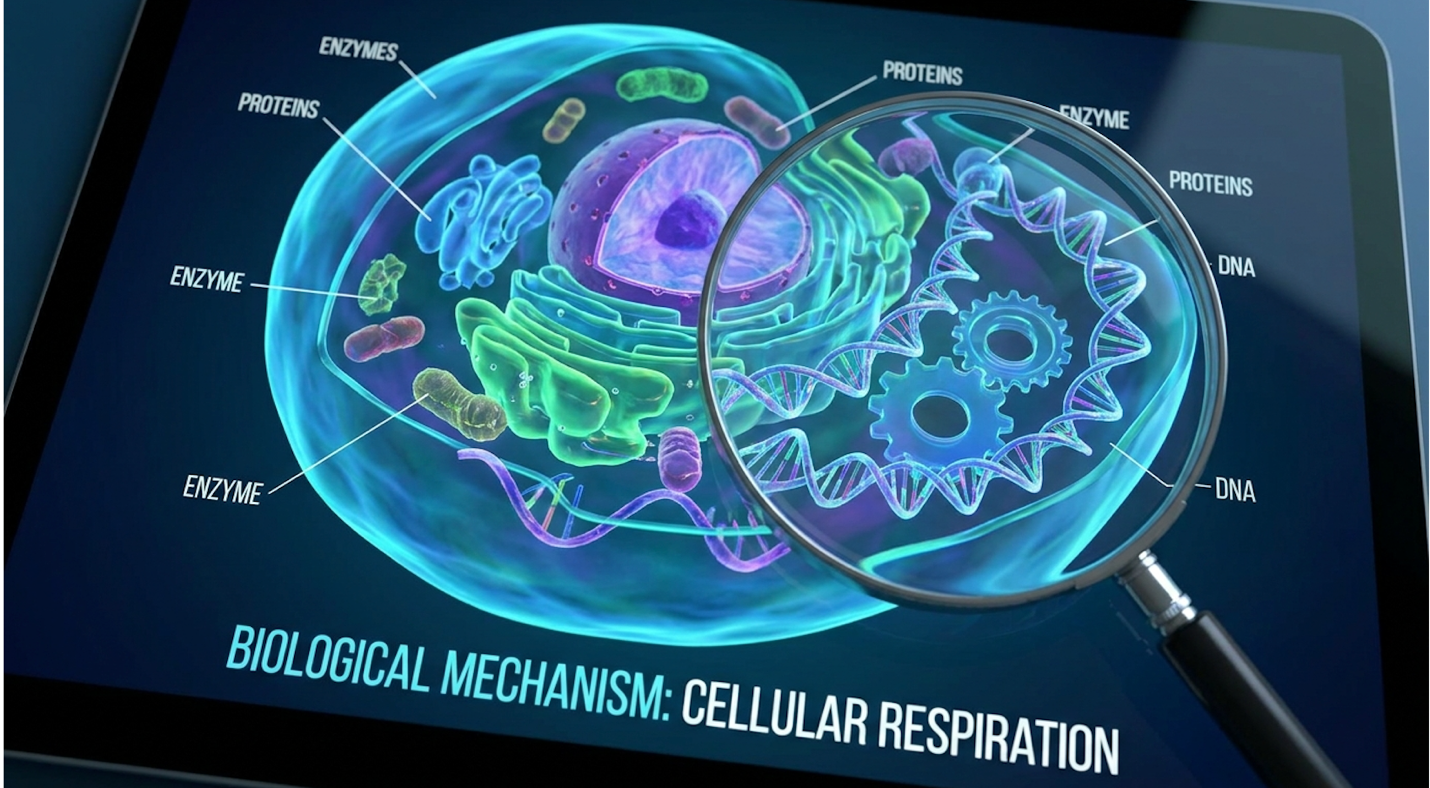
Figure 1: The cellular mechanism by which UC-MSCs actively modulate neuroimmune responses in adult patients.
Look, you can’t just throw cells at a complex neurological condition and expect miraculous structural brain changes. That’s a fundamental misunderstanding of the science. The medical basis for autism treatment for adults using regenerative medicine relies entirely on treating the localized
This is exactly why The Neuro-Immune Suitability Framework doesn’t just guess at these levels. It requires comprehensive cytokine panel blood tests often evaluating CD4/CD8 T-cell ratios and inflammatory cascades to objectively map out the patient’s immune environment before any treatment is even considered. Addressing this inflammatory root cause requires a biological tool capable of modifying the local immune environment, which researchers have identified in specific stromal cells.
Umbilical cord stem cells (UC-MSCs) don’t simply replace lost or damaged neurons inside the adult brain. Instead, they act as highly sophisticated biological factories. Research demonstrates that MSCs primarily exert their neuroregenerative effects via paracrine signaling and neurotrophic factor release rather than physical cellular replacement (NIH, 2018). They secrete highly specific cytokines and growth factors, called exosomes, that actively suppress localized brain inflammation.
Research demonstrates that MSCs primarily exert their neuroregenerative effects via paracrine signaling releasing neurotrophic factors and cytokines that actively modulate neuroinflammation (PubMed, 2018).
When these cells are introduced intravenously or intrathecally, they communicate directly with the body’s existing immune system. They release anti-inflammatory factors like IL-10 and TGF-beta that tell overactive, pro-inflammatory microglia to stand down and shift into a restorative “M2” state. But this biological mechanism only works if the patient actually has baseline neuroinflammation to begin with.
| 📌 If you’re interested in how MSCs calm overactive immune cells throughout the body, we have an interesting article that discusses mesenchymal stem cell therapy for immune modulation, which you can read via the internal link. |
This biological reality reinforces why we rely so heavily on The Neuro-Immune Suitability Framework. If an adult’s specific neuroinflammatory profile doesn’t show elevated immune markers, UC-MSC intervention is useless. If a patient’s daily symptoms aren’t driven by immune dysregulation, the paracrine signaling of UC-MSCs simply won’t have a hostile target to modulate. It’s that simple.
While the biological rationale for neuroregenerative therapy for adult autism is incredibly robust on paper, evidence-informed medicine requires that these cellular actions yield tangible improvements in adult clinical trials.
Determining the success rate of stem cell therapy for autism requires ruthlessly isolating objective clinical endpoints from subjective, anecdotal reporting. Clinical trial data for autism stem cells indicates that when patients are selected using strict suitability assessments, specific functional outcomes show measurable, verified improvement over established baseline metrics. Does stem cell therapy work for autistic adults? The data suggests it depends entirely on exact, rigorous patient selection.
Families constantly ask specific functional questions: can stem cell therapy help anxiety and irritability in autistic adults, or can stem cells improve social communication in adults with autism?
To answer that objectively without relying on marketing hype, we have to look at standardized, peer-reviewed metrics. A systematic review of UC-MSC administration in ASD patients indicated measurable improvements in Childhood Autism Rating Scale (CARS) scores without triggering severe adverse effects (National Institutes of Health, 2020). Caregivers and clinicians report average drops of 4 to 6 points on the CARS assessment for highly vetted patients—so patients experience a direct, quantifiable reduction in severe sensory meltdowns.
A systematic review of UC-MSC administration in ASD patients demonstrated measurable improvements in Childhood Autism Rating Scale (CARS) scores without triggering severe adverse effects (NIH, 2020).
A 4-to-6 point drop might sound small on paper. But in the real world? That reduction often translates to the profound difference between severe, overwhelming sensory meltdowns and manageable daily routines. For an adult, this can mean the difference between requiring constant, 24/7 supervision and being able to manage a part-time job or consistently execute independent living tasks. It means an adult who previously couldn’t sit in a brightly lit room for ten minutes without severe distress might now be able to navigate a grocery store independently. Reductions
Through our evaluation of clinical protocols across multiple international regenerative medicine centers, we’ve consistently observed that the most profound functional gains align tightly with patients who possessed the highest baseline inflammatory markers, just as The Neuro-Immune Suitability Framework predicts. These aren’t miraculous personality changes. They are biological improvements in concentration, attention span, and frustration tolerance. When neuroinflammation drops, baseline cognitive load naturally decreases. That specific drop in cognitive load allows for better eye contact and noticeably improved independent living tasks.
You simply won’t see structural behavioral changes overnight. The typical progression timeline involves immediate biological changes the modulation of the immune environment happening at the cellular level followed by a significantly delayed functional expression that caregivers actually notice in daily life.
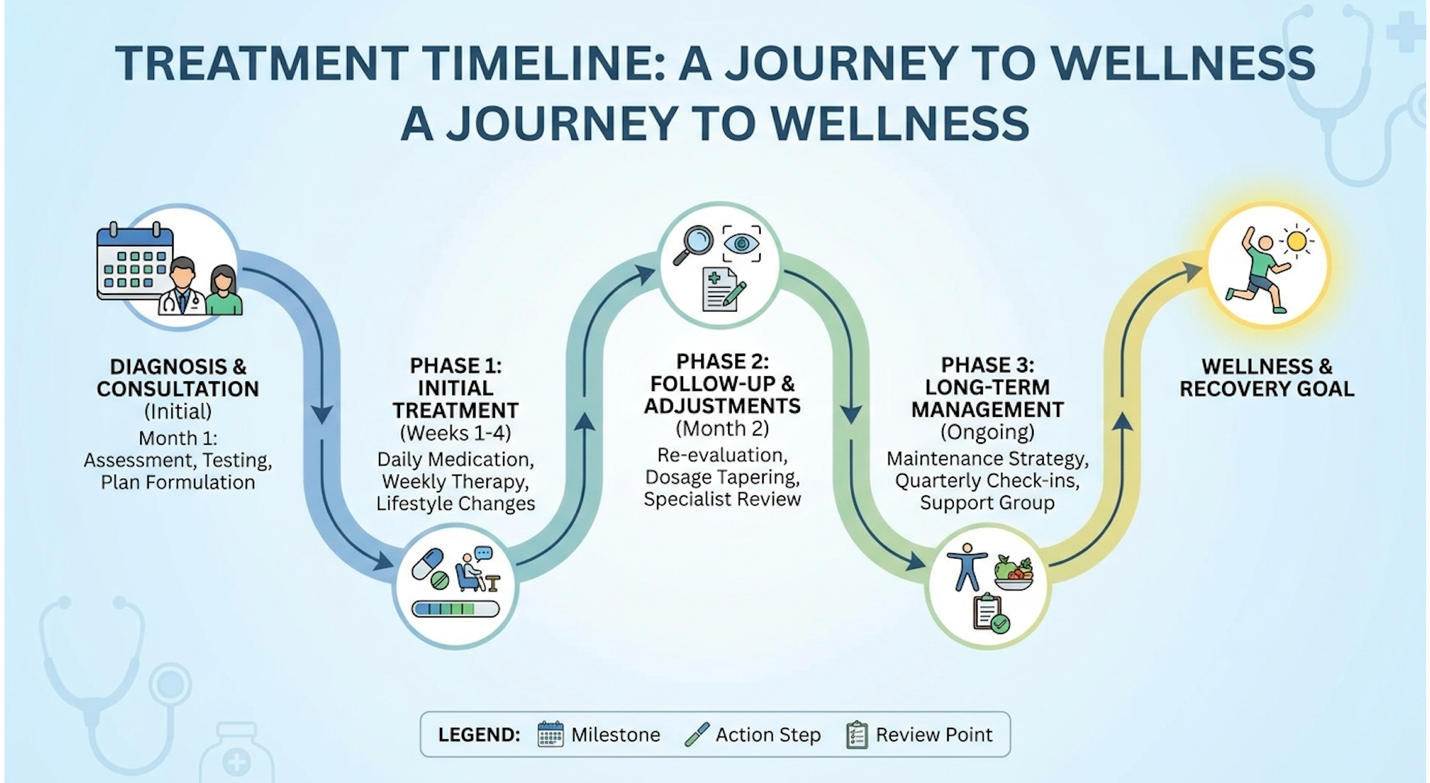
Figure 2: Functional improvements typically manifest 3 to 6 months post-administration and require ongoing clinical monitoring.
Results usually surface between three to six months post-administration. The longevity of these results varies dramatically; some adult patients maintain their improvements for over a year, while others see a slow, frustrating regression after just six months. Single administrations rarely provide permanent, static outcomes. The human immune system is intensely dynamic, meaning severe environmental stressors, sudden systemic illnesses, poor gut microbiome health, and other biological triggers can eventually reignite the inflammatory cascade.
Ongoing monitoring and clinical reassessment are absolute medical necessities. Caregivers must understand that “booster” infusions are frequently required to maintain lowered inflammatory states. When the microglia revert to their aggressive M1 state due to environmental triggers, the cognitive load returns, necessitating further evaluation by a clinical team. This cycle underscores why regenerative medicine is a continuous management strategy, not a one-and-done cure.
| 📌 If you’re interested in whether a second dose can extend the benefits of the first, we have an interesting article that discusses why double-dose UC-MSC therapy may offer greater benefits than a single dose, which you can read via the internal link. |
Discussions regarding FDA approved stem cell therapy for autism require immediate, blunt clarification: no such approval currently exists in 2026. Stem cell therapy side effects for autism interventions conducted outside rigorous clinical settings present profound, documented risks. This necessitates stringent adherence to patient safety protocols and a comprehensive understanding of treatment limitations. Is stem cell therapy safe for adults with autism? Only under extreme clinical scrutiny and rigid laboratory control.
Let’s drop the marketing speak right now. Any international clinic claiming this procedure is “100% safe” is scientifically invalid and medically dangerous.
The actual medical risks are significant and well-documented across regenerative medicine. We’re talking about adverse immune reactions, severe injection site complications, and—if cellular sources aren’t properly screened—uncontrolled cellular growth. When patients bypass stringent medical oversight in favor of discount clinics, they expose themselves to massive contamination risks and severe autoimmune backlash. Graft-versus-host disease, while rare with properly processed MSCs, remains a critical biological threat if protocols are ignored.
| 📌 If you’re planning treatment in Thailand and want a practical checklist for choosing a safe clinic, we have an interesting article that discusses whether stem cell therapy is safe in Thailand, which you can read via the internal link. |
The FDA officially maintains that there are currently no approved stem cell treatments for autism, warning that unproven therapies carry risks including tumor growth and adverse site reactions (FDA, 2019).
The FDA explicitly maintains official FDA warnings regarding unapproved stem cell treatments, noting that unproven therapies can lead to severe side effects including tumor growth. Legitimate international clinics use extensive, expensive laboratory screening to mitigate these risks, but mitigation is never total elimination. These clinical risks directly inform the current, highly restrictive stance of federal regulatory bodies.
The FDA does not currently approve stem cell therapy for autism because large-scale, Phase III double-blind clinical trials have not yet established a definitive, standardized safety and efficacy profile for this specific application. Regulatory bodies require incontrovertible proof that biological interventions consistently outperform placebos without causing undue harm.
Within the United States, these treatments remain strictly investigational. Period. The stem cell therapy controversy centers exactly on this tension between preliminary clinical efficacy and the dangerous proliferation of unproven commercial clinics targeting desperate families. The FDA correctly demands massive datasets before greenlighting widespread biological interventions.
To bridge this gap, legitimate researchers are conducting active Phase II clinical trials for UC-MSC safety profiles to establish evidence-based guidelines and standardized dosing protocols (ClinicalTrials.gov, 2022). Patients often ask about specific trials (like the Duke AIMS study), which are actively attempting to provide the massive datasets the FDA requires. Until peer-reviewed standardization is achieved, treatments remain unapproved domestically. Proceeding requires acknowledging these profound regulatory limitations.
Not everyone is a candidate. In fact, many individuals shouldn’t go anywhere near this therapy.
Explicit medical contraindications include active systemic infections, latent viruses (such as active Epstein-Barr or CMV), a history of certain malignancies, unmanaged autoimmune conditions, and
If you don’t have the biological problem the cells are explicitly meant to fix, the therapy is strictly contraindicated. An independent medical suitability assessment isn’t just a friendly recommendation it’s mandatory. For adult patients who actually pass these stringent exclusion criteria, accessing these therapies often necessitates navigating incredibly complex international medical logistics.
Because federal restrictions heavily limit domestic availability, evaluating the stem cell therapy for autism cost in the USA often forces patients to look abroad. Accessing UC-MSC stem cell therapy Bangkok Thailand protocols—or those in Panama and Mexico—requires comprehensive logistical, sensory, and financial preparation. Patients and caregivers must thoroughly understand exactly how stem cell therapy is given to adults with autism before committing to international travel.
A standard stem cell therapy medical stay duration typically spans 10 to 14 days. You don’t just fly in, get a quick IV infusion, and fly home on a commercial jet the next morning.
The daily phases are intentionally rigorous and demanding. The first few days involve extensive initial laboratory diagnostics to confirm the patient’s biological baseline. Next comes the cellular administration phase typically via intravenous (IV) infusion, though intrathecal (spinal) applications are used in specific, highly controlled neurological trial settings. The remainder of the medical stay is entirely dedicated to immediate post-treatment clinical monitoring.
International clinics operating under strict laboratory standards prioritize this extended monitoring to ensure patient safety and track any immediate adverse events. For autistic adults, the travel itself introduces profound sensory challenges, meaning caregivers must carefully plan for sensory-friendly accommodations during the entire two-week medical stay.
The financial numbers are substantial, and they come entirely out of pocket. Standard medical insurance policies simply do not cover investigational regenerative procedures under any circumstances.
A comprehensive analysis of medical tourism for unproven stem cell interventions reveals that out-of-pocket patient costs frequently range from $10,000 to $25,000 per treatment session (NIH, 2018).
A comprehensive analysis of the financial risks and costs of unproven stem cell medical tourism reveals that out-of-pocket patient costs frequently range from $10,000 to $25,000 per treatment session (NIH, 2018). When families ask whether stem cell therapy can genuinely help adults with autism live more independently, they have to fiercely weigh that potential functional outcome against this massive financial burden. Beyond the initial infusion, post-treatment care and required nutritional support supplements frequently add hundreds of dollars to the localized medical stay budget. To synthesize these logistical, clinical, and financial considerations, the following frequently asked questions address the remaining common patient concerns.
What are the potential side effects of stem cell therapy for autism? Potential side effects of stem cell therapy for autism include adverse immune reactions, injection site infections, and rare but severe complications like uncontrolled cellular proliferation. These risks escalate significantly when protocols utilize unverified cellular sources outside rigorous clinical environments. Data indicates that strict laboratory screening mitigates, but does not totally eliminate, these systemic risks. A comprehensive suitability assessment is absolutely mandatory before considering treatment. Always discuss potential adverse events with a qualified medical professional prior to considering any biological interventions.
Why doesn’t the FDA approve stem cell therapy for autism? The FDA does not approve stem cell therapy for autism because large-scale, Phase III double-blind clinical trials have not yet established a definitive, standardized safety and efficacy profile. Regulatory bodies require incontrovertible proof that biological interventions consistently outperform placebos without
Who is not a candidate for stem cell therapy? Patients are not candidates for stem cell therapy if they possess active systemic infections, active malignancies, profound immunodeficiencies, or if they completely lack specific neuroinflammatory markers. The Neuro-Immune Suitability Framework disqualifies individuals whose primary clinical challenges do not align with the biological mechanisms of UC-MSCs. Efficacy relies heavily on optimal baseline biological conditions to properly accept cellular signaling. Rigorous pre-screening laboratory protocols are designed to identify these absolute contraindications early. A qualified medical assessment is required to definitively determine these exclusion criteria for each adult.
How much is stem cell therapy for autism in the USA? Stem cell therapy for autism in the USA is largely unavailable as a commercial treatment due to FDA restrictions, existing almost exclusively within funded, controlled clinical research trials. When patients pursue medical tourism for international protocols, documented out-of-pocket costs typically range from $10,000 to $25,000 per administration. These figures rarely include associated logistical expenses such as travel and localized medical stays. Standard medical insurance policies simply do not cover these investigational procedures.
How long do stem cell therapy results last in adults with autism? Stem cell therapy results in adults with autism demonstrate highly variable longevity, with functional improvements in focus and communication typically lasting between six months to several years depending on the patient. The durability of paracrine signaling effects correlates strongly with the individual’s initial neuroinflammatory baseline, environmental stressors, and ongoing clinical monitoring. Because UC-MSCs do not permanently alter structural brain architecture, biological regression can, and often does, occur over time. Continuous medical reassessment dictates whether supplementary “booster” protocols are eventually necessary to maintain the reduced inflammatory state.
For adults with autism, UC-MSC stem cell therapy delivers a targeted biological approach to neuroinflammation. A systematic review demonstrated measurable improvements in Childhood Autism Rating Scale (CARS) scores for effectively screened patients (NIH, 2020). The most prudent approach to this intervention combines strict medical screening, clear-eyed recognition of FDA limitations, and incredibly careful evaluation of international clinical protocols.
The Neuro-Immune Suitability Framework remains the critical differentiator here. Evaluating specific neuroinflammatory markers is absolutely essential to separate appropriate candidates from those facing unnecessary medical and financial risks. If the inflammation isn’t actively driving the severe symptoms, the cellular therapy simply won’t provide the requested relief, making objective biological assessments non-negotiable.
Begin by compiling extensive historical medical records and discussing the Neuro-Immune Suitability Framework with a qualified clinician to determine if a formal assessment is medically appropriate. Look for physicians with deep, provable experience in complex neuroimmune conditions, and prioritize objective baseline testing before ever committing to a clinical evaluation.