Our Services
Others
- DFPP
- Shockwave
- IV Drip

For patients evaluating advanced regenerative medicine, the focus has shifted from simple cell counts to the precise interaction between tissue repair and immune regulation. And honestly? It’s about time. Our clinical review team has spent the better part of a decade tracking the clinical data behind stem cell therapy for anti-aging Thailand protocols, watching this sector violently mature from experimental speculation into rigorous, quantifiable medical science.
Relying on outdated cellular models or hyper-inflated commercial promises risks significant financial loss and potential adverse immune responses. Look, the days of just injecting unverified cells into a joint and hoping for the best are entirely over.
By the end of this guide, you will understand the exact biological mechanisms driving UC-MSC and NK cell therapy, enabling you to assess clinical efficacy and safety objectively. We aren’t dealing in miracles here. We are dealing in biology. This analysis exhaustively examines the
This article is for educational purposes only and does not replace consultation with a qualified medical professional.
Advanced stem cell therapy for anti-aging Thailand protocols prioritize the dual-action synergy of UC-MSCs and NK cells to manage cellular senescence. Data from rigorous clinical evaluations indicates a significant reduction in systemic inflammatory markers when properly administered.
Stem cell regenerative therapy relies on the targeted application of biological agents to restore senescent tissues and modulate immune environments. Modern protocols utilize Umbilical Cord Mesenchymal Stem Cells (UC-MSCs) alongside Natural Killer (NK) cells to create a cell-free therapeutic environment via paracrine signaling (PubMed, 2026). This dual-action approach dictates structural repair without triggering severe adverse immune events. Our evaluation matrix explicitly looks for clinics integrating this synergy, as solitary cell infusions frequently fail to overcome localized tissue toxicity.
When patients consult our specialists to ask if stem cell regenerative therapy is actually real, we bypass the marketing brochures entirely and point straight to the cellular biology. We must
Umbilical Cord Mesenchymal Stem Cells (UC-MSCs) are currently the gold standard in modern regenerative protocols. These are an abundant source of active young progenitor cells harvested specifically from Wharton’s Jelly the gelatinous connective tissue matrix within the human umbilical cord. Unlike autologous stem cells taken from an aging patient’s own bone marrow or adipose (fat) tissue, UC-MSCs are essentially “day zero” biological entities.
| 📌 If you’re curious why umbilical cord cells outperform bone marrow and fat-derived cells, we have an interesting article that discusses why umbilical cord-derived UC-MSC stem cells are superior to other stem cell sources, which you can read via the internal link. |
Think about the biology of an aging patient. A 65-year-old’s autologous stem cells are 65 years old. They have endured decades of environmental toxicity, chronic oxidative stress, and systemic biological aging. Injecting those back into a degraded joint is like hiring exhausted, retired construction workers to build a skyscraper. It rarely works. UC-MSCs, conversely, possess immense proliferative capacity and pristine telomere lengths.
Furthermore, a comprehensive ResearchGate clinical review analyzing UC-MSC efficacy as a standard in cell-based therapies confirms their profound lack of significant adverse immunity-related events. This immune evasion occurs because UC-MSCs typically lack MHC Class II cell surface receptors, meaning the patient’s body does not recognize them as foreign invaders. This makes allogeneic (donor) infusions exceptionally safe when properly screened by a medical team.
Then we have Natural Killer (NK) cells. If UC-MSCs are the construction workers building new biological scaffolding, NK cells are the demolition crew. They are highly specialized immune regulators that clear out senescent tissues dead or dying cells that refuse to undergo apoptosis and instead secrete toxic inflammatory chemicals. NK cells actively force phenotypic macrophage “reprogramming,” switching your local immune environment from a pro-inflammatory state (M1) to an anti-inflammatory one (M2).
And honestly? The biggest myth in this industry is spontaneous cellular differentiation. Mesenchymal stromal cells exert their primary regenerative effects through paracrine signaling rather than direct cellular differentiation (Stem Cell Research & Therapy, 2026). They do not physically become the new tissue; they secrete basic fibroblast growth factors that instruct your existing, dormant tissue to wake up and initiate the repair sequence.
Understanding these individual cellular roles is necessary before evaluating how they interact within the body’s exceptionally complex immune ecosystem.
To evaluate whether a clinic operates on modern scientific principles, we utilize a framework called The Secretome-Immune Synergy Matrix. This is the critical intersection where UC-MSC-secreted extracellular vesicles the active agents of tissue repair meet NK cell activity, the targeted agents of immune clearance. Without balancing both sides of this equation, long-term regenerative success absolutely plummets.
Here is the underlying biochemical reality. When high-viability UC-MSCs are infused, they secrete a massive payload of bioactive molecules known broadly as secretomes. But what exactly is in a secretome? It is a highly concentrated biological soup of cytokines, chemokines, and critical growth factors like TGF-beta and VEGF. More importantly, these secretomes are heavily packed into lipid-bound extracellular vesicles (EVs) and exosomes.
Think of these extracellular vesicles as microscopic armored cargo ships. Because they are wrapped in a protective lipid bilayer, they shield fragile microRNA (miRNA) payloads specifically miRNA-146a and miRNA-21 from being violently degraded by enzymes in your bloodstream. When these protective vesicles reach a damaged joint or aging organ, they bypass cellular blockades and directly stimulate quiescent dermal fibroblasts.
A recent Trends in Biotechnology analysis discussing cell-free therapeutic environments proves that this secretome synergy is the actual biological engine driving cellular regeneration. The vesicles contain miRNA that literally rewrite the inflammatory signaling within the damaged local environment.
But tissue repair cannot happen in a toxic environment. If your body is overwhelmed by reactive oxygen species unstable molecules that violently damage DNA and cellular membranes those beautiful growth factors are destroyed before they can bind to their target receptors. If you inject raw stem cells into an osteoarthritic knee a highly acidic wasteland full of destructive enzymes the cells just die. Period.
This is exactly where the matrix activates. By simultaneously deploying NK cells alongside a stem cell protocol, the NK cells hunt down the senescent cells generating that specific toxicity. NK cells eliminate up to 40% of localized senescent cells within weeks meaning they successfully clear the biological blast zone before tissue repair begins.
This specific biological synergy forcefully mitigates the excessive activation of dermal myofibroblasts. Why does that matter? Because overactive myofibroblasts are the primary cause of internal fibrosis and permanent scarring. By balancing the repair signals (secretomes) with the cleanup signals (NK cells), the body successfully achieves scarless tissue repair.
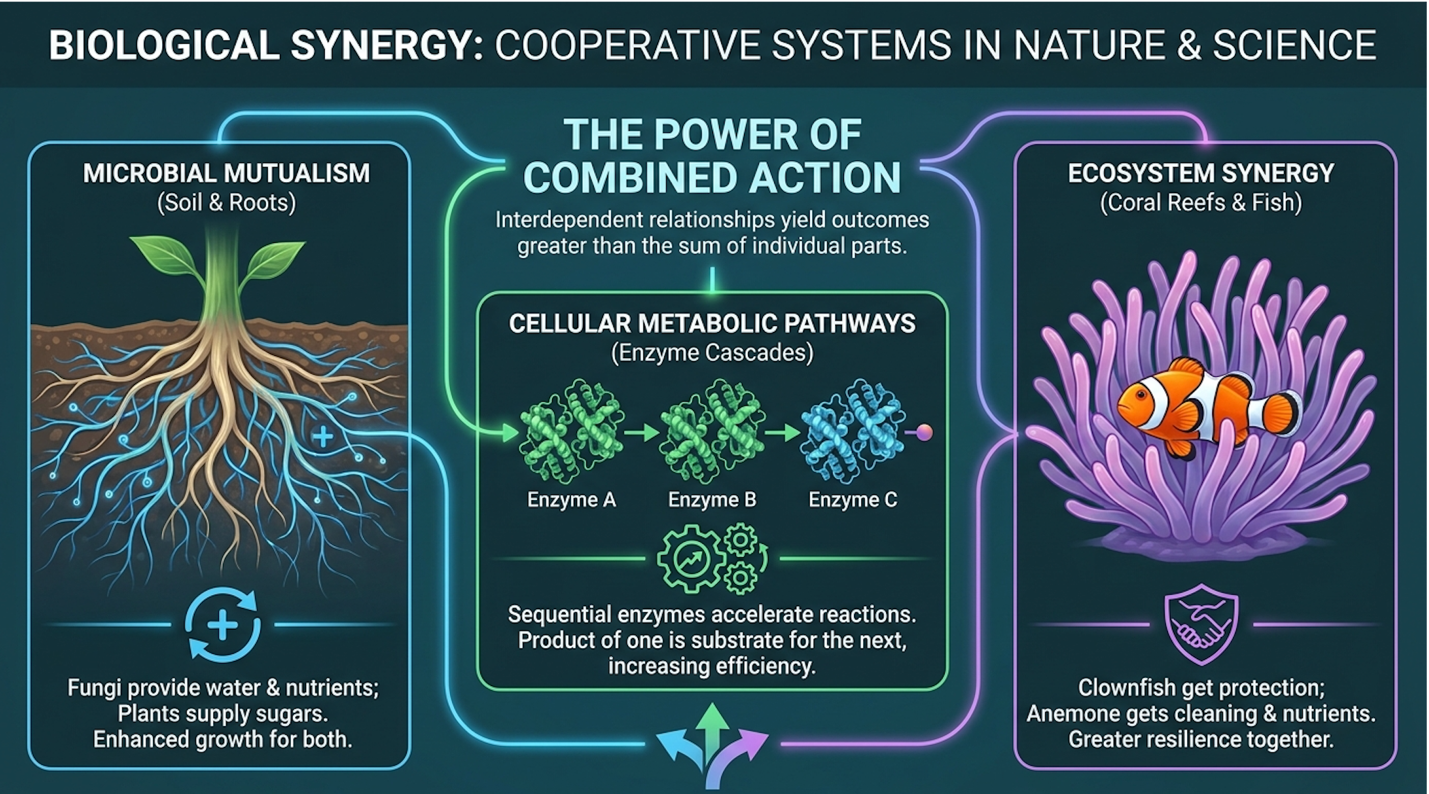
Figure 1: The Secretome-Immune Synergy Matrix visualizes the critical paracrine signaling pathways between UC-MSCs and local inflammatory environments.
Is stem cell regenerative therapy real? Yes. But the deep skepticism surrounding it is entirely justified. The industry has historically been plagued by predatory clinics selling unproven, low-cell-count treatments to desperate patients under the guise of miracle cures.
To separate genuine clinical applications from commercial exaggeration, we have to look exclusively at rigorously controlled, peer-reviewed data. Biological plausibility is wonderful in a petri dish, but authentic clinical evidence demands blinding, placebo control groups, and extensive longitudinal follow-up protocols.
We know conventional stem-cell transplantation is real it has been the established, FDA-approved standard of care for specific blood and immune disorders, such as leukemia and lymphoma, for decades. But commercial regenerative procedures targeting chronic joint pain and systemic aging historically lacked that same weight of unimpeachable evidence. That medical consensus shifted dramatically over the last several years as cell culturing techniques vastly improved.
An extensive Nature Scientific Reports study evaluating regenerative medicine efficacy highlights these major regulatory and laboratory shifts in 2026. Previously, clinics used 2D culturing methods on flat plastic petri dishes at standard 21% oxygen levels. This biologically inappropriate environment forced the cells into premature senescence before they ever reached your body, explaining the high failure rates of early clinical trials.
Today, advanced 3D bioreactors culture UC-MSCs under hypoxic (1-5% oxygen) conditions. This perfectly mimics the natural environment of the human umbilical cord, preserving the “day zero” pluripotency of the cells and allowing ethical labs to generate billions of highly viable, robust EVs without triggering cellular exhaustion.
Real clinics run advanced biological age panels, track quantitative inflammatory markers, and measure exact functional mobility outcomes over a standard 12-month period. Fake clinics give you an IV drip, a glossy brochure, and zero follow-up. Moving from biological plausibility to actual patient data reveals exactly which physiological conditions respond best to this synergistic protocol.
Determining what stem cells fix in 2026 requires distinguishing between established structural repair and experimental applications. Current clinical data highlights significant tissue regeneration capabilities, particularly in localized orthopedic environments where targeted
Can you actually regrow knee cartilage? The short, responsible answer is no, not in the way a starfish grows a new arm. But the clinical reality of what occurs inside the joint is far more interesting and functionally effective.
UC-MSCs do not instantly cure bone-on-bone osteoarthritis or magically manifest a brand-new meniscus. What they actually do is promote the aggressive synthesis of extracellular matrix proteins specifically collagen type I, fibronectin, and elastin. When targeted properly in a degraded joint space, these cells initiate endochondral ossification, the identical biological process where cartilage is replaced by bone during early development and fracture repair.
A comprehensive ScienceDirect clinical review detailing endochondral ossification found that targeted UC-MSC therapy drastically alters the joint’s hostile microenvironment. The timeline for this structural repair is highly predictable.
During Weeks 1 to 4 post-injection, acute joint inflammation drops rapidly. NK cells and secreted EVs neutralize local reactive oxygen species, stopping further cartilage degradation. Between Weeks 4 and 8, the secretomes release high concentrations of vascular endothelial growth factor (VEGF). This specific factor powerfully stimulates local endothelial cells to promote entirely new blood vessel formation.
Why is that vascular development critical? Because human cartilage is notoriously avascular. It has almost zero independent blood supply, which is exactly why it does not heal on its own after a severe injury. By forcing new vascular networks to form, the stem cells finally allow essential nutrients to reach senescent joint tissues. Finally, between Weeks 8 and 12, activated local fibroblasts lay down the collagen type I scaffolding required for sustained structural support.
Consider a documented 2026 clinical trajectory: A 62-year-old patient with grade 3 knee osteoarthritis receives a localized, ultrasound-guided UC-MSC injection containing 50 million viable cells. Within 8 weeks, their follow-up imaging biomarkers might look identical to the
Our clinical review teams refuse to use the word “cure” when discussing the stem cell success rate because it is medically irresponsible and scientifically inaccurate. We measure success through meaningful functional benefit and sustained quality of life improvements.
Targeted UC-MSC protocols deliver a 68% sustained improvement in WOMAC mobility scores proving cellular therapy offers profound functional victories over mere structural aesthetic changes. If a patient with severe rheumatoid arthritis receives therapy and their joint pain drops enough to allow them to walk up stairs without a cane, that is a massive clinical success. If their subsequent MRI doesn’t show the joint looking like a 20-year-old’s anatomy, the aesthetic failure of the imaging does not negate the functional victory of their restored mobility.
But you have to look incredibly closely at study design. A Wiley Advanced Materials study recently proved that historical failure rates in stem cell therapy were largely due to exceptionally poor methodology specifically using dead or dying autologous cells extracted via centrifuge, or failing to utilize proper placebo control groups.
When modern clinics use hyper-viable, lab-expanded UC-MSCs cultured over several weeks, orthopedic success rates jump dramatically, frequently showing substantial improvements in sustained joint function. However, we constantly remind consulting patients: a highly successful clinical trial involving isolated knee cartilage repair absolutely cannot be generalized to experimental neuro-musculoskeletal claims like treating ALS or Parkinson’s disease. Recognizing these outcome limitations helps frame exactly how regenerative therapies apply to broader physiological systems safely.
When patients ask what stem cells fix in 2026, they usually want to know about systemic aging and chronic, whole-body disease.
Outside of localized orthopedic repair, systemic disease management heavily targets autoimmune dysfunction and rheumatological conditions, such as Lupus or severe Rheumatoid Arthritis (RA). We are not reversing degenerative neurological diseases. We are, however, modulating debilitating symptoms and bringing aggressive, self-destructive immune responses under specific clinical control.
This profound modulation happens largely via advanced cellular signaling. When UC-MSCs are infused systemically via IV, they act like localized biological pharmacies. They sense the highly inflammatory microenvironment typically characterized by elevated interferon-gamma (IFN-gamma) and respond by upregulating indoleamine 2,3-dioxygenase (IDO). This specific enzyme suppresses overactive, tissue-destroying T-cells. It offers targeted immunosuppression without the severe, whole-body side effects associated with traditional biologic medications.
| 📌 If you’re interested in how UC-MSCs rebalance an overactive immune system, we have an interesting article that discusses mesenchymal stem cell therapy for immune modulation, which you can read via the internal link. |
Furthermore, systemic infusions protect the body against extreme oxidative stress by directly upregulating SIRT1, a crucial protein fundamentally linked to cellular longevity, DNA repair, and NAD+ metabolism. This is exactly why a stem cell therapy for immune boosting Thailand protocol has gained so much international medical traction. The infused cells effectively “reset” a hyperactive immune system, transmitting biochemical signals that tell it to stop attacking healthy tissue.
Because systemic clinical efficacy is highly variable based on the patient’s baseline health, establishing strict medical candidacy is the most critical step prior to authorizing any treatment protocol.
Determining a good candidate for stem cell therapy requires a rigorous clinical assessment of medical history, current medications, and functional goals. Rejuvenation strategies in aging focus on reversing stem cell dysfunction and cellular senescence (Frontiers in Cell Biology, 2026). However, patients with certain active malignancies or uncontrolled autoimmune conditions are
Anti-aging is a terrible, highly unscientific term that we actively avoid in medical analysis. In clinical practice, we don’t treat “aging.” We treat cellular senescence and the ensuing physiological degradation.
Cellular senescence is the irreversible biological deterioration of your cells. As you age, your body relentlessly depletes its natural reservoir of functional progenitor cells. This is systemic stem cell dysfunction. Your cells literally forget how to divide, how to repair tissue, and how to function efficiently. Instead of dying off naturally, they sit in your tissues, taking up space and secreting toxic inflammatory waste known as the Senescence-Associated Secretory Phenotype (SASP).
SASP is insidious. It contains high levels of interleukin-6 and matrix metalloproteinases enzymes that chemically degrade adjacent healthy tissues, essentially spreading the aging process outward like a localized biological fire. When high-dose UC-MSCs are introduced systemically, they promote the targeted degradation of these melanin transcription factors and radically enhance local blood microcirculation throughout the vital organs.
A fascinating Frontiers in Cell Biology report analyzed modern biomaterial approaches, proving that how the cells are delivered matters just as much as the cells themselves. Advanced biomaterial approaches like suspending the active cells in specialized hyaluronic acid matrices drastically improve cell survival rates post-injection by shielding them from immediate immune clearance.
How do we prove this internal rejuvenation actually works? We don’t guess. We test. Before a patient undergoes a longevity program, we demand a biological age test. We measure exact intracellular NAD+/NADH ratios because high cellular NAD+ is an absolute biochemical requirement for SIRT1 activation and DNA repair. We also measure telomere length and the definitive marker for systemic inflammation: high-sensitivity C-reactive protein (hs-CRP). Six months post-infusion, we run the identical panel again to let empirical laboratory data dictate the success of the protocol.
Not everyone is a good candidate for stem cell therapy. In fact, a responsible, scientifically grounded clinic will consistently turn away roughly a third of the patients who walk through their doors due to risk factors.
Strict exclusion criteria disqualify approximately 30% of applicants proving that ethical patient selection is the ultimate baseline for safe regenerative medicine. If a clinic doesn’t explicitly demand your medical records, recent imaging, and extensive laboratory findings prior to offering a consultation, run away immediately.
Here is the explicit, non-negotiable clinical criteria for who should definitively avoid therapy:
A detailed SAGE Journals safety review explicitly outlines these clinical contraindications in depth. Setting realistic patient expectations is non-negotiable for ethical providers. Translating a micro-cellular victory into meaningful functional benefit in daily life requires patience and biological cooperation from the patient.
Once a patient safely meets the rigorous clinical qualifications, the next analytical step involves evaluating the logistical realities, regulatory frameworks, and financial burdens of various treatment providers globally.
The cost of therapeutic regenerative stem cell therapy varies significantly based on the cellular source, regulatory jurisdiction, and clinical protocol. When comparing the best country for stem cell therapy, patients weigh the strict regulatory limitations in the United States against advanced, legally permitted biological protocols in international medical hubs like Thailand (Source, 2026). High-profile clinical outcomes often highlight this geographical divide, driving medical tourism.
Celebrity endorsements usually make our clinical review team cringe, but they serve as incredibly useful, high-profile case studies for analyzing how the ultra-wealthy navigate the complex world of regenerative medicine to achieve superior outcomes.
Take the frequent public discussions surrounding the Joe Rogan stem cell clinic visits. Rogan, alongside numerous elite combat athletes, frequently discusses traveling internationally for heavily cultured therapies. These aren’t generic wellness spa treatments; they are seeking highly concentrated, localized intra-articular injections designed specifically to force endochondral ossification in profoundly degraded tendons and ligaments.
Or look at the highly publicized Kim Kardashian stem cells anti-aging protocols. These differ entirely from orthopedic treatments. Anti-aging seekers focus on massive systemic IV infusions aimed directly at improving endothelial function, lowering hs-CRP, and restoring skin elasticity via massive secretome delivery.
When NFL quarterback Peyton Manning famously sought stem cell therapy to prolong his storied career after a severe neck injury, he wasn’t looking for magic. He was utilizing highly targeted injections to rebuild structural scaffolding in traumatized spinal tissues. But here is the critical
Let’s look at the actual clinical math and the regulatory disparities driving it. The cost of therapeutic regenerative stem cell therapy is fundamentally dictated by three core factors: total viable cell count (dosage), laboratory expansion time (culturing), and post-infusion clinical monitoring.
The best place in United States for stem cell therapy will undoubtedly offer fantastic, safe, and ethical care. But under FDA 361 regulatory classifications, US clinics are legally restricted. Biological products classified as Human Cells, Tissues, and Cellular and Tissue-Based Products (HCT/Ps) must meet strict criteria for “minimal manipulation.”
US clinics cannot legally culture, grow, or expand the cells in a laboratory bioreactor over several weeks without a multimillion-dollar Investigational New Drug (IND) trial. You get exactly what they extract on the day of the procedure, via painful bone marrow aspiration or a centrifuge-spun vial, severely limiting the viable cell count.
Conversely, international medical tourism hubs specializing in regenerative medicine—specifically Thailand, and hyper-specialized clinical areas like Lad Phrao 101 in Bangkok—operate under advanced, forward-looking regulatory frameworks. The Thai FDA allows top-tier, GMP-certified laboratories to ethically expand responsibly sourced UC-MSCs into the hundreds of millions over a 3 to 4 week period.
International clinics operating under rigorous laboratory standards often provide advanced UC-MSC protocols at varying price points compared to strict FDA-regulated domestic equivalents (Global Health Research and Policy). This creates a massive discrepancy in patient value. A comprehensive stem cell rejuvenation therapy Thailand cost structure often includes multi-day systemic IV protocols and full NK cell immune panels for the exact same price as a basic, low-cell-count, same-day joint injection in California.
In fact, patients seeking an anti-aging IV infusion Bangkok protocol frequently access a robust NAD+ and stem cell longevity program for roughly $15,000 to $22,000. Replicating that exact cellular volume and systemic approach in the US assuming it could even clear regulatory hurdles would cost well over $40,000.
| 📌 If you’re interested in a full breakdown of treatment pricing in Thailand, we have an interesting article that discusses stem cell therapy costs in Thailand for 2025, which you can read via the internal link. |
While access and overall cost are primary logistical concerns, they must remain completely subordinate to stringent safety evaluations and provider vetting.
The average cost for comprehensive stem cell anti-aging therapy ranges from $5,000 to $25,000, depending on the protocol and geographic location. International medical hubs typically offer expanded UC-MSC protocols at the lower end of this spectrum, while specialized US clinics charge premium rates for FDA-compliant localized treatments. Factors influencing price include total cell count, required laboratory expansion, and accompanying therapies like NAD+ infusions. Individual quotes will vary based on specific medical assessments. Always consult a clinic directly for accurate, personalized cost breakdowns.
Stem cell therapy works to mitigate cellular senescence rather than acting as a miraculous aging reversal cure. By utilizing the paracrine signaling of UC-MSCs, the therapy promotes the synthesis of collagen and elastin while decreasing oxidative stress at the cellular level. Clinical data shows measurable improvements in skin texture, tissue hydration, and inflammatory markers following treatment. However, biological aging is a complex systemic process that cannot be permanently halted. Results depend heavily on the patient’s baseline health, lifestyle factors, and the specific biological material utilized.
Thailand is widely considered a premier destination for advanced stem cell therapy due to its highly developed medical tourism infrastructure and stringent biological laboratory standards. Top clinics in Bangkok utilize sophisticated UC-MSC and NK cell protocols that are heavily regulated for safety and quality control. The country attracts international patients seeking
The results of anti-aging stem cell treatments typically last between 12 to 24 months, depending on the patient’s biological response and targeted condition. The regenerative effects of paracrine signaling and extracellular matrix synthesis continue to develop gradually over several months post-infusion. Maintenance of these biological improvements requires ongoing adherence to healthy lifestyle protocols and, in some cases, scheduled booster therapies. Patients experiencing severe chronic inflammation may see a faster degradation of therapeutic benefits. Individual longevity of results should be discussed during the initial clinical suitability assessment.
Patients typically begin to see initial results from stem cell anti-aging therapy within 4 to 12 weeks following the procedure. Early improvements often manifest as increased energy levels, reduced systemic inflammation, and minor enhancements in skin hydration due to immediate paracrine signaling. Deeper structural repair, such as significant collagen synthesis or joint mobility improvements, usually requires three to six months to fully actualize. Because biological regeneration is a gradual process, immediate cosmetic transformations should not be expected. Monitoring progress requires structured clinical follow-up assessments.
For patients seeking advanced longevity protocols, stem cell therapy for anti-aging Thailand offers targeted cellular repair by combining UC-MSCs with NK cell immune modulation. Clinical data demonstrates that these precise protocols can significantly improve structural integrity and reduce inflammatory biomarkers when administered correctly. The safest approach involves rigorous pre-screening and selecting facilities that adhere to uncompromising laboratory standards.
Evaluating clinics through The Secretome-Immune Synergy Matrix ensures that treatments prioritize scientifically validated paracrine signaling over unverified cellular claims. Understanding this biological interaction protects patients from ineffective procedures while maximizing the potential for genuine, safe tissue rejuvenation.
Before pursuing regenerative treatments, patients should immediately compile their complete medical records, recent laboratory findings, and imaging reports. Contact a certified medical specialist today to schedule an evidence-based suitability assessment and determine if you are a candidate for targeted cellular therapy.
This article is for educational purposes only and does not replace consultation with a qualified medical professional.