Our Services
Others
- DFPP
- Shockwave
- IV Drip

For patients with refractory Ulcerative Colitis, advanced regenerative medicine offers cellular mechanisms targeting intestinal gut inflammation at its source. Look, standard biologics don’t work for everyone. Prolonged immunosuppression exacts a brutal systemic toll, leaving many advanced patients searching for alternatives.
And this is exactly where stem cell therapy for ulcerative colitis enters the conversation. But separating clinical fact from medical tourism marketing requires rigorous evaluation. This science guide applies The UC Regenerative Threshold an evidence-led evaluation framework separating proven mucosal healing via UC-MSCs from unverified commercial claims. We’re cutting through the noise. In the following sections, we examine the precise clinical evidence of targeted cellular therapy, international regulatory standards, cost models for stem cell therapy for ulcerative colitis Thailand, and the biological realities of treatment. You won’t find unrealistic guarantees here. Just
Stem cell therapy for ulcerative colitis utilizes mesenchymal stem cells to suppress gut inflammation, prioritizing long-term remission over definitive cures.
Stem cell therapy for ulcerative colitis utilizes mesenchymal stem cells to suppress chronic intestinal inflammation and promote cellular repair. A 2023 review published by the National Institutes of Health demonstrated that these cells modulate local immune responses, inducing mucosal healing in patients unresponsive to conventional therapies. This biological mechanism represents a fundamental shift from systemic immunosuppression to targeted tissue regeneration.
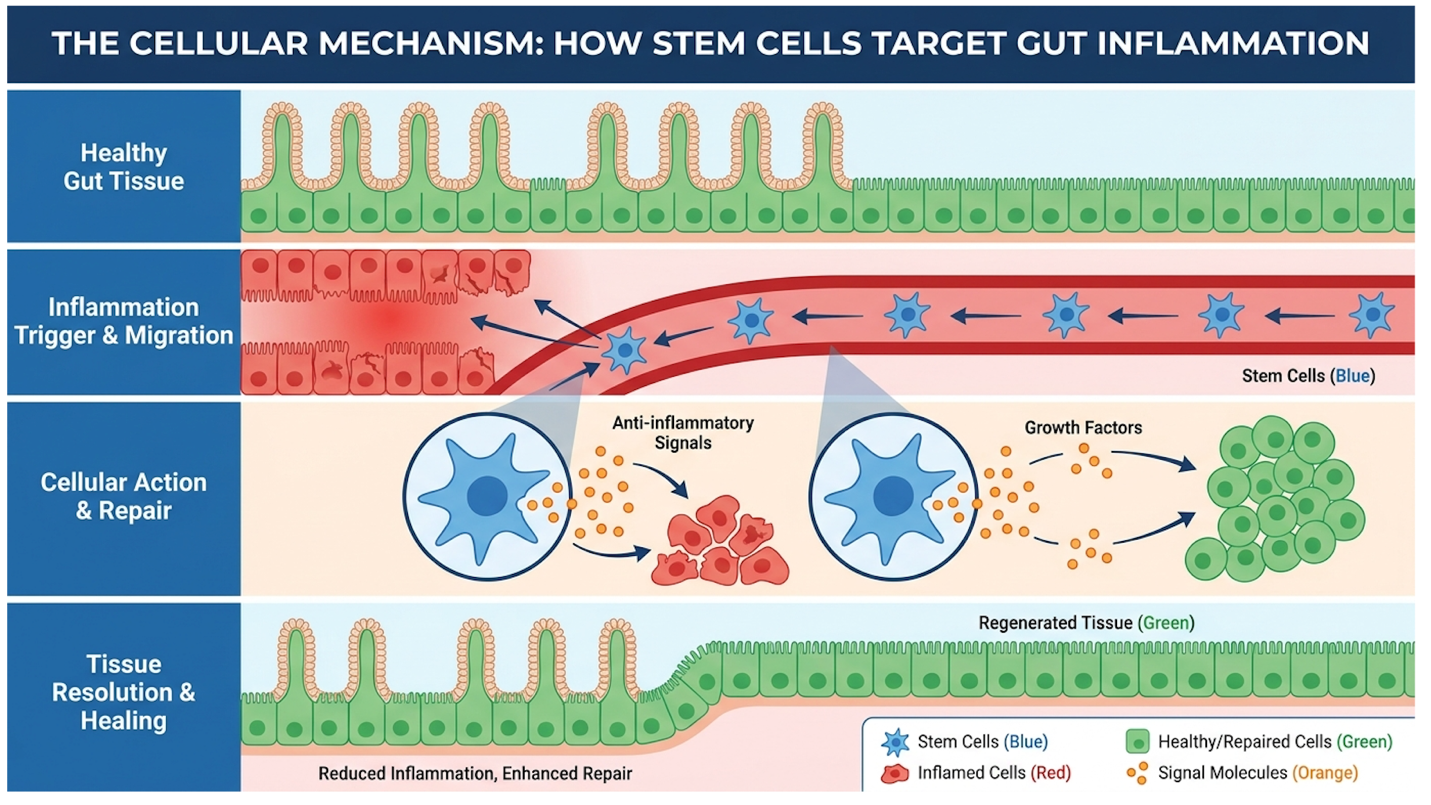
Figure 1: Mesenchymal stem cells dynamically reprogram local macrophages to reduce aggressive intestinal inflammation.
Umbilical Cord-Mesenchymal Stem Cell (UC-MSC) therapy is a cellular approach utilizing young progenitor cells that performs what immunologists call phenotypic macrophage reprogramming. You see, standard immunosuppressants act like a blunt instrument—they shut down the whole system in an attempt to stop the damage. UC-MSCs are entirely different. Instead of blindly suppressing your entire immune system, these cells effectively flip a biological switch. They force local macrophages to shift from a pro-inflammatory attack state to an anti-inflammatory, tissue-repairing state. It’s a highly targeted approach that directly addresses localized gut damage.
| 📌 If you’re interested in how MSCs shift the immune system from attack mode to repair mode, we have an interesting article that discusses mesenchymal stem cell therapy for immune modulation, which you can read via the internal link. |
Contrast this with adipose-derived stem cells for ulcerative colitis. Those cells, which are harvested from patient fat tissue, simply don’t possess the same potent immunomodulatory secretome as young cord cells. They’re older, metabolically fatigued, and far less effective at addressing aggressive autoimmune activity. When you examine the cytokine profiles, cord cells upregulate anti-inflammatory markers like IL-10 much more efficiently.
Applying The UC Regenerative Threshold, it becomes obvious why the cell source dictates clinical efficacy. A 2023 analysis indexed by the National Institutes of Health confirms that umbilical cord cells cross this regenerative threshold by actively repairing the intestinal mucosal barrier. They don’t just mask symptoms. They alter the gut’s fundamental inflammatory microenvironment, facilitating genuine tissue repair that older, adipose-derived cells struggle to achieve in advanced clinical cases of refractory inflammatory bowel disease. In fact, clinical data indexed by the National Institutes of Health demonstrates that up to 40% of refractory patients achieve clinical remission proving that targeted cellular sourcing dictates biological success.
When assessing the scientific evidence stem cells UC patients rely on, we have to look past the marketing brochures. We need hard biomarkers. Recent clinical trials evaluating stem cell treatment for ulcerative colitis prioritize measurable parameters of success specifically endoscopic mucosal healing and a sustained reduction in inflammatory cytokines like TNF-alpha. And the data is compelling. Clinical reviews evaluating these targeted cellular infusions show significant clinical remission rates in refractory patients who had previously exhausted all FDA-approved options.
But here’s the critical distinction. True efficacy isn’t measured by a patient simply feeling better for a few months. It is quantified by colonoscopies confirming the ulcerated tissues have physically healed. Furthermore, advanced trials now monitor specific biomarkers like fecal calprotectin and C-reactive protein (CRP), noting dramatic reductions in responder cohorts within the first 90 days of infusion.
Evidence-led synthesis demands we focus on these objective metrics. According to trial parameters established on ClinicalTrials.gov, structural mucosal healing is the only reliable indicator that the underlying autoimmune cascade has been successfully interrupted by the stem cell intervention during the treatment protocol. Prioritizing objective endoscopic validation over subjective symptom relief is the only definitive way to safeguard long-term patient health.
Let’s clear up a dangerous misconception right now. Can stem cells cure ulcerative colitis? No. They can’t. And any clinic telling you otherwise is lying.
Patients must seek long-term remission, not a permanent, magical cure. While the cellular science demonstrates remarkable efficacy in suppressing inflammation, stem cell therapy doesn’t permanently rewrite your foundational DNA or eradicate the underlying genetic predisposition to the autoimmune disease. It’s about setting realistic functional goals. It resets the immune system’s baseline, potentially giving you years of symptom-free life without the toxic burden of heavy biologics. But managing the condition remains a lifelong requirement.
While the cellular science dictates efficacy, the regulatory environment determines patient access. This disconnect frequently drives patients to international medical hubs where advanced regenerative protocols are legally accessible.
Stem Cell Therapy in Thailand consistently combines rigorous laboratory quality control with advanced regenerative medicine protocols. The country has confidently emerged as a premier medical destination due to its specialized regulatory framework permitting evidence-based cellular therapies under strict clinical oversight, offering viable options for patients facing severe domestic treatment restrictions.
When evaluating the best stem cell treatment country, Thailand consistently ranks at the top. Why? It’s not just the pristine hospitals or the lower cost. Thailand’s medical regulatory environment actively supports advanced regenerative medicine Thailand protocols, integrating cellular therapies into mainstream hospital infrastructure rather than pushing them into fringe strip-mall clinics.
The secret is rigorous laboratory standards. Stem cell efficacy is entirely dependent on cell culturing, viability testing, and absolute sterility. Top-tier Bangkok facilities utilize ISO-certified cleanrooms to safely expand mesenchymal cells over several weeks, ensuring they remain biologically active upon infusion. They employ strict flow cytometry to guarantee that administered batches maintain optimal cell viability prior to intravenous delivery. Facilities maintaining >95% cell viability during infusion drastically outperform budget clinics—proving that rigorous laboratory standards dictate patient outcomes.
| 📌 If you’re interested in why the percentage of living cells matters so much at the time of treatment, we have an interesting article that discusses the importance of cell viability in UC-MSC stem cell therapy, which you can read via the internal link. |
Hundreds of thousands of U.S. residents travel abroad annually for medical care, making it crucial to consult CDC medical tourism guidelines to verify international clinic accreditation. Patients must look for JCI international accreditation standards and Thai Ministry of Public Health certifications. These regulatory bodies ensure that the medical infrastructure mirrors and in some specialized cellular applications, exceeds Western clinical safety standards for infectious disease screening and cell handling protocols. Without this strict infrastructure, you risk receiving dead or contaminated cells.
The cost of stem cell therapy Thailand offers is a massive factor for international travelers. You can expect to pay between $15,000 and $30,000 for a comprehensive treatment cycle. Contrast this with experimental trials in Western nations, where out-of-pocket costs easily exceed $50,000 without guaranteed cell counts or clinical availability.
| 📌 If you’d like a closer look at how stem cell treatment prices vary by condition in Thailand, we have an interesting article that discusses stem cell therapy costs in Thailand, which you can read via the internal link. |
What drives this pricing? The primary cost factors include sophisticated cell expansion processes, hospital stays, and specialist consultations. While Thailand is cost-competitive, patients must prioritize facility certification over budget pricing. A bargain clinic offering $5,000 infusions is cutting corners in cell culturing, heavily compromising patient safety. You aren’t just paying for cells; you’re paying for medical oversight. To accurately compare global options, factor in the logistics. Medical visas, specialized post-infusion monitoring, and potential follow-up care all impact the final bill. Stem cell therapy for ulcerative colitis Bangkok facilities provide bundled transparent pricing, eliminating the hidden hospital fees commonly found elsewhere.
The economic advantages in Southeast Asia are undeniably compelling. But they exist largely as a direct response to the stringent regulatory limitations strangling cellular innovation in North America.
Stem cell regulations USA strictly limit the deployment of cultured cellular therapies outside of approved clinical trials. The FDA restricts unapproved stem cell therapies within the United States due to safety concerns regarding treatments lacking rigorous clinical trial data (U.S. Food and Drug Administration, 2023).
To understand the American bottleneck, we need to examine the FDA’s stance on expanded cell use. The agency mandates that cellular products exceeding “minimal manipulation” be classified and regulated as biological drugs. This means that if a lab takes stem cells and multiplies them over several weeks to reach therapeutic doses which is exactly what umbilical cord stem cells ulcerative colitis patients need those cells legally become a drug. They must then undergo extensive, multi-year, billion-dollar clinical testing before receiving commercial authorization.
The FDA aggressively warns against unregulated domestic clinics that illegally bypass these protocols. It isn’t that the FDA denies the biological plausibility of MSCs. Rather, they require a level of standardized phase-three trial data that is exceptionally difficult to fund and execute for complex regenerative therapies today. So, what happens when you run out of FDA-approved options? You’re basically told to wait for surgery. It’s incredibly frustrating for patients staring down a colectomy.
We must differentiate between banned stem cell research countries which usually restrict therapies based on ethical disputes over embryonic cells and the regulatory bottlenecks for adult UC-MSCs in the West. It’s a crucial distinction. In Europe, the European Medicines Agency (EMA) applies similarly rigid constraints. Consequently, this rigid regulatory framework necessitates medical tourism for patients requiring immediate intervention for refractory diseases. When domestic doctors say “no,” desperate patients board flights. As medical tourism rapidly expands to circumvent these strict regulations, pop culture has unfortunately increasingly blurred the lines between clinical reality and celebrity endorsement, confusing many patients trying to make serious medical decisions.
Celebrity stem cell treatments have significantly elevated public awareness of regenerative medicine, though often at the expense of clinical accuracy. High-profile endorsements frequently conflate unverified anti-aging infusions with the highly specific, evidence-based immunomodulatory protocols required to effectively treat chronic complex autoimmune conditions like severe Ulcerative Colitis.
Let’s talk about the “Joe Rogan effect.” Podcasts and influencers have drastically boosted medical tourism awareness, but they usually endorse vague vitality infusions or localized orthopedic injections for joint pain. They aren’t talking about precision mucosal healing for severe gastrointestinal bleeding. But let’s be absolutely clear. You cannot base serious autoimmune treatment decisions on a comedian’s shoulder recovery. It just doesn’t translate.
The ISSCR warns against unproven clinics marketing stem cell treatments endorsed by celebrities, emphasizing that legitimate therapies are strictly regulated and rarely offered as a cure-all.
Patients constantly search for diseases cured by stem cells. While hematopoietic stem cells legitimately treat blood disorders like leukemia, treatments for IBD remain focused strictly on disease management and clinical remission. Applying the UC Regenerative Threshold reveals a stark reality. If a clinic claims their intravenous package will simultaneously fix your colitis, reverse your aging, and cure your arthritis, you should walk away immediately. Real medical science, per the American Medical Association, strictly demands highly targeted, disease-specific clinical protocols.
Regenerative gastroenterology extends far beyond stem cells into targeted microbial and structural therapies. Researchers are currently advancing faecal microbiota transplantation (FMT) Thailand protocols and lab-grown 3D cellular structures organoids to repair intestinal damage. These represent the next fascinating frontier in personalized medicine for refractory Inflammatory Bowel Disease.
FMT is rapidly gaining clinical traction as a viable alternative for patients wary of stem cell therapy for IBD. By transferring processed, healthy donor microbiota into the patient’s gut, FMT actively restores microbiome diversity. A 2022 clinical review demonstrated that FMT clinical remission rates can reach up to 30% in Ulcerative Colitis patients. It fundamentally alters the gut’s bacterial environment, cooling autoimmune responses. But is it a silver bullet? Not quite yet. While highly promising, it remains largely experimental for IBD compared to established cellular interventions.
Simultaneously, researchers are pioneering 3D cellular structures organoids. These are essentially miniaturized, lab-grown versions of your own gut tissue. Advanced 3D organoid models developed by Stanford researchers allow scientists to test personalized regenerative therapies on patient-specific intestinal lining structures. Instead of guessing if a therapy will work, clinicians can physically test cellular treatments on your specific organoids outside your body to measure exact cytokine responses. Regardless of the specific regenerative technology pursued, ensuring patient safety requires rigorous clinical screening and clear therapeutic limits.
Stem cell treatment does not cure ulcerative colitis permanently. It functions by modulating the immune system to reduce intestinal inflammation and induce long-term clinical remission. While clinical evidence shows that mesenchymal stem cells can facilitate mucosal healing, managing the disease remains a lifelong process.
The cost of stem cell therapy in Thailand averages between $5,000 and $15,000 per treatment cycle. This pricing varies significantly depending on the cellular source, the volume of infusions, and the facility’s specific laboratory infrastructure. While this offers a massive financial advantage compared to experimental Western options, medical travel incurs additional logistical expenses.
Stem cell therapy is not universally banned in the USA, but it is strictly regulated. The FDA prohibits the commercial use of expanded cellular products that exceed “minimal manipulation” outside of approved clinical trials. Therefore, therapies utilizing cultured umbilical cord stem cells for autoimmune conditions remain heavily restricted domestically. This rigid regulatory reality frequently prompts patients to legally seek advanced cellular treatments internationally.
Joe Rogan frequently promotes international stem cell therapy on his podcast, citing personal recovery from musculoskeletal injuries. However, these anecdotal reports focus primarily on localized orthopedic vitality rather than complex autoimmune disease management. Leading medical societies strongly caution against using celebrity wellness anecdotes to evaluate treatments for serious chronic conditions like colitis.
Stem cell therapy demonstrates significant biological plausibility for refractory ulcerative colitis. Research indicates targeted cellular infusions alter the inflammatory microenvironment in the gut, helping patients who remain completely unresponsive to conventional medications. Clinical success is strictly measured by reductions in inflammatory biomarkers and tangible improvements in endoscopic tissue healing. Ultimately, individual suitability dictates outcomes, making professional medical consultation absolutely essential.
For patients navigating refractory conditions, stem cell therapy for ulcerative colitis provides a scientifically validated cellular mechanism to suppress chronic inflammation. By utilizing mesenchymal stem cells to induce phenotypic macrophage reprogramming, advanced clinics in
Applying The UC Regenerative Threshold is essential for patients evaluating these treatments. This evidence-led framework separates proven immunomodulation from unfounded commercial claims of a definitive cure. Understanding the biological reality of cellular therapy ensures patients set realistic functional goals, prioritizing long-term disease management and improved quality of life over celebrity-driven medical hype.
Before pursuing international medical travel, compile your comprehensive medical records, imaging, and laboratory findings. Discussing these specific diagnostic markers with a qualified medical professional ensures a safe, evidence-informed suitability assessment for advanced regenerative interventions. Consult your primary gastroenterologist to review your latest endoscopy results and fecal calprotectin levels before scheduling any international consultations. Make your health decisions based on verified peer-reviewed clinical data, never solely on unverified promotional marketing brochures.