Our Services
Others
- DFPP
- Shockwave
- IV Drip

For patients experiencing diminishing returns from standard stimulant protocols, investigational treatments like mesenchymal stem cell (MSC) therapy have rapidly entered the clinical conversation. However, navigating the modern regenerative medicine ecosystem requires distinguishing biological plausibility from unverified commercial claims that promise unrealistic cures. Clinical reviews indicate that while the marketing copy from offshore clinics sounds phenomenal, the science is profoundly more complicated.
By the end of this guide, you’ll understand the exact neurobiological mechanisms, current clinical trial data, and strict regulatory realities of MSCs, empowering you to make evidence-informed medical decisions. We will rigorously analyze the baseline etiology of ADHD, standard treatment limitations, the actual cellular mechanisms of action, and the global network of investigational clinics as they stand today.
This article is for educational purposes only and does not replace consultation with a qualified medical professional.
Stem cell therapy for ADHD remains an investigational treatment targeting neuroinflammation and neurotransmitter imbalances through the paracrine signaling of Mesenchymal Stem Cells (MSCs).
Genetics remains the primary driver of ADHD development, with CDC research invalidating theories that the condition is caused by environmental lifestyle factors alone (CDC, 2023). Before we can accurately assess the biological viability of Stem Cell Therapy for ADHD, we have to look closely at the underlying neurodevelopmental baseline. Too many clinics market regenerative therapies as a way to “fix” brain damage, which fundamentally misunderstands how attention-deficit/hyperactivity disorder actually forms in the human brain.
If you don’t understand the physiological baseline, it’s virtually impossible to separate a legitimate investigational treatment from a predatory commercial scam.
When parents ask, “Are you born with ADHD?”, the clinical data provides a definitive answer: yes. The heritability of ADHD is exceptionally high, hovering around 74-80% in modern psychiatric literature. This makes it as genetically linked as human height. CDC research on the genetic root causes confirms that genetics is a primary factor in ADHD development, noting that current research simply does not support outdated views that ADHD is caused by environmental lifestyle factors like poor parenting, sugar intake, or early screen time (2023).
We also see this clearly validated in twin studies published across major databases like the National Institutes of Health (NIH) genetics database. If one identical twin has ADHD, the probability that the other twin shares the diagnosis is overwhelming.
To understand the cellular necessity of treatments, one must look at the specific dopaminergic mechanics. The DAT1 gene, for example, dictates the production of dopamine transporters. When this gene expresses atypically, the brain essentially vacuums up dopamine from the synaptic cleft before it can successfully transmit executive function signals. Similarly, variations in the DRD4 receptor gene mean the prefrontal cortex is fundamentally less receptive to the dopamine that does manage to bridge the gap. These genetic variations physically alter how dopamine is transported and absorbed, creating a chronic deficit that cannot be disciplined or parented away.
Environmental triggers simply load the weapon that genetics built. We often look at the “7 triggers” that exacerbate existing executive dysfunction. Systemic nutritional deficits, particularly in magnesium and zinc, can severely compromise neurotransmitter synthesis, starving the brain of the raw materials needed to produce dopamine. Meanwhile, severe sleep deprivation disrupts the brain’s overnight glymphatic clearance, leaving the prefrontal cortex exhausted and saturated with metabolic waste. High-stress domestic environments and comorbid anxiety don’t cause the neurological divergence, but they act like gasoline on a fire.
Clinical consensus indicates that treating the environment is often the first step to stabilizing the baseline. Contrast a genetic dopamine deficiency with environmental stress-induced executive dysfunction. The former requires physiological intervention; the latter requires behavioral and environmental modification. Until you control the environmental triggers, measuring the efficacy of any advanced medical protocol regenerative or pharmacological is basically guesswork.
A pervasive question in pediatric neurology is what age does ADHD get better? The answer isn’t straightforward. While roughly 30% to 50% of patients experience a notable reduction in outward symptoms by late adolescence, the neurodivergent brain structures do not disappear. Instead, the presentation of the disorder evolves.
Childhood ADHD is frequently characterized by extreme physical hyperactivity and outward impulsivity. During puberty, hormonal fluctuations dramatically alter neurotransmitter receptivity, frequently exacerbating emotional dysregulation. As the central nervous system matures and the prefrontal cortex attempts to catch up in development usually a 3-year delay compared to neurotypical brains that physical hyperactivity often internalizes. By adulthood, it manifests as severe internal restlessness, executive dysfunction, and chronic mental fatigue.

This transition is incredibly dangerous for patient burnout. The intersection of decreasing physical symptoms but exponentially increasing societal demands such as financial independence, higher education, and career management creates a profound masking effect. Adult patients frequently expend massive amounts of cognitive energy simply attempting to appear neurotypical in professional settings, leading to severe neurological exhaustion.
This ADHD age progression is critical to understand because clinical trial endpoints for regenerative therapies often measure completely different behavioral markers depending on the age cohort. A treatment that reduces physical pacing in an 8-year-old might do absolutely nothing for the working memory deficits of a 35-year-old.
Furthermore, the American Academy of Pediatrics guidelines clearly note that executive function demands actually peak during early adulthood (2019). Just as a patient’s biological hyperactivity begins to naturally wane, society suddenly demands they manage complex modern lives. This intersection is precisely when many patients abandon standard protocols and begin researching experimental alternatives.
While etiology is genetic, symptom severity fluctuates aggressively throughout the patient’s lifespan, requiring dynamic management strategies.
While standard stimulant medications effectively reduce symptoms in up to 80% of individuals, they do not offer a permanent neurobiological cure (NIMH, 2023). The search for the most successful treatment for ADHD usually begins in the pediatrician’s office and ends, years later, in a frustrating cycle of medication adjustments.
Standard pharmacological protocols are the undisputed gold standard in Western medicine. They have decades of double-blind, placebo-controlled data backing their efficacy. But they are entirely palliative. When the medication leaves the bloodstream, the structural neurobiology of the brain remains unchanged. This limitation is the exact friction point that drives informed patients to look toward alternative, holistic, and ultimately regenerative interventions.
Standard pharmacological treatments primarily target the dopaminergic and noradrenergic pathways. Stimulants like methylphenidate and amphetamines act as potent reuptake inhibitors. They block the dopamine transporter (DAT), forcing dopamine to remain in the synaptic cleft longer, thereby enhancing signaling in the prefrontal cortex.
The immediate clinical efficacy of these drugs is staggering. NIMH overview of standard medications notes that while standard treatments effectively reduce symptoms, they do not cure ADHD (2023). They act like prescription eyeglasses—they correct the deficit perfectly while worn, but they don’t fix the underlying shape of the eye.
However, tolerance build-up, or tachyphylaxis, frequently complicates long-term stimulant use. Patients often hit dosage ceilings where increasing the medication yields no further cognitive benefit, only amplifying cardiovascular stress and central nervous system burnout.
Similarly, evidence-based treatment protocols reviewed by Johns Hopkins Medicine highlight that successful ADHD management currently relies on a combination of behavioral therapy and carefully calibrated medication (2024). But the side effects are often brutal.
Discontinuation rates show that many adult patients abandon stimulants due to severe appetite suppression, chronic insomnia, and underlying cardiovascular anxiety. When the central nervous system is constantly flooded with synthetic reuptake inhibitors, the adrenal system can become chronically fatigued, leading to a profound crash when the medication wears off. Non-stimulants like atomoxetine offer an alternative by targeting norepinephrine, but they often take weeks to reach steady-state efficacy and have a statistically lower response rate.
| Treatment Type | Mechanism of Action | Clinical Efficacy | Primary Limitations |
| CNS Stimulants | Dopamine/Norepinephrine reuptake inhibition | High (70-80% response rate) | Palliative only; sleep disruption; cardiac load |
| Non-Stimulants | Selective norepinephrine reuptake inhibition | Moderate (40-50% response rate) | Delayed onset; gastrointestinal distress |
| MSC Stem Cells | Paracrine signaling / anti-inflammatory | Investigational (unproven) | No FDA approval; extreme cost; no standardized dosing |
The limitations of chronic medication management frequently drive patients toward holistic alternatives and, increasingly, experimental regenerative models.
When standard protocols fail, patients understandably look elsewhere. The internet is flooded with claims regarding the best supplements for ADHD, untested neurofeedback devices, and highly expensive regenerative procedures. To objectively evaluate these claims, utilizing the Evidence-Informed Regenerative Assessment (EIRA) Framework is essential. This structured methodology protects patients from predatory marketing by demanding rigid scientific proof across three distinct pillars:
If we run common holistic alternatives through the EIRA framework, the results are mixed. High-dose Omega-3 fatty acids, Magnesium L-threonate, and Zinc have a verified mechanism (reducing general neuroinflammation and supporting neurotransmitter synthesis). However, their Phase III clinical data shows only very mild efficacy. They are excellent adjunctive therapies, but they are not standalone treatments.
When evaluating traditional Chinese ADHD treatment methodologies or a japanese adhd treatment protocol like Kampo herbal medicine, the EIRA framework often flags a lack of standardized, replicable Phase III data. While these modalities have rich historical usage, their biochemical mechanisms are incredibly difficult to isolate in controlled Western clinical environments.
This brings us to stem cells. The marketing surrounding regenerative therapy often completely bypasses the EIRA framework, promising functional cures based strictly on theoretical mechanisms. To protect yourself, you must demand that regenerative clinics answer to this framework.
Mesenchymal Stem Cells (MSCs) do not directly become new neurons; instead, they utilize paracrine signaling to secrete neurotrophic factors that theoretically reduce neuroinflammation (Harvard Stem Cell Institute, 2024).
When patients Google “how do stem cells treat ADHD,” they are usually met with wildly inaccurate diagrams showing a stem cell floating into the brain, finding a damaged neuron, and magically morphing into a healthy replacement cell. That is absolute biological fiction. And honestly, it’s a dangerous narrative. To understand why clinics charge $15,000 for these treatments and why researchers are genuinely excited but extremely cautious you have to understand the grueling, highly technical reality of cellular biology. Mesenchymal Stem Cells (MSCs), multipotent adult stem cells derived from tissue such as the umbilical cord or bone marrow, operate as microscopic pharmacies, not as spare parts. They don’t replace; they communicate.
When mainstream media podcasts like the Joe Rogan Experience feature athletes and celebrities praising the miraculous recovery times of joint injuries using stem cells, public interest naturally explodes. But the cultural conversation frequently glosses over the biological nuances of neurodevelopmental applications. Translating localized orthopedic success into psychiatric neurology is wildly complex. Injecting cells into a torn meniscus is fundamentally different than attempting to rewrite the dopaminergic pathways of the prefrontal cortex.
MSCs possess robust immunomodulatory properties and home in on sites of tissue injury or severe inflammation. But in the context of neurodevelopmental disorders, their proposed value lies almost entirely in a process called paracrine signaling.
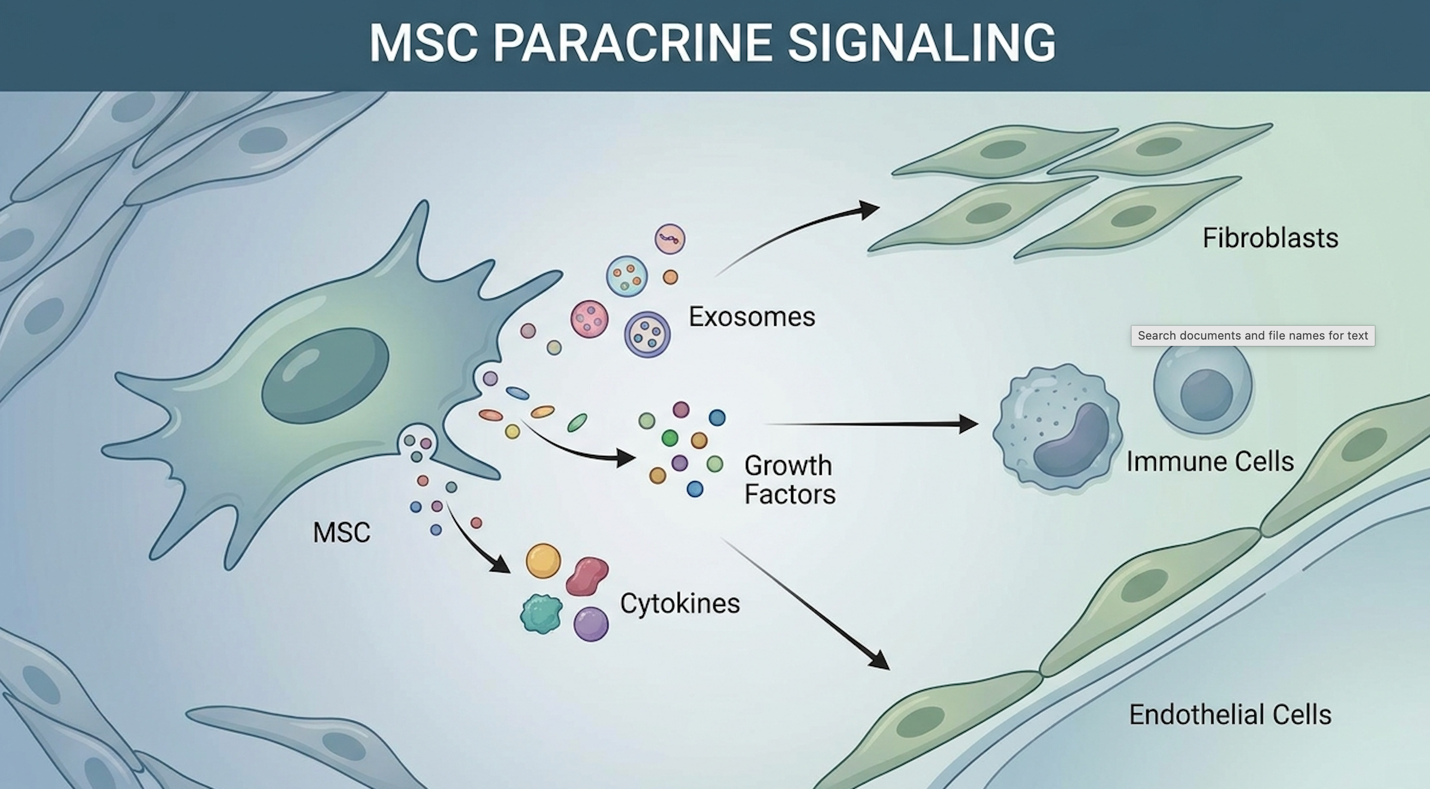
When MSCs are introduced into the body typically via intravenous infusion or, in riskier offshore settings, intrathecal injection into the spinal fluid they do not engraft and become permanent brain tissue. Instead, they act as transient cellular factories. They secrete a vast, highly complex cocktail of bioactive molecules known as the secretome.
This secretome is packed with cytokines, chemokines, and critical neurotrophic factors. These secreted factors are frequently packaged into exosomes tiny extracellular vesicles that act as the delivery vehicles for this biological cargo. Exosomes can easily cross the blood-brain barrier, which is one reason intravenous delivery of MSCs is even considered a viable route in some trial protocols. Once these exosomes reach the neuro-environment, they dump their cargo directly into the surrounding tissue.
The two most important factors for psychiatric neurology are Brain-Derived Neurotrophic Factor (BDNF) and Glial Cell Line-Derived Neurotrophic Factor (GDNF). Harvard Stem Cell Institute’s research demonstrates that while stem cells have profound potential for mapping and treating neurodegenerative pathways, their application requires rigorous, phased validation (2024). BDNF is absolutely essential for neurogenesis and synaptic plasticity. It physically supports the survival of existing neurons and encourages the growth and differentiation of new neurons and synapses.
The prevailing theory in MSC stem cell therapy for ADHD is that by flooding the central nervous system with these neurotrophic factors, the brain’s native cells are stimulated to repair their own damaged neurotransmitter pathways. Look at it this way: the MSCs aren’t the bricklayers fixing the wall. They are the foremen yelling instructions and handing out high-quality mortar to the local crew. NCBI reviews on stem cell paracrine mechanisms confirm that this signaling can theoretically promote the synthesis of neurotransmitters, attempting to address the specific dopamine and norepinephrine deficits seen in the ADHD brain.
But does stem cell therapy for dopamine imbalance and ADHD symptoms actually work in practice? The biological plausibility is phenomenal. The lab data on animal models is highly encouraging. We’re talking about profound molecular repair at a level we couldn’t even visualize twenty years ago. Yet, generating BDNF in a petri dish is a universe away from sustainably correcting executive dysfunction in a living human being. Paracrine signaling provides a brilliant theoretical bridge, but crossing it requires clearing monumental clinical hurdles.
If we move beyond neurotransmitters, we hit the second major therapeutic target for MSC stem cell therapy: chronic neuroinflammation. Over the last decade, psychiatric neurology has undergone a fundamental change regarding brain inflammation. We now have compelling evidence that chronic, low-grade neuroinflammation heavily exacerbates neurodevelopmental disorders. It’s no longer just a fringe theory; it’s a central biological mechanism.
How do MSC stem cells reduce brain inflammation in ADHD? It comes down to microglia the primary immune cells of the central nervous system. In a healthy brain, microglia prune unused synapses and clean up cellular debris. But in chronically inflamed nervous systems, microglia get stuck in a hostile, pro-inflammatory state (the M1 phenotype). They stop cleaning and start attacking.
Let’s look at how neuroinflammation specifically disrupts dopamine. Chronic inflammation doesn’t just make the brain ‘tired’; it actively depletes the biochemical precursors needed to synthesize dopamine. When the brain is inflamed, the kynurenine pathway steals tryptophan away from producing serotonin and dopamine, routing it instead toward producing inflammatory neurotoxins. So, when MSC stem cells for neurodevelopmental disorders initiate macrophage reprogramming, they are theoretically halting this biochemical theft.
When MSC stem cells detect this inflammation, they release anti-inflammatory cytokines (like IL-10 and TGF-beta). This triggers phenotypic macrophage reprogramming. The MSCs literally force the hostile M1 microglia to switch to a healing, anti-inflammatory state (the M2 phenotype). By quieting the immunological storm in the brain, the theory suggests that neural plasticity the brain’s ability to adapt, learn, and form new functional pathways is drastically improved. They shut down the kynurenine pathway over-activation. The patient experiences less physiological stress because their brain is literally no longer consuming its own neurotransmitter building blocks to fight a phantom infection.
Patients often ask about stem cell treatment for brain plasticity and executive function. If the brain is no longer fighting chronic inflammation, it frees up metabolic resources. The patient might experience less brain fog, better emotional regulation, and improved focus. The science here is deeply fascinating. But we have to look at the reality of the data.
Let’s apply the EIRA Framework here. The verified mechanism of action (Pillar 1) is absolutely solid. MSC Stem Cell definitely reduce inflammation. But when we look at Measurable Functional Outcomes (Pillar 3), we hit a wall. Reducing general brain inflammation might make a patient feel subjectively better more rested, less irritable but does it actually correct the genetic dopamine transporter deficit that causes ADHD?
Current evidence suggests it does not. Stem cells for brain inflammation are incredibly promising for autoimmune conditions, but translating that generalized anti-inflammatory effect into a permanent cure for a highly specific genetic neurodevelopmental disorder remains entirely unproven. While the theoretical cellular mechanics present a compelling case, patient safety mandates that these mechanisms be validated through rigorous, human-based clinical trials. The gap between biological possibility and a clinical cure is exactly why standard protocols remain the baseline of care.
Applications of stem cells for neurodevelopmental disorders remain in early Phase I/II investigational trials, and are not yet classified as standard medical practice (ClinicalTrials.gov, 2024).
The gap between what clinical trial data actually says and what international medical clinics claim on their websites is staggering. When evaluating stem cell therapy for neurodevelopmental disorders, you have to become ruthless about data quality. Marketing brochures rely on testimonials; medical science relies on double-blind, placebo-controlled data. Right now, the data pool for ADHD-specific regenerative therapy is incredibly shallow. Across neurodevelopmental research, the consensus is that the vast majority of current human trials are engineered to test basic safety, not long-term psychiatric efficacy.
If you review the scope of stem cell research on the NIH registries, a distinct pattern emerges. The trials are heavily concentrated in Phase I and early Phase II stages. Phase I trials are designed strictly to answer one question: Will this treatment kill or harm the patient? Phase II trials begin to look at efficacy, but in very small, highly controlled cohorts.
The early investigational status on ClinicalTrials.gov shows that stem cell applications for neurodevelopmental disorders remain in early investigational phases, indicating these treatments are strictly experimental (2024). There are virtually no Phase III trials the massive, multi-center, placebo-controlled studies required for FDA approval currently nearing completion for ADHD.
Furthermore, the existing ADHD stem cell clinical trials suffer from severe methodological flaws. They often have sample sizes of fewer than 30 patients. They frequently lack sham-controlled arms. Without a sham-controlled arm, there is no placebo group to rule out the incredibly powerful psychological placebo effect, which is notoriously strong in psychiatric interventions. If you spend $15,000 on a treatment, you naturally look desperately for signs that it worked.
Consider the statistical reality. Statistics showing 6 million childhood ADHD diagnoses reveal an estimated 6 million children in the United States alone have been diagnosed with ADHD, representing a massive patient population (2024). Yet the total number of patients who have participated in rigorous, peer-reviewed stem cell trials for ADHD globally is a fraction of a percent of that. You simply cannot extrapolate a guaranteed medical cure from a statistically insignificant sample size.
The murky nature of this clinical data is further complicated by dual diagnoses. A significant percentage of patients investigating these treatments have comorbid presentations. Autism and ADHD stem cell therapy are frequently marketed together by clinics under the broad umbrella of treating “neurodevelopmental delay.”
The clinical reality is that Autism Spectrum Disorder (ASD) has a much larger body of ongoing stem cell research compared to isolated ADHD. In published case literature regarding ASD and ADHD dual diagnoses, some parents do report distinct, noticeable improvements following MSC infusions.
Let’s look at a widely circulated YouTube case study frequently discussed in regenerative medicine circles that perfectly illustrates this dynamic. The video diaries detailed the journey of a 21-year-old patient diagnosed with both severe ASD and comorbid ADHD. After failing to respond to maximum doses of standard amphetamine stimulants and experiencing severe, daily behavioral meltdowns, the family pursued an international MSC infusion protocol. They documented a high-dose intravenous umbilical cord MSC treatment spanning several days.
Over a six-month post-treatment observation period, the subjective clinical notes were undeniably intriguing. The patient’s severe aggressive outbursts decreased by roughly 60%. His sleep architecture previously fragmented and chaotic stabilized into normal REM cycles. Eye contact and baseline communicative efforts noticeably improved. The family felt they had achieved a medical miracle.
And honestly, for a family pushed to the absolute brink, that level of behavioral calming is a massive, life-altering victory. But when we apply the EIRA Framework to this case study, we have to rigidly isolate the variables. Did the MSCs cure the genetic dopamine deficit causing the ADHD? Or did the secretome’s massive anti-inflammatory payload simply quiet the severe neuroinflammation commonly seen in profound autism?
The behavioral calming allowed the patient to function better in his household, but independent neurological assessments showed his baseline working memory and executive dysfunction remained largely unchanged. He was calmer, but the core ADHD neurobiology persisted. This is exactly why dual-diagnosis outcomes are so notoriously difficult to interpret in uncontrolled settings.
When stem cells quiet the brain’s immune microenvironment via macrophage reprogramming, the patient experiences less physiological stress. A child who is no longer suffering from chronic neuroinflammation is naturally going to be calmer and exhibit fewer behavioral meltdowns. This generalized calming is deeply valuable. However, it is not the same as restoring the dopamine deficits required for sustained executive function, working memory, and complex task initiation.
Because these treatments lack domestic FDA approval, patients pursuing these investigational outcomes are driven toward the complex, often dangerous ecosystem of international medical tourism.
The FDA strictly warns that unapproved stem cell therapies pose significant safety risks, as the only approved treatments in the U.S. are derived from cord blood for specific blood disorders (FDA, 2024).
If you decide that the biological plausibility of MSC therapy is worth the investigational risk, you immediately hit a geographical roadblock. You cannot walk into a hospital in New York or London and request stem cell therapy for ADHD. Because it lacks Phase III clinical validation, it is illegal for domestic clinics to market and administer these unapproved biologics for psychiatric conditions.
This regulatory environment has birthed a massive global medical tourism industry. Finding a clinic is incredibly easy; finding a safe, ethically run clinic is remarkably difficult.
Over the last decade, countries with decentralized medical regulatory frameworks have become hubs for regenerative medicine. Clinics in Mexico, Panama, and Turkey have become primary destinations because their local health ministries permit expanded access to investigational cell therapies that the FDA strictly blocks.
Patients frequently navigate this ecosystem using medical tourism aggregators like Bookimed or Lyfboat. While these platforms streamline the logistical process of booking flights, arranging hotels, and providing translation services, they are ultimately commercial brokers, not medical regulators. If you are exploring adhd stem cell therapy turkey or Mexico, you have to understand that the local health ministry’s oversight does not mirror Western medical board standards. Many patients assume that because a clinic has high-end waiting rooms and slick marketing, their laboratory standards must match Western clinical hospitals. This is a potentially fatal assumption.
The FDA guidelines and warnings explicitly state that the only approved stem cell products are for blood disorders, warning that unapproved therapies pose significant safety risks (2024). Furthermore, CDC advisories on medical tourism urge extreme caution, noting the high risk of severe bacterial infections and complications from unregulated overseas facilities (2024).
When evaluating stem cell treatment for ADHD Mexico or experimental ADHD clinics globally, patients must act as their own regulatory agency. You have to demand proof of third-party cellular viability testing. You need to see actual ISO-certified clean-room documentation. Documented adverse events include cases where families paid tens of thousands of dollars for “millions of live MSCs,” only to suffer severe systemic infections because the overseas clinic lacked basic sterile compounding standards. Regenerative therapy for ADHD is dangerous enough biologically; adding compromised lab hygiene into the mix is catastrophic.
The financial barrier to entry for investigational regenerative medicine is staggering. Because these procedures lack regulatory approval from bodies like the FDA or the EMA, they are entirely out-of-pocket. No traditional medical insurance, Medicare, or national health service will cover a single cent of an unapproved psychiatric stem cell infusion.

Let’s break down the true Total Cost of Care. The stem cell therapy for ADHD cost is rarely just the price of the infusion.
| Expense Category | Estimated Cost Range (USD) | Notes |
| MSC Infusion (per session) | $8,500 – $15,000 | Depends on cell count (e.g., 50 million vs 100 million cells) |
| Travel & Lodging | $1,500 – $3,000 | Flights, hotels, ground transport in medical hubs |
| Pre/Post Medical Testing | $1,000 – $2,500 | Independent blood panels, inflammatory markers, neurologist visits |
| Total Estimated Cost | $11,000 – $20,500 | Per single treatment trip |
Clinics often recommend a series of 2 to 3 treatments over a 12-month period to achieve “maximum neurotrophic effect.” You can quickly see how this escalates into a $50,000 gamble on an unproven biological theory.
No matter how compelling the underlying science of paracrine signaling is, patient safety has to remain the absolute priority. The regenerative medicine space is filled with exceptional, well-meaning scientists, but it is equally populated by aggressive salespeople exploiting desperate families. You have to install firm psychological and medical guardrails before signing a consent form for investigational treatments.
Investigational therapies are, by definition, therapies of last resort. If you have a patient with mild-to-moderate ADHD who has only tried one class of stimulant medication, they have no business pursuing experimental medical tourism.
Standard pharmacological and behavioral frameworks remain the empirically proven first-line defense. You must exhaust the dopaminergic stimulants (both methylphenidate and amphetamine classes), non-stimulants, and rigorous cognitive behavioral therapy protocols before ever considering international stem cell infusions. Jumping straight to regenerative medicine because you fear standard pharmaceuticals is an irrational calculation of clinical risk.
You absolutely cannot navigate this ecosystem alone. Before wiring a deposit to an overseas clinic, you must consult directly with your primary board-certified neurologist or psychiatrist.
Do not hide your intentions from your local medical team out of fear of judgment. An expert clinician will help you evaluate whether abandoning standard care for unapproved treatments poses severe physiological and psychological risks to your specific neurobiology. If your local neurologist vehemently opposes the trip, you need to listen closely to their methodological reasoning.
ADHD does not typically go away naturally, as it is rooted in permanent neurodevelopmental and genetic brain structures. While hyperactive symptoms often decrease as a patient matures, approximately 30% to 50% of individuals continue to experience significant executive dysfunction and inattention into adulthood (NIH research on ADHD lifespans). The brain’s prefrontal cortex develops coping mechanisms and compensatory neural pathways over time. However, true clinical management requires ongoing behavioral strategies or pharmacological support, as the baseline neurobiology remains divergent.
The most clinically supported supplements for ADHD symptom management include Omega-3 fatty acids, Magnesium, Zinc, and Vitamin D. These micronutrients support baseline neurotransmitter synthesis and reduce general neuroinflammation, showing mild to moderate efficacy in clinical trials. They are most effective when utilized as adjunctive therapies alongside prescribed stimulant or non-stimulant medications. Patients should always undergo serum level testing before beginning supplementation to avoid toxicity and ensure proper dosing protocols with a physician.
The most recent focus in stem cell therapy for ADHD involves the use of Mesenchymal Stem Cells (MSCs) to target neuroinflammation via paracrine signaling. Rather than attempting to grow new brain cells, researchers are investigating how MSC secretomes might theoretically repair damaged neural pathways and balance dopamine levels. It is critical to note that these applications remain strictly in early-phase clinical trials and are not approved as a standard medical breakthrough or cure by the FDA.
For patients researching advanced ADHD interventions, mesenchymal stem cell (MSC) therapy represents an investigational frontier targeting neuroinflammation rather than a verified cure. Current clinical registries demonstrate that these therapies remain in early testing phases, lacking FDA approval. An estimated 6 million pediatric patients are diagnosed in the U.S. alone (Statista, 2024). The best approach combines a strict understanding of neurobiology with rigorous skepticism of international clinic claims.
To protect yourself, always apply the Evidence-Informed Regenerative Assessment (EIRA) Framework. Evaluating experimental treatments requires demanding peer-reviewed Phase III data, a verified mechanism of action, and functional outcome proof, rather than relying on commercial marketing and unverified testimonials. Biomarker improvements do not inherently guarantee behavioral cures.
Your next step is critical: you must gather your complete neurological records and consult directly with a board-certified neurologist to discuss your current medication efficacy. Book a dedicated evaluation appointment to exhaust all standard, evidence-based pharmacological and behavioral options before ever considering the severe financial and medical risks of out-of-pocket, investigational medical tourism.
This article is for educational purposes only and does not replace consultation with a qualified medical professional.