Our Services
Others
- DFPP
- Shockwave
- IV Drip

When your MRI or X-ray report reveals “subchondral sclerosis,” standard advice often stops at pain management or joint replacement. Treating the cartilage without addressing the hardened, inflamed bone beneath it inevitably leads to continued degeneration, localized pain, and loss of functional outcomes. By the end of this guide, you will understand the specific biological mechanisms of The Subchondral-First Regenerative Approach and exactly how it targets the root cause of your imaging findings. We will analyze imaging terminology, review the latest clinical efficacy data, compare biological therapies to surgical subchondroplasty, and outline strict suitability criteria.
Because here’s the reality: cartilage doesn’t exist in a vacuum. If the structural foundation of the joint is crumbling, surface-level treatments won’t save it. For patients seeking evidence-informed alternatives to invasive surgery, understanding the interplay between bone marrow lesions and primary stem cell therapy for subchondral sclerosis is the necessary first step.
Stem cell therapy for subchondral sclerosis focuses on treating the inflamed bone beneath the cartilage, known as The Subchondral-First Regenerative Approach.
Subchondral sclerosis is the abnormal hardening and thickening of the bone situated directly beneath the articular cartilage. This physiological response occurs when cartilage loss forces the underlying bone to bear increased mechanical stress, leading to microfractures, intense localized inflammation, and eventual bone densification. Patients obsessing over the white lines on their X-rays are often focusing on the wrong target; the active fluid seen on an MRI dictates the true clinical timeline and pain severity.
Reading a radiology report can feel like translating a dead language. Patients frequently misunderstand what their imaging actually reveals about their joint health and structural longevity. What is subchondral sclerosis, practically speaking?
To understand it, you have to look at the anatomy. The subchondral bone isn’t just a static, lifeless shelf; it is a highly vascularized, dynamic trabecular network engineered to dissipate kinetic energy. Under normal physiological conditions, this spongy bone absorbs roughly 30% of the mechanical load during regular movement. But when things go wrong, the imaging tells a specific story:
An MRI is vastly superior to an X-ray for treatment planning. Why? Because an MRI visualizes the active inflammatory phase (BMLs) before irreversible hardening occurs, pinpointing the exact targets for regenerative intervention.
Clinical evaluations of imaging reports consistently demonstrate that patients often believe osteoarthritis is solely a “wear and tear” cartilage issue. This is an outdated biological model. The subchondral bone and articular cartilage share an intricate, biochemical crosstalk that dictates the health of the entire joint complex.
When subchondral sclerosis and osteoarthritis develop together, the inflamed bone releases catabolic cytokines destructive proteins such as Interleukin-1 (IL-1) and Tumor Necrosis Factor-alpha (TNF-α) upward into the cartilage, actively accelerating cartilage degradation. Subchondral sclerosis knee pathology isn’t just a byproduct of cartilage loss; it actually drives the disease forward. “Bone-on-bone” osteoarthritis is simply the end-stage manifestation of this process, where the cartilage buffer is completely obliterated, forcing the hardened subchondral plate to absorb 100% of your body’s mechanical impact.
Let’s address the anxiety directly. Is subchondral sclerosis reversible? True, established subchondral sclerosis the dense, calcified bone that appears white on an X-ray is largely irreversible structurally. You cannot turn hardened, densified bone back into a pristine, youthful biological sponge.
However, the active inflammation driving your pain and disease progression is absolutely treatable. Regenerative interventions target active bone marrow lesions to halt degenerative crosstalk and reverse localized inflammation. The primary goal of a subchondral sclerosis treatment isn’t to magically erase the white lines on a diagnostic X-ray. It is to modulate the localized microenvironment, arrest disease progression, and restore your functional outcomes so you can walk, bend, and sleep without severe pain.
Clinical radiological evidence confirms that active bone marrow lesions drive localized joint pain proving that targeting this inflammation yields superior functional improvements over surface-level treatments (PubMed).
The Subchondral-First Regenerative Approach is the practice of delivering biological therapies directly into the damaged bone, rather than the joint space. Because subchondral sclerosis and bone marrow edema drive the degenerative process, targeting the bone microenvironment is clinically essential for restoring joint homeostasis and improving long-term functional outcomes. Standard joint injections act as a superficial band-aid, fundamentally ignoring the structural foundation that actually dictates joint longevity.
Standard intra-articular injections where a doctor blindly pushes corticosteroids or hyaluronic acid into the joint cavity often fail completely in advanced osteoarthritis. They simply don’t penetrate the hardened subchondral bone plate where the actual inflammation lives. We can’t just inject the joint and hope for the best when the bone itself is dying.
The subchondral bone acts as the critical shock absorber. When its structural integrity fails, the entire joint biomechanics fail. A subchondral bone stem cell injection bypasses the joint capsule entirely.
Navigating a specialized intra-osseous trocar into densified bone requires extreme precision. Using live fluoroscopic (X-ray) or advanced ultrasound guidance, clinicians map the exact trajectory into the bone marrow lesion. This avoids necrotic bone cysts and ensures the biological payload is deposited directly into the inflammatory epicenter where the cellular signaling is malfunctioning.
| 📌 If you’re interested in why the percentage of living cells matters so much at the time of treatment, we have an interesting article that discusses the importance of cell viability in UC-MSC stem cell therapy, which you can read via the internal link. |
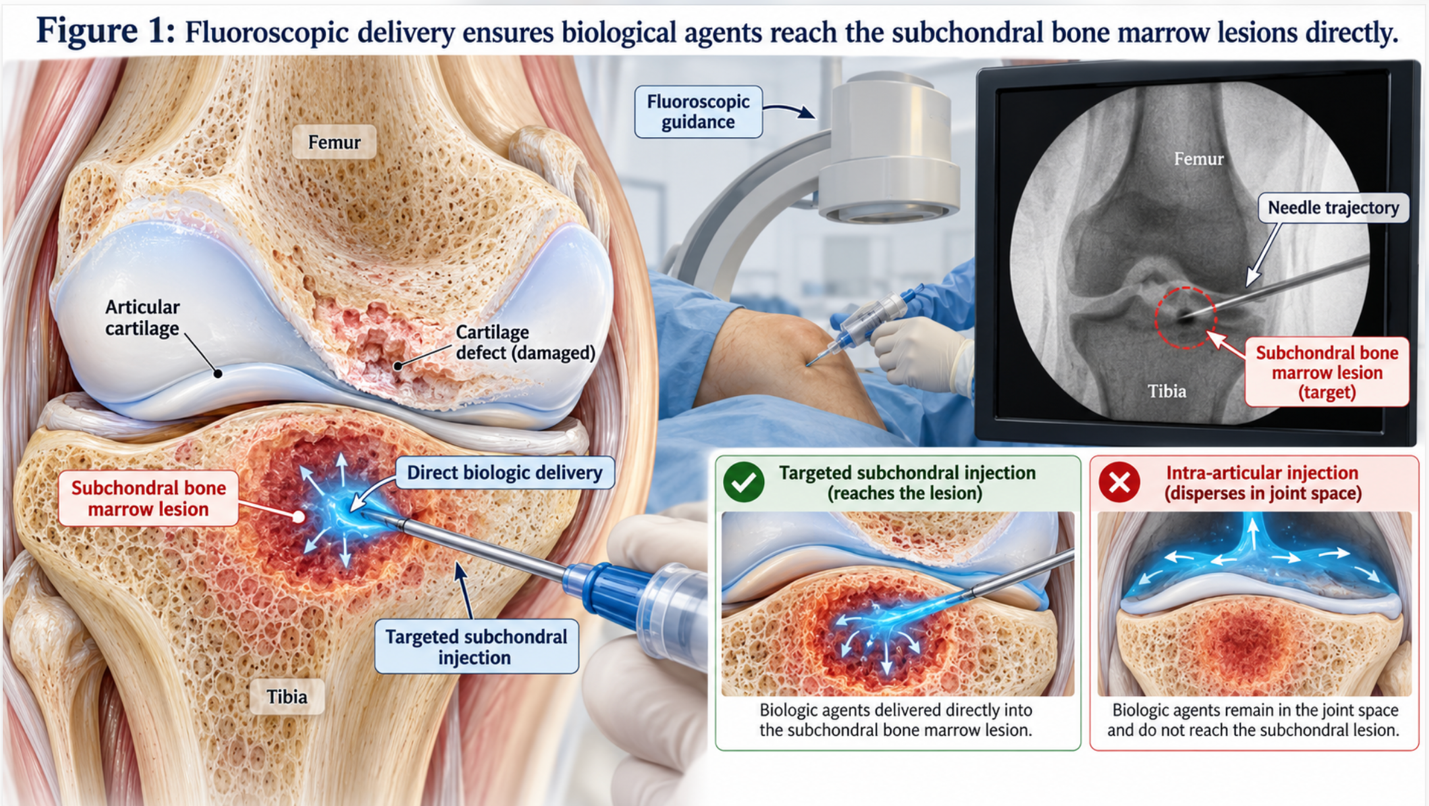
Figure 1: Fluoroscopic delivery ensures biological agents reach the subchondral bone marrow lesions directly.
For years, skeptics questioned whether injecting the bone was worth the procedural complexity and advanced imaging requirements. The data now provides a definitive, clinical answer favoring the subchondral approach.
A landmark 2025 World J Stem Cells review analyzing 298 knees systematically compared delivery methods. The findings were stark and undeniable: patients receiving stem cell therapy for subchondral sclerosis injected directly into the bone demonstrated statistically significant, long-lasting improvements in pain (measured via VAS scales) and function (measured via WOMAC scores) compared to those receiving standard injections into the joint space.
By physically placing the cells into the high-stress bone environment, clinicians effectively disrupt the degenerative feedback loop. Subchondral injections of mesenchymal stem cells yield superior clinical outcomes compared to intra-articular injections by directly addressing bone marrow lesions (World J Stem Cells, 2025). Evidence-informed clinics globally now utilize this specific data to justify the more complex, image-guided subchondral delivery method as the gold standard of care.
Clinical data confirms significant improvements in functional mobility when targeting the bone directly validating the superiority of subchondral injections over intra-articular delivery (World J Stem Cells, 2025).
So, what exactly happens on a cellular level once these cells are deposited into the diseased bone?
Mesenchymal stem cells (MSCs) don’t magically “become” new bone or cartilage. That is a common patient misconception perpetuated by outdated marketing. Instead, they operate through a powerful process called paracrine signaling. MSCs act as microscopic site managers, secreting a localized payload of cytokines, growth factors (like VEGF), and exosomes that actively reprogram the toxic inflammatory environment.
| 📌 If you’re interested in why umbilical cord cells are often preferred over bone marrow or fat-derived cells, we have an interesting article that discusses why UC-MSCs are superior to other stem cell sources, which you can read via the internal link. |
Once situated in the lesion, MSCs release critical anti-inflammatory cytokines, specifically Interleukin-1 receptor antagonist (IL-1ra) and Transforming Growth Factor-beta (TGF-β). This biological modulation addresses bone marrow edema by promoting angiogenesis the formation of new blood vessels to heal necrotic tissue and aggressively inhibiting pro-inflammatory macrophages. Clinical research confirms that this mechanism of action reduces the physiological stress on the subchondral plate. In advanced regenerative practices like Vega Stem Cell, precision targeting ensures these exosomes reach the exact point of structural failure. Theoretically, this paracrine effect prevents the further progression of sclerosis, allowing the joint to stabilize structurally rather than continue its rapid deterioration.
While most literature heavily focuses on the knee, The Subchondral-First Regenerative Approach is absolutely critical for treating complex axial and appendicular joints. Conditions involving the hip and spine feature identical bone-level pathology, requiring precision biological interventions rather than generalized surface therapies. Surgical intervention should always be reserved for catastrophic mechanical failure, not utilized as a first-line defense against modifiable biological inflammation.
The hip is a deep, tightly encapsulated ball-and-socket joint, making it notoriously difficult to treat conservatively. Acetabular subchondral sclerosis develops under the cartilage of the pelvic socket (the acetabulum) and the femoral head.
In the hip, the labrum acts as a critical suction seal. Once that seal tears or impingements alter the joint mechanics, synovial fluid pressure fluctuates wildly. This hammers the underlying acetabular bone, rapidly accelerating subchondral sclerosis. Because of the hip’s extreme mechanical depth, generic “hip injections” usually only deliver corticosteroids into the joint space, temporarily masking pain while completely failing to address this underlying bone stress.
Fluoroscopically guided subchondral stem cell injections bypass this capsule restriction. Acetabular subchondral sclerosis and spinal endplate sclerosis represent high-stress bone responses that can be targeted via fluoroscopically guided stem cell injections Orthopedic literature. By targeting the bone marrow lesions in the femoral head and acetabulum directly, clinicians address the mechanical root of the dysfunction, offering a viable alternative to early total hip arthroplasty.
The massive weight-bearing demands on the human spine result in comparable subchondral pathology. In the spine, the subchondral bone separating the vertebral body from the intervertebral disc is called the vertebral endplate. The endplates must balance immense axial loads while providing essential nutrients to the avascular intervertebral discs.
Endplate sclerosis spine treatment involves addressing Modic changes (specifically Type 1 edema and Type 2 fatty replacement) active, inflammatory bone marrow lesions adjacent to degenerating discs. When the disc loses height and hydration, the endplates grind together, causing severe vertebrogenic low back pain. Standard epidural steroid injections primarily target nerve roots; they do absolutely nothing for the inflamed bone. Regenerative therapies are currently being utilized to treat this bone-disc interface directly, injecting biologics into the vertebral endplate to modulate the deep inflammation causing the chronic, debilitating back pain.
Orthopedic studies indicate that chronic, localized joint pain frequently stems directly from subchondral pathology highlighting the critical need for advanced intra-osseous interventions in hip and spine care (PubMed).
For patients with severe subchondral lesions across these joints, orthopedic surgeons often push surgical alternatives. Choosing between mechanical stabilization and biological modulation requires rigorous clinical assessment, imaging review, and realistic expectation management.
Subchondroplasty is a surgical procedure where a calcium phosphate bone substitute (bone cement) is injected into the bone marrow lesion to structurally fill and harden it. It’s an invasive, permanent mechanical fix. However, injecting rigid cement alters the natural elasticity of the bone, which can inadvertently increase stress on adjacent cartilage or spinal segments. Stem cell therapy for subchondral sclerosis, conversely, is a biological intervention aimed at cellular tissue modulation without destroying native architecture.
Regenerative medicine isn’t a universal magic wand for joint pain. A responsible clinic relies on strict evidence-informed protocols and rigorous suitability assessments to ensure patient safety and realistic expectations. The treatment workflow for subchondral stem cell injections follows a highly standardized, non-negotiable clinical pathway designed to filter out patients who require traditional surgery.
If you are considering subchondral sclerosis treatment globally, understanding the exact procedural steps protects you from sub-standard medical care. A legitimate regenerative clinic will never skip the advanced imaging review or rely solely on outdated X-rays.
The safety of receiving stem cell treatments in Thailand or any other international medical hub hinges entirely on the precision of Step 4. Blind injections into the bone are dangerous and profoundly ineffective; real-time image guidance is absolutely mandatory for clinical success.
Not every patient who completes Step 1 will be approved for Step 4. Clinical integrity demands turning away unsuitable candidates to preserve high efficacy rates.
In clinical suitability assessments at Vega Stem Cell, we evaluate patients using strict methodology-backed protocols to determine if the biological foundation can still support cellular modulation. This involves a rigorous review of T2-weighted MRI sequences to confirm the presence of active edema. A good candidate possesses these active bone marrow lesions, localized pain that explicitly matches those precise imaging findings, a healthy BMI that limits excessive joint overload, and has exhausted conservative care options like physical therapy.
Conversely, you are likely not a suitable candidate if you have:
A consultation never guarantees eligibility. Clinical trial criteria consistently exclude patients with severe mechanical deformity because biological therapies cannot rebuild a completely destroyed architectural framework.
The primary symptom of subchondral sclerosis is deep, localized joint pain that noticeably worsens with weight-bearing activities. This pain is often accompanied by joint stiffness, a severely reduced range of motion, and localized inflammatory swelling. Because the bone has lost its native shock-absorbing capacity, patients frequently experience a deep, throbbing ache that feels structurally different from typical cartilage-related pain. In advanced cases, bone spurs (osteophytes) may also develop, further restricting mobility and function. A thorough clinical assessment is required to differentiate these symptoms from generalized osteoarthritis.
Subchondral sclerosis itself is simply a radiological finding on a chart, not a specific disability classification. However, the severe osteoarthritis and functional impairment associated with advanced sclerosis certainly can qualify as a disability if it severely limits daily activities and mobility. Determining formal disability status depends entirely on the specific joint affected, the documented loss of functional outcomes, and your local jurisdictional medical guidelines. For instance, severe acetabular sclerosis heavily impacting the ability to walk may meet disability criteria. Patients must discuss their specific physical limitations with a qualified clinician.
Yes, evidence-informed therapies strongly indicate that stem cells can help address bone marrow edema in the knee. When mesenchymal stem cells are injected directly into the subchondral bone, they actively modulate the local inflammatory microenvironment. This biological intervention precisely targets the active lesions driving the edema, promoting angiogenesis and vital tissue repair. Clinical data suggests this targeted approach yields vastly superior functional outcomes compared to standard intra-articular injections. Results will naturally vary based on the severity of the edema and strict patient suitability.
| 📌 If you’re interested in how MSCs calm overactive immune cells throughout the body, we have an interesting article that discusses mesenchymal stem cell therapy for immune modulation, which you can read via the internal link. |
For patients facing chronic joint degeneration, addressing subchondral sclerosis is structurally critical. A 2025 review of 298 knees clearly demonstrated that stem cells injected directly into the bone statistically outperform standard joint space injections. Overlooking the bone marrow lesions while exclusively treating the cartilage practically guarantees continued joint deterioration and inevitable surgical intervention. The absolute best approach combines precise MRI evaluation, strict suitability assessment, and targeted subchondral delivery to address the root pathology.
The importance of The Subchondral-First Regenerative Approach cannot be overstated. Treating surface-level cartilage while ignoring the hardened, inflamed bone beneath it is a clinical half-measure. By targeting the bone marrow lesions, evidence-informed clinicians can directly disrupt the degenerative crosstalk causing your pain, offering a biological path forward that actually aligns with the physiological damage your MRI report is showing.
Take proactive control of your joint health today. Gather your comprehensive medical records, recent X-rays, and MRI imaging reports, and schedule a formal suitability assessment with a board-certified regenerative medicine specialist. Ask explicitly if you are a candidate for subchondral bone targeting before committing to irreversible surgical procedures.