Our Services
Others
- DFPP
- Shockwave
- IV Drip

This article is for educational purposes only and does not replace consultation with a qualified medical professional.
For individuals experiencing hair thinning or shedding, identifying the specific types of hair loss is the critical first step before considering advanced treatments like stem cell therapy. Hair loss presents in multiple forms. Some types resolve entirely on their own. Others are fiercely progressive and permanent.
Regenerative medicine specifically autologous Adipose-Derived Stem Cell (ADSC) therapy is primarily studied for genetic thinning and select, stable cases of autoimmune alopecia. It isn’t a magic fix. It is entirely unsuitable for conditions involving active scarring.
This clinical guide breaks down the different types of alopecia. We’ll identify exactly which conditions may respond to clinical stem cell support in Thailand, and which absolutely will not.
Understanding the specific types of hair loss is necessary to determine if regenerative therapies may support follicles.
Visual patterns provide the very first clue to your diagnosis. It isn’t just about counting hairs in the shower drain. It’s about where they fall from, how fast they drop, and what the skin underneath looks like. Assessing these factors accurately can save you thousands of dollars in inappropriate treatments.
If you are asking, “what type of hair loss do I have,” start by assessing the geographic pattern on your scalp. Thinning strictly at the crown or a receding hairline heavily points to genetic pattern loss. You might also notice a widening part line, which is a classic indicator of female pattern thinning. Conversely, diffuse thinning across the whole scalp where your ponytail suddenly feels half as thick suggests a shedding disorder.
Speed matters, too. Sudden onset shedding usually points to a systemic trigger like extreme stress or illness. Gradual thinning over years is the hallmark of hormonal and genetic factors.
Normal-looking scalp skin is a good sign. It generally means the follicles, though perhaps dormant, aren’t being actively attacked by your immune system. But if you see smooth, shiny patches, localized redness, flaky buildup around the hair shaft, or actual scarring, you are looking at red flags for cicatricial (scarring) conditions.
If uncertainty exists, seeing a dermatologist is mandatory before booking any procedures. A clinical diagnosis using trichoscopy is the only definitive method to confirm if hair follicles are dormant or dead (American Academy of Dermatology, 2024). Only then can you determine if you are an ideal clinical candidate for cellular therapies.
Navigating a medical diagnosis requires seeing the full picture quickly. Not all alopecia operates by the same biological rules.
To help frame your clinical expectations, here is how the primary diagnoses break down regarding their permanence and potential responsiveness to advanced cellular support.
| Type of Hair Loss | Who it Affects | Temporary vs Permanent | First-Line Treatment | May Stem Cells Help? |
| Pattern Loss | Men & Women | Progressive | Minoxidil/Finasteride | Yes (Early/Moderate) |
| Telogen Effluvium | Mostly Women | Temporary | Time/Trigger Removal | Not Necessary |
| Alopecia Areata | All Ages | Unpredictable | Corticosteroids/JAKs | Potential (Stable cases) |
| Traction Alopecia | Mostly Women | Depends on stage | Remove tension | Yes (If early) |
| Scarring Alopecia | Adults | Permanent | Immunosuppressants | Not Suitable |
These categories aren’t just clinical labels. They dictate your entire biological timeline. Alopecia areata affects approximately 2% of the global population at some point in their lifetime (NHS Hair Loss Guidelines, 2023). Yet, treating it requires a vastly different approach than treating stress-induced shedding. We classify these types of alopecia primarily by whether the underlying follicle remains biologically alive.
Clinical reviews reveal a common reality: patients frequently think their hair is gone forever when it’s simply resting. Conversely, specialists routinely see patients hoping to regrow hair on smooth scar tissue. The biological distinction here is absolute, and properly diagnosing the cellular state dictates the entire medical intervention path.
Temporary hair loss defines conditions where the hair follicle remains alive but sits dormant. Think of a bear in hibernation. The biological machinery is intact. The blood supply exists. The follicle is simply stuck in the resting (telogen) phase of the hair cycle, conserving energy while the body diverts resources elsewhere.
Clinical evidence demonstrates that the vast majority of acute shedding cases resolve naturally meaning aggressive cellular interventions are rarely required for these patients.
When you ask is hair loss permanent or temporary, the answer hinges entirely on cellular viability. If the follicle is alive but sluggish, regenerative therapies like Adipose-Derived Stem Cells (ADSC) may help support the local microenvironment, encouraging the hair back into the active growth phase by upregulating local signaling proteins.
| 📌 If you’re interested in why the percentage of living cells matters so much at the time of treatment, we have an interesting article that discusses the importance of cell viability in UC-MSC stem cell therapy, which you can read via the internal link. |
Permanent hair loss means the follicle is destroyed. It is dead. The body replaces that tiny anatomical structure with dense, fibrotic scar tissue, primarily composed of rigid collagen. Once this fibrotic transformation occurs, the skin surface becomes visually smooth and shiny.
Once scar tissue forms, no amount of ADSC therapy, laser light, or topical serum will bring that specific hair back. Early intervention is critical to catch conditions before a struggling, dormant vs dead follicles situation tips over into permanent necrosis.
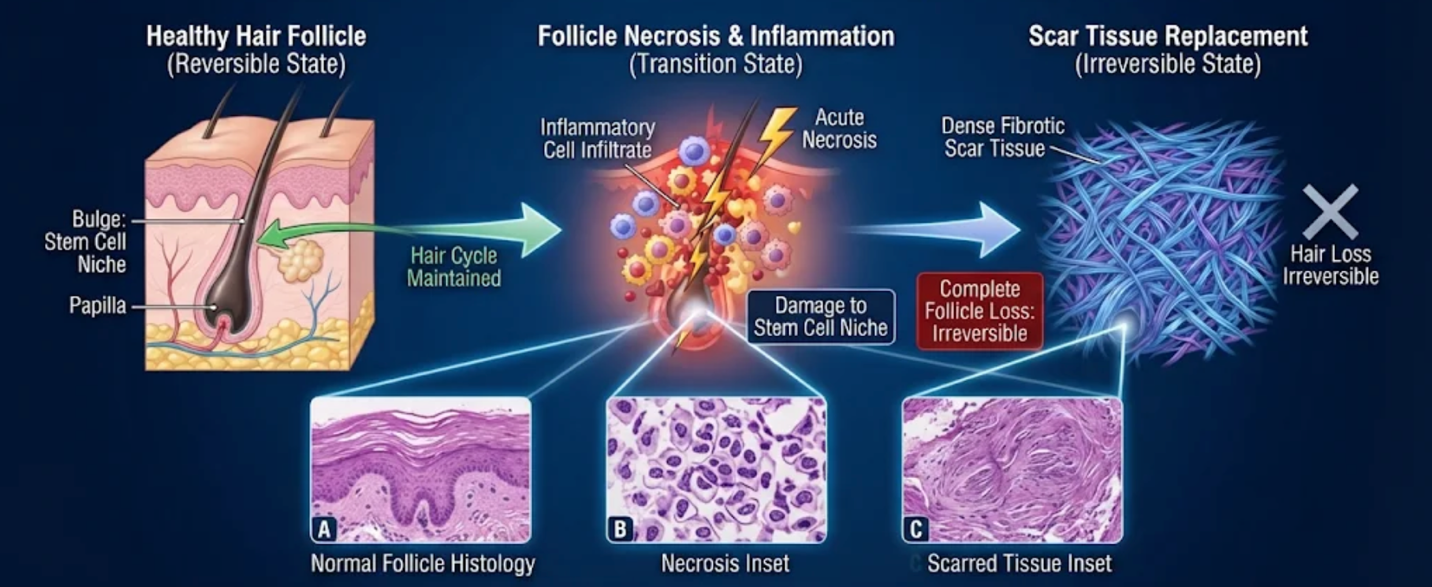
Figure 1: Once a follicle undergoes necrosis and is replaced by scar tissue, the hair loss becomes completely irreversible.
Androgenetic alopecia pattern hair loss is the most common genetic and hormonal cause of thinning worldwide. It affects both men and women, though it manifests differently across genders.
Pattern loss doesn’t happen overnight. It’s a slow, insidious process called follicular miniaturization. Dihydrotestosterone (DHT) binds to susceptible follicles, causing them to shrink with each successive hair cycle. The hairs become shorter, finer, and lighter in color.
First-line medical therapies remain topical minoxidil and oral finasteride or dutasteride. But these medications require strict daily compliance, and some patients simply don’t tolerate them well. This is particularly true for female pattern thinning, where hormonal treatments carry different risk profiles.
This is exactly where regenerative medicine enters the conversation. In early to moderate stages of androgenetic alopecia, before the follicle is fully lost, clinical female pattern treatments utilizing autologous ADSC therapy may support follicles by enhancing local microcirculation and upregulating cellular signaling directly around the miniaturized hairs.
Research published in Stem Cells Translational Medicine (Tak et al. (2020)) indicates that adipose-derived stem cell extracts show measurable efficacy in supporting hair density for genetic thinning. The cells are harvested from your own fat tissue, processed, and reintroduced to the scalp to optimize the growth environment.
When your immune system mistakenly identifies your hair follicles as foreign invaders, the result is alopecia areata.
This condition causes sudden, totally smooth, round patches of hair loss. It can happen on the scalp, the beard, or even involve the entire body in extreme cases (alopecia universalis). Because it is an autoimmune disease, the severity and frequency of flare-ups are notoriously unpredictable.
| 📌 If you’re interested in how MSCs calm overactive immune cells throughout the body, we have an interesting article that discusses mesenchymal stem cell therapy for immune modulation, which you can read via the internal link. |
For severe, rapidly progressing cases, dermatologists rely on advanced pharmaceuticals. Recent FDA approvals (2022, 2023) of JAK inhibitors like baricitinib and ritlecitinib have dramatically shifted the treatment protocol for severe alopecia areata, suppressing the immune attack effectively.
Can regenerative therapy play a role here? Sometimes, but timing is everything.
When the autoimmune attack is active and raging, injecting stem cells isn’t the answer. The immune system must be quieted first. However, when the condition is clinically stable—meaning no new patches have formed for several months—using ADSC or skin-derived therapies may have a potential role in waking up the dormant follicles. But be clear: it is not a first-line alopecia areata treatment.
Diffuse shedding terrifies patients because the volume of hair falling out daily is visually alarming. But clinically? Diffuse shedding is often the most reversible form of hair loss, provided the root trigger is accurately identified and managed.
Understanding stress hair loss vs genetic hair loss saves immense anxiety. Telogen effluvium (stress shedding) is strictly trigger-based. It physically shifts the follicular life cycle. Instead of the normal 10% of hair resting, up to 30% or even 50% prematurely enter the telogen phase. This massive biological shift causes widespread thinning, especially noticeable when washing or brushing. It typically occurs roughly two to three months after a severe physical or emotional shock like major surgery, a severe fever, massive weight loss, or intense psychological trauma.
Genetic thinning, conversely, is gradual and localized. The good news? Telogen effluvium usually resolves naturally within six to nine months as the biological stressor clears the system. You generally do not need cellular therapies for telogen effluvium; you just need time, proper nutrition, and patience.
Postpartum shedding is entirely normal and driven strictly by endocrine shifts. During pregnancy, elevated estrogen keeps hairs artificially locked in the growth phase, making your hair look thicker than ever. After childbirth, estrogen levels plummet, and all that retained hair sheds at once.
This dramatic hormonal crash can feel terrifying, but it represents a return to baseline, not a permanent loss. If you are looking for a postpartum hair loss treatment, the clinical advice is usually simple observation. Shedding peaks around three to four months post-delivery and stabilizes by your baby’s first birthday. Explicitly: stem cell therapy is not recommended for women currently breastfeeding, nor is it biologically necessary for this temporary condition.
Can thyroid hair loss grow back? Yes, but only if the systemic medical issue is actually corrected at the endocrine level.
Before even considering advanced therapies, mandatory blood panels must check your thyroid stimulating hormone (TSH), ferritin (iron stores), and Vitamin D. Ferritin is a critical co-factor for DNA synthesis in the hair matrix. If your ferritin is sitting at 12 ng/mL, your hair will not grow properly. Period. No advanced cellular procedure in Thailand or anywhere else can override a severe systemic nutritional or hormonal deficiency. You must fix the internal soil before treating the surface.
| 📌 If you’re planning treatment in Thailand and want a practical checklist for choosing a safe clinic, we have an interesting article that discusses whether stem cell therapy is safe in Thailand, which you can read via the internal link. |
Mechanical stress on the hair follicle creates its own distinct category of hair loss, completely separate from genetics or internal health.
Traction alopecia is caused by constant, pulling tension. Tight ponytails, heavy extensions, tight braids, or dreadlocks physically stress the follicle unit. Over time, this constant mechanical strain induces inflammation in the scalp, weakening the hair shaft and pulling the follicle slightly out of its natural dermal alignment.
It commonly affects the frontal hairline and the temples.
Patients constantly ask: can traction alopecia grow back? The answer heavily depends on your timeline.
In the early stages, simply removing the tension allows the inflammation to subside, and the follicles will usually recover on their own. However, prolonged tension over years causes permanent follicular scarring. According to mechanical stress guidelines from the British Association of Dermatologists, if the area is completely smooth and shiny, the damage is likely permanent. For early-stage recovery, ADSC therapy can be used as an effective traction alopecia treatment to reduce localized inflammation and support tissue repair.
Cicatricial (scarring) alopecia represents the most urgent, aggressive category of hair loss. It requires immediate medical attention, not cosmetic clinic visits.
Scarring alopecia destroys the hair follicle entirely, replacing it with dense scar tissue. Warning signs include severe itching, a burning sensation, pain, and noticeable redness or scaling around the hair base. Patients often describe a deep, uncomfortable “crawling” feeling on their scalp before the hair actually falls out.
Can scarring alopecia be reversed? No. Destroyed follicles cannot grow back. The singular goal of any proper scarring alopecia treatment is to halt the inflammatory progression and save the hair you currently have. Once the skin is scarred and shiny, the damage is strictly permanent. Your body essentially seals over the space where the follicle used to be with fibrotic collagen.
Women over 50 frequently present with a slowly receding frontal hairline, often accompanied by the highly specific symptom of losing their eyebrows. This is classically Frontal Fibrosing Alopecia (FFA), a variant of lichen planopilaris.
Effective frontal fibrosing alopecia treatment requires heavy-hitting dermatological management often involving intralesional corticosteroid injections, topical calcineurin inhibitors, or oral systemic medications. This is an active medical disease requiring a specialized dermatologist. Delaying pharmaceutical care in favor of cosmetic serums allows the permanent scarring to advance further into the hairline.
What about stem cell therapy for scarring alopecia? The clinical consensus is highly cautious.
While some small-scale studies have explored autologous fat grafting to manage the intense scalp inflammation seen in these conditions, it remains strictly investigational. Researchers are exploring if the anti-inflammatory properties of adipose tissue can calm the hostile scalp environment and reduce the localized burning sensations. The Cicatricial Alopecia Research Foundation notes that while cellular therapies might alter the inflammatory microenvironment, they cannot resurrect dead follicles. We do not use stem cells as a primary treatment for active scarring.
Regenerative procedures in Thailand primarily utilize autologous Adipose-Derived Stem Cells (ADSC) or skin-derived cells to support existing, viable follicles. We absolutely do not use umbilical cord-derived MSCs for these specific hair protocols due to regulatory and efficacy standards.
Not every condition warrants a cellular approach. Here is the evidence-informed breakdown of which type of hair loss can stem cells treat effectively, offering a transparent framework for patients considering travel.
| Suitability Level | Hair Loss Conditions | Clinical Rationale |
| Suitable | Early to moderate genetic pattern hair loss. | ADSCs support viability in miniaturized, dormant follicles. |
| Potential/Maybe | Stable alopecia areata; early traction alopecia. | May help optimize the local scalp microenvironment if tension/autoimmunity is removed. |
| Not Suitable | Active scarring; untreated thyroid issues; completely bald skin. | Cannot regenerate dead follicles; cannot override systemic deficiencies. |
This therapy is a biological support mechanism, not an overnight miracle. According to cellular therapy mapping by Gentile & Garcovich (2019), ADSC efficacy relies on treating follicles that are still alive. This Revolutionary Approach Thailand utilizes your body’s own adipose tissue to extract stromal vascular fraction cells, which are then precisely reintroduced into the thinning areas of your scalp.
The main types of hair loss include androgenetic alopecia (genetic pattern loss), telogen effluvium (stress shedding), alopecia areata (autoimmune patches), and scarring alopecia. Pattern loss is the most common form globally, driven largely by genetics and hormones. Identifying the exact type via trichoscopy is necessary because treatments vary drastically. Medical evaluation determines whether the condition is temporary or progressive, allowing clinics to build targeted care plans. (American Academy of Dermatology, 2024).
Hair loss is permanent when the hair follicle is completely destroyed and replaced by scar tissue, as seen in cicatricial alopecia. In contrast, conditions like telogen effluvium or early genetic thinning involve dormant but living follicles. As long as the biological machinery survives, there is hope for recovery. If the follicle is alive, regenerative therapies or medications may help support regrowth. Consult a specialist for a definitive assessment.
Stem cell therapy is generally not suitable as a primary treatment for active scarring alopecia. Once a follicle is destroyed by scar tissue, it cannot be regenerated. While some investigational research uses adipose-derived cells to manage inflammation, conventional dermatological medications remain the standard of care to halt progression. Patients must act quickly when symptoms first appear to preserve their existing hair. (Cicatricial Alopecia Research Foundation).
Early traction alopecia can grow back if the mechanical tension on the hair is completely removed. Changing hairstyles immediately gives the inflamed tissue a chance to heal. However, prolonged tension over years causes permanent follicle damage and scarring. In these advanced stages, the hair loss becomes irreversible. Early intervention is the most critical factor for recovery.
Postpartum hair loss typically resolves on its own without medical treatment. Shedding peaks approximately three to four months after childbirth as hormone levels stabilize. The hair usually regains its normal density within a year, making intervention unnecessary. Advanced therapies like stem cell treatments are not required and are not recommended during breastfeeding. (NHS, 2023).
Genetic hair loss occurs gradually over years in a predictable pattern, such as a receding hairline or thinning crown. Stress hair loss (telogen effluvium) happens suddenly, causing diffuse shedding across the entire scalp 2-3 months after a triggering event. A doctor can confirm the diagnosis using clinical scalp examination and trichoscopy.
Early to moderate androgenetic alopecia (pattern hair loss) generally shows the most potential response to stem cell therapy. Regenerative therapies utilizing adipose-derived cells may help support the viability of miniaturized, dormant follicles. It is ineffective for completely bald areas where follicles have died. (Tak et al., 2020).
Yes, comprehensive blood tests are mandatory before initiating advanced hair loss treatments. Tests check for underlying health conditions like thyroid dysfunction, iron deficiency (ferritin), and vitamin D levels. If a systemic deficiency is causing the shedding, regenerative therapies will not be effective until the underlying medical issue is resolved.
For individuals experiencing hair thinning, diagnosing the specific condition is absolutely critical. Early genetic pattern loss may benefit from Adipose-Derived Stem Cell therapy, whereas active scarring alopecia requires immediate conventional medical intervention. Accurate diagnosis dictates clinical success. (Gentile & Garcovich, 2019). The best approach combines thorough diagnostic blood panels, high-resolution trichoscopy, and targeted, evidence-based cellular support when appropriate.
The Stem Cell Suitability Matrix makes this complex biological reality simple to grasp. Understanding whether your follicles are dormant or permanently dead ensures patients avoid ineffective, expensive treatments and set highly realistic clinical expectations.
Schedule a consultation with a specialized hair restoration clinic in Bangkok today to establish a definitive diagnosis via trichoscopy and a clinical ADSC suitability assessment.