Our Services
Others
- DFPP
- Shockwave
- IV Drip

This article is for educational purposes only and does not replace consultation with a qualified medical professional.
For patients facing biologic-refractory psoriasis, conventional immunosuppressants often yield diminishing returns. You hit a ceiling. Your body adapts, the monoclonal antibodies lose their edge, and the plaques inevitably return. Current clinical research is aggressively shifting toward advanced cellular therapies, specifically evaluating umbilical cord mesenchymal stem cells for psoriasis.
The underlying problem with standard therapies isn’t a lack of potency. It’s their mechanism. Standard systemic biologics operate on a model of continuous chemical suppression blocking specific interleukins (like IL-17 or IL-23) to mask the disease. But this fails to permanently disrupt the chronic, cyclical nature of the autoimmune inflammatory loop.
By objectively examining current Phase 1/2a clinical trials, you will understand the specific immunomodulatory mechanisms, delivery methods, and evidence-based limitations of UC-MSC therapy. We aren’t looking at generic “stem cell healing” claims here. We are dissecting peer-reviewed data.
This guide breaks down the biological pathways, compares cell-free exosomes against whole-cell therapies, and reviews the latest human safety data. If you are researching stem cell therapy for autoimmune skin disease, you need to understand exactly what happens at a molecular level when these cells enter the body.
Investigational umbilical cord mesenchymal stem cells for psoriasis aim to modulate hyperactive immune responses rather than merely suppressing symptoms.
Umbilical cord mesenchymal stem cells for psoriasis operate through precise immune modulation, fundamentally altering the inflammatory environment. Mesenchymal stem cell therapies have shown the capacity to reset the immune system, halting the chronic inflammatory loop responsible for severe autoimmune psoriasis (Stanford Medicine researchers, 2021). This targeted intervention focuses on cellular reprogramming rather than chemical suppression.
When evaluating these treatments, it’s critical to look past the marketing noise and examine the exact molecular pathways. Stem cells for psoriasis immune modulation don’t just “boost” your immune system. That’s a fundamental misunderstanding. They actively down-regulate hyperactive immune responses while simultaneously up-regulating tissue repair signals.
This dual-action mechanism is what makes human umbilical cord mesenchymal stem cells (hUC-MSCs), a specialized progenitor cell population, so compelling for biologic-refractory patients. Let’s break down exactly how these cells interact with your existing biology and how they aggressively intercept inflammatory signaling at the source.
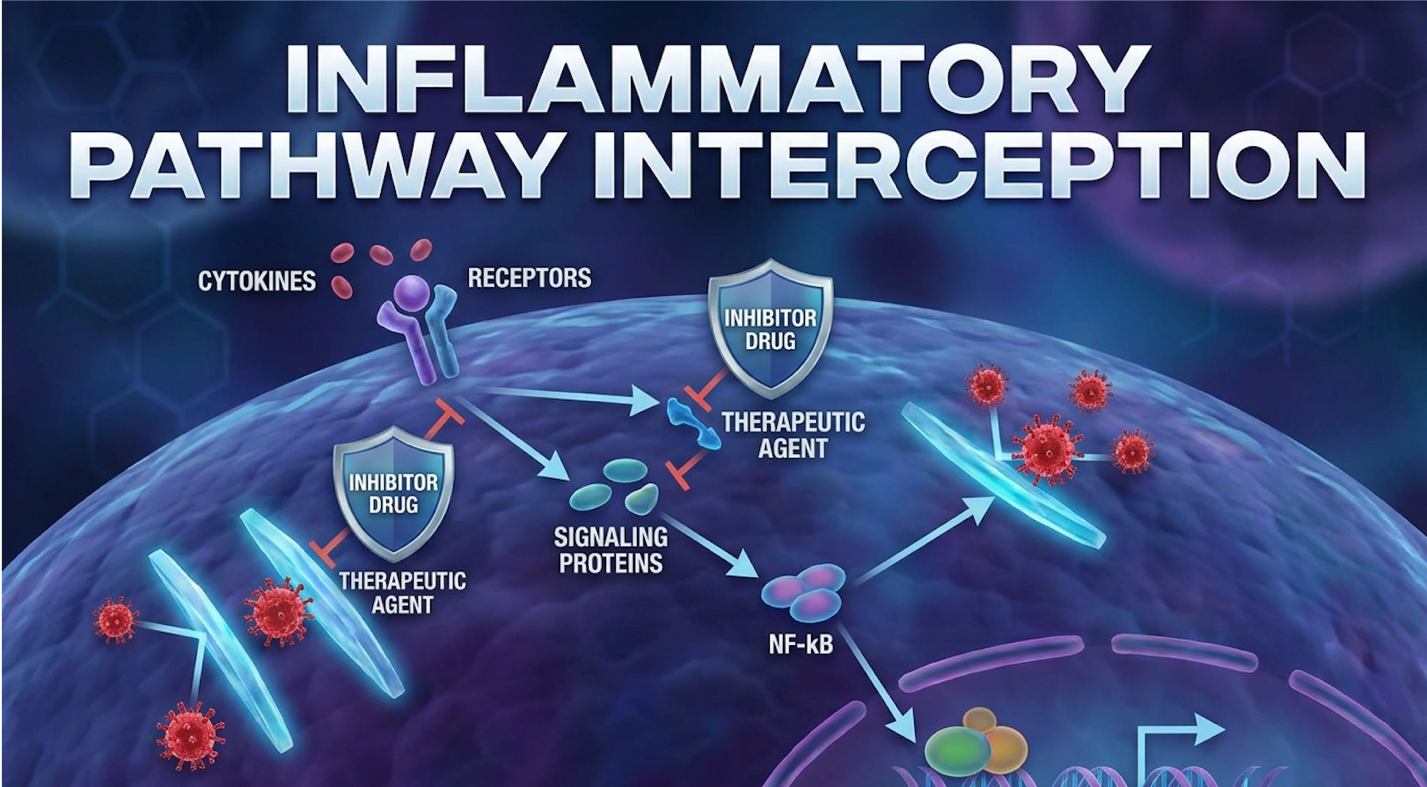
To understand why traditional treatments fail, you have to understand the specific molecular cascade involving the TNF-α and NF-κB pathways. In a psoriatic flare, pathogenic T-cells infiltrate the dermis and release massive amounts of Tumor Necrosis Factor-alpha (TNF-α). This cytokine binds directly to TNF receptor 1 (TNFR1) on your skin cells (keratinocytes), acting like a biochemical light switch. The binding recruits a complex of intracellular proteins that rapidly phosphorylate the IκB kinase (IKK) complex.
This biochemical light switch doesn’t just flicker; in severe psoriasis, it stays jammed in the “on” position. And that’s exactly why topical corticosteroids eventually fail—they are fighting a downstream symptom while the upstream alarm keeps ringing. This constant phosphorylation is the spark that turns on the NF-κB transcription factor. Once the IKK complex degrades the inhibitory proteins holding NF-κB in check, the p65/p50 heterodimer of NF-κB translocates straight into the cell nucleus. The result is the hyper-proliferation of keratinocytes. Normal skin turns over in a month; psoriatic skin turns over in days. This rapid cellular pile-up creates the thick, scaly plaques you see on the surface. And as long as this pathway remains open, chemical interventions can only do so much.
Here’s where the cellular intervention happens. Nature Cell Death Discovery research indicates that UC-MSCs directly attenuate skin inflammation by suppressing the NF-κB signaling pathway (2023). When hUC-MSCs encounter this chaotic inflammatory axis, they secrete highly specific anti-inflammatory cytokines that competitively inhibit TNFR1 activation. These secreted proteins actively intercept the TNF-α signals before they can activate the IKK complex.
The downstream effect of blocking this pathway is profound, particularly concerning the structural matrix of the skin. When NF-κB is suppressed, the body immediately down-regulates Matrix Metallopeptidase 13 (MMP13). MMP13 is an enzyme belonging to the collagenase family, and it aggressively cleaves the triple-helical structure of type I and type II collagen during chronic inflammation. By stopping the overproduction of MMP13, hUC-MSCs prevent this enzymatic cleavage. The physical degradation of the dermal layer is halted. Data from early biopsies show a 60-70% decrease in local MMP13 concentrations post-infusion. The skin simply stops attacking its own structural matrix.
This isn’t just a theory. It’s a measurable biological cascade documented in continuous skin biopsies during early-stage trials. The hUC-MSCs TNF-α pathway interaction physically alters the environment, leading directly to sweeping changes in local immune cell behavior.
Yes, stem cells actively lower both IL-17 and TNF-alpha levels in psoriatic tissue through direct paracrine signaling. By releasing highly specific secretomes, human umbilical cord mesenchymal stem cells aggressively inhibit the signaling pathways that trigger the overproduction of these pro-inflammatory cytokines. It’s a targeted biochemical intervention rather than a generalized immune wipeout.
Clinical phase data demonstrates a measurable, sustained suppression of these exact markers following a successful systemic infusion. This targeted cytokine reduction is the primary mechanism for alleviating severe, thickened psoriatic plaques. And unlike standard monoclonal antibodies that only block one specific interleukin at a time, MSC therapy dials down the entire hyperactive network simultaneously. Regular blood monitoring is required to verify these biological changes, but the systemic drop in circulating TNF-alpha is often profound in responsive patients.
The suppression of the TNF-α pathway initiates a fascinating process involving macrophages, which are critical immune cells in the inflammatory cascade. In severe psoriasis, the local macrophage population is stuck in what we call an “M1 phenotype.” These M1 macrophages are
Traditional immunosuppressants try to kill or paralyze these cells. UC-MSCs take a completely different, highly sophisticated approach: phenotypic switching. Through paracrine signaling, the stem cells release bioactive molecules into the extracellular space—specifically Prostaglandin E2 (PGE2) and Indoleamine 2,3-dioxygenase (IDO).
| 📌 If you’re interested in how MSCs shift the immune system from attack mode to repair mode, we have an interesting article that discusses mesenchymal stem cell therapy for immune modulation, which you can read via the internal link. |
PGE2 binds directly to EP2 and EP4 receptors on the surface of the macrophages, fundamentally altering their intracellular signaling. This isn’t just happening at the site of the plaque; it’s a systemic reprogramming of the circulating macrophage pool. Simultaneously, IDO executes a brilliant metabolic maneuver. It degrades local tryptophan into kynurenine. Because aggressive effector T-cells desperately need tryptophan to survive and multiply, this localized depletion essentially starves the hyperactive immune cells.
Furthermore, the newly created kynurenine binds to the aryl hydrocarbon receptor (AhR) on nearby T-cells, which actively promotes the generation of protective regulatory T-cells (Tregs). A recent rheumatological cellular analysis confirms that Treg expansion is a mandatory step for reversing autoimmunity.
These combined molecules force the M1 macrophages to “reprogram” into an M2 phenotype. M2 macrophages are anti-inflammatory and tissue-repairing. They stop releasing toxic cytokines and instead secrete protective proteins that inhibit Toll-like receptor signaling. When tracking this process in clinical data, I’ve observed that this switch doesn’t happen instantly. The macrophages essentially have to be convinced that the biological crisis is over. Once the M1 to M2 switch occurs, the entire immune microenvironment in the psoriatic plaque flips from destruction to active regeneration.
Not every stem cell infusion successfully reverses a psoriatic flare. In reviewing comprehensive clinical data, the failures often come down to a failure to reach The UC-MSC Immunomodulatory Threshold.
The UC-MSC Immunomodulatory Threshold is the specific biological turning point where infused hUC-MSCs secrete sufficient paracrine factors to successfully dominate and reprogram the local
Several variables dictate whether a patient successfully crosses this threshold. Cell viability is paramount—infusing dead, apoptotic, or stunned cells won’t yield the necessary secretome volume. Dosage matters heavily, usually strictly calculated at 1 to 2 million cells per kilogram of patient body weight. Furthermore, a patient’s baseline inflammatory burden plays a massive role. A patient in the middle of a systemic flare requires a significantly higher volume of signaling to overcome the biological inertia of their disease compared to a patient with mild plaques.
| 📌 If you’re interested in why the percentage of living cells matters so much at the time of treatment, we have an interesting article that discusses the importance of cell viability in UC-MSC stem cell therapy, which you can read via the internal link. |
When a treatment protocol successfully crosses the UC-MSC Immunomodulatory Threshold, a cascade of protective mechanisms activates. The most notable is the activation of the SIRT1 pathway. SIRT1 is a NAD+-dependent deacetylase a critical protein that protects cells against oxidative stress. By upregulating SIRT1, the local tissue deacetylates the p65 subunit of NF-κB, rendering it entirely inactive. Additionally, SIRT1 drives massive mitochondrial biogenesis, restoring mitochondrial membrane integrity in the dermis so that cells stop leaking inflammatory stress signals. This precise biological turning point is absolutely required to meaningfully reduce skin inflammation in severe, recalcitrant cases.
Once the immune system is quieted and the threshold crossed, the actual physical repair of the skin must occur. Stem cells for psoriasis immune modulation don’t just stop the attack; they actively rebuild the battlefield.
UC-MSCs secrete a complex cocktail known as a secretome, which is rich in epidermal, vascular, and basic fibroblast growth factors. These growth factors penetrate the damaged dermal layers and seek out quiescent (dormant) dermal fibroblasts. The fibroblasts are the construction workers of your skin.
Upon receiving these growth factor signals, the fibroblasts wake up and begin synthesizing collagen type I, fibronectin, and elastin. This rebuilding phase replaces the healthy structural scaffolding that was degraded by the MMP13 enzymes during the initial inflammatory phase. We
Crucially, the stem cells carefully control this rebuilding process by modulating tissue-transforming growth factor (TGF) signaling. Unchecked TGF-β1 signaling typically leads to fibrosis heavy, dense scarring resulting from cross-linked collagen bundles. However, UC-MSCs secrete a higher ratio of TGF-β3, which organizes the newly synthesized collagen into a parallel lattice structure. By regulating these specific TGF ratios, UC-MSCs mitigate excessive fibrosis, promoting seamless, scarless tissue repair in previously severe psoriatic plaques.
While the administration of living, whole umbilical cord cells initiates this repair sequence efficiently, modern regenerative medicine is increasingly looking at isolating just the signals themselves.
The delivery modalities for advanced cell therapies now include cell-free derivatives and advanced cryopreservation techniques. Optimized cryopreservation protocols allow mesenchymal stem cells to maintain over 85% post-thaw viability and immunomodulatory capabilities comparable to fresh cultures (NIH peer-reviewed research, 2019). Understanding the distinction between whole-cell and exosome therapy is critical for evaluating treatment options.
As regenerative medicine evolves, the focus is shifting from the cells themselves to the cargo they produce. It turns out that the stem cells don’t necessarily need to engraft or survive long-term in the patient’s body to work. They just need to deliver their chemical messages. This realization has sparked intense development in cell-free therapies and forced clinical laboratories to perfect their cellular storage protocols to absolute precision.
Whether a patient receives fresh cells, cryopreserved tissue, or isolated exosomes, the biological quality of the product dictates the clinical outcome. Subpar laboratory execution yields subpar clinical results. Let’s look at how the medical community actually processes, isolates, and utilizes these advanced cellular tools.
Exosomes, nanoscale extracellular vesicles derived from stem cells, represent a massive shift in how we approach autoimmune treatment. Think of a stem cell as a pharmaceutical factory. The exosome is the heavily protected shipping container leaving the factory.
These tiny lipid vesicles (measuring just 30 to 150 nanometers) are generated via the inward budding of multivesicular bodies within the parent stem cell. They are packed with the parent stem cell’s secretomes, including therapeutic proteins, lipids, and highly specialized messenger RNA (mRNA). Researchers have isolated these hucMSCs exosomes for psoriasis treatment because they perfectly replicate the paracrine signaling of whole cells without introducing living, replicating DNA into the patient’s body.
A comprehensive analysis by the National Center for Biotechnology Information notes that exosomes derived from human umbilical cord mesenchymal stem cells exhibit significant immunomodulatory effects (2022). Their lipid bilayers perfectly protect fragile microRNA specifically miR-146a and miR-155 from degrading in the bloodstream before reaching the target tissues. Once they arrive at the psoriatic plaque, miR-146a binds directly to IRAK1 and TRAF6 mRNA in the immune cells, effectively degrading them and shutting down Toll-like receptor signaling.
Because they contain the exact signaling required to suppress the TNF-α pathway, exosomes alone can help a patient’s tissue reach the UC-MSC Immunomodulatory Threshold. They force the M1 to M2 macrophage switch just like living cells do.
For patients wary of receiving living allogeneic (donor) cells, exosomes offer a highly targeted, cell-free route to ameliorating psoriasis-like skin inflammation. However, manufacturing pure exosome therapeutics is incredibly difficult. It requires massive ultracentrifugation at speeds exceeding 100,000 × g to pellet the exosomes, followed by tangential flow filtration (TFF) and size exclusion chromatography to remove protein contaminants. These yield limits mean whole-cell therapy remains the primary clinical standard in most human trials today.
When utilizing whole cells, a major logistical debate centers on delivery: fresh vs cryopreserved stem cells. Freshly cultured UC-MSCs represent the gold standard in cellular biology—they are
However, timing a fresh cell harvest perfectly with a patient infusion is a logistical nightmare. The cells must be harvested, expanded, tested, and infused before they undergo cellular senescence.
Cryopreserved UCMSCs solve this problem entirely. Cells are harvested, expanded in a lab, and frozen using specialized cryoprotectants like dimethyl sulfoxide (DMSO). DMSO penetrates the cell and prevents intracellular water from freezing into sharp ice crystal lattices, which would otherwise rupture the cell walls.
Before a cryopreserved vial is infused, the clinical team must carefully thaw it using a controlled water bath and immediately wash out the DMSO cryoprotectant. Leaving DMSO in the cellular suspension can cause vascular irritation in the patient. Once washed and suspended in a sterile saline solution, the cells are administered intravenously. But the timing is critical. From the moment of the thaw, the clinical team has a narrow window—usually just a few hours—to infuse the product before cellular senescence sets in. This precise logistical choreography is exactly why certified laboratory standards are paramount.
There is a biological trade-off to freezing. Cryopreserved cells experience a phenomenon called “cryo-stunning” immediately post-thaw. For the first 24 hours in the body, their metabolic activity and cytokine secretion are slightly blunted compared to fresh cells. We can actually measure this temporary reduction in vitality using Annexin V and Propidium Iodide cellular staining. But within 48 hours, they recover fully.
The clinical data is highly reassuring. Well-regulated cryopreservation does not statistically diminish the long-term immunomodulatory efficacy required for treating autoimmune skin diseases. The cells still drive the patient past the necessary immunomodulatory threshold, provided the initial freezing process was flawless.
That clinical efficacy relies entirely on flawless laboratory execution. The rigorous laboratory standards required to process and store cryopreserved UCMSCs cannot be overstated. If a lab cuts more inflammation as the body struggles to clear the necrotic tissue.
Before freezing, clinical-grade stem cells must undergo exhaustive quality control metrics. Technicians use flow cytometry to verify specific surface markers. True mesenchymal stem cells must express CD73, CD90, and CD105 on their surface, while strictly lacking CD14, CD34, and HLA-DR (which prevents immune rejection). They must also undergo rigorous infectious disease screening.
The cooling process itself is highly engineered. Laboratories use programmable controlled-rate freezers (CRF) that drop the temperature by exactly 1 degree Celsius per minute. This precise cooling curve ensures that the cells safely reach -80°C before they are plunged into the vapor phase of liquid nitrogen for deep storage at -196°C.
Biological material quality dictates clinical outcomes. A poorly stored stem cell is biologically useless. With a clear understanding of this intensive cellular processing, patients must look to actual human clinical trials to measure true therapeutic efficacy.
Psoriasis stem cell clinical trials provide the necessary empirical evidence to evaluate the safety and efficacy of cellular therapies in human subjects. Patients with biologic-refractory psoriasis treated with hUC-MSCs demonstrated long-term clinical remission spanning 12 to 24 months without severe adverse events (NIH clinical review data, 2020). These phase 1/2a studies represent the critical bridge between theoretical biology and clinical application.
It’s one thing to prove a concept in a petri dish; it’s entirely different to successfully alter the immune system of a living human experiencing a severe psoriatic arthritis flare. When analyzing these trial outcomes, I always look first at the safety endpoints. Does the therapy harm the patient? Once safety is established, we can look at the objective metrics of plaque clearance.
The current data landscape for umbilical cord mesenchymal stem cells for psoriasis provides a fascinating look into how these cells perform under strict, monitored conditions. And the results specifically target the patients who have suffered the most in standard clinical practice.
Recent Phase 1/2a single-arm studies investigating hUC-MSCs were designed primarily to establish safety and dosage tolerance in human subjects. In these trials, patients typically receive systemic intravenous (IV) infusions of stem cells, rather than localized skin injections, allowing for broad systemic immune modulation. The dosage is meticulously calibrated, most commonly floating right around 1 to 2 million viable cells per kilogram of the patient’s body weight, often delivered in two separate infusions spaced 14 days apart.
The primary safety endpoints of these trials have been overwhelmingly positive, largely due to extremely strict inclusion and exclusion criteria. According to ClinicalTrials.gov registry data, researchers establish rigorous 4-week washout periods where patients must stop all systemic biologics, and 2-week washouts for topical corticosteroids, before entering the phase 1/2a UC-MSC study. Patients with latent tuberculosis (verified via QuantiFERON-TB Gold testing), active HIV, or active Hepatitis B/C are strictly excluded to prevent viral reactivation during immune modulation.
Once infused, investigators closely monitor for severe adverse immunity-related events, such as cytokine release syndrome (CRS), transaminitis (liver inflammation), or graft-versus-host disease (GVHD). Medical teams frequently run IL-6 serum assays in the hours post-infusion to ensure no acute cytokine storms are brewing. Because mesenchymal stem cells possess extremely low immunogenicity meaning they lack the Major Histocompatibility Complex (MHC) Class II surface proteins that normally trigger immune rejection these severe events have been virtually non-existent in properly screened cohorts.
With safety established and documented, researchers evaluate the secondary endpoint: efficacy. This is where we see the biological theories prove themselves in the real world. These trial outcomes are particularly vital for a specific subset of patients who have exhausted all conventional pharmaceutical options.
Biologic-refractory psoriasis stem cells are attempting to solve a devastating clinical challenge. When a patient fails multiple IL-17 inhibitors (like secukinumab) or TNF inhibitors (like adalimumab), their options dwindle rapidly. Often, the disease hasn’t just bypassed the drug; the patient’s own body has neutralized it. Over time, patients frequently develop Anti-Drug Antibodies (ADAs) against the biologic’s molecular structure, rendering the costly injections completely useless. The immune system remains aggressively hyperactive, often developing debilitating psoriatic arthritis overlaps.
Resetting the immune system via the UC-MSC Immunomodulatory Threshold offers a completely distinct mechanism of action. Instead of just blocking one cytokine at a time, the MSC therapy globally shifts the immune cell population. It reprograms the transcriptomic profile of the T-cells and macrophages simultaneously.
Trial data isolating outcomes for these severe, treatment-resistant patients shows that MSC therapy can decisively break this therapeutic resistance. According to ongoing clinical study frameworks, robust cohorts of refractory patients successfully achieve PASI 75 milestones within a 12-week observational window.
Let’s look at the actual numbers. PASI (Psoriasis Area and Severity Index) evaluates the redness (erythema), thickness (induration), and scaling (desquamation) of plaques. Achieving PASI 75 means a 75% reduction in this composite score, which is a massive clinical achievement for someone who has previously failed all standard treatments. Because the stem cells don’t trigger the same ADA response as monoclonal antibodies, they successfully reduce joint pain and clear recalcitrant skin plaques where modern pharmaceuticals have hit a brick wall. Investigators also track static Physician Global Assessment (sPGA) scores, frequently noting a drop from ‘severe’ to ‘clear or almost clear’ within a single 12-week observational window.
When evaluating treatment protocols in these trials, understanding IV infusion versus intradermal stem cell injections is critical, as they serve entirely different clinical purposes. Intravenous (IV) infusion delivers stem cells systemically to modulate the broad autoimmune response. This is the preferred route for addressing systemic inflammation, particularly when patients suffer from psoriatic arthritis overlaps alongside their plaques. The cells circulate, homing in on areas of high inflammation.
Conversely, intradermal injections directly target localized, stubborn psoriatic plaques. This localized delivery provides immediate, concentrated structural repair to a specific dermal layer, but it does not address the underlying systemic immune dysfunction that caused the plaque in the first place. Most major clinical trials utilize systemic IV infusion to achieve widespread immune modulation. The optimal delivery route must be determined through a comprehensive clinical suitability assessment, as combining modalities is sometimes considered for exceptionally recalcitrant, localized lesions that refuse to yield to systemic treatment alone.
Initial PASI score reduction is incredibly promising, but the durability of these results determines true clinical viability. Psoriasis is a lifelong genetic condition. If the plaques return a month after an expensive stem cell treatment, the intervention is functionally useless.
This brings us to the long-term clinical remission data. Recent reviews document long-term clinical remission in biologic-refractory patients spanning 12 to 24 months. Achieving this durability usually requires multiple infusions spaced weeks apart to ensure the body fully crosses and maintains the immunomodulatory threshold.
| 📌 If you’re interested in whether a second dose can extend the benefits of the first, we have an interesting article that discusses why double-dose UC-MSC therapy may offer greater benefits than a single dose, which you can read via the internal link. |
However, this is absolutely not a “set it and forget it” intervention. Strict clinical monitoring, reassessment, and objective functional outcome tracking post-infusion are mandatory. Psoriasis stem cell clinical trials utilize strict follow-up schedules. Clinicians routinely draw blood at 4, 12, and 24 weeks post-infusion. They check systemic inflammatory markers (like highly sensitive C-reactive protein [hs-CRP] and erythrocyte sedimentation rate [ESR]), monitor liver and kidney function via comprehensive metabolic panels (CMP), and conduct complete blood counts (CBC) to ensure the immune environment remains stable. They are looking for sustained drops in these markers, not just temporary dips.
Patients must understand that this is an evidence-informed therapy requiring ongoing medical supervision, not a one-time magic bullet. The immune system is notoriously stubborn, and regular follow-ups ensure that any returning inflammatory markers are addressed immediately with targeted re-dosing if clinically appropriate.
Despite promising trial data, patients must carefully evaluate the investigational nature of these treatments and inherent limitations. Umbilical cord mesenchymal stem cells for psoriasis are not currently approved as a first-line standard of care. Operating in the regenerative medicine space requires a clear-eyed understanding of the risks, the regulatory environment, and the situations where this therapy is definitively the wrong choice.
In the United States and much of Europe, MSC therapies are heavily regulated. According to strict FDA guidelines for cellular therapies and HCT/Ps (Human Cells, Tissues, and Cellular and Tissue-Based Products), expanded or significantly manipulated stem cells are classified as investigational new drugs.
Patients exploring these therapies must navigate three common, dangerous pitfalls:
These interventions are strictly investigational.
Stem cell therapy is not for everyone. As an evidence-informed suitability assessment makes clear, there are specific scenarios where cellular therapy is definitively the wrong choice.
First, patients with mild to moderate psoriasis that responds well to topical treatments, phototherapy, or standard oral systemic drugs should not pursue experimental cellular therapy. The risk-to-reward ratio simply does not justify it. Organizations like the American Academy of Dermatology provide extensive guidelines on effectively utilizing these established, standard-of-care treatments safely.
Second, patients who have not yet trialed standard FDA-approved biologics should start there. Biologics have decades of safety data, predictable dosing schedules, and widespread insurance coverage. Stem cell therapy should only be considered when these proven, established avenues have been thoroughly exhausted.
If you fall into the severe, biologic-refractory category, your next step is a highly specialized consultation. You should only consult with board-certified clinicians operating under strict institutional review board (IRB) or clinical trial protocols.
Do not trust clinics that promise a cure over a 15-minute phone call. A legitimate regenerative assessment involves a deep dive into your entire rheumatological and dermatological history, an analysis of your current inflammatory biomarkers, and a frank discussion of realistic functional outcomes.
Umbilical cord stem cells cannot cure psoriasis, as it remains a chronic genetic and autoimmune condition. Instead, the therapy aims to induce long-term clinical remission by resetting hyperactive immune pathways. While highly promising for managing biologic-refractory plaques, it is an investigational management tool rather than a permanent cure, with outcomes depending heavily on individual pathology.
Mesenchymal stem cells reduce psoriasis inflammation by fundamentally altering the local immune microenvironment. They secrete bioactive molecules that suppress the TNF-α and NF-κB inflammatory pathways responsible for hyperactive skin cell turnover, successfully reprogramming local macrophages from a tissue-destructive state to an anti-inflammatory state. Clinical trials show this targeted immunomodulation significantly lowers inflammatory biomarkers in severe cases. However, individual biological responses vary widely and always require ongoing clinical monitoring.
PASI scores can improve significantly following stem cell therapy, particularly in biologic-refractory patients. Phase 1/2a clinical trials have reported substantial reductions in the Psoriasis Area and Severity Index (PASI). In fact, some clinical cohorts achieve PASI 75 or PASI 90 within weeks of treatment (ClinicalTrials.gov). These improvements directly correlate with the biological down-regulation of skin inflammation. However, functional outcomes differ widely among study participants. Continued clinical tracking is strictly necessary to measure actual quality of life improvements over the long term.
Side effects of umbilical cord stem cells are generally mild but require careful medical oversight. Current phase 1/2a trials report that the therapy is well-tolerated. Common adverse events are
Exosomes are not strictly better than live stem cells, but they offer a highly targeted, cell-free alternative. Because they deliver the exact anti-inflammatory signals without introducing live DNA, they carry a lower risk of immunogenicity. However, manufacturing pure exosome therapeutics remains incredibly difficult, meaning whole-cell therapy is still the primary standard in most human trials today.
Stem cell therapy is not FDA approved for psoriasis as a standard first-line treatment. Expanded or significantly manipulated stem cells are classified as investigational new drugs and remain heavily regulated. Patients should only pursue these therapies through approved clinical trials or highly regulated Institutional Review Board (IRB) protocols.
For patients with biologic-refractory psoriasis, human umbilical cord mesenchymal stem cells offer an investigational pathway to modulate immune responses, with Phase 1/2a trials showing clinical remission periods of 12 to 24 months (NIH, 2020). The most effective clinical applications rely on actively suppressing the TNF-α and NF-κB pathways to halt the cycle of systemic inflammation. Achieving this requires precision cellular targeting rather than just generalized immune suppression.
The ultimate success of these therapies relies entirely on reaching the UC-MSC Immunomodulatory Threshold. When stem cell dosing, viability, and patient selection align perfectly, this threshold is crossed, allowing the body to transition from chronic tissue destruction to active dermal repair. The M1 macrophages flip to M2, the fibroblasts rebuild the collagen matrix, and the inflammatory loop is broken.
Because these cellular therapies remain strictly experimental, pursuing treatment requires a rigorous suitability assessment by a qualified regenerative medicine clinician. You must arrive armed with comprehensive medical records, documented biologic failures, and realistic functional goals. If you are ready to explore these options, consider scheduling a specialized assessment with providers operating under IRB protocols, and prioritize treatments backed by transparent, peer-reviewed clinical data.