Our Services
Others
- DFPP
- Shockwave
- IV Drip

Orthotopic liver transplantation remains the absolute gold standard for patients surviving with decompensated liver failure. But let’s look at the clinical reality. Severe donor organ shortages mean thousands of patients deteriorate on waitlists every year. When standard pharmacological interventions fail to halt cellular senescence especially for patients battling liver destruction driven by hepatitis B (which is highly prevalent across Asia), chronic alcohol use, or metabolic fatty liver disease patients desperately need an alternative.
This analysis examines the rigorous clinical evidence surrounding umbilical cord stem cell therapy for liver cirrhosis. We aren’t looking at miraculous “cures” here. We’re strictly evaluating how these specific cells function at a molecular level, the exact laboratory markers they influence, and the rigid eligibility requirements for treatment. Our team evaluated the current clinical data to map out exactly what regenerative medicine can and cannot do for a failing liver.
We will break down the cellular mechanisms, track proven clinical efficacy, outline patient safety protocols, and examine the realistic costs of seeking this treatment in Bangkok.
This article is for educational purposes only and does not replace consultation with a qualified medical professional.
Stem cell therapy facilitates liver regeneration by interrupting the fibrotic cascade and modulating local immune responses. Rather than directly replacing damaged tissue like building blocks, umbilical cord mesenchymal stem cells (UC-MSCs) secrete bioactive molecules. These molecules stimulate the patient’s existing hepatocytes to repair structural damage. Can stem cell therapy help regenerate the liver? Yes, but this specific mechanism provides a measurable, functional pathway for managing end-stage liver disease rather than generating a brand-new organ overnight.
To understand how umbilical cord stem cells repair the liver, you have to abandon the old idea that injected cells simply turn into new liver cells. They don’t. The regenerative heavy lifting actually comes from the paracrine effect of mesenchymal stem cells in liver repair.
When infused, UC-MSCs release a highly concentrated cocktail of extracellular vesicles and bioactive molecules including epidermal, vascular, and basic fibroblast growth factors. These secretions directly target and inhibit hepatic stellate cells. In a diseased liver, hyperactive stellate cells are the primary culprits driving aggressive liver fibrosis. By forcing these stellate cells into a quiescent state, the stem cells effectively shut down the scar-tissue production line.
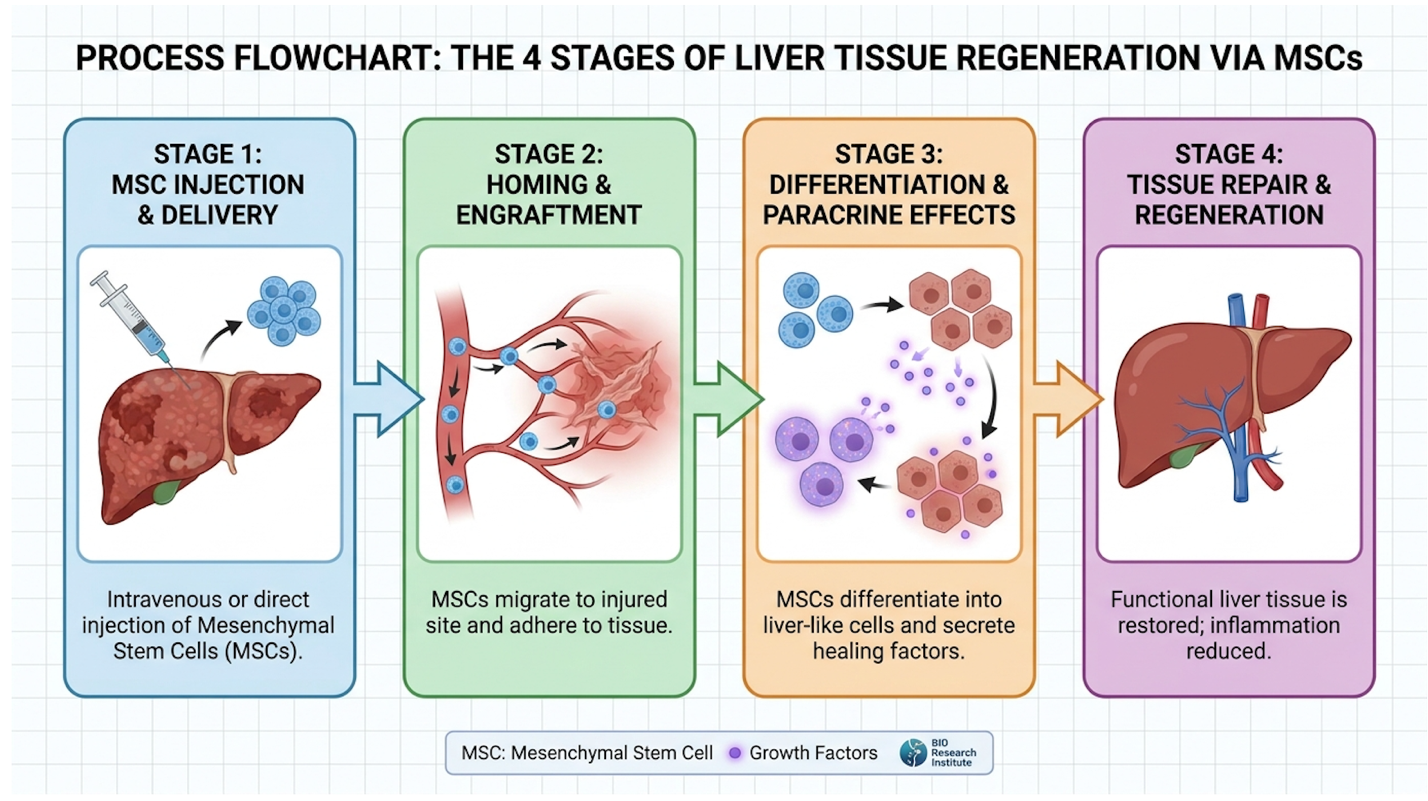
This signaling cascade also promotes the synthesis of healthy extracellular matrix proteins through the ERK MAPK signaling pathway. The National Institutes of Health (NIH) notes that these mechanisms of anti-fibrosis and immunoregulation in the liver are foundational to structural recovery.
While paracrine signaling directly addresses structural scarring, the simultaneous modulation of the patient’s immune system prevents further inflammatory damage.
The anti-inflammatory effects of uc-msc in liver disease are profound, particularly in cases of viral or toxin-induced damage. End-stage cirrhosis is characterized by a hostile, hyper-inflammatory microenvironment. UC-MSCs act as molecular peacekeepers through a process called phenotypic macrophage switching.
| 📌 If you’re interested in how MSCs shift the immune system from attack mode to repair mode, we have an interesting article that discusses mesenchymal stem cell therapy for immune modulation, which you can read via the internal link. |
They literally reprogram tissue-destructive M1 macrophages into tissue-repairing M2 macrophages. By inhibiting Toll-like receptor signaling and actively promoting the SIRT1 pathway, the therapy drastically reduces localized oxidative stress. This immunomodulatory shift is critical when dealing with stem cell therapy for hepatitis B cirrhosis or stem cell therapy for alcoholic liver cirrhosis, where chronic, unrelenting inflammation is the primary driver of tissue death. You can’t rebuild a house while it’s still on fire. UC-MSCs put out the immunological fire first.
Understanding these intense molecular changes naturally prompts a common clinical question regarding cellular longevity post-infusion.
How long do injected stem cells stay in your body? A massive misconception in regenerative medicine is that infused stem cells permanently move in and live forever in the host tissue.
The reality is a highly efficient “hit-and-run” mechanism. Once administered, umbilical cord mesenchymal stem cells for liver failure navigate to the site of injury, exert their massive therapeutic paracrine effects, and initiate systemic repair protocols. Afterward, the patient’s immune system gradually clears these cells over a period of several weeks to a few months. They don’t need to survive indefinitely because they have already fundamentally altered the host’s own cellular behavior.
These profound molecular changes, however, are only clinically valuable if they translate into measurable improvements in patient outcomes.
Stem cell therapy cannot completely cure decompensated liver cirrhosis, but it can significantly improve critical hepatic function markers. Can liver cirrhosis be cured by stem cell therapy? No. However, clinical data indicates that UC-MSC interventions effectively reduce Model for End-Stage Liver Disease (MELD) scores and alleviate severe symptoms like ascites and jaundice in specific patient populations. This clinical reality shifts the treatment approach from seeking an absolute cure to strategic, aggressive disease management. This data-first approach clearly demonstrates why measuring functional capacity outranks subjective symptom reports.
We have to address the cure myth head-on. Advanced liver disease involves permanent, highly chaotic structural architectural changes. Stem cells cannot magically “erase” dense fibrotic bands that have been hardening for decades.
How many years does stem cell therapy last? The therapeutic benefits usually sustain for several months up to a few years, depending heavily on the patient’s underlying condition, diet, and lifestyle. Because the cells are eventually cleared by the body, patients dealing with severe regenerative medicine for liver disease often require subsequent booster infusions to maintain their biological bridge. Top-tier medical travel facilities in Bangkok, such as Vega Stem Cell, actively emphasize this longitudinal approach to ensure ongoing biomarker stability over time.
| 📌 If you’re interested in whether a second dose can extend the benefits of the first, we have an interesting article that discusses why double-dose UC-MSC therapy may offer greater benefits than a single dose, which you can read via the internal link. |
Given these clinical realities, evaluating the safety profile and determining strict patient eligibility becomes the next mandatory step.
Patient safety in stem cell therapy depends entirely on rigorous clinical assessment and standardized administration protocols. Because UC-MSCs possess incredibly low immunogenicity, they rarely trigger severe graft-versus-host responses. But experimental procedures still carry inherent risks of localized reactions or unintended immune responses. What is the downside of stem cell therapy? It requires invasive delivery methods and precise hepatic staging. Suitability is ultimately determined by metabolic health, not just chronological age.
| 📌 If you’re interested in why umbilical cord cells are often preferred over bone marrow or fat-derived cells, we have an interesting article that discusses why UC-MSCs are superior to other stem cell sources, which you can read via the internal link. |
The debate between an iv infusion vs intrahepatic injection of stem cells for liver repair usually comes down to disease severity and clinical capability.
Systemic intravenous (IV) infusion is minimally invasive essentially mirroring a standard blood draw or saline drip. It allows for broad, systemic distribution of the cells, though some cells inevitably get trapped in the pulmonary first-pass (the lungs) before reaching the liver.
Targeted intrahepatic injections, conversely, require an interventional radiologist. Using ultrasound or fluoroscopic guidance, the physician threads a catheter directly into the hepatic artery or portal vein to deliver the cells right into the damaged organ. How painful is a stem cell injection? IV infusions are virtually painless. Intrahepatic procedures require local anesthesia and mild sedation, causing some post-procedural bruising or localized pressure.
The Mayo Clinic extensively documents potential risks and injection side effects associated with these advanced delivery routes.
However, not every patient with liver disease is a candidate for these specialized administration routes.
Am I too old for stem cell therapy? Chronological age is actually far less restrictive than your current metabolic health.
Who is a candidate for stem cell therapy for liver disease? Ideal candidates have decompensated cirrhosis or severe fatty liver disease but possess enough baseline organ function to actually respond to paracrine signaling.
There are hard contraindications. Patients with active malignancies (cancer) or severe, uncontrolled acute infections are instantly disqualified. Stem cells promote vascular growth; if you have an undetected tumor, the therapy could inadvertently accelerate its growth. This is why legitimate clinics require comprehensive metabolic panels, tumor marker screenings (like AFP), and Doppler ultrasounds prior to any infusion.
| Myth | Clinical Reality |
| “I’m over 70, so I don’t qualify.” | Biological age and metabolic stability matter more than the year you were born. |
| “The injections are excruciating.” | IV protocols are painless; intrahepatic delivery uses targeted local anesthesia. |
| “One injection lasts a lifetime.” | Benefits typically last 6 to 24 months, requiring ongoing monitoring and potential boosters. |
| “It’s a guaranteed cure for cirrhosis.” | It stabilizes biomarkers and reduces inflammation; it does not reverse dense structural scarring. |
The Pew Research Center has highlighted the gap between celebrity claims and scientific reality. What does Joe Rogan say about stem cell therapy? While podcast endorsements drive massive awareness, they often gloss over the rigid exclusionary criteria required for true patient safety.
Once a patient is deemed medically eligible, the final barrier to treatment is navigating the financial realities of global regenerative medicine.
Stem cell therapies for liver cirrhosis require substantial out-of-pocket investments because they are generally classified as investigational by regulatory bodies. Without standardized FDA approval for this specific indication, traditional health insurance providers uniformly deny coverage for these regenerative procedures. Patients must evaluate global treatment options with complete financial transparency and understand exactly what they are paying for.
How much does stem cell regeneration cost? If you are looking into stem cell therapy for liver disease in Thailand, you need to budget realistically.
High-tier, internationally accredited clinics in Bangkok generally charge between $5,000 and $25,000. This massive variance depends entirely on the cell count required (often 50 million to 200 million MSCs), the complexity of the administration protocol, and the number of days admitted.
These international medical travel packages usually bundle pre-treatment testing, cellular expansion in a GMP-certified lab, the infusion procedure, and post-treatment facility monitoring.
The heavy burden of these out-of-pocket costs is directly tied to the strict regulatory environment governing cellular products.
Will my insurance pay for stem cell therapy? The short, blunt answer is no.
The FDA currently only approves cord blood-derived hematopoietic stem cells for very specific blood cancers and immunological disorders. They do not approve UC-MSCs for hepatic cirrhosis. Because of this strict investigational classification, major health insurance carriers view the treatment as experimental.
The Harvard Stem Cell Institute frequently outlines estimated out-of-pocket costs and lack of insurance coverage for patients seeking off-label regenerative care. You should assume zero financial contribution from your standard health insurance policy.
Understanding both the financial and rigid medical realities leads directly to a vital assessment of the therapy’s absolute limitations.
Navigating regenerative medicine requires an objective view of where the science stops and surgical necessity begins. Stem cell therapy is a powerful tool, but treating it as a flawless panacea is dangerous.
The most dangerous pitfall we see is patients abandoning proven standard-of-care treatments. You cannot substitute targeted pharmacological management like antiviral therapy for Hepatitis B or strict dietary protocols for stem cell therapy for fatty liver disease with unproven cellular injections.
Furthermore, seeking unregulated treatments in strip-mall clinics that do not utilize GMP-certified laboratory safety standards or third-party cell validation exposes patients to massive bacterial contamination risks. The U.S. Food and Drug Administration (FDA) is incredibly clear regarding current FDA approval status for stem cell therapies, urging patients to avoid unvetted providers.
There is a hard clinical line where stem cell therapy vs liver transplant is no longer a debate.
Patients suffering from acute, fulminant liver failure or those presenting with excessively high MELD scores that guarantee immediate donor matching must prioritize orthotopic transplantation. In these severe scenarios, the liver’s architecture has collapsed beyond the point where paracrine signaling can rescue it. Transplantation remains the definitive, curative alternative. Stem cells are only a supportive biological bridge, never a permanent substitute for necessary surgical intervention.
Before boarding a flight for regenerative care abroad, a multidisciplinary team anchored by a board-certified hepatologist must review all patient imaging and lab work. Complex cases involving hepatorenal syndrome or advanced portal hypertension require expert oversight to ensure the introduction of fluid volume (via IV infusion) won’t inadvertently trigger severe cardiac or renal distress. Do not attempt to bypass traditional hepatology assessments.
Umbilical cord stem cells repair the liver by secreting bioactive molecules that reduce inflammation and halt tissue scarring. This process, known as paracrine signaling, stimulates the patient’s existing liver cells to regenerate rather than replacing them directly. Clinical data indicates this mechanism can synthesize new extracellular matrix proteins. For patients with cirrhosis, this helps stabilize liver architecture over time. Results vary heavily based on the severity of the pre-existing fibrotic damage.
Liver fibrosis cannot be completely reversed by stem cells in late-stage cirrhosis, but its aggressive progression can be significantly slowed. Mesenchymal stem cells inhibit the activation of hepatic stellate cells, which are responsible for producing excessive scar tissue. This intervention downgrades the severity of the fibrosis, allowing for improved blood flow and vital nutrient delivery. Patients often see stabilization in their disease staging following treatment. However, severe architectural changes to the liver remain permanent.
Side effects of UC-MSC therapy for liver disease are generally mild and include localized pain at the injection site, transient fever, or fatigue. Because umbilical cord cells have extremely low immunogenicity, severe allergic reactions or graft-versus-host disease are exceedingly rare. In some cases involving targeted intrahepatic injections, patients may experience minor bleeding or bruising. These symptoms typically resolve within 24 to 48 hours post-procedure. Patients with active infections are excluded from treatment to prevent severe complications.
Stem cell therapy after a liver transplant is currently utilized in clinical trials primarily to manage immune rejection, not to regenerate the new organ. UC-MSCs possess potent immunomodulatory properties that can help suppress the recipient’s immune system, potentially reducing the reliance on harsh, kidney-damaging immunosuppressive drugs. This targeted approach aims to promote long-term tolerance of the donor graft. It is not used as a standard-of-care procedure following successful surgery. Any post-transplant cellular therapy requires strict oversight from the surgical team.
Exosome therapy for liver disease utilizes the extracellular vesicles secreted by stem cells rather than the live cells themselves. These nano-sized vesicles contain the exact growth factors and RNA responsible for the paracrine healing effect, offering a completely cell-free regenerative option. This approach massively reduces the risk of unwanted immune responses while still delivering potent anti-fibrotic signals to the damaged liver. Exosome therapy represents the next generation of regenerative medicine. It is currently under intensive clinical investigation for treating decompensated cirrhosis.
For patients navigating decompensated cirrhosis, umbilical cord stem cell therapy for liver cirrhosis offers a scientifically validated method to reduce inflammation and stabilize vital biomarkers like MELD scores and serum albumin (National Institutes of Health). The best clinical approach combines strict pre-treatment hepatology assessments, standardized UC-MSC protocols, and ongoing lifestyle management to halt further fibrotic degradation. Hepatocyte regeneration with mesenchymal stem cells is a tool, not magic.
Applying The Biological Bridge Framework ensures patients and their families maintain realistic, data-driven expectations. Regenerative medicine does not erase severe architectural scarring. Rather, it buys critical time, improves immediate quality of life, and sustains systemic health for those languishing on prolonged transplant waitlists. Stem cell therapy for ascites and jaundice management fits perfectly within this biological bridge concept.
Ready to determine your medical suitability? Patients seeking advanced regenerative evaluations should contact or visit a specialized, GMP-certified facility in Bangkok to assess whether UC-MSC therapy aligns with their specific clinical trajectory.