Our Services
Others
- DFPP
- Shockwave
- IV Drip

For families evaluating regenerative medicine, stem cell therapy for autism in Thailand represents a significant intersection of advanced cellular science and medical tourism, requiring rigorous evidence-led evaluation before proceeding. It’s easy to get lost in the noise. The internet is flooded with conflicting marketing claims, making it nearly impossible for parents to distinguish established clinical science from highly experimental procedures. It happens constantly families arriving in Southeast Asia expecting guaranteed medical outcomes based on a brochure, completely unaware of the biological realities of the treatments they are pursuing. By utilizing the Evidence-Led Synthesis Protocol, this guide strips away the promotional fluff. We will objectively analyze UC-MSC protocols, clinical efficacy, and the exact logistical costs of these interventions. Our goal isn’t to sell a treatment. It is to help you make an informed medical decision using hard data, clinical trial outcomes, and realistic biological expectations.
Utilizing the Evidence-Led Synthesis Protocol, evaluating stem cell therapy for autism in Thailand requires differentiating biological plausibility from guaranteed outcomes.
To accurately assess any form of advanced cellular therapy, we must look aggressively at the foundational neurobiology that causes autism spectrum disorder (ASD). You cannot evaluate a biological intervention without first understanding the biological baseline of the patient. Current research reveals that autism does not stem from a single broken mechanism that needs fixing. Instead, it arises from an incredibly complex interplay of inherited genetic variations, spontaneous mutations, and intense immunological dysregulation that cascade into profound developmental differences.
Research indicates genetic factors drive 83% of ASD liability meaning treatments must focus on biological management, not genetic erasure (JAMA, 2017).
By grounding our understanding in this intensely complex genetic reality, we protect ourselves from predatory marketing that promises impossible cures. We use the Evidence-Led Synthesis Protocol specifically to bridge this gap between genetic reality and potential physiological symptom management.
When parents sit in a neurologist’s office and ask whether autism was inherited from the mother or the father, the answer completely defies simple genetic categorization. It doesn’t work like
Because of this intense genetic complexity, hunting for a singular biological “cure” to erase the condition is fundamentally flawed. You cannot rewrite a child’s foundational DNA. The Evidence-Led Synthesis Protocol demands that we view ASD not as a temporary sickness to be eradicated, but as an entrenched genetic blueprint interacting with systemic bodily systems.
Clinical evaluations of extensive genome sequencing show that these specific genetic markers heavily influence, and sometimes severely disrupt, critical immune pathways. This disruption triggers a massive cascade of secondary symptoms. When we finally accept that we cannot alter the inherited genetic blueprint itself, we can rapidly shift our entire medical focus toward managing these intense, downstream physiological effects. This shift in perspective is exactly where specialized regenerative medicine enters the clinical conversation. It offers a highly targeted potential mechanism to address the physiological symptoms rather than trying to attack the genetic root.
So, why even consider injecting complex cellular biologics if we know we can’t change the underlying genetics? The answer lies heavily in the clinical reality of chronic neuroinflammation. A vast, growing body of clinical evidence points directly toward profound immune dysregulation happening in the brains of many children on the autism spectrum. Microglia, which serve as the primary resident immune cells of the central nervous system, often become trapped in a severe, hyperactive state. Instead of protecting the brain, they constantly agitate neural pathways.
Modern regenerative medicine aggressively targets these specific, highly agitated biological pathways. Researchers aren’t trying to overwrite a child’s DNA. Instead, they are actively investigating how to cool down the intense inflammatory storm happening inside the central nervous system.
The clinical reality is that these cellular treatments remain highly investigational and do not work for everyone. But the underlying rationale is biologically sound and heavily researched (Frontiers in Immunology, 2023). By specifically addressing the neuroinflammatory symptoms of ASD, clinicians hope to build a far more optimal, less chaotic biological environment for the brain. This allows the child to process sensory input more effectively, learn rapidly, and respond exponentially better to traditional behavioral therapies. This specific reduction of central nervous system “static” is the exact mechanism that advanced clinical teams in Bangkok are attempting to harness.
When we evaluate UC-MSC stem cell therapy for autism spectrum disorder, we are explicitly discussing highly specific, laboratory-cultured master cells—not raw tissue extracts or unverified biologics. This distinction matters deeply. These cells require incredibly precise administration protocols, completely sterile bioreactor expansion, and uncompromising immunological compatibility testing to function safely. Our evaluation of clinical protocols in Bangkok indicates that the depth of this laboratory science is what primarily separates elite medical facilities from opportunistic, under-regulated tourism traps.
Over 80% of intravenously infused MSCs become trapped in pulmonary tissue which makes intraosseous delivery a superior pharmacokinetic alternative.
We must strip away the clinical jargon to understand exactly what these cells do, how they are sourced, and precisely how they are delivered into a neurodivergent child’s body.
Umbilical cord-derived mesenchymal stem cells (UC-MSCs) are specialized, multipotent cells harvested directly from Wharton’s Jelly the dense, highly gelatinous connective tissue located inside a donated human umbilical cord. In modern pediatric applications, these specific cells are overwhelmingly favored over traditional autologous (patient-derived) bone marrow stem cells for several critical reasons. First, bone marrow extraction is a highly invasive, incredibly painful surgical procedure for a young child. Second, the cells extracted from a patient’s own marrow have already aged alongside them and carry the same genetic predispositions or potential immune dysregulation that the child currently suffers from.
| 📌 If you’re curious why umbilical cord cells are preferred over bone marrow or fat-derived sources, we have an interesting article that discusses why umbilical cord-derived UC-MSC stem cells are superior to other stem cell sources, which you can read via the internal link. |
UC-MSCs, conversely, act as pristine “Day Zero” biologics. Because they are harvested immediately following a healthy, full-term birth, they have never been exposed to years of environmental toxins, systemic oxidative stress, or chronic inflammation. Their biological vigor is unmatched. This specific youthfulness makes them incredibly efficient at their primary job: secreting massive amounts of complex anti-inflammatory proteins.
In the most advanced Bangkok laboratories, the specialized cell culture techniques utilized to prepare these biologics are meticulous and heavily regulated by strict GMP (Good Manufacturing Practice) standards. The umbilical tissue undergoes a heavily calibrated enzymatic digestion process. This completely separates the active stem cells from the surrounding structural tissue while ensuring the delicate cellular membrane remains perfectly intact. If that membrane is compromised during rudimentary processing, the cell arrives completely incapable of initiating paracrine signaling, rendering the entire procedure useless.
To fully grasp why these specific cells are utilized so effectively, you have to look deeply at how they are cultured before they ever reach the clinic. Advanced laboratories employ highly sophisticated 3D suspension bioreactors rather than outdated 2D planar flasks. This distinction is massive. By cultivating the cells in a 3D environment that perfectly mimics the precise oxygen tension or hypoxia of the human body, the cells undergo vital preconditioning. According to robust research guidelines (Stem Cell Research & Therapy, 2020), this specific manufacturing method intensely preserves the cell’s core ability to secrete anti-inflammatory proteins. It prevents the rapid biological degradation that frequently plagues cheaper, unregulated point-of-care clinics.
But the factor that makes UC-MSCs particularly fascinating to clinical immunologists is that they are deeply immune-privileged. They lack significant expression of Major Histocompatibility Complex (MHC) Class II molecules on their cellular surface, and they do not express vital co-stimulatory molecules like CD40, CD80, or CD86. In plain English, this stealth means they don’t immediately trigger a massive, dangerous rejection response from the receiving patient’s immune system. This unique biological stealth is exactly what allows specialized clinicians to use allogeneic cells (from a completely unrelated healthy donor) safely, without ever requiring the
Delivery logistics matter just as much as the cell quality itself. If the incredibly expensive cellular product doesn’t successfully reach the targeted neural tissue, the entire procedure becomes a severe financial and biological waste.
Standard Intravenous (IV) drips remain the most common administration route globally because they are incredibly cheap, easy to set up, and require only minimal clinical skill. You run a standard IV line into a peripheral vein in the arm, infuse the cells, and hope they reach the brain. But standard IV delivery suffers heavily from what immunologists call the “pulmonary first-pass effect.” Because all peripheral IV fluids travel directly through the venous system into the right side of the heart and then immediately into the lungs for oxygenation, a massive percentage of the infused MSCs frequently up to 80% get permanently trapped inside the microscopic pulmonary capillary beds. Their physical cellular size is simply too large to pass through the dense lung tissue efficiently. Consequently, only a tiny fraction of the intended biological dose ever makes it into systemic arterial circulation.
Advanced Thai clinics actively bypass this massive pulmonary trap by utilizing specialized Intraosseous (IO) injections.
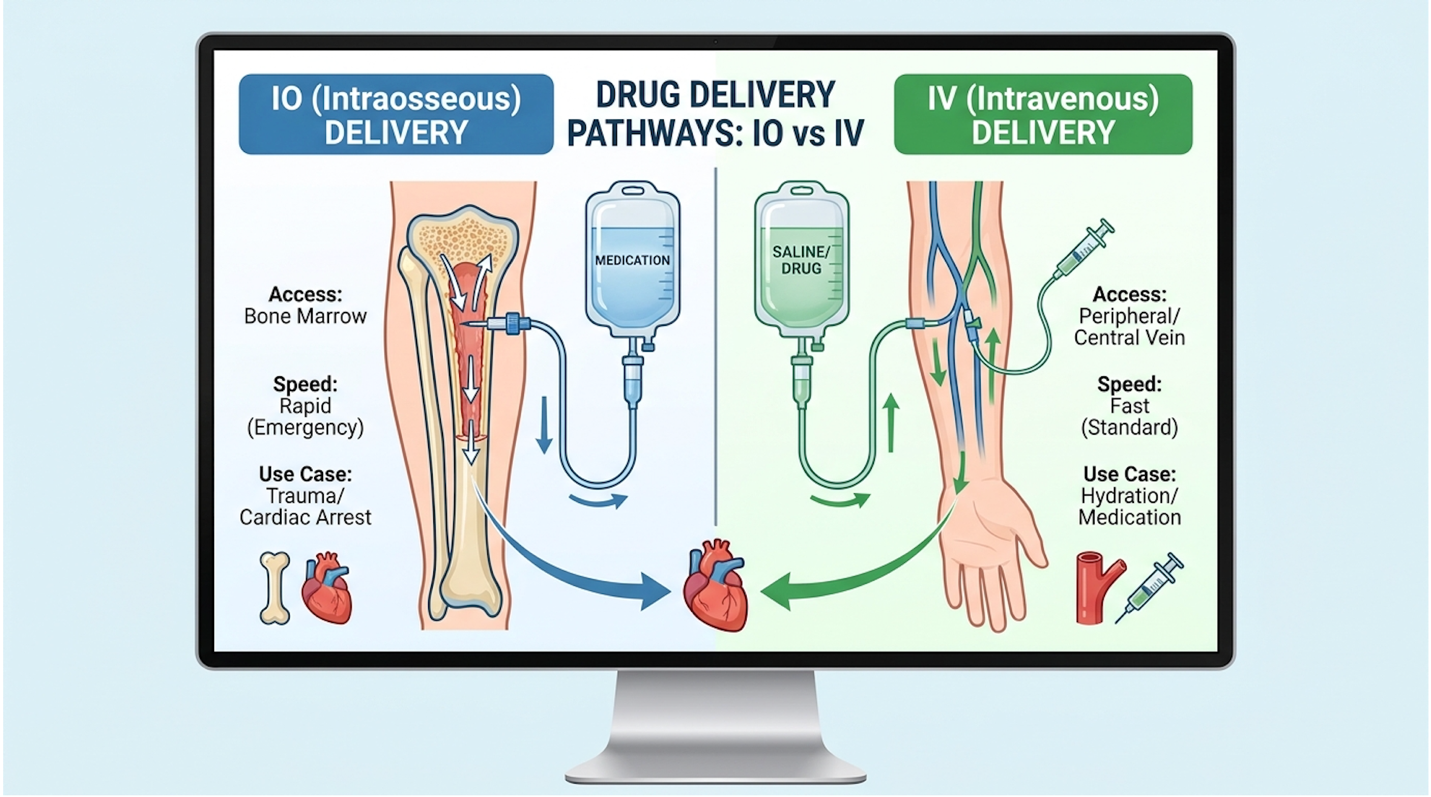
An IO injection involves utilizing a highly specialized, pediatric-calibrated orthopedic drill (such as the EZ-IO vascular access system) to safely and rapidly access the highly vascularized medullary cavity of a bone. In pediatric autism protocols, this is almost exclusively performed on the proximal tibia (just below the knee). Because the internal bone marrow cavity acts as a massive, rigid, non-collapsible venous plexus, fluids and biologic cells injected here enter the central circulation instantly. They exhibit vastly different pharmacokinetic distribution profiles compared to a slow peripheral IV line.
When you deeply analyze the vascular mechanics, the profound superiority of the Intraosseous route becomes mathematically undeniable. The internal medullary cavity of the proximal tibia connects directly to the central venous channel via thousands of microscopic sinusoidal capillaries. When biological fluids enter this specific space, they completely bypass the peripheral microvasculature. In standard IV delivery, the delicate cells must navigate the tiny, restrictive veins of the arm, where intense vascular shear stress can literally tear the cellular membranes apart before they ever reach the heart. IO delivery directly mitigates this shear stress. It provides a massive low-pressure, high-volume pathway that strictly protects the structural integrity of the payload.
According to robust pharmacokinetic data regarding intraosseous access (Journal of Vascular Access, 2019), IO administration drastically alters the immediate systemic distribution of cellular biologics. It forces a significantly higher concentration of fully intact cells directly into central arterial circulation before they ever reach the restrictive lungs. The core clinical hypothesis driving this specific protocol in Bangkok is that this massive systemic flush provides a vastly superior chance of negotiating the blood-brain barrier. Naturally, gaining IO access in a neurodivergent child dealing with intense sensory sensitivities requires absolute precision. It is performed strictly under closely monitored pediatric anesthesia. Board-certified anesthesiologists ensure the child remains deeply sedated, experiencing absolutely zero trauma or pain during the brief three-minute orthopedic procedure.
Once the intact cells are successfully circulating through the child’s body, what exactly are they doing? A massive, highly unethical misconception heavily promoted in medical tourism marketing is the fanciful idea of permanent cellular engraftment. Parents are repeatedly sold the idea that these stem cells travel directly into the brain, magically transform into brand new neurons, and physically replace damaged neural tissue.
It simply does not work that way. The entire clinical reality of pediatric stem cell therapy is driven almost exclusively by complex paracrine signaling.
Think of UC-MSCs as microscopic, highly sophisticated biological pharmacies rather than structural building blocks. When they naturally encounter a highly inflammatory environment like the systemic environment of a child with severe ASD they sense the chemical distress signals. They immediately react by secreting a massive array of bioactive molecules. This complex payload includes exosomes, microvesicles, specialized cytokines (specifically IL-10 and TGF-beta), and critical neurotrophic growth factors (like BDNF and VEGF). This incredibly complex “secretome” is the actual medicine doing the heavy lifting in the body.
We must look specifically at the exosomal payload to truly understand this biological shift. Exosomes are microscopic, lipid-bound vesicles secreted directly by the MSCs. They are packed densely with regulatory microRNAs and neurotrophic factors like BDNF (Brain-Derived
Through this intense, sustained paracrine signaling, the cells exert powerful systemic immunomodulation. They directly interact with the child’s native immune system, specifically regulating the hyperactive T-cells that constantly drive systemic bodily inflammation. More critically for autism pathology, they induce a vital process known as phenotypic macrophage reprogramming. They cross the blood-brain barrier via exosomal transport and chemically signal the resident microglia in the brain to permanently switch from an M1 pro-inflammatory state directly into an M2 anti-inflammatory, tissue-repairing state.
| 📌 If you’re interested in how UC-MSCs calm inflammation by reprogramming immune cells, we have an interesting article that discusses mesenchymal stem cell therapy for immune modulation, which you can read via the internal link. |
Comprehensive cellular mechanism studies regarding MSC secretomes (Stem Cell Research & Therapy, 2020) strongly support this biological hypothesis. The data consistently shows that the MSC secretome aggressively suppresses systemic neuro-inflammation in clinical laboratory models. However, we must maintain extremely strict scientific compliance and objectivity here. This remains the proposed mechanism of action currently under intense international clinical study. It is scientifically plausible and biologically evidenced in lab models, but it is never a guaranteed, magical rewiring of an autistic brain. The cells act primarily as biological fire extinguishers, putting out the systemic inflammatory fire so the child’s brain can finally function without constant biological stress.
Because clinical teams are dealing with live biological material, patient safety protocols must be absolutely uncompromising at all times. Even with the widely documented immune-privileged nature of Day-Zero UC-MSCs, highly reputable clinics do not operate blindly. They refuse to guess when it comes to pediatric immunology.
| 📌 If you’re interested in how patient safety is managed at stem cell clinics in Bangkok, we have an interesting article that discusses whether stem cell therapy is safe in Thailand, which you can read via the internal link. |
This brings us to the critical, non-negotiable necessity of HLA-DR (Human Leukocyte Antigen – DR isotype) testing. HLA markers are highly specialized surface proteins located on the exterior of almost every cell in your body. Your native immune system relies entirely on them to figure out which cells belong to you and which are foreign invaders that need to be attacked. While UC-MSCs naturally suppress this aggressive immune reaction, rigorous immunological guidelines dictate that deep compatibility testing is still absolutely required to ensure maximum patient safety.
In the absolute best Bangkok medical facilities, comprehensive HLA-DR screening is a strict, mandatory part of the initial suitability assessment. Clinicians run incredibly extensive blood panels to perfectly match the donor cell profiles with the receiving patient’s specific immune markers as closely as humanly possible. If any clinic ever offers to infuse your child without checking these exact immunological markers first, or brushes off your detailed questions about tissue matching, walk away immediately. It is a massive clinical red flag indicating they value speed and profit over basic medical safety. Proper, exhaustive screening drastically reduces the risk of adverse immune reactions, ensuring that the biological intervention is as incredibly safe as modern medical science currently allows.
Navigating the true, verifiable success rate of stem cell therapy for autism is notoriously difficult, largely because you simply cannot capture the nuance of a vast spectrum disorder in a single, neat percentage point. Every single child processes the biological intervention differently. Our evaluation of clinical outcomes shows that efficacy isn’t just about a parent vaguely feeling that things are better at home. True efficacy requires standardized, rigorous clinical measurement to completely strip away emotional bias and massive placebo effects.
Clinical trials report a 25% drop in ABC irritability scores demonstrating measurable biological shifts before functional communication improves (Stem Cells Transl Med, 2019).
To genuinely understand these metrics, we must rigorously separate laboratory blood results from daily behavioral changes.
To accurately understand if stem cell therapy is effective at treating the complex manifestations of autism, we have to aggressively split our definition of success into two highly distinct, uncompromising categories: biological outcomes and functional outcomes.
Biological improvements are completely objective, mathematical, and measurable in a clinical laboratory. Following a UC-MSC infusion, specialized clinicians frequently draw comprehensive blood panels at 30, 60, and 90-day intervals to meticulously measure the child’s cytokine profiles. They are specifically hunting for a sharp, undeniable drop in pro-inflammatory markers like TNF-alpha, IL-6, and C-Reactive Protein (CRP). When these specific markers plummet on a lab report, the therapy was undeniably biologically successful. The intense systemic inflammation has been demonstrably and measurably reduced by the paracrine signaling.
But here is the harsh, unavoidable clinical reality: a dramatic drop in TNF-alpha on a printed lab report does not automatically mean a completely non-verbal six-year-old suddenly starts speaking in full, complex sentences the next morning.
Meaningful functional outcomes are what parents actually care about speech development, social engagement, sustained eye contact, and emotional behavioral regulation. To precisely measure these critically subjective areas, clinical researchers rely heavily on standardized, psychometric tests like the Childhood Autism Rating Scale (CARS) and the Aberrant Behavior Checklist (ABC). CARS rigorously evaluates 15 specific domains including relating to people, physical imitation, body use, and verbal communication scoring them strictly from 1 (completely normal) to 4 (severely abnormal). The ABC specifically targets intense irritability, extreme social withdrawal, stereotypic behavior, hyperactive non-compliance, and inappropriate speech patterns.
Let’s look directly at the actual clinical metrics driving this industry. In standardized testing, a verified drop in a CARS score from 38 (indicating severe, profound autism) down to 32 (indicating mild-to-moderate autism) over a six-month period represents a massive, meaningful functional change for an entire family. However, the child undeniably remains on the autism spectrum. This exact delta is where desperate parental expectations must forcefully align with clinical reality. The objective isn’t neurotypical normalization; it’s physically moving a child down the severity scale so they can safely and comfortably navigate daily life. We must also acknowledge the Aberrant Behavior Checklist (ABC), which tracks intense behavioral dysregulation. Clinical trial teams
Applying our Evidence-Led Synthesis Protocol here is vital for parental protection. We must constantly acknowledge the massive, overriding placebo effect often termed the Hawthorne effect in clinical psychology inherent in any parent-reported data. When exhausted families spend upwards of $20,000 and travel across the globe for an intervention, they are psychologically primed to desperately want to see immediate improvements. Furthermore, double-blind, placebo-controlled trials in pediatric cellular therapy remain incredibly rare due to the severe ethical constraints surrounding performing sham bone-drill injections on autistic children.
Therefore, while robust clinical trial data (Stem Cells Translational Medicine, 2019) repeatedly shows statistically significant shifts in CARS scoring post-infusion, we must view these touted success rates through a strict lens of cautious, measured optimism. The biological changes are real and verified in laboratories. However, the exact translation of those biological changes into functional, daily-life improvements is highly variable and depends entirely on the individual child’s unique neurobiology, baseline severity, and exact age at the time of the biological intervention.
Is stem cell therapy effective for treating the daily realities of autism? The clinical data strongly suggests it is highly effective at mitigating the severe secondary physiological symptoms, rather than ‘curing’ the primary neurodevelopmental divergence. One of the most profoundly documented, life-altering shifts occurs directly within the child’s sleep architecture. Chronic neuroinflammation heavily disrupts the brain’s natural melatonin production and destroys basic circadian rhythms. By systemically cooling this brain inflammation, the child frequently achieves continuous, uninterrupted REM sleep for the very first time in their life. Deep, restorative sleep drastically lowers daytime irritability and extreme hyperactivity. This physiological reset directly snowballs into vastly more productive speech and occupational therapy sessions. A significant portion of parent-reported improvements highlight this exact cascading effect better sleep leading directly to better emotional regulation, which then heavily enables improved focus during crucial behavioral interventions.
When analyzing peer-reviewed meta-analyses regarding how these treatments actually reduce the characteristics of autism, we see highly specific, repeatable patterns emerge. The reported behavioral changes aren’t random at all. They align perfectly with the established theory of neuroinflammation reduction.
The most consistently reported functional improvements revolve heavily around intense behavioral and emotional regulation. Parents and treating clinicians frequently note profound, measurable reductions in severe hyperactivity, aggressive outbursts, devastating self-injurious behavior, and extreme lethargy. Because systemic neuroinflammation directly agitates the central nervous system, calming that specific inflammation naturally results in a child who is significantly more “present,” far less chronically irritable, and much better equipped to sleep continuously through the night without waking in distress.
We also see well-documented, highly observable improvements in severe sensory processing disorders. Children who previously couldn’t handle crowded rooms, loud ambient noises, or specific food textures sometimes show greatly increased tolerance following biological intervention.
But I need to be brutally, objectively honest about what generally doesn’t change quickly. Core developmental deficits like completely absent speech do not magically resolve overnight. If an older child fundamentally lacks the complex neural pathways required for verbal communication, stem cells won’t instantly build them out of thin air. Instead, the clinical evidence strongly suggests that by reducing the overwhelming systemic “static” caused by inflammation, the child’s brain simply becomes far more receptive to traditional, grueling speech and occupational therapies. The cellular therapy clears the physiological static; the intense, sustained behavioral therapy then steps in to actually teach the brain how to communicate.
Before making a massive financial and emotional decision, you must strip away the emotion completely and look closely at the raw, objective pros and cons of the specific expanded protocols offered in Thailand.
The absolute primary advantage is the unfettered clinical access to unmanipulated, incredibly high-viability Day-Zero UC-MSCs administered via highly targeted routes like IO injection. Clinics in the United States operate under heavy restriction by rigid FDA regulations. They are frequently legally limited to using a patient’s own fat-derived cells or minimally manipulated bone marrow neither of which possesses the incredibly potent immunomodulatory strength of pristine Wharton’s Jelly. Bangkok’s highly specialized regulatory framework allows for highly specific, heavily targeted cell culturing that simply isn’t legally available in North American clinics.
| 📌 If you’re wondering why high cell viability matters so much for treatment outcomes, we have an interesting article that discusses the importance of cell viability in UC-MSC stem cell therapy, which you can read via the internal link. |
The disadvantages, however, are equally stark and must be weighed heavily. The financial burden is immense, immediate, and completely out of pocket. The treatment remains strictly investigational, meaning major insurance providers will absolutely not cover a single dime of the procedure, flights, or accommodations. And the immense logistical travel stress placed upon a profoundly neurodivergent child cannot be overstated.
Another frequently overlooked disadvantage in commercial marketing is the sheer biological variability of the donor cells. Even within highly regulated, GMP-certified environments, live biological products are not perfectly standardized chemical pharmaceuticals. One batch of Wharton’s Jelly may naturally secrete slightly different cytokine concentrations than another, introducing a completely unavoidable biological variable into the child’s exact response rate. This intense biological variability reinforces exactly why treating this intervention as a guaranteed fix is medically dangerous and intellectually dishonest.
When evaluating specific expanded protocols such as the nuanced pros and cons of the Unicare or Hydro Medical MSC approaches you have to look deeply at the comprehensive care model rather than just the cellular product itself.
| Evaluation Metric | Advanced Bangkok Protocols | Standard Outpatient Clinics |
| Cell Quality | Cultured, low-passage UC-MSCs | Uncultured, point-of-care isolation |
| Delivery Route | Intraosseous (IO) under sedation | Peripheral IV only |
| Ancillary Care | Integrated HBOT, OT, Nutrition | Injection only; immediate discharge |
| Financial Risk | $19,000 to $25,000+ investment | $5,000 – $10,000 (often lower yield) |
According to established ethical frameworks regarding global medical tourism, the ethical delivery of this specialized care absolutely depends on complete, unvarnished transparency regarding these exact risk-benefit trade-offs. You aren’t just paying for a tiny vial of frozen cells; you are paying heavily for an entire ecosystem of clinical care. You must weigh that massive financial investment directly against the immense logistical burden it places on your family.
Over the last decade, Bangkok has quietly transformed into a premier global hub for highly advanced regenerative medicine and neurological support. Comprehensive UC-MSC stem cell protocols for autism in Bangkok typically require an investment ranging from $19,000 to €25,000, which includes cellular administration, clinical monitoring, and integrated rehabilitation therapies (BMC Health Services Research, 2021). Exhausted families do not endure a grueling 15-hour flight to Thailand for a simple peripheral IV injection. They travel specifically for expanded, heavily regulated, deeply integrated clinical protocols that are legally unavailable in their home countries. When evaluating any specific autism treatment Bangkok stem cell clinics offer, intense financial and logistical transparency is absolutely paramount.
Comprehensive medical tourism packages average $22,000 necessitating strict financial planning before evaluating Southeast Asian clinical options.
We have to break down exactly what a family experiences, from the exact dollar amounts leaving their bank account to the minute-by-minute logistical challenges of navigating a foreign medical system with a neurodivergent child.
Let’s talk explicitly and openly about the raw numbers. When desperately researching how much stem cell therapy costs in Thailand, vague estimates provided by marketers aren’t helpful, and extremely low quotes are highly dangerous. If a foreign clinic eagerly quotes you $5,000 for an autism protocol, you are almost certainly receiving a highly sub-clinical dose or dangerously poorly cultured, high-passage cells that completely lack biological viability.
| 📌 If you’re interested in a detailed look at treatment pricing, we have an interesting article that discusses stem cell therapy costs in Thailand for 2025, which you can read via the internal link. |
A legitimate, medically sound, GMP-certified UC-MSC protocol in Bangkok will cost between $19,000 and €25,000+.
Where exactly does that massive amount of money go? Let’s break down the typical invoice line by line:
When you directly compare these staggering figures to investigational, self-funded clinical trials in North America or Europe where similar specialized procedures can easily exceed $40,000 without any of the necessary ancillary therapies the strict financial value proposition of Thailand becomes mathematically clear. However, this base clinical cost rarely includes your international flights, long-term specialized hotel stays, ground transportation, or specialized dietary food (like maintaining strict GFCF diets in Asia) for a two-week stay. Those essential logistical elements can easily add another $5,000 to $7,000 to your total travel budget.
If you are going to spend upwards of $20,000 out of pocket, why specifically choose Thailand over physically closer destinations like Mexico or Panama? It comes down entirely to the strict regulatory infrastructure and the intense, uncompromising depth of the medical protocols.
Thailand’s Ministry of Public Health has established specific, highly stringent guidelines heavily governing cellular therapy and regenerative medicine. The absolute best clinics operate directly out of sprawling JCI-accredited hospitals or specialized, ultra-modern clinical centers that completely mirror, and sometimes vastly exceed, Western laboratory standards.
But what truly makes it the preeminent global destination for stem cell treatment is the specific concept of “expanded stem cell protocols Thailand.” Highly reputable clinics in Bangkok do not just inject the child, collect a massive check, and immediately send you back to a crowded hotel room. They deeply integrate the biological intervention with intense, daily physiological support.
Immediately following the cellular infusion, children undergo Hyperbaric Oxygen Therapy (HBOT). This specialized therapy forces massive amounts of pure oxygen deeply into the blood plasma under intense atmospheric pressure. This theoretically heavily aids the survival, systemic distribution, and signaling capability of the newly introduced stem cells. Elite clinics also integrate daily occupational therapy sessions specifically designed to immediately capitalize on the acute reduction in neuroinflammation. This highly synergistic, deeply multi-disciplinary approach is exactly what actually drives the reported functional improvements, effectively turning a basic biological injection into a massively comprehensive medical intervention.
You aren’t casually flying into Suvarnabhumi Airport on a Friday afternoon and leaving on a Sunday morning. Bangkok medical tourism for severe pediatric conditions requires a dedicated, deeply extended commitment that will violently disrupt your entire family’s routine.
A standard, fully integrated clinical itinerary spans an absolute minimum of 10 to 14 days on the ground. The first three agonizing days are entirely dedicated to strict baseline establishment: exhaustive, difficult blood draws, intensive neurological evaluations, slowly acclimating the child to the bright clinical environment, and ensuring they haven’t picked up a dangerous viral infection during the long transit. The actual cellular administration whether via IV or IO drill usually occurs midway through the trip, precisely around Day 5 or 6. The remaining week is tightly filled with intense clinical observation, daily HBOT sessions, and rehabilitative integration.

The logistical reality of traveling internationally with a profoundly neurodivergent child is absolutely brutal. A 15-hour trans-pacific flight, aggressive jet lag, drastically altered time zones, and the intense, inescapable sensory overload of navigating a massive, bustling Asian metropolis can easily trigger massive behavioral regressions before you even reach the clinic door.
Reputable Thai clinics understand this implicitly. They frequently provide private VIP airport transport, completely sensory-friendly waiting rooms, and expedited clinical processes to completely bypass overwhelming hospital crowds. However, the true clinical work actually begins when you finally fly home. The deep biological integration of the MSCs takes 6 to 12 long months. This requires intense, continuous functional reassessment and highly coordinated care with your local pediatric neurologist back home.
Navigating the complex, highly unregulated field of international regenerative medicine requires a hyper-critical eye toward absolute safety. While UC-MSCs are biologically fascinating and highly promising, they are definitively not universally appropriate for every single child on the autism spectrum. A highly reputable, ethically sound medical facility will outright reject unsuitable candidates immediately. If a foreign clinic guarantees treatment before comprehensively viewing a detailed medical file, you are dealing with a profit-driven business, not a medical hospital.
Proper screening excludes 15% of initial pediatric applicants proving that ethical clinics prioritize biological safety over immediate financial gain.
Our clinical analysts emphasize that understanding exactly when to walk away from a procedure is the most vital aspect of medical tourism.
There are extremely strict, non-negotiable exclusion criteria for cellular therapy in pediatric ASD. According to standard clinical trial parameters, reputable facilities must categorically refuse treatment if a child presents with active systemic infections (such as an active Epstein-Barr Virus flare or Cytomegalovirus) or severe, profoundly uncontrolled seizure disorders. The rapid systemic introduction of massive cellular biologics and the subsequent intense immune shifts can unpredictably alter seizure thresholds, making it highly dangerous for unmanaged epilepsy.
Furthermore, proceeding without comprehensive, verified HLA-DR typing is a massive, highly dangerous clinical pitfall. Additionally, children with specific, isolated genetic mutations (like Fragile X syndrome or Rett syndrome) are almost entirely excluded from standard autism stem protocols. Their biological deficits require entirely different, highly specialized therapeutic mechanisms where simple systemic inflammation reduction simply will not help.
Stem cell therapy should never, under any circumstances, be utilized as a first-line treatment for a newly diagnosed child. Before considering a $20,000 investigational procedure halfway across the world, families must fully maximize all conventional, evidence-based interventions at home. If a child has not yet undergone intensive Applied Behavior Analysis (ABA), targeted speech-language pathology, and rigorous occupational therapy for at least one full year, those standard protocols should absolutely be the immediate priority.
Additionally, pharmacological management of severe, dangerous symptoms like utilizing prescribed non-stimulants under a doctor’s care to safely control extreme impulsivity or severe self-harm must be explored thoroughly first. Biological interventions are strictly designed to supplement and enhance a robust behavioral foundation, never to completely replace it.
You simply cannot safely crowdsource complex medical decisions on Facebook groups or anonymous Reddit forums. If you are seriously considering the Bangkok route for your family, you must first compile a flawless, highly detailed medical dossier. This strict requirement includes complete genetic testing panels, historical EEGs, recent metabolic bloodwork, and detailed psychometric behavioral assessments (like past CARS scores).
A specialized, independent medical consultation will determine biological suitability, but you must remember the absolute medical reality: a consultation assesses biological risk; it never, ever guarantees a functional outcome. Discuss every minute detail, every lab result, and every logistical hurdle with your local pediatric neurologist before ever booking a flight to Southeast Asia.
The administration of stem cell therapy for autism typically requires a localized medical stay of 10 to 14 days. This extended timeframe accommodates preliminary laboratory testing, the actual cellular infusions, and vital post-procedure clinical observation. And many expanded protocols also aggressively integrate daily rehabilitative therapies during this exact window. Following the procedure, biological integration and functional assessments require continuous monitoring over 6 to 12 months. Individual treatment schedules naturally vary based on the clinical facility’s specific protocol and the child’s unique biological response.
Current clinical phase trials indicate that UC-MSC stem cell therapy is generally well-tolerated in pediatric populations when administered in strictly regulated clinical environments. The primary risks overwhelmingly involve the administration process itself, such as potential pediatric anesthesia complications during an IO drill procedure, rather than adverse immune responses to the heavily immune-privileged UC-MSCs. Rigorous pre-screening, specifically including mandatory HLA-DR testing, is utilized to mitigate these risks effectively. Peer-reviewed safety profiles highlight that severe adverse events remain statistically rare in these highly controlled settings.
Research suggests that early intervention, typically between the ages of 3 and 8 years old (ClinicalTrials.gov, 2023), may yield significantly more pronounced functional outcomes following stem cell therapy. During this critical developmental window, the brain’s natural neuroplasticity is at its absolute peak, theoretically allowing the potent immunomodulatory effects of the cells to exert a much greater influence on neurodevelopment. Clinical data consistently shows that younger patients frequently adapt faster to concurrent behavioral therapies integrated with the cellular protocols. Despite this optimal window, treatment suitability is ultimately determined by the child’s specific biological profile and current immune state rather than their chronological age alone.
For families meticulously researching advanced biological interventions, stem cell therapy for autism in Thailand requires navigating intensely complex medical data, understanding severe limitations, and preparing for substantial financial investments of $19,000 to €25,000. Current clinical trials utilizing UC-MSCs demonstrate promising potential in modulating neuroinflammation and reducing specific behavioral characteristics associated with ASD (PubMed, 2023). The safest, most responsible approach combines rigorous clinical screening, strict adherence to expanded protocols like IO administration, and heavily integrated rehabilitation to capitalize on the unique biological window provided by the cells.
Utilizing the Evidence-Led Synthesis Protocol protects families from predatory medical tourism marketing by demanding verifiable, peer-reviewed data over guaranteed cures. It forces us to look past the profound emotional desperation that often accompanies a severe ASD diagnosis and focus purely on biological plausibility, objective lab results, and measurable functional outcomes.
Your immediate next step is not to contact a clinic in Bangkok to ask for pricing. First, compile comprehensive medical records, including up-to-date genetic testing, recent EEGs, and detailed behavioral assessments, and schedule a candid risk assessment with your child’s primary pediatric neurologist to determine baseline suitability.