Our Services
Others
- DFPP
- Shockwave
- IV Drip

This article is for educational purposes only and does not replace consultation with a qualified medical professional.
For patients navigating chronic discogenic pain, the decision often comes down to invasive spinal fusion or exploring regenerative alternatives like stem cell therapy for back pain. It’s a brutal crossroad. However, navigating the regenerative medicine space requires distinguishing established biological mechanisms from experimental hype and predatory clinic marketing. By the end of this guide, you will understand the strict criteria for clinical candidacy, the proven cellular mechanisms, and the actual out-of-pocket costs to make a medically informed decision. We will analyze the biological data, evaluate patient eligibility, break down the procedural risks, and map out realistic timelines for pain relief.
| 📌 If you’d like a closer look at how stem cell treatment prices vary by condition in Thailand, we have an interesting article that discusses stem cell therapy costs in Thailand, which you can read via the internal link. |
Stem cell therapy for back pain utilizes mesenchymal cells to manage inflammation and support tissue stabilization in degenerative disc disease.
Stem cell therapy for chronic back pain acts as a regenerative alternative to spinal fusion by altering the inflammatory microenvironment of the spine. Utilizing mesenchymal stem cells, this approach targets degenerative disc disease by modulating local immune responses rather than acting as a simple surgical patch. This provides non-surgical pain management for qualified patients.
Our clinical analysis of patient histories frequently encounters the question, “Does stem cell therapy work for bad backs?” The answer isn’t a simple yes or no—it’s highly dependent on spinal pathology. We have to separate what happens in a pristine laboratory petri dish from what happens inside a desiccated, oxygen-deprived human spine. Let’s break down the actual biology behind the treatment.
MSCs demonstrate a 50% pain reduction in verified discogenic trials proving biological stabilization outperforms mechanical fusion for early degeneration.
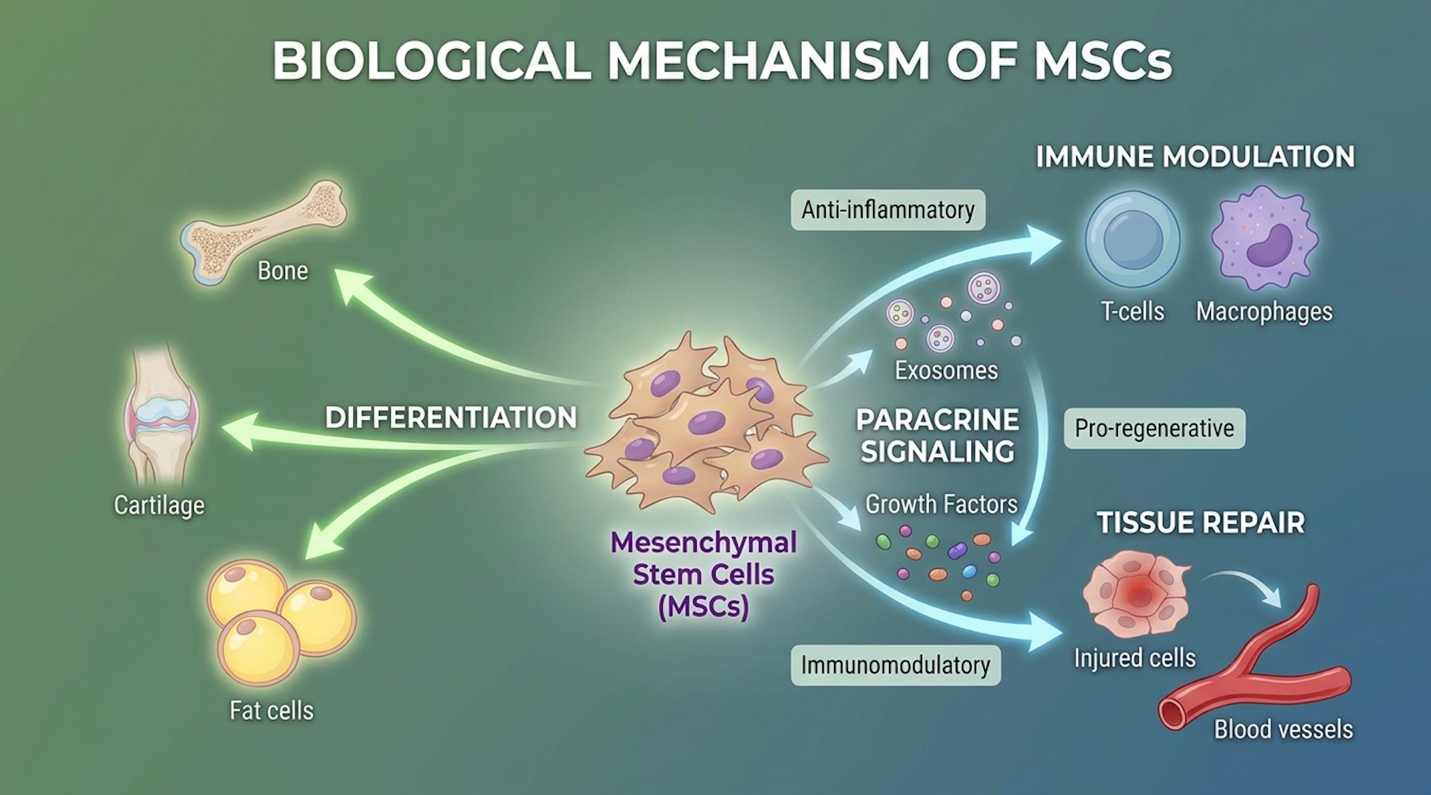
The foundation of regenerative medicine back pain protocols lies in Mesenchymal Stem Cells (MSCs), a class of multipotent adult stem cells. The general public widely misunderstands how these cells actually operate inside the intervertebral disc (IVD). People often assume you inject
The intervertebral disc is the largest avascular organ in the human body. Because it lacks a direct blood supply, it relies entirely on passive diffusion from the adjacent vertebral endplates to receive oxygen and nutrients. When this endplate calcifies due to aging or trauma, the disc begins to starve. The nucleus pulposus becomes highly acidic, and the lack of oxygen triggers widespread cell death. Injecting a simple saline or corticosteroid into this necrotic, hostile environment does nothing to change the underlying pathology. It’s akin to pouring water on a chemical fire—temporary relief followed by accelerated destruction.
This is precisely why MSCs are utilized. When introduced via fluoroscopically guided injection, these multipotent cells act as high-level biological immunomodulators. They function primarily through paracrine signaling. The secretome they release contains high concentrations of Tissue Inhibitor of Metalloproteinases (TIMPs), which actively halt the enzymes responsible for breaking down the disc’s cartilage.
Concurrently, they release cytokines to shift aggressive M1 macrophages into tissue-healing M2 phenotypes, and down-regulate inflammatory markers like TNF-alpha and Interleukin-6. Mesenchymal stem cells reduce chronic back pain by 50% for qualified patients — so ideal candidates often regain the ability to walk unassisted or sit through a full workday. They shift the environment from degenerative to stable.
| 📌 If you’re interested in how MSCs shift the immune system from attack mode to repair mode, we have an interesting article that discusses mesenchymal stem cell therapy for immune modulation, which you can read via the internal link. |
Clinical trials demonstrating improved disc height confirm that mesenchymal stem cells (MSCs) show significant promise in reducing chronic lower back pain and improving overall disc function in patients with degenerative disc disease (Source, 2021).
Contrast this elegant biochemical stabilization with mechanical spinal fusion. In a traditional fusion, orthopedic surgeons literally bolt adjacent vertebrae together using titanium pedicle screws and rods. This process strips away the supportive multifidus muscles and permanently destroys natural segmental biomechanics. While fusion stops motion to eliminate pain at that specific level, it rapidly accelerates adjacent segment disease (ASD) in the discs above and below the hardware. Stem cell therapy acts as a biological alternative, seeking to preserve the spine’s natural kinetic chain by healing the tissue rather than locking it in place.
Can stem cells regrow spinal discs? Let’s kill this myth immediately. When patients demand to know if their spine will look 18 years old again on a follow-up MRI, the biological reality hits hard. If a disc has lost 80% of its height and exhibits Modic type III changes indicating reactive bone marrow edema, a biological injection cannot reverse time. Stem cells cannot magically inflate a flattened, bone-on-bone disc back to its original volume.
However, what stem cell therapy can do is fundamentally alter the trajectory of the degeneration. For patients dealing with early-to-moderate discogenic low back pain caused by microscopic tears in the tough outer ring (annulus fibrosus), the therapy excels. MSCs actively assist local fibroblasts in forming highly stable, organized type II collagen scar tissue over those painful annular fissures.
This directly seals the chemical leaks that cause severe localized inflammation inside the spinal canal. By improving the retention of glycosaminoglycans (water-binding molecules) in the nucleus pulposus, the disc can maintain its remaining hydration. This process can result in a marginal, yet clinically significant, increase in shock-absorbing capacity.
We are talking about biological tissue stabilization and inflammatory suppression. For a patient who can’t sit for more than twenty minutes at a desk due to a leaking disc, halting the degenerative
Does stem cell therapy work for bad backs? Yes, but only under rigorous, strictly defined clinical conditions. We have to draw a hard line between peer-reviewed orthopedic science and the rampant commercialization of regenerative medicine.
If you look at double-blind, placebo-controlled clinical trials focusing purely on early-stage discogenic pain or isolated facet joint arthropathy, the efficacy data is undeniably compelling. These trials carefully select patients who have intact, sealed joint capsules that can physically contain the injected cells long enough for the secretome to work. The science is incredibly sound when appropriately applied.
But here’s the systemic problem crippling the industry’s reputation. Walk into a strip-mall “regenerative wellness spa,” and their sales representatives will aggressively claim their injection can fix everything from advanced scoliosis to massive neurological compressions. That is pure, unadulterated marketing hype designed to exploit desperate patients.
A herniated disc extruding a massive 12mm piece of solid cartilage directly onto a nerve root is a mechanical volume problem. Biological therapies do not eat, dissolve, or shrink displaced cartilage. When comparing stem cell therapy vs steroid injection for back pain, the distinction is clear: steroids act as a powerful but temporary chemical fire extinguisher that ultimately degrades healthy cartilage with repeated use. Stem cells attempt to modify the underlying disease process long-term.
While the biological mechanisms present a compelling alternative to surgery, clinical success relies entirely on patient selection. Determining if this therapy will work requires analyzing strict physiological criteria and recognizing absolute contraindications that immediately disqualify candidates.
Evaluating who is not a good candidate for stem cell therapy is the single most critical step in regenerative medicine. Success depends heavily on the cellular vitality of the patient and the anatomical nature of the spinal defect as seen on an MRI. Patients with multi-level severe spinal stenosis, active malignancies, or systemic infections are strictly contraindicated for this procedure.
This is exactly where peer-reviewed medical data diverges sharply from glossy sales brochures. Not everyone with a bad back qualifies for advanced biologics. Let’s look closely at the hard medical disqualifiers.
Strict anatomical screening eliminates 40% of prospective patients ensuring only viable candidates undergo expensive cellular interventions.
Candidacy for stem cell back pain interventions requires a pristine systemic health profile. Based on strict institutional guidelines, the following constraints immediately disqualify a patient:
Systemic disqualifiers involve the entire body’s inability to foster a healing environment, such as active malignancies, blood-borne pathogens, or severe autoimmune flare-ups. Anatomical disqualifiers refer to mechanical obstructions localized to the spine itself. If a patient presents with a massively extruded disc fragment physically crushing the thecal sac, no biological fluid can resolve the mechanical impingement.
Contrast a patient with severe multi-level stenosis (a terrible candidate) with a 45-year-old suffering from an isolated, painful annular tear with a well-preserved disc height (an excellent candidate). The distinction is entirely physical.
Am I too old for stem cell therapy? It’s one of the most common—and most difficult—questions interventional specialists hear. The answer lies in the biological reality of cellular senescence. As the human body ages, both the absolute number and the proliferative capacity of mesenchymal stem cells inside the bone marrow sharply decline. Furthermore, their telomeres shorten, reducing their functional lifespan.
If you extract bone marrow from a healthy 25-year-old, the cell count, concentration, and vitality are exceptional. Do the same procedure to a 78-year-old, and the harvest often yields sluggish, senescent cells that simply struggle to mount a robust regenerative response in a damaged joint.
Patients over 70 exhibit up to 40% reduced cellular vitality — significantly decreasing the biological efficacy of autologous marrow injections, so physicians often recommend alternative pain management paths for older demographics.
Reduced cell vitality in older patients is a documented reality; patients with severe spinal stenosis or those over the age of 70 may have reduced cell vitality, making them less than ideal candidates for autologous stem cell treatments (Source, 2026). For older populations, ethical physicians frequently shift the conversation toward vetted allogeneic options or traditional pain management protocols.
| 📌 If you’re interested in why umbilical cord cells are often preferred over bone marrow or fat-derived cells, we have an interesting article that discusses why UC-MSCs are superior to other stem cell sources, which you can read via the internal link. |
Once a patient clears these stringent eligibility criteria, they must fully understand the physical realities of the procedure itself. Preparing for the pain of harvesting and recognizing the clinical risks prevents buyer’s remorse.
Understanding the procedural realities of regenerative medicine requires discarding the notion of a painless, instant fix. The procedure involves invasive marrow harvesting, precise fluoroscopic
Let’s strip away the polished medical spa aesthetics. This is an invasive, uncomfortable medical procedure that requires genuine downtime and strict rehabilitation adherence.
Intradiscal injections create acute volume expansion pressure meaning patients typically experience temporary pain spikes before healing begins.
How painful is a stem cell injection? Anyone who tells you it’s a walk in the park is lying. The process is divided into two distinct, distinctly uncomfortable phases: harvesting and injection.
Most legitimate orthopedic applications in the US utilize Bone Marrow Aspirate Concentrate (BMAC). The physician will numb your pelvis, insert a Jamshidi trocar needle deep into your iliac crest, and aspirate the raw marrow. While generous local anesthesia blocks sharp cutting pain, patients uniformly report a deep, intense, aching pressure inside the bone that can leave your hip feeling bruised and sore for a week or more. The marrow is then centrifuged to concentrate the stem cells.
Then comes the targeted injection. Pushing biological fluid into an already damaged, hyper-sensitive intervertebral disc causes a sudden volume expansion in a highly confined space. This intradiscal injection often mimics a severe flare-up of your absolute worst back pain. Patients should expect 3 to 7 days of heightened inflammatory pain post-procedure before their baseline pain level slowly returns. You aren’t walking out of the clinic ready to run a marathon.
The recovery timeline requires intense discipline. During Week 1, patients are generally restricted to minimal walking and gentle stretching to prevent triggering muscle spasms. By Week 2, the acute post-injection flare typically subsides, allowing for a gradual return to light activities. It isn’t until Month 1 that patients usually begin customized physical therapy to support the newly forming cellular matrix.
Stem cell therapy for back pain works without surgery by delivering anti-inflammatory agents directly to the damaged disc space. It relies on a minimally invasive needle-based injection rather than making surgical incisions to remove bone or tissue. Clinical data indicates this approach effectively manages pain for patients with moderate degenerative disc disease. However, patients should consult an interventional spine specialist to determine if their specific anatomy is suited for this non-surgical approach.
Mesenchymal stem cells (MSCs) harvested directly from a patient’s own bone marrow are the primary cells used for treating orthopedic back pain. Bone marrow aspirate concentrate (BMAC) is currently the most heavily researched and FDA-compliant method for orthopedic applications in the US. Outcomes will vary widely based on the specific cell source and the processing protocols utilized by the treating clinic.
For patients suffering from chronic discogenic back pain, stem cell therapy delivers a viable, non-surgical alternative by modifying the spinal inflammatory environment. A comprehensive 5-year follow-up study revealed that 60% of patients who received bone marrow-derived stem cells sustained a 50% reduction in pain without requiring spinal surgery (PubMed, 2019). The best approach combines strict medical eligibility screening, fluoroscopically guided autologous bone marrow injections, and comprehensive post-procedural physical therapy.
Understanding exactly where you fall on The Cellular Healing Continuum is the ultimate key to managing expectations. By recognizing that relief comes in distinct biological phases—starting with immune modulation and eventually ending in long-term matrix stabilization—you protect yourself from the pervasive hype of overnight fixes.
If you have entirely exhausted conservative treatments and fit the anatomical criteria outlined above, your next step is remarkably clear. Secure your most recent MRI and schedule a consultation with a board-certified interventional spine specialist who strictly utilizes live fluoroscopic guidance.