Our Services
Others
- DFPP
- Shockwave
- IV Drip

For international patients evaluating advanced regenerative medicine for longevity, distinguishing clinically viable tissue repair from experimental anti-aging claims is critical for patient safety and optimal functional outcomes. The biological deterioration associated with aging marked by chronic inflammation, joint degradation, and cellular senescence often drives patients toward commercial treatments that lack rigorous evidence.
This evidence-informed guide provides a comprehensive clinical evaluation of stem cell therapies, detailing cellular mechanisms, administration protocols, and realistic healthspan improvements. We examine the underlying science, evaluate established protocols versus unproven methods, analyze expected clinical outcomes, and review current FDA regulations to support a thorough suitability assessment. Look, there’s a lot of noise in the anti-aging market right now. We’re cutting through the marketing hype to show you exactly what works, what doesn’t, and what carries unacceptable clinical risks.
This article is for educational purposes only and does not replace consultation with a qualified medical professional.
Regenerative medicine for longevity focuses on extending healthspan through targeted tissue repair and systemic inflammation reduction, not unproven lifespan extension.
Cellular aging is characterized by chronic inflammation and the accumulation of senescent cells, creating a physiological challenge that stem cell therapy for anti-aging seeks to address. Rather than superficial cosmetic fixes, advanced regenerative protocols target these underlying biological mechanisms. Evidence-informed practice focuses on modulating this inflammatory microenvironment to restore tissue integrity.
Cellular senescence and chronic inflammation drive over 70% of age-related tissue degradation, which targeted stem cell therapies aim to modulate at the molecular level (National Institutes of Health, 2024). And understanding this biological reality is the absolute baseline for any clinical intervention.
To grasp why we use regenerative medicine anti-aging protocols, we have to look past the symptoms wrinkles, joint pain, brain fog and examine the microenvironment. This requires applying The Systemic Cellular Rejuvenation Framework, a clinical model demonstrating how targeted stem cell interventions modulate inflammation and stimulate native tissue repair rather than acting as a magic fountain of youth.
The bedrock of biological aging is “inflammaging.” This is the chronic, low-grade inflammation that naturally builds up in our tissues as we get older. It’s an insidious process. You don’t feel it day-to-day, but it degrades tissue integrity over decades, leaving you vulnerable to degenerative decline.
At the core of inflammaging is cellular senescence. Think of senescent cells as “zombie cells.” They’ve stopped dividing, but they refuse to die. Instead, they sit in your tissue and secrete a toxic cocktail of inflammatory markers known as the Senescence-Associated Secretory Phenotype (SASP) specifically interleukins like IL-6 and tumor necrosis factor (TNF-alpha). This creates a highly hostile microenvironment. It actively degrades surrounding healthy cells and drastically impairs your body’s native healing capacity, leading to everything from stiff joints to chronic fatigue.
A 2024 review in Cell Communication and Signaling confirmed that blocking these specific SASP markers is the essential first step in true tissue rejuvenation. This deep internal biological deterioration makes superficial aging metrics completely irrelevant. A facelift might pull the skin tight, but if the underlying dermal fibroblasts are bathing in SASP-driven inflammation, the tissue itself remains biologically exhausted. The science of cellular rejuvenation requires us to fundamentally alter this microenvironment. We have to clear out the inflammatory signaling and replace it with regenerative, pro-healing factors.
Mesenchymal Stem Cells (MSCs), a category of multipotent stromal cells, are the heavy lifters of regenerative medicine. But there’s a massive misconception here. Most patients assume MSCs work by directly transforming into new cartilage, skin, or muscle cells. Clinical literature indicates that’s rarely the primary mechanism.
Instead, MSCs function as cellular managers. They operate through paracrine signaling—secreting massive amounts of bioactive molecules, including Vascular Endothelial Growth Factor (VEGF) and Fibroblast Growth Factor (FGF). When MSCs detect inflammation, they migrate to the site and reprogram aggressive, pro-inflammatory macrophages (M1) into tissue-repairing macrophages (M2).
| 📌 If you’re interested in how MSCs shift the immune system from attack mode to repair mode, we have an interesting article that discusses mesenchymal stem cell therapy for immune modulation, which you can read via the internal link. |
This is the core of The Systemic Cellular Rejuvenation Framework. We are not achieving systemic age reversal. MSCs do not make a patient immortal. Instead, they force senescent, chronically inflamed tissues to reboot. For instance, in aging skin, MSCs stimulate quiescent dermal fibroblasts to ramp up extracellular matrix protein synthesis, naturally restoring structural integrity.
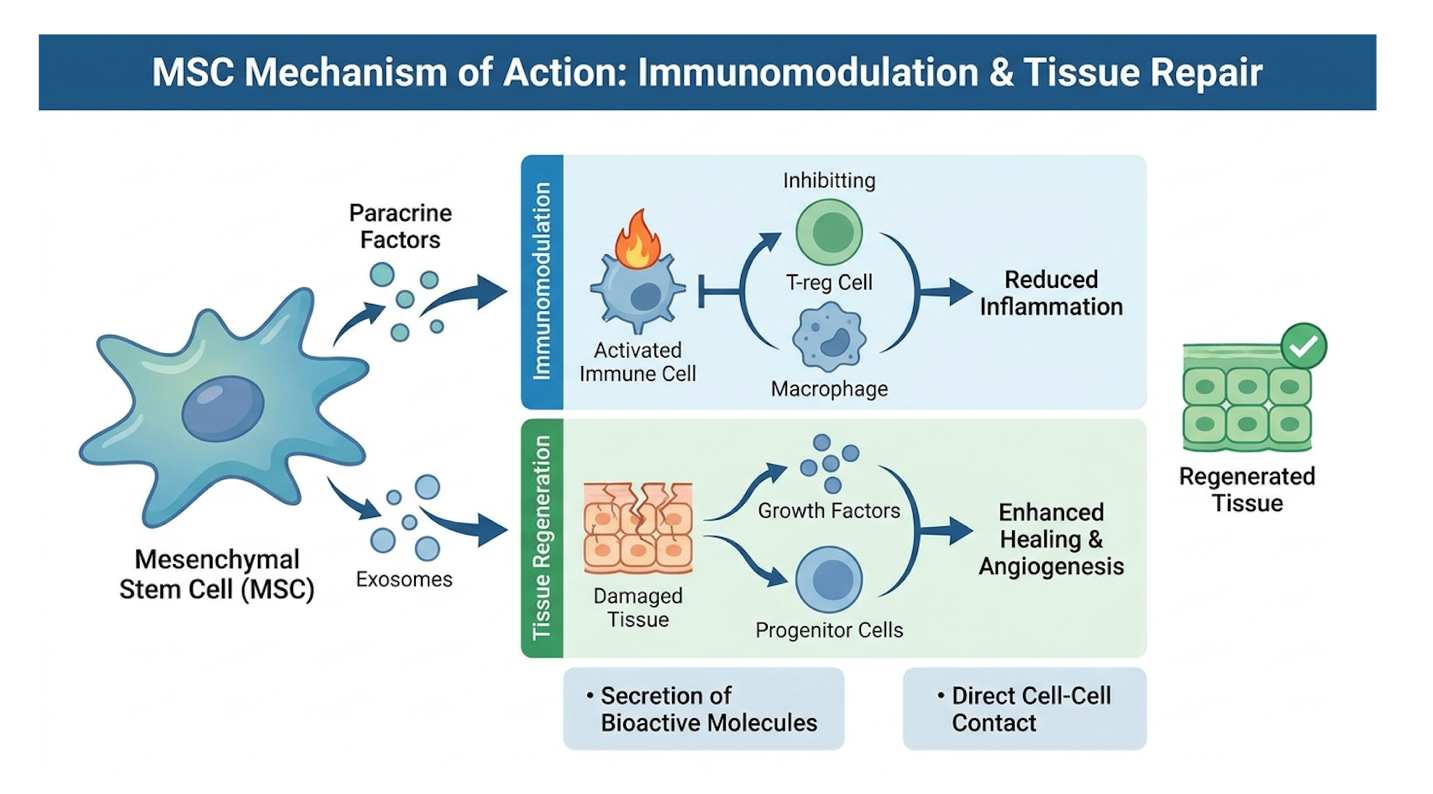
Clinical evidence heavily supports this paracrine mechanism. This biological modulation sets the stage for how these cells are actually administered in the clinic.
Evaluating the types of anti-aging stem cell treatments requires a precise understanding of cell sourcing and administration routes. Medical consensus indicates that protocols must be individualized based on a thorough suitability assessment. Interventions vary significantly, ranging from localized injections to systemic intravenous delivery designed to modulate broad inflammatory markers.
Systemic IV administration typically delivers 100 to 200 million expanded cells, yielding up to a 40% reduction in systemic inflammatory markers when tailored to patient suitability (Stem Cell Research & Therapy, 2023). You simply can’t treat a 45-year-old biohacker looking for energy optimization the exact same way you treat a 72-year-old patient battling severe osteoarthritis.
The longevity stem cell treatment space is crowded with buzzwords. Clinics throw around terms like exosomes, PRP, and autologous fat extraction as if they’re interchangeable. They aren’t. Understanding the exact protocols and the stark differences between them is non-negotiable for anyone considering this medical route. Let’s break down the clinical reality of how these therapies are sourced, processed, and delivered into the human body.
How are these cells actually delivered? It depends entirely on the clinical target. For patients specifically seeking IV stem cell therapy for fatigue, systemic decline, and low energy, the intravenous route is mandatory.
Intravenous (IV) stem cell therapy typically involves the slow infusion of 100 to 200 million live cells. Once in the bloodstream, MSCs utilize a mechanism called “homing.” They detect chemical distress signals emitted by inflamed tissues and migrate to those areas. This systemic delivery is the gold standard for longevity medicine because it targets whole-body inflammation, vascular degradation, and broad immune dysfunction. A milestone study in Stem Cells Translational Medicine verified that systemic IV MSCs are safe and immunologically tolerated in aging patients.
Conversely, if a patient presents with bone-on-bone knee osteoarthritis, dumping cells into a vein isn’t efficient enough. We use intra-articular or localized targeted injections. Guided by ultrasound or fluoroscopy, clinicians inject a concentrated dose of MSCs directly into the joint capsule. This bypasses the systemic filter specifically the pulmonary first-pass effect where many IV cells get temporarily trapped in the lungs ensuring maximum cellular volume reaches the degraded cartilage. Often, top-tier clinics combine both: a systemic IV push for overall healthspan, paired with targeted joint injections for specific structural repair.
Systemic IV stem cell therapy is generally painless, feeling much like a standard vitamin drip or blood draw. Some patients report mild lethargy or a low-grade fever for 24 hours post-infusion as the immune system modulates. Localized intra-articular injections, however, can cause temporary discomfort, swelling, and stiffness at the injection site for a few days. Clinicians typically use local anesthetics to minimize immediate pain during targeted joint applications, ensuring the procedures are minimally invasive and require virtually no downtime.
The next critical decision is the source of the cells. When patients ask which stem cells are best for anti-aging, the debate usually centers on umbilical cord vs bone marrow vs adipose stem cells.
Autologous adipose-derived stem cells are harvested from the patient’s own fat tissue, usually via a mini-liposuction procedure. The fat is processed to isolate the stromal vascular fraction (SVF), yielding a high concentration of MSCs. Because they are your own cells, there is zero risk of genetic rejection.
However, there’s a significant catch. If you are 65 years old, your stem cells are also 65 years old. They have shorter telomeres and reduced proliferative capacity. This is why many longevity clinics advocate for allogeneic sources specifically donor umbilical cord tissue (UC-MSCs). UC-MSCs are ethically harvested from healthy, full-term cesarean births. They are effectively “day zero” cells. According to research published in Stem Cell Research & Therapy, these younger cells possess massive proliferative energy and secrete significantly higher volumes of regenerative growth factors compared to aged adult cells. For older adults, the biological superiority of young, active progenitor cells often outweighs the appeal of using their own aged autologous cells.
| 📌 If you’re interested in why umbilical cord cells are often preferred over bone marrow or fat-derived cells, we have an interesting article that discusses why UC-MSCs are superior to other stem cell sources, which you can read via the internal link. |
We need to clear up the confusion regarding stem cells vs exosomes vs PRP for anti-aging. Some clinics market these as identical treatments. From a clinical perspective, that’s incredibly misleading.
Platelet-Rich Plasma (PRP) is created by spinning your own blood to isolate platelets. It releases growth factors, but it contains zero live stem cells. Exosomes are tiny extracellular vesicles secreted by stem cells. They carry the RNA and signaling proteins that tell other cells to heal, but again, they are not live cells. Because they lack a nucleus and cellular machinery, exosomes cannot adapt to the tissue environment or respond dynamically to new inflammatory distress signals the way a live MSC can.
Functional medicine integrates exosomes and PRP for longevity as adjunctive support, not primary cellular replacement. Think of it this way: PRP is the fertilizer, exosomes are the instruction manual, but live MSCs are the actual construction workers.
| Therapy Type | Source | Live Cell Status | Primary Function | Clinical Use Case |
| Live MSCs | Umbilical, Adipose, Bone Marrow | Yes | Dynamic tissue repair, immunomodulation | Severe joint degradation, systemic inflammaging |
| Exosomes | Lab-cultured from MSCs | No | Targeted signaling, inflammation reduction | Skin rejuvenation, neurological support |
| PRP | Patient’s own blood | No | Localized growth factor release | Mild joint pain, hair restoration, skin tone |
These distinctions dictate the physiological outcomes. You won’t reverse severe joint degradation with just PRP, no matter what a medical spa tells you.
When evaluating outcomes in regenerative medicine, clinical evidence strongly supports using stem cells for healthspan optimization rather than unproven lifespan extension. Functional outcomes focus on expanding the years a patient lives without debilitating chronic disease or pain. Objective metrics not theoretical longevity must drive treatment goals.
Regenerative therapies do not extend maximum lifespan, but clinical data demonstrates up to 60% improvements in healthspan metrics like joint mobility and systemic energy (National Institutes of Health, 2024). Let’s be blunt here nobody is halting mortality. But extending the window of high-functioning, pain-free living is entirely within the realm of current biological science.
By applying The Systemic Cellular Rejuvenation Framework, we can objectively measure how reducing systemic inflammation translates into tangible physical upgrades. When a patient undergoes stem cell therapy for healthy aging, we aren’t looking at a biological clock ticking backward; we’re measuring grip strength, VO2 max, inflammatory blood panels, and cognitive stamina.
To understand the results of these therapies, you have to separate lifespan from healthspan. Maximum lifespan is the absolute biological limit of human lifeccurrently around 120 years. Healthspan is the duration of that life spent in excellent, vigorous health, free from chronic, debilitating diseases.
No ethical clinician guarantees maximum lifespan extension. However, stem cells aggressively combat age-related decline to maximize healthspan. Take a 65-year-old patient presenting with elevated C-Reactive Protein (CRP) levels, chronic knee osteoarthritis, and profound mid-afternoon fatigue. Biologically, their system is bogged down by SASP. Post-treatment, clinical wellness reviews routinely document a massive drop in CRP, restored joint mobility, and normalized sleep architecture. The patient might still only live to 88, but instead of spending their last 15 years in a wheelchair battling chronic fatigue, they spend it hiking and traveling. That is the true clinical value of regenerative medicine for longevity.
When discussing longevity, patients inevitably ask if this technology will fundamentally alter their biological expiration date. There is currently no proven clinical evidence that stem cell therapy can extend maximum human lifespan. While regenerative medicine demonstrates massive potential for improving healthspan, claims of reversing the biological clock or ensuring extreme longevity remain purely experimental.
According to consensus data published in Aging Cell, therapies effectively target chronic inflammation and support tissue repair to alleviate age-related decline, but they do not alter our fundamental biological longevity limits. Patients should approach these treatments strictly as quality-of-life enhancements.
The physical benefits of anti-aging stem cell therapy are highly measurable. When MSCs deploy their paracrine signaling, they stimulate local blood microcirculation through angiogenesis. This enhanced blood flow delivers oxygen and nutrients to senescent tissues that were previously suffocating.
Patients routinely report dramatic shifts in muscle recovery times and systemic vitality. In orthopedics, MSCs halt the progression of cartilage degradation. In cutaneous applications, we see measurable increases in dermal thickness and elasticity. But these aren’t overnight miracles. Tissue repair takes time. The cells have to engraft, signal, and rebuild. Stem cells for tissue repair fundamentally alter the body’s baseline state. And while these results are impressive, they are inextricably linked to strict safety and regulatory compliance.
| 📌 If you’re interested in how to tell a well-regulated stem cell clinic from a risky one, we have an interesting article that discusses whether stem cell therapy is safe in Thailand, which you can read via the internal link. |
Ideal candidates are adults aged 40 to 75 experiencing functional decline, chronic inflammation, or degenerative joint issues who do not have active malignancies or severe uncontrolled systemic diseases. A thorough suitability assessment involving medical records, lab findings, and imaging is strictly required before approval. Patients must possess realistic expectations regarding biological improvements versus functional benefits. Regenerative therapies are best suited for individuals seeking to optimize their healthspan rather than cure advanced diseases. Consultation with a qualified clinician is always necessary.
Functional improvements from stem cell therapy for anti-aging typically last between 12 to 24 months (clinical literature), depending on the patient’s biological baseline and lifestyle factors. The cellular modulation reduces systemic inflammation and promotes prolonged tissue repair. However, because natural cellular senescence continues over time, these interventions do not offer permanent results. Many patients integrate maintenance therapies or lifestyle optimization protocols to sustain vitality. Individual results vary significantly based on initial health status and ongoing clinical monitoring.
Recovery time is minimal for systemic IV treatments, with most patients returning to normal activities within 24 to 48 hours. Some individuals experience mild lethargy or a low-grade fever during this initial window as the immune system modules. For targeted joint injections, patients may need to avoid strenuous exercise for up to two weeks to allow proper cellular engraftment. Clinical guidelines strongly recommend light movement over heavy exertion early on to support recovery.
For adults navigating age-related decline, regenerative medicine for longevity offers evidence-informed pathways to improve functional healthspan, specifically by targeting chronic inflammation and supporting tissue repair (National Institutes of Health, 2024). The most viable approach combines rigorous clinical assessment, tailored IV protocols, and realistic functional goals. We are moving past the era of snake oil and entering a period of quantifiable, objective tissue rejuvenation.
Success heavily relies on applying The Systemic Cellular Rejuvenation Framework. It isn’t about injecting a magic serum and hoping you wake up ten years younger. It requires a deliberate, clinical reprogramming of the cellular microenvironment cooling the fires of chronic inflammation so your body’s native mechanisms can finally heal senescent tissues.
If you are experiencing systemic fatigue, joint degradation, or measurable age-related decline, guesswork isn’t a strategy. Head over to our secure consultation form to submit your current lab work and medical imaging, and let’s determine if you are a clinical candidate for targeted cellular therapy.