Our Services
Others
- DFPP
- Shockwave
- IV Drip

For multiple sclerosis patients navigating the brutal limitations of conventional disease-modifying therapies, international regenerative medicine often appears on the shortlist of alternative options. And frankly, it makes sense. When you’re dealing with plateaued efficacy from standard B-cell depleters or watching your EDSS score creep up, you start looking beyond local clinic protocols.
But evaluating umbilical cord stem cell therapy for multiple sclerosis from afar is incredibly frustrating. The internet is flooded with promotional medical tourism marketing that blur the lines between proven clinical data and experimental hype. Finding objective, unvarnished facts feels nearly impossible.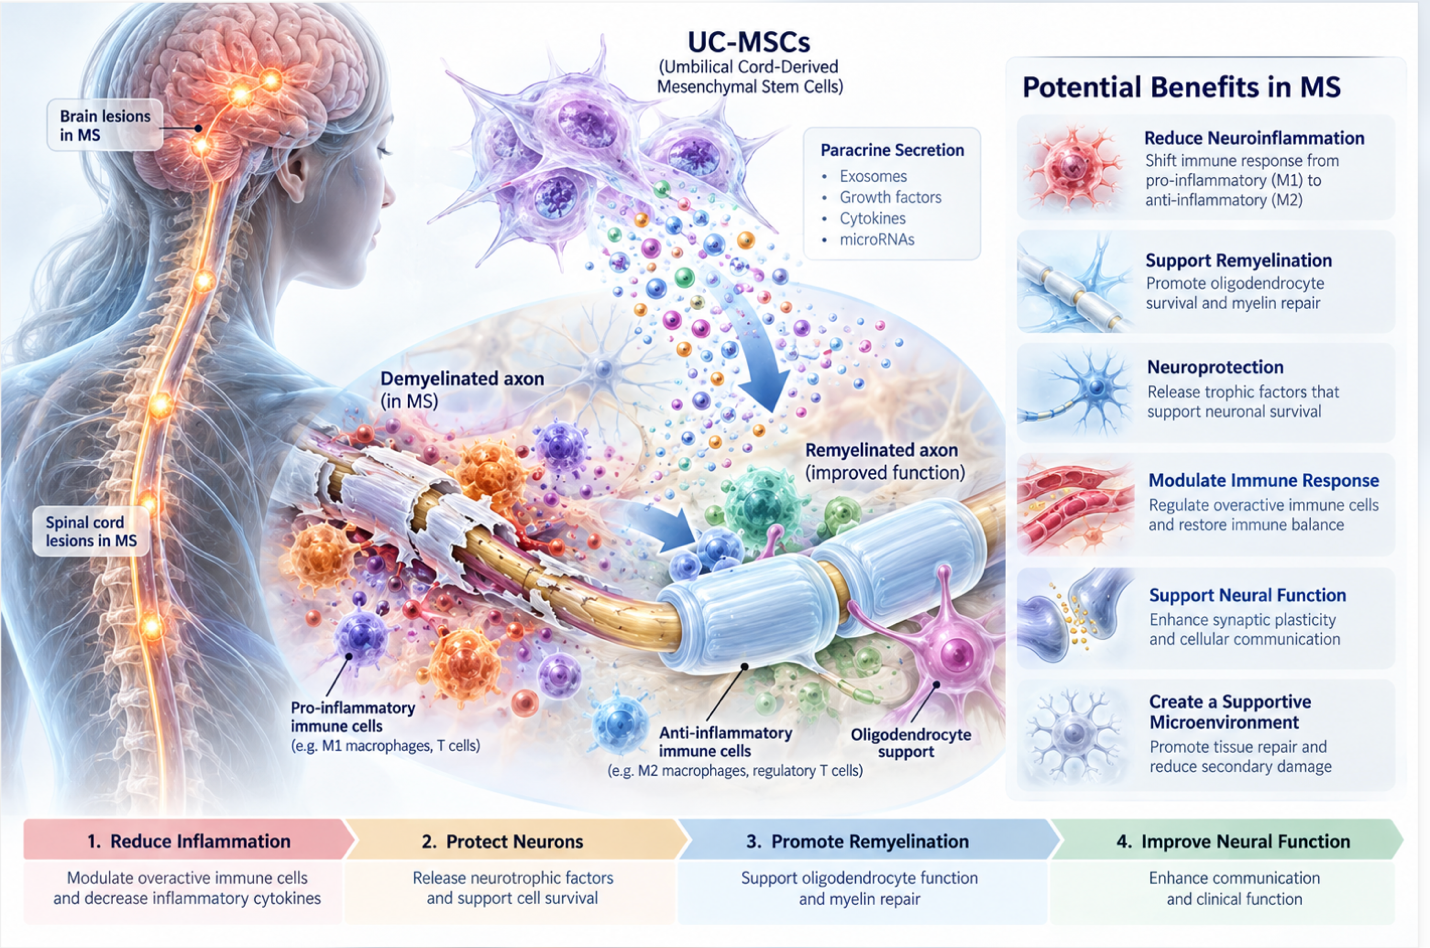
By the end of this guide, you will understand the precise biological mechanisms, regulatory realities, and financial logistics of pursuing stem cell therapy in Thailand. We’re going to strip away the marketing speak. We’ll evaluate the actual clinical evidence for umbilical cord mesenchymal stem cells (UC-MSCs), outline expected treatment timelines, and dissect the $13,400+ baseline cost of medical travel.
Umbilical cord stem cell therapy for multiple sclerosis utilizes intravenous UC-MSCs in an investigational capacity to target neuroinflammation.
UC-MSC stem cell therapy for multiple sclerosis operates primarily through immunomodulation rather than structural neural regeneration. A 2018 NCBI clinical trial demonstrated 70% EDSS stabilization rates proving these cells manage systemic inflammation rather than cure MS entirely. While patients desperately want to know if these cells can definitively reverse MS damage, current data indicates that umbilical cord mesenchymal stem cell transplantation focuses heavily on halting progressive neuroinflammation. This biological reality completely dictates how we must frame realistic patient outcomes and set expectations for international treatment.
Most people assume stem cells work like microscopic construction workers—traveling to your brain, settling into a damaged lesion, and physically turning into brand-new neurons (oligodendrocytes). That’s a fundamental misunderstanding of the current science.
Umbilical Cord Mesenchymal Stromal Cells (UC-MSCs), an abundant source of active progenitor cells, rarely engraft permanently in the central nervous system. Instead, they act as cellular dispatchers through a process called paracrine signaling. When administered intravenously typically at doses ranging from 1 to 2 million cells per kilogram of body weight these cells secrete a highly complex cocktail of bioactive molecules, cytokines, and exosomes known collectively as the secretome.
This secretome fundamentally alters the local immune microenvironment across the blood-brain barrier. Clinical reviews demonstrate how researchers track this phenotypic macrophage “reprogramming” where aggressive, pro-inflammatory immune cells are chemically coaxed into an anti-inflammatory, tissue-repairing state. The process successfully downregulates Th1 and Th17 cell responses while upregulating regulatory T-cells (Tregs).
| 📌 If you’re interested in how MSCs shift the immune system from attack mode to repair mode, we have an interesting article that discusses mesenchymal stem cell therapy for immune modulation, which you can read via the internal link. |
Contrast this specific stem cell treatment for multiple sclerosis with Hematopoietic Stem Cell Transplantation (HSCT). HSCT requires brutal chemotherapy to entirely wipe out and reboot your immune system. You are essentially brought to the brink of profound neutropenia with high-dose cyclophosphamide, running significant risks of severe systemic infections, before your own harvested cells rescue your marrow. UC-MSCs attempt to gently negotiate with the existing immune system to calm the demyelinating attacks without requiring total, life-threatening immunosuppression. University of Cambridge research indicates that intravenous injections of mesenchymal stem cells can help reduce neuroinflammation in patients suffering from active progressive multiple sclerosis.
When you look at the raw umbilical cord stem cell MS clinical trial results, the data tells a nuanced story of disease stabilization rather than a dramatic, overnight reversal.
The Expanded Disability Status Scale (EDSS), a standard method for quantifying MS disability, is notoriously stubborn in progressive disease phases. However, reviewing historical phase II clinical trial data reveals a fascinating and highly relevant pattern. Researchers demonstrated the stabilization of EDSS scores and a notable reduction in inflammatory markers over a 12-month period with no severe adverse events (PubMed, 2018).
Digging deeper into these markers reveals exactly how the paracrine mechanism performs in human subjects. The study tracked specific cytokines in the blood, noting a marked upregulation of anti-inflammatory interleukin-10 (IL-10) by up to 40% in responsive patients. Simultaneously, they recorded a corresponding downregulation of aggressive, pro-inflammatory markers like tumor necrosis factor-alpha (TNF-alpha) and interferon-gamma.
What does “stabilization” actually mean here? It means the disease stops getting measurably worse. In the relentless trajectory of advanced progressive MS, arresting the progression is a massive clinical victory. But it’s vital to separate this stabilization from the concept of a cure. Patients undergoing umbilical cord mesenchymal stem cells for multiple sclerosis often show halted lesion volume growth on their MRIs a critical biological marker that proves the immune assault on the myelin sheath has temporarily ceased.
This brings us to the most important concept in regenerative neurology: The Biological-to-Functional Gap.
The Biological-to-Functional Gap is the critical distinction between measurable biological improvements (like a pristine MRI report showing suppressed inflammatory markers) and meaningful functional recovery (like dropping your cane or regaining lost peripheral vision).
Can this treatment reverse MS damage? In advanced progressive stages where profound axonal loss has already occurred, stem cells cannot magically reconstruct dead nerves. Moving an EDSS score from a 6.0 (requiring a cane for walking) down to a 4.0 requires massive structural remyelination. If axons are completely transected by years of severe demyelination, paracrine signaling cannot bridge that physical void. The biological markers might improve beautifully—with lab reports showing suppressed cytokines—but the functional gap remains because the architectural damage is permanent. For patients with highly active, relapsing-remitting disease where inflammation is the primary driver, the gap is narrower.
UC-MSC therapy is actively investigated for both relapsing-remitting and active progressive multiple sclerosis. Clinical data suggests the most measurable biological responses occur in patients who still exhibit active inflammatory lesions on imaging.
For advanced, non-active progressive MS where the disease is driven more by smoldering neurodegeneration than acute peripheral inflammation the efficacy of immunomodulation decreases significantly. Identifying the correct disease sub-type is absolutely critical before undergoing treatment. Advanced patients must undergo rigorous neurological screening to determine if their specific MS presentation makes them a viable candidate, or if the structural damage is too extensive for paracrine signaling to make a functional difference.
How long does it take for mesenchymal stem cells to work? Mesenchymal stem cell therapy requires a minimum 6-to-12-month evaluation window proving that neurological stabilization is a sustained biological shift. Because UC-MSCs target underlying neuroinflammation rather than providing an instant, pharmaceutical symptom masking, patients must exercise immense patience. Initial biological changes occur under the surface rapidly, but functional improvements require sustained cellular processes. Expecting overnight miracles sets patients up for devastating emotional letdowns.
The timeline following an infusion is notoriously deceptive. During the acute phase roughly weeks one through four the secretome is actively circulating, and systemic inflammation begins to violently shift down. You likely won’t feel this. In fact, due to the stress of international travel fatigue and mild immune infusion reactions, you might actually feel worse for the first month.
The mid-term phase hits around months three to six. This is where clinical reports often note subtle, qualitative shifts: a slight easing of spasticity, a reduction in the crushing weight of MS fatigue, or perhaps fewer bladder spasms.
But remember The Biological-to-Functional Gap. Even if your immune system halted its attack on your myelin on day seven, the central nervous system takes months to attempt any level of remyelination or neural workarounds. This is why neurologists heavily emphasize its experimental status and expected evaluation timelines, noting that mesenchymal stem cell therapy requires several months to accurately evaluate clinical stabilization (Mayo Clinic).
A brutal reality of this disease is that MS is deeply entrenched. As outlined by the National MS Society, MS pathology is driven by complex genetic and environmental immune dysfunctions. Because of this chronicity, how long does stem cell therapy last? The effects of a single UC-MSC protocol almost always plateau over time. It is a potent, temporary management tool, not a permanent cure that deletes the disease from your immune memory.
This leads directly into asking how many times can you do stem cell therapy, or exactly how many UC-MSC infusions are needed for MS. The answer depends heavily on the specific clinic’s protocol, your disease subtype, and your unique biological response.
Many international treatment centers recommend a primary intensive protocol, followed by “booster” infusions every 12 to 24 months to maintain the anti-inflammatory pressure. Some patients achieve multi-year stabilization from a single comprehensive trip, while others see symptom creep at month eight. Long-term, standardized data simply doesn’t exist yet to declare a universal dosing schedule.
| 📌 If you’re interested in whether a second dose can extend the benefits of the first, we have an interesting article that discusses why double-dose UC-MSC therapy may offer greater benefits than a single dose, which you can read via the internal link. |
Umbilical cord stem cells demonstrate clinical potential to help multiple sclerosis by significantly reducing neuroinflammation and actively modulating the immune system. Rather than replacing damaged nerve cells directly, these administered cells secrete powerful proteins that encourage the body’s natural repair mechanisms over time. Early phase trials show they can help stabilize disability scores in certain patients with active lesion development.
UC-MSC therapy is currently being investigated for both relapsing-remitting and active progressive multiple sclerosis presentations. Clinical data strongly suggests the most measurable biological responses occur in patients who still exhibit active inflammatory lesions on their imaging. For advanced, non-active progressive MS without active inflammation, the efficacy of immunomodulation decreases significantly because structural damage outweighs peripheral immune attacks. Identifying the correct disease sub-type is critical before undergoing any stem cell treatment. Patients must undergo rigorous screening to determine if their specific MS pathology makes them a genuinely viable candidate.
Before committing to an MS stem cell clinic, you should ask for exact details regarding their cell sourcing, laboratory expansion protocols, and formal medical accreditation. Request peer-reviewed clinical data supporting their specific intravenous infusion protocol for multiple sclerosis. Ask about the ratio of live to dead cells in their final product and their procedures for managing adverse immune reactions. Finally, demand absolute clarity on their post-treatment neurological monitoring plans and follow-up schedules.
You must consult your primary home-country neurologist to determine if you can safely maintain your specific MS medication during stem cell therapy. Some disease-modifying therapies (DMTs) severely suppress the immune system in ways that could theoretically interact with the immunomodulatory effects of stem cell infusions. A reputable regenerative medicine clinic will always require coordination with your neurologist to manage your medication schedule. Never discontinue prescribed MS medications without direct, documented medical supervision.
For multiple sclerosis patients researching international options, umbilical cord stem cell therapy for multiple sclerosis offers an investigational pathway focused on systemic immunomodulation rather than instant regeneration. While clinical trials demonstrated 12-month EDSS score stabilization (PubMed, 2018), treatment requires careful logistical planning. The best approach combines thorough neurological consultation, verified JCI-accredited facilities, and a clear understanding of the $13,400+ baseline costs in medical hubs like Thailand.
| 📌 If you’re planning treatment in Thailand and want a practical checklist for choosing a safe clinic, we have an interesting article that discusses whether stem cell therapy is safe in Thailand, which you can read via the internal link. |
Maintaining realistic expectations requires navigating The Biological-to-Functional Gap. While intracellular signaling may rapidly reduce neuroinflammation, patients must prepare for a 6 to 12-month evaluation window to determine if those biological changes translate into meaningful, functional improvements in mobility or fatigue.
If you are considering traveling for regenerative medicine, begin by compiling your most recent MRI results and comprehensive medical history. Book a consultation with your primary neurologist to discuss how investigational UC-MSC therapy might align with your current disease-modifying therapies before engaging with international clinics.