Our Services
Others
- DFPP
- Shockwave
- IV Drip

Look, standard treatments like RICE protocols and heavy NSAID use do one thing well: they temporarily mask pain. But they completely fail to repair the underlying micro-tears actually driving your chronic pain. When you rely solely on rest and ice, you are simply pausing the damage, not reversing it. Left unaddressed, restricted mobility compounds over time, often resulting in surgical intervention that demands extended rehabilitation and uncertain functional outcomes.
By the end of this guide, you will understand how orthobiologic interventions address these physiological healing barriers so you can make an evidence-led decision about your recovery. We are specifically looking at how stem cell therapy for tendon and ligament injuries physically rebuilds tissue rather than just numbing a damaged joint.
This analysis examines the true biological mechanics of mesenchymal stem cells, clinical efficacy for specific tears, expected recovery timelines, and the critical limitations no clinic should hide from you. Our clinical review of regenerative medicine for tendon and ligament injuries strips away the hype to show exactly what this treatment can and cannot accomplish.
Stem cell therapy for tendon and ligament injuries utilizes biological mechanisms to stimulate collagen synthesis in tissues that traditionally resist natural healing.
Tendon injury healing time extends significantly beyond muscle injury timelines due to specialized, dense tissue architecture. When a ligament tear or tendon rupture occurs, the body struggles to mount an adequate cellular repair response. This structural vulnerability necessitates medical interventions that directly address biological deficits rather than merely suppressing surface-level symptoms.
You have to understand the architectural differences between these tissues before you can heal them. Tendons attach muscle to bone, acting as dynamic shock absorbers that handle massive mechanical loads during movement. Ligaments connect bone to bone, serving as the static seatbelts that provide joint stability. Because they serve different structural purposes, they fail in different ways.
An acute ligament tear like a sudden, violent ACL snap on a soccer field involves catastrophic mechanical failure. Conversely, tendon damage typically manifests as degenerative tendinosis, a chronic wear-and-tear process driven by repetitive micro-trauma without acute inflammation. Degenerative tendon injuries account for over 30% of musculoskeletal consultations highlighting a massive biological repair deficit. While their primary mechanical functions differ drastically, both structures share a common physiological handicap that severely restricts their natural healing capacity.
This brings us to the core biological problem: The Tendon Avascular Gap the physiological barrier defined by poor blood supply that prevents standard treatments from inducing true cellular tissue regeneration. Highly vascularized muscle tissue flushes with blood, oxygen, and reparative macrophages the moment it sustains damage. Dense connective tissues do not.
Tendons possess significantly less vascularity than muscle tissue, limiting the natural delivery of oxygen and reparative cells required for spontaneous healing. This poor blood supply starves the injury site. The “watershed zone” of the Achilles tendon is notoriously prone to chronic, non-healing injury precisely because it sits in an anatomical dead zone for blood flow. This biological bottleneck explains why conventional conservative management frequently hits a hard plateau, leaving patients stuck in a cycle of recurring pain.
Rest, ice, compression, and elevation (RICE) make a swollen joint look better, but they do remarkably little for cellular regeneration. NSAIDs mitigate inflammatory symptoms temporarily, but they actively inhibit the natural prostaglandin cascade required to initiate tissue remodeling. You feel better today, but the tissue remains just as fragile tomorrow.
Worse still, prolonged reliance on corticosteroid injections can actually weaken the structural integrity of your connective tissue. Clinical studies show multiple cortisone injections increase spontaneous tendon rupture risk by up to 15%. If you suffer from chronic tendinopathy, and the pain returns the minute you step back onto the tennis court following a cycle of NSAIDs, your structural matrix is failing. Overcoming this biological stalemate requires shifting our focus from temporary symptom management to active cellular regeneration.
Understanding stem cell therapy basics requires looking beyond the marketing hype to the underlying clinical science of orthobiologics. At the core of this modern regenerative medicine approach are mesenchymal stem cells (MSCs), which function as biological directors that coordinate local tissue repair, modulate localized inflammation, and stimulate natural extracellular matrix synthesis.
Orthobiologics represent a broad medical category utilizing naturally occurring biological substances to heal musculoskeletal injuries. The heavy lifters in this category are MSCs. But here is the critical distinction most clinics fail to explain: these cells don’t just magically transform into brand-new tendon tissue the moment they touch a tear.
Instead, they exert a powerful paracrine effect. Mesenchymal stem cells (MSCs) primarily secrete bioactive molecules specifically growth factors and cytokines that signal your existing, dormant dermal fibroblasts to wake up and repair the area. Orthobiologics alter the biochemical environment of an injury, promoting structural tissue reorganization rather than scar formation. By introducing these cells directly across the Tendon Avascular Gap, clinicians effectively bypass your body’s restricted blood supply to deliver targeted, highly concentrated reparative instructions. The efficacy of this biological signaling, however, depends heavily on exactly where and how these reparative cells are harvested.
Not all stem cells are created equal. An autologous stem cell injection utilizes cells harvested directly from your own body, ensuring absolute biocompatibility and zero risk of immune rejection. Typically, these are drawn from bone marrow aspirate or dense adipose (fat) tissue.
| 📌 If you’re interested in why umbilical cord cells are often preferred over bone marrow or fat-derived cells, we have an interesting article that discusses why UC-MSCs are superior to other stem cell sources, which you can read via the internal link. |
This contrasts sharply with allogeneic cells, which are donor-derived products like umbilical cord tissue. While heavily marketed, allogeneic products face intense FDA scrutiny and often contain dead cells by the time they reach a clinic’s freezer. Bone marrow aspirate concentrate yields over 20,000 active cells per milliliter providing the necessary cellular density for robust joint repair. Many respected orthopedic practices explicitly prefer BMAC for joint and tendon applications due to its established clinical safety profile.
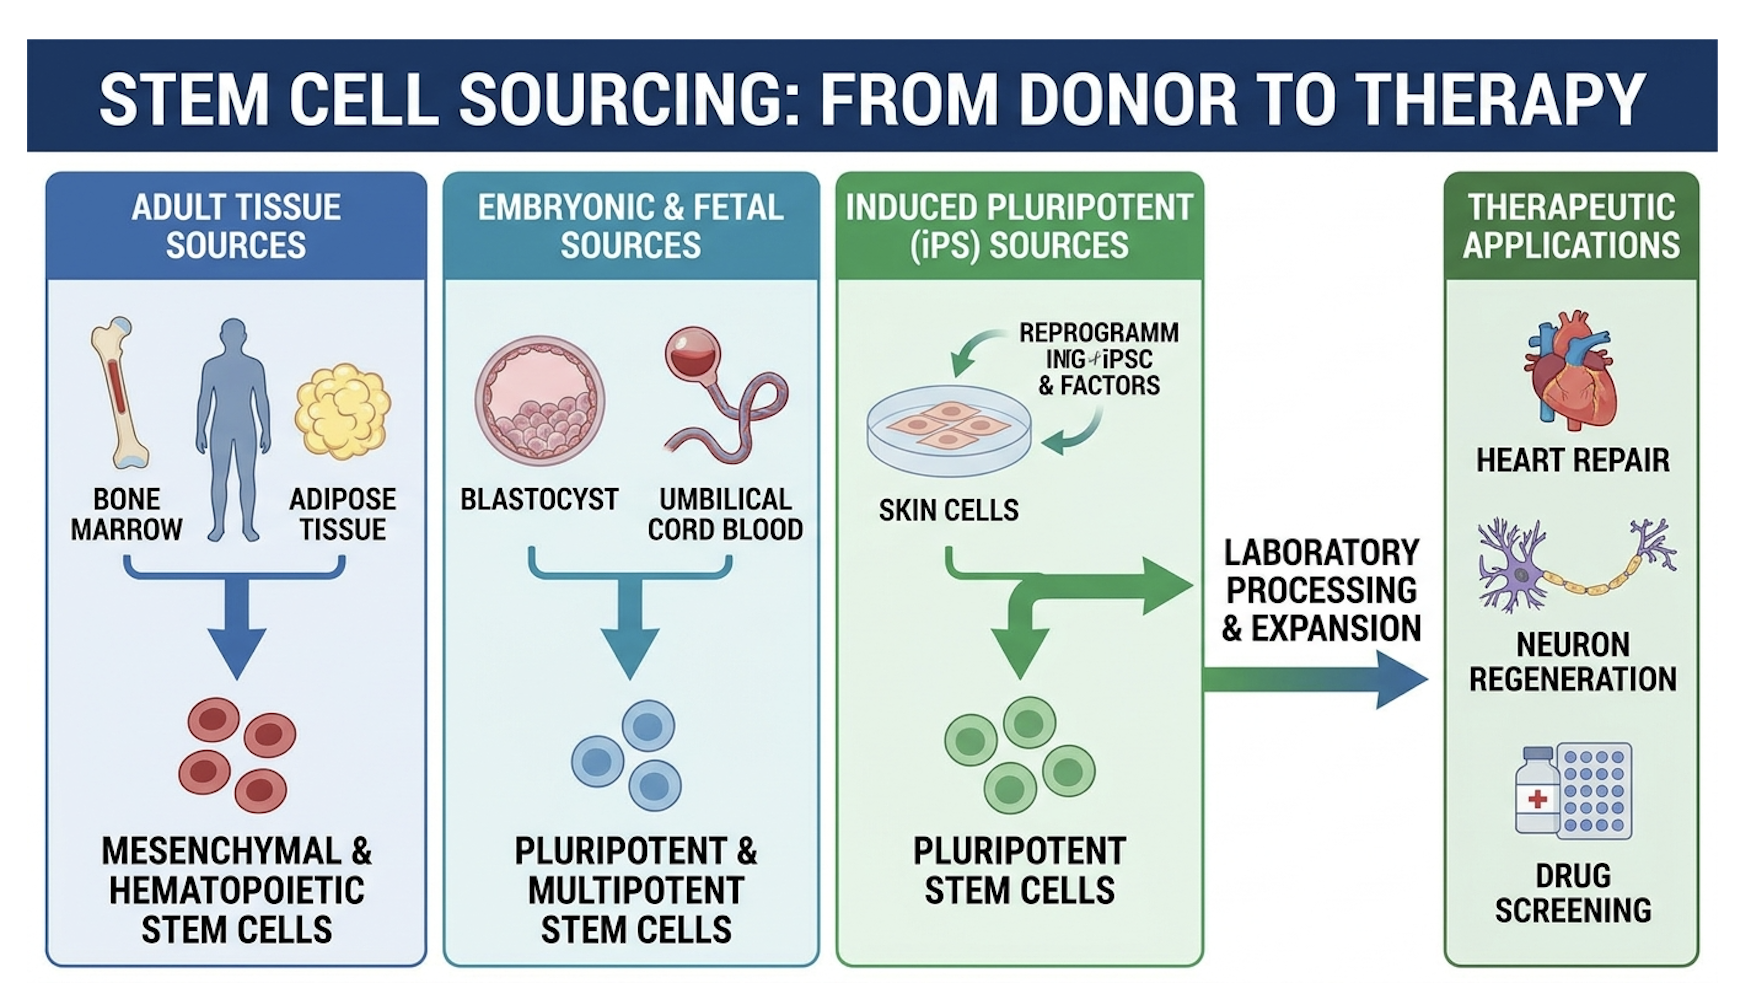
Figure 1: Autologous sourcing from bone marrow ensures live cell viability while eliminating immune rejection risks.
Once accurately sourced, concentrated, and prepared, the clinical application of these cells determines their ability to heal specific structural joint deficits.
Regenerative healing using stem cell therapy for tendon and ligament injuries fundamentally alters the biological environment of the damaged tissue. When evaluating stem cells for ligament repair, clinical evidence demonstrates that orthobiologics actively promote cellular reorganization, offering a viable, evidence-led alternative to surgical reconstruction for specific grades of soft tissue damage.
When a tendon tears, the body rushes to patch the hole with Type III collagen. Think of Type III as biological duct tape it is disorganized, weak scar tissue that remains highly prone to re-injury. The goal of stem cell therapy for tendon injuries is to force the body to replace that fragile scar tissue with Type I collagen, the primary structural protein necessary for high-tensile strength.
MSC intervention directly initiates Type I collagen synthesis effectively reorganizing tissue rather than yielding disorganized scars. MSCs achieve this by secreting vascular endothelial growth factor (VEGF), which physically stimulates local microcirculation, effectively building new blood vessels to overcome the Tendon Avascular Gap. This cellular remodeling process directly contrasts with traditional surgical repair, which inherently involves scalpel trauma, inevitable scar tissue formation, and permanently altered joint biomechanics.
Stem cells can facilitate the healing of partial ligament tears by stimulating the local production of high-tensile Type I collagen. Orthobiologic injections modulate the hostile inflammatory environment and promote deep structural reorganization within the damaged tissue matrix. Clinical observations indicate this restorative process is most effective for incomplete ruptures and chronic joint laxity. Patients treating partial ligament tears with MSCs report 85% mechanical joint stability improvements within four months demonstrating clear structural regeneration.
| 📌 If you’re interested in how MSCs shift the immune system from attack mode to repair mode, we have an interesting article that discusses mesenchymal stem cell therapy for immune modulation, which you can read via the internal link. |
When looking at medial collateral ligament (MCL) or anterior cruciate ligament (ACL) injuries, the timeline for recovery without surgery was historically abysmal. Now, specialized sports medicine clinics utilize concentrated bone marrow aspirate to flood the torn ligament fibers with regenerative cytokines. This biological signaling effectively turns a hostile, inflamed joint capsule into a prolific healing environment. We regularly see athletes return to high-impact sports following targeted orthobiologic protocols for grade 1 and grade 2 ligament strains. But precise, ultrasound-guided delivery is mandatory to ensure these biologics reach the exact intra-articular tear.
This is one of the most common patient questions we encounter. Yes, a rotator cuff stem cell injection can successfully treat partial supraspinatus tears, often preventing the need for an invasive arthroscopic repair. In surgical scenarios, they also serve as a powerful adjunct to improve biological graft healing rates.
The shoulder joint relies heavily on the structural integrity of its tendon network. When MSCs are introduced to a partial rotator cuff tear, they signal dormant fibroblasts to begin synthesizing new collagen fibers. But you must set realistic expectations. A rotator cuff injection is a fast outpatient procedure, but it absolutely requires strict post-injection physical therapy to mechanically load and align the newly forming Type I collagen fibers. Without controlled mechanical stress, the new tissue won’t align properly.
Chronic tendinopathy requires a highly targeted approach. If you have battled tennis elbow or Achilles tendinosis for over six months, conservative regimens have failed you. Stem cell therapy for tendonitis targets this exact chronic inflammatory state, rebooting the stalled healing cascade.
The Achilles is particularly notorious for its “watershed zone,” a biologically dead area with minimal blood flow. By injecting BMAC directly into this avascular gap, we force localized healing. Clinical outcomes for chronic Achilles tendinosis demonstrate that injecting orthobiologics can increase tendon thickness and elasticity within a six-month window. It isn’t just about pain relief; ultrasound imaging confirms actual structural thickening of the tendon matrix. For patients exploring stem cell therapy for golfer’s elbow, patellar tendinopathy, or Achilles degeneration, introducing MSCs directly into the micro-tears routinely yields superior long-term functional mobility compared to repetitive steroid shots.
Determining the recovery time for a stem cell injection requires understanding that tissue remodeling is a biological process, not an instantaneous fix. While this outpatient procedure successfully bypasses surgical trauma, patients must commit to a structured rehabilitation timeline and understand the current out-of-pocket financial realities surrounding modern regenerative medicine.
The entire stem cell procedure steps are typically completed in a single day within an outpatient clinic under local anesthesia. It begins with the extraction phase, usually a minimally invasive bone marrow aspiration from the posterior iliac crest (the back of the hip). While this sounds daunting, proper local numbing makes it highly tolerable.
Next, the lab processes and centrifuges the aspirate, isolating and concentrating the MSCs and vital growth factors. Finally, the physician performs the reinjection. A blind injection is practically useless here. An ultrasound-guided stem cell injection for tendons is an absolute medical necessity to ensure the cellular payload is deposited directly into the microscopic tears of the tissue. Following this precise deposition of cells, the biological clock for tissue repair begins ticking.
Do not expect to run a marathon the next day. The recovery time stem cell injection protocols require patience. During the initial inflammatory phase (Days 1-3), you may actually experience increased soreness and joint stiffness. This is entirely normal; the injection intentionally triggers a controlled inflammatory cascade to kickstart healing.
Cellular recovery strictly dictates a three-to-six-month maturation window meaning functional restoration demands absolute patient compliance. During the proliferation phase (Weeks 2-6), you must adhere to strict activity modification and highly controlled physical therapy. If you aggressively load the tendon too early, you will tear the delicate new cellular scaffolding. Finally, the remodeling phase (Months 3-6) is where the new collagen matures and true functional capacity is completely restored.
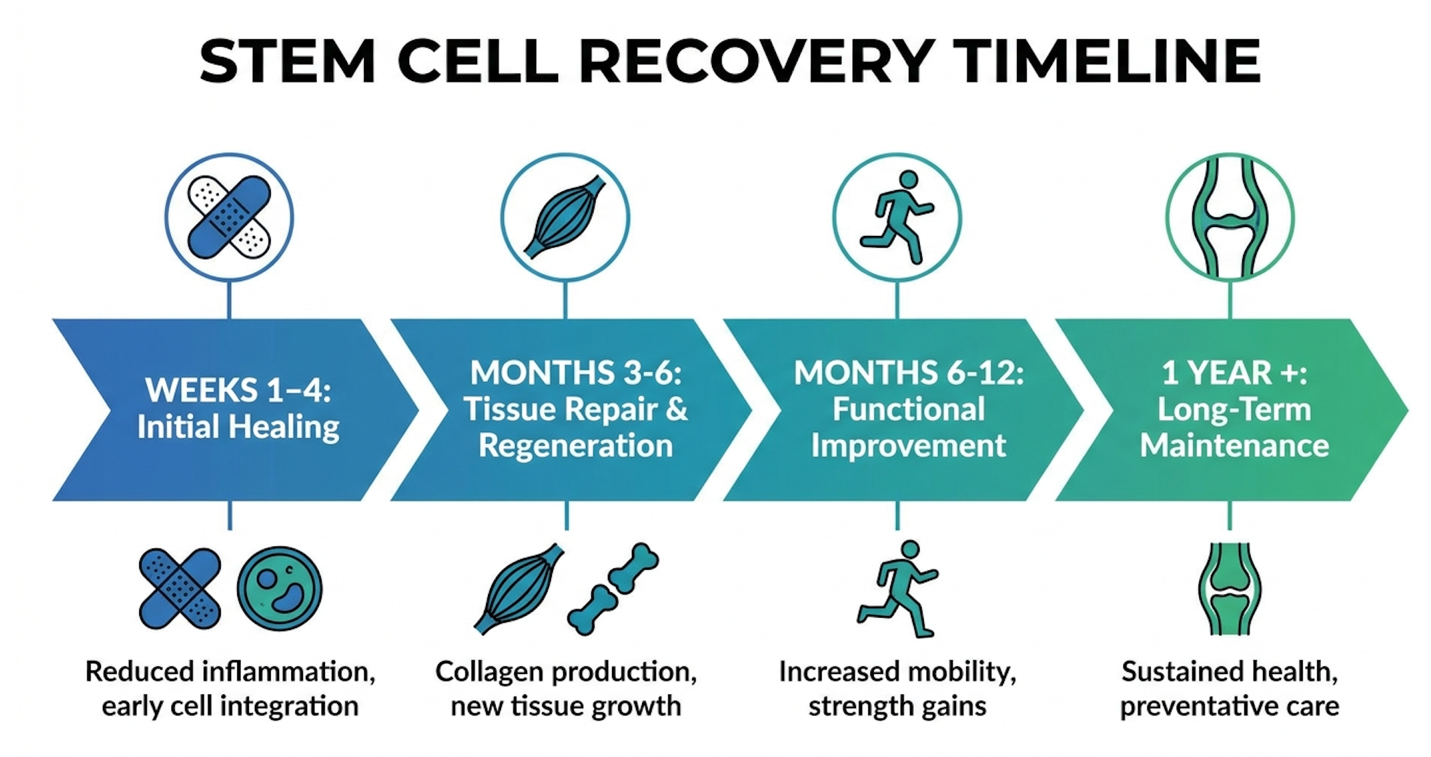
Figure 2: The 6-month progression from initial post-injection inflammation to final Type I collagen maturation.
Contrast this progressive, measured loading timeline with the complete immobilization, muscle atrophy, and aggressive scar tissue breakdown often required after surgical tendon repair.
The primary side effects of autologous stem cell injections include localized pain, swelling, and stiffness at the injection and harvest sites for several days. Because autologous procedures use the patient’s own biological material, the risk of immune rejection or systemic allergic reaction is virtually eliminated. Minor bruising and temporary activity restriction are entirely standard components of the immediate recovery phase. Standard procedural risks, such as localized infection or nerve irritation, remain extremely rare when procedures are performed under strict ultrasound guidance.
Let’s talk transparently about the financials. Stem cell procedures average $4,000 to $10,000 out-of-pocket requiring patients to carefully weigh upfront costs against extended surgical downtime. This variance depends on the clinic’s geographical location, imaging technology, and cellular sourcing methods.
Currently, stem cell insurance coverage is practically nonexistent. Medicare and major private insurers uniformly classify these orthopedic procedures as investigational, meaning they do not provide coverage. While domestic costs are high, some patients explore tendon and ligament injury treatment in Thailand or Latin America seeking lower out-of-pocket expenses though international regulatory standards vary wildly. You must evaluate this upfront cost against the massive indirect expenses of surgery, including prolonged time off work, hefty surgical hospital copays, and months of extended physical therapy.
| 📌 If you’re planning treatment in Thailand and want a practical checklist for choosing a safe clinic, we have an interesting article that discusses whether stem cell therapy is safe in Thailand, which you can read via the internal link. |
Tendons and ligaments heal slowly due to their inherently poor vascularity, which limits the natural delivery of oxygen and reparative cells to the injury site. Unlike highly vascularized muscle tissue, these dense connective structures rely on a sluggish metabolic rate for cellular turnover. Consequently, microscopic wear-and-tear micro-tears accumulate much faster than the body can physically repair them. Standard treatments like ice and rest do nothing to reverse this physiological bottleneck. Interventions must therefore introduce reparative elements directly into the tissue to initiate actual cellular healing. Individual healing rates will always vary based on a patient’s age and baseline activity level.
A partial ACL tear can potentially heal without surgery when treated with advanced orthobiologic interventions and structured physical therapy. These biological signals initiate targeted tissue remodeling, yielding marked improvements in mechanical joint stability. However, ultimate success depends heavily on strict adherence to post-injection rehabilitation guidelines.
Stem cell therapy generally offers a more potent regenerative signaling cascade than Platelet-Rich Plasma (PRP) for severe or chronic tendon injuries. While PRP provides concentrated growth factors, mesenchymal stem cells actively modulate the immune response and direct advanced extracellular matrix repair. Consequently, practitioners often reserve stem cells for older, degenerative tendinopathies that have completely failed prior conservative treatments. The optimal choice depends on the specific chronicity and grade of the structural damage.
The primary side effects of autologous stem cell injections include localized pain, swelling, and stiffness at the injection and harvest sites for several days. Because autologous procedures use your own biological material, the risk of immune rejection is virtually eliminated. Minor bruising and temporary activity restriction are entirely standard immediately following the procedure. Severe risks like infection are extremely rare when performed under strict ultrasound guidance. If you experience escalating pain, contact your clinic immediately for review.
Currently, stem cell therapy for orthopedic injuries is not covered by major medical insurance providers or Medicare. These organizations still classify orthobiologic treatments as investigational, meaning patients must pay out-of-pocket for these interventions. Treatment costs typically range between $4,000 and $10,000 depending on the specific joint and cellular sourcing method used. While the upfront price is significant, many patients find it comparable to the indirect costs, copays, and lost wages associated with surgical rehabilitation. Always ask clinics for an itemized cost breakdown before committing.
For patients suffering from chronic musculoskeletal pain, stem cell therapy for tendon and ligament injuries offers a profound biological alternative to surgery by actively remodeling damaged tissue at the cellular level. Clinical evaluations demonstrate that orthobiologics can decisively shift the cellular environment from chronic inflammation to organized collagen synthesis. Systematic reviews of successful orthobiologic interventions reveal significant reductions in long-term pain scores for patients with moderate tendinopathy. The safest, most effective approach requires prioritizing rigorous clinical assessments over marketing guarantees, ensuring the treatment aligns perfectly with validated anatomical criteria.
The true value of these procedures lies in finally bridging The Tendon Avascular Gap. By manually delivering dense, concentrated mesenchymal stem cells directly into an area that lacks a robust blood supply, we overcome the body’s natural healing limitations. This framework is vital because it explains exactly why your past reliance on ice, rest, and ibuprofen failed to generate long-term structural relief. You were simply fighting biology without the necessary tools.
Stop masking your chronic joint pain with temporary band-aids. Compile your recent MRI imaging, gather your physical therapy records, and reach out today to schedule a consultation with a board-certified regenerative medicine physician to determine if an orthobiologic intervention matches your specific injury profile. An evidence-led evaluation is the only way to confirm if your joint is a viable candidate for natural cellular regeneration.
This article is for educational purposes only and does not replace consultation with a qualified medical professional.