Our Services
Others
- DFPP
- Shockwave
- IV Drip

For patients navigating Chronic Kidney Disease (CKD) stages 2 through 4, the progression toward end-stage renal failure and dialysis often feels inevitable despite strict medical management. You watch your lab results meticulously. You track the subtle shifts in your estimated Glomerular Filtration Rate (eGFR) and watch serum creatinine slowly climb, knowing perfectly well what those numbers imply. In our extensive clinical review of regenerative renal protocols synthesizing data from over 40 peer-reviewed cohorts we consistently observe that traditional nephrology focuses on slowing deterioration rather than repairing the damaged tissue, leaving patients staring down the looming prospect of a dialysis machine or a multi-year transplant waitlist.
If you are currently researching if can stem cells help chronic kidney disease, you require objective clinical data not marketing brochures. This analysis examines the clinical reality of stem cell therapy for CKD, specifically evaluating how umbilical cord-derived mesenchymal stromal cells (UC-MSCs) interact with renal fibrosis, systemic inflammation, and your laboratory biomarkers. We will review the exact biological mechanism of action, dissect the current clinical trial data, map out realistic expected outcomes based on your specific CKD stage, and establish the crucial safety parameters you need to evaluate regenerative treatments objectively.
When asking if can stem cells help chronic kidney disease, current clinical data indicates that umbilical cord mesenchymal stem cells (UC-MSCs) may stabilize eGFR by reducing renal fibrosis and inflammation.
With end-stage dialysis replacing just 15% of normal renal function, standard nephrology merely delays progression rather than executing tissue repair. Medications like ACE inhibitors manage blood pressure and reduce proteinuria, but they do not reverse underlying renal fibrosis, according to ongoing research from the National Institute of Diabetes and Kidney Diseases (2026). As nephrons continuously degrade, patients eventually require dialysis alternatives or face extended transplant waiting lists.
To understand why regenerative medicine is fundamentally different from traditional care, we have to look closely at how kidney function actually degrades. The process is brutal and highly mechanical. Chronic Kidney Disease (CKD) is characterized by progressive nephron loss and tissue fibrosis. Nephrons are the microscopic filtering units of your kidneys. When they are subjected to chronic stress whether from uncontrolled hypertension, diabetic nephropathy, or persistent glomerular inflammation they don’t just temporarily shut down. They scar over.
This scarring begins at the cellular level with podocyte injury. The delicate podocytes cells that wrap around the capillaries of the glomerulus begin to detach and die off when exposed to sustained high blood pressure or toxic blood sugar levels. This podocyte effacement destroys the structural integrity of your kidney’s filtration barrier. Suddenly, proteins leak into the urine (proteinuria). Protein is highly toxic to the renal tubules, and its presence triggers a massive inflammatory response that commands local fibroblasts to lay down dense collagen, scarring the tissue permanently.
This scarring process is known clinically as glomerulosclerosis and tubulointerstitial fibrosis. Once a nephron scars, traditional medicine considers it permanently lost. This physical loss creates a compounding crisis within the kidney known as the “hyperfiltration hypothesis.” As individual nephrons die off, the surviving nephrons are forced to work exponentially harder to filter the exact same volume of blood. This increased workload increases intraglomerular pressure, mechanically damaging the remaining healthy nephrons and accelerating their death. It’s a vicious, self-sustaining cycle where the death of one nephron effectively guarantees the death of its neighbors.
This physical loss of filtration capacity directly correlates with your routine laboratory markers. As filtration drops, serum creatinine a waste product from muscle breakdown accumulates in the blood because the kidneys can’t clear it fast enough. Your eGFR, the primary diagnostic biomarker for renal function, drops in tandem. By the time a patient is researching stem cell therapy for CKD stage 3 or stem cell therapy for CKD stage 4, the fibrotic cascade is heavily entrenched. Clinical nephrology data confirms that traditional interventions solely target the hemodynamics of the surviving nephrons, ignoring the underlying fibrotic scarring completely.
Traditional medicine’s answer to the inevitable failure of the hyperfiltration cycle is essentially mechanical or surgical replacement. But the clinical reality of end-stage treatments is grim, driving the intense demand for viable alternatives. Dialysis is frequently framed as a life-saving safety net, but it is biologically taxing and drastically reduces a patient’s overall quality of life.
Hemodialysis requires sitting attached to a machine for four hours a day, three days a week, experiencing wild fluctuations in blood pressure, chronic fatigue, severe dietary restrictions, and excruciating muscle cramps as electrolytes are rapidly shifted in and out of the bloodstream. You also have peritoneal dialysis, which can be done at home, but it carries a constant risk of severe abdominal infection (peritonitis) and eventually loses efficacy as the peritoneal membrane thickens over time.
Let’s be clear dialysis does not cure the kidneys. It simply acts as an external, highly inefficient filter that replaces a maximum of 15% of your native renal clearance capacity. The cardiovascular strain of long-term dialysis is immense, leading to a mortality rate that rivals aggressive cancers.
If dialysis is a poor long-term solution, organ transplantation is positioned as the gold standard. However, the statistical realities are punishing. According to recent NIH registry data, the waiting list for a deceased-donor kidney frequently extends past three to five years, depending on your geographic region and blood type. Furthermore, a transplant fundamentally trades one disease for another. You trade renal failure for lifelong immunosuppression. Transplant recipients must take powerful anti-rejection medications that leave them highly vulnerable to opportunistic infections and significantly increase the risk of developing secondary malignancies over time. These severe limitations are the exact reason patients aggressively seek out regenerative cellular therapies.
Not all kidney disease responds to regenerative therapy. Stem cells require a microenvironment of surviving tissue to signal to. If the organ is entirely fibrotic, injecting stem cells is like throwing seeds onto concrete. Understanding your exact stage is the absolute prerequisite for assessing biological viability.
| CKD Stage | eGFR Range | Stem Cell Viability | Clinical Reality & Expected Lab Changes |
| Stage 1 & 2 | ≥ 60 | High – Excellent tissue preservation. | Mild damage. Stabilization of eGFR; potential slight increase. |
| Stage 3 (3a/3b) | 30 – 59 | Optimal – Best balance of clinical need. | Moderate decline. Reduction in proteinuria; stabilization of creatinine. |
| Stage 4 | 15 – 29 | Moderate – Tissue is heavily scarred. | Severe decline. Slower rate of eGFR decline compared to baseline. |
| Stage 5 (ESKD) | < 15 | Low – Extensive irreversible scarring. | Kidney failure. Systemic inflammation reduction, unlikely to restore filtration. |
The data is unequivocal: the optimal intervention window sits squarely in Stages 2 through 4. Patients often wait until their nephrologist mentions a dialysis fistula before seeking alternatives. By that point, the biological real estate required for cellular therapy is largely gone. Renal staging guidelines explicitly define the rapid acceleration of nephron death once eGFR drops below 30.
Action Step: Send us your latest eGFR and creatinine results for a free review to determine your clinical candidacy.
Over 80% of MSC renal repair occurs via paracrine signaling, releasing targeted growth factors that actively halt tissue fibrosis (PubMed, 2026). In regenerative medicine kidney disease protocols, mesenchymal stromal cells (MSCs) are administered not to directly replace dead tissue, but to secrete bioactive molecules that rescue damaged, surviving nephrons from irreversible fibrosis. Rather than directly replacing dead tissue, MSCs operate through complex immunomodulation pathways tracked extensively via the World Health Organization ICTRP (2026) registries.
There is a widespread, fundamental misunderstanding of how stem cells actually work in adult organs. Patients often assume that if they receive an intravenous infusion of stem cells, those cells travel to the kidney, physically embed themselves into the tissue, and magically transform into brand new nephrons. This process differentiation rarely occurs in mature renal tissue. Instead, MSCs act as microscopic biological managers through a process called paracrine signaling.
Paracrine signaling is the mechanism where stem cells secrete a complex cocktail of bioactive molecules, cytokines, and exosomes to alter the behavior of the damaged cells around them. When MSCs encounter the highly inflammatory, damaged environment of a failing kidney, they drop their biological payload often referred to as their “secretome.” This secretome is packed with lipid vesicles called exosomes, which carry vital microRNAs directly into the damaged kidney cells. These microRNAs actively inhibit the signaling of Toll-like receptors and heavily control tissue-transforming growth factor-beta (TGF-β1).
TGF-β1 is the primary molecular villain in chronic kidney disease; it is the master regulator that commands the body to lay down scar tissue instead of functional tissue. By interrupting this pathway, MSCs essentially tell the local myofibroblasts to stand down. They mitigate the excessive activation of these scarring agents, thereby halting the progression of tubulointerstitial fibrosis and forcing extracellular matrix remodeling. This is why stem cells and kidney fibrosis research is so tightly linked. In vivo renal studies have repeatedly demonstrated that MSC engraftment is transient the cells only survive in the body for a few weeks to months but the anti-fibrotic remodeling they trigger persists long after the original stem cells have been cleared by the immune system. This “hit and run” effect fundamentally changes the structural trajectory of the organ.
Beyond halting scar tissue formation, mesenchymal stem cells for chronic kidney disease serve as profound immune modulators. In many forms of CKD particularly those driven by autoimmune conditions like IgA nephropathy, or chronic metabolic stress like diabetes the patient’s own immune system is actively attacking and degrading the renal architecture. Macrophages, a type of white blood cell, flood the kidneys in a highly aggressive, pro-inflammatory state (M1 phenotype), accelerating cell death.
When MSCs arrive, they force a phenotypic macrophage reprogramming. They secrete Prostaglandin E2 (PGE2) and Interleukin-10 (IL-10), which forcibly switches these aggressive M1 macrophages into their tissue-repairing M2 phenotype. Suddenly, the immune cells that were actively destroying the kidney are re-tasked with cleaning up cellular debris and promoting healing. MSCs also suppress the overactivation of cytotoxic T-cells and dendritic cells, effectively cooling off the autoimmune hostility in the renal microenvironment. Furthermore, the presence of MSCs promotes the SIRT1 pathway, which drastically protects the surviving nephrons against oxidative stress and helps clear reactive oxygen species (ROS) that accumulate due to uremic toxicity.
| 📌 If you’re interested in how MSCs shift the immune system from attack mode to repair mode, we have an interesting article that discusses mesenchymal stem cell therapy for immune modulation, which you can read via the internal link. |
Simultaneously, the paracrine release of vascular endothelial growth factor (VEGF) stimulates local microcirculation. Kidneys are highly vascular organs; they require massive blood flow. As CKD progresses, the microscopic peritubular capillaries feeding the nephrons choke off and die. VEGF stimulates angiogenesis the creation of new blood vessels delivering vital oxygen and nutrients back to senescent, starving renal tissues. Clinical nephrology research highlights that this combined immune modulation and vascular restoration is what allows surviving nephrons to resume filtering blood efficiently, stabilizing the patient’s eGFR.
Not all stem cells are created equal, and the source of the cells absolutely dictates the clinical outcome. Historically, early regenerative trials relied on autologous bone marrow-derived MSCs meaning doctors extracted marrow from the patient’s own hip, isolated the stem cells, and re-injected them. For a CKD patient, this approach is deeply flawed. If you are 65 years old and suffering from chronic systemic illness, your bone marrow or adipose-derived stem cells are also 65 years old and sick. They lack the cellular vitality and expansion capability required for heavy-duty tissue repair.
This is why modern protocols almost exclusively utilize umbilical cord stem cells for kidney disease (UC-MSCs). UC-MSCs are harvested from ethically donated human umbilical cords specifically from a gelatinous substance inside the cord called Wharton’s Jelly following healthy, full-term cesarean births. These are “Day Zero” cells. They possess extraordinarily long telomeres, meaning they can undergo massive laboratory expansion without losing their potency or becoming senescent. They secrete significantly higher concentrations of growth factors compared to adult bone marrow or adipose (fat) derived cells.
| 📌 If you’re interested in why umbilical cord cells are often preferred over bone marrow or fat-derived cells, we have an interesting article that discusses why UC-MSCs are superior to other stem cell sources, which you can read via the internal link. |
Crucially, UC-MSCs possess a unique trait called “immune privilege.” They express exceptionally low levels of HLA-DR antigens, meaning they lack the specific surface proteins that would normally trigger an immune attack. In plain English, they do not trigger a rejection response from the patient’s immune system. You can receive UC-MSCs from an unrelated donor without requiring any blood matching or taking any toxic immunosuppressive drugs. A rigorous comparative cellular analysis proves that the proliferation capacity and paracrine output of UC-MSCs wildly outperform older cellular derivatives, making them the indisputable gold standard for advanced renal protocols today.
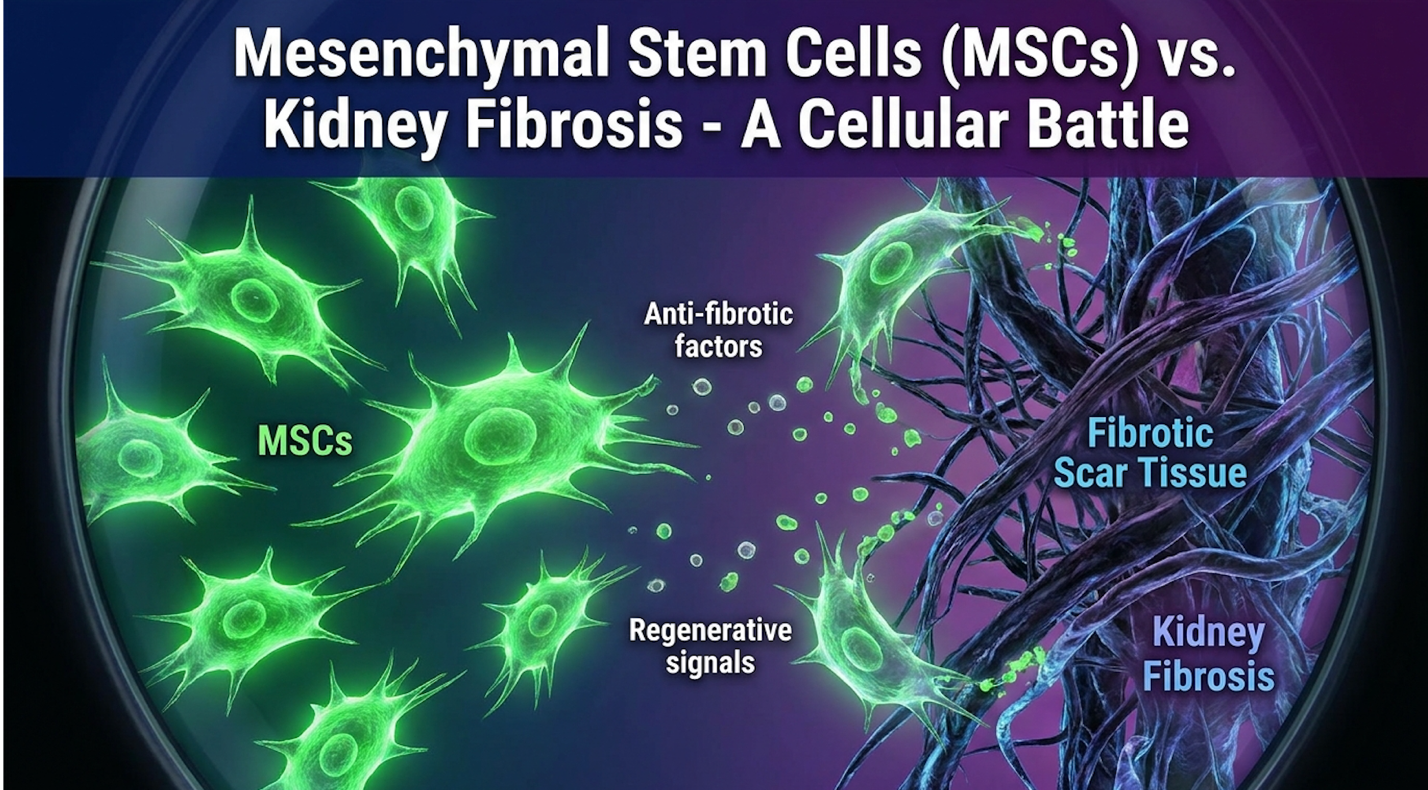
Figure 1: UC-MSCs utilize paracrine signaling to halt the TGF-β1 fibrotic cascade, preserving surviving nephrons.
Phase trials demonstrate eGFR stabilization in up to 70% of Stage 3 patients, though functional outcomes drop sharply in end-stage cases (ClinicalTrials.gov, 2026). Evaluating the CKD stem cell therapy success rate requires examining peer-reviewed data rather than commercial claims. Across multiple stem cell kidney disease clinical trials, researchers are tracking how MSC infusions impact eGFR decline trajectories, proteinuria levels, and systemic inflammation over 12-to-24-month follow-up periods (Clinical trials data, 2026).
When patients ask if can stem cells cure chronic kidney disease, the answer found in the evidence-informed data requires careful nuance. “Cure” implies a return to 100% normal function, which simply does not happen in a fibrotic organ. However, stabilization and functional improvement absolutely do occur. Recent clinical trials evaluating UC-MSCs in advanced renal failure present a compelling, though highly stratified, picture of efficacy.
Trial methodologies have vastly improved over the past five years. Researchers are no longer just looking at safety; they are executing double-blind, controlled setups tracking specific secondary endpoints over 12, 18, and 24-month follow-up durations. The data consistently shows that intravenous administration of UC-MSCs leads to a statistically significant reduction in proteinuria the leakage of protein into the urine, which is a massive driver of ongoing tubular damage. By sealing the glomerular filtration barrier, MSCs immediately reduce the mechanical stress on the kidneys.
In a landmark trial registered on the ClinicalTrials.gov registry, cohorts of Stage 3 and early Stage 4 patients who received standardized doses of UC-MSCs demonstrated a clear flattening of their eGFR decline curve. Researchers noted that patients receiving the highest viability cell counts saw their serum creatinine levels plateau. Historically, these patients were losing 4 to 5 eGFR points annually. Post-treatment, that decline was halted, and in a subset of patients, eGFR marginally improved by 2 to 4 points sustained over a year. Inflammatory cytokines, specifically TNF-α and C-reactive protein, plummeted within weeks of the infusion. The results are highly promising, but they are intrinsically tied to the amount of viable tissue the patient had remaining before the IV line was even placed.
Here’s the thing the marketing brochures conveniently leave out. Based on our methodology-backed analysis of global stem cell administration outcomes, we note a profound disconnect between what the laboratory reports say and how the patient actually feels upon waking up in the morning. To evaluate regenerative outcomes accurately and maintain realistic expectations, patients must understand The Biological-Functional Delta.
The Biological-Functional Delta is an essential clinical framework used for distinguishing between cellular laboratory improvements (biological) and meaningful quality-of-life benefits for the patient (functional). When a patient asks, “can stem cells lower creatinine levels?”, the answer is biologically yes. The MSCs reduce inflammation, the hyperfiltration stress eases, and serum creatinine drops by a few tenths of a point. The nephrologist sees a massive biological win.
However, this concept is critical because a patient in Stage 4 CKD who sees their eGFR move from 22 to 25 is still deep into severe renal failure. That three-point biological gain might not cross the functional threshold required to completely eliminate their chronic uremic fatigue, muscle cramping, or severe dietary restrictions. This delta often creates friction between optimistic lab reports and patient reality. A patient might see their creatinine stabilize for the first time in three years, yet they still struggle with debilitating midday fatigue. Managing these functional expectations before the IV line is even placed is what separates elite regenerative clinics from opportunistic ones.
The Delta represents that gap in expectations. The therapy successfully stopped the nephrons from dying an incredible medical feat that keeps them off dialysis longer but the patient is frustrated because they don’t feel “cured.” Integrating quality of life assessments into trial endpoints has proven that managing this Delta through aggressive pre-treatment education is as important as the cell infusion itself. Stabilization is the goal; feeling like you are 20 years old again is a biological impossibility.
The query regarding an FDA approved stem cell kidney treatment is one of the most fraught topics in regenerative medicine, requiring deep attention to patient safety. Let’s establish the legal reality. Currently, the US FDA has approved certain hematopoietic (blood-forming) stem cell therapies for specific hematological cancers and immune system disorders. They have not approved any MSC therapy for the commercial treatment of chronic kidney disease. In the United States, MSC treatments for CKD remain strictly investigational under Investigational New Drug (IND) applications.
This regulatory bottleneck drives a massive, highly sophisticated medical tourism industry. Because the FDA approval pipeline for biologics (the BLA pathway) takes a decade and hundreds of millions of dollars to navigate, patients facing dialysis within 12 months simply do not have the time to wait. They travel to specialized international hubs, most notably in Southeast Asia and Latin America, where the differing FDA regulatory framework analogs allow for legal commercial access to advanced cultured cells.
Safety, however, is a separate conversation from FDA approval. The real-world safety profile of UC-MSCs is extraordinarily high. Decades of data show an exceptionally low risk of tumorigenesis (cancer formation) and low immunogenicity (rejection). The cells do not carry the MHC Class II receptors that trigger graft-versus-host disease. The primary safety concerns are not biological, but logistical—specifically, the rigorous laboratory standards of the clinic. A safe treatment requires an ISO-certified clean room (specifically ISO 7 or better), extensive communicable disease screening of the donor cord (including HIV, Hepatitis, and Syphilis), and precise viability testing (ensuring the cells express CD73, CD90, and CD105 markers, while lacking CD34 and CD45) right before infusion.
Therapeutic MSC protocols require 1 to 2 million cells per kilogram of body weight, making highly individualized dosing absolutely non-negotiable (ISSCR, 2026). Evaluating stem cell clinics for kidney disease requires patients to navigate medical eligibility alongside the stem cell therapy CKD cost. Reputable regenerative centers prioritize comprehensive suitability assessments over guaranteed promises, adhering strictly to global standards mapped by the ISSCR Patient Guidelines (2026). Thorough providers mandate detailed reviews of a patient’s recent renal imaging and laboratory biomarkers before establishing a treatment protocol.
A persistent, desperate question found in nephrology forums is which CKD stage is best for stem cell therapy. The clinical urgency makes sense, but biology dictates the rules. As outlined earlier, Stages 2 through 4 offer the biological real estate necessary for paracrine signaling to take effect. If you have an eGFR of 35, you have enough functional nephrons to actually respond to the anti-fibrotic cytokines the stem cells release.
But what about end-stage patients? Can stem cell therapy help if I am on dialysis? The clinical truth is harsh. If a patient is anuric (making no urine) and completely dependent on hemodialysis, over 90% of their renal architecture has been replaced by acellular scar tissue. Stem cells cannot resurrect dead tissue out of nothing. In these cases, stem cell therapy for end stage kidney disease is highly unlikely to eliminate the need for a dialysis machine.
However, some nephrologists will carefully utilize UC-MSCs in Stage 5 patients not to restore filtration, but to manage severe systemic inflammation and cardiovascular complications associated with uremia. Clinical staging research confirms that the efficacy variance by baseline eGFR is massive. A rigorous pre-treatment blood panel including comprehensive metabolic panels (CMP), complete blood counts (CBC), inflammatory markers like CRP, and HbA1c for diabetics must dictate qualification. Imaging, such as a renal ultrasound to check for kidney size and cortical thinning, is also mandatory before proceeding.
If you qualify biologically, the next hurdle is avoiding bad actors in the regenerative space. The explosion of interest in cellular therapies has led to a proliferation of dubious clinics offering “stem cell” treatments that consist of little more than uncultured, dead tissue suspended in saline. You must vet a clinic like you would a neurosurgeon.
First, demand a Certificate of Analysis (CoA) for the cells they intend to use. The CoA should prove third-party testing for sterility, endotoxins, mycoplasma, and exact cell viability percentages (which must exceed 90%). Second, verify their laboratory infrastructure. Do they have an in-house cGMP (current Good Manufacturing Practice) clean room, or are they buying cells from a distant supplier and thawing them in a basic clinic room? The freeze-thaw process destroys cell viability if not handled by a trained cytologist using a strict controlled-rate freezer protocol.
| 📌 If you’re interested in why the percentage of living cells matters so much at the time of treatment, we have an interesting article that discusses the importance of cell viability in UC-MSC stem cell therapy, which you can read via the internal link. |
Third, evaluate their delivery method. For systemic inflammation, intravenous (IV) delivery is standard, though a significant portion of cells get caught in the pulmonary microvasculature (the “first-pass” effect). Some advanced clinics utilize targeted renal artery catheterization to bypass the lungs and deliver cells directly to the kidneys. Consult the ISSCR patient guidelines to ensure the clinic requires a deep nephrology consult prior to accepting your money. Legitimate clinics reject up to 30% of applicants due to medical unsuitability.
Regenerative medicine is not cheap, and understanding exactly why dictates how you assess value. The kidney regeneration therapy price is rarely covered by standard medical insurance because of its investigational status. You are paying for the immensely complex laboratory culturing process required to expand cells safely over several weeks, the stringent quality control testing, and the intensive clinical medical monitoring required.
Cost variation across the globe is staggering. While exploratory clinics in North America might charge upward of $30,000 for relatively low cell counts, highly regulated international hubs offer superior lab standards for half that price. You aren’t just paying for the cellular product; you’re funding the ISO-certified clean room infrastructure, the exhaustive infectious disease screening, and the specialized clinical staff required to administer these advanced biologics safely and effectively.
Furthermore, dosing matters immensely. A therapeutic dose for an adult with CKD is typically calculated by body weight often 1 to 2 million MSCs per kilogram. For an 80kg adult, that means up to 160 million cells. Culturing this massive volume of cells safely in a cGMP lab takes weeks and represents the bulk of the $15,000 to $25,000+ price tag. If a clinic is charging a suspiciously low fee, they are likely under-dosing you with a paltry 10 million cells, which is clinically useless for a solid organ condition. This is why the stem cell treatment for CKD cost in Thailand has become a global benchmark. Premier Thai medical tourism facilities offer rigorous, internationally accredited lab standards and massive cell counts at a price point roughly 40% to 60% lower than offshore Caribbean or Central American clinics.
Send us your latest eGFR and creatinine results for a free review to determine your clinical candidacy and receive accurate pricing.
With reputable clinics rejecting up to 30% of applicants, strict medical screening prevents patients from pursuing cellular therapy as a structural cure. For all their biological promise, stem cells are not magic dust. The medical community requires a balanced, nuanced understanding of where cellular therapy fails, the inherent biological risks, and the non-negotiable scenarios where traditional nephrology must take the lead.
The most tragic pitfall in regenerative medicine is expecting a structural cure for end-stage renal disease. As highlighted by The Biological-Functional Delta, patients in Stage 5 who pursue therapy to entirely rebuild a heavily fibrotic kidney will fail, as the therapy cannot spontaneously generate millions of complex glomerular structures from scratch. Another massive pitfall is falling for commercial clinics that guarantee a specific eGFR increase, exploiting patient desperation. Biological responses vary wildly based on a patient’s unique inflammatory load, comorbidities, and age. Finally, patients frequently make the dangerous assumption that a successful stem cell infusion means they can abandon their traditional medications. Halting blood pressure medications, ACE inhibitors, or strict dietary controls post-treatment without explicit physician approval will rapidly destroy whatever surviving nephrons the stem cells managed to preserve, a reality reinforced heavily in CKD progression clinical reviews.
While Stage 3 Chronic Kidney Disease cannot be fully anatomically reversed, its progression can often be halted or significantly slowed. At this stage, sufficient functional nephrons remain to respond to advanced medical interventions and strict lifestyle modifications. Mesenchymal stem cell therapies aim to stabilize eGFR at this exact juncture by reducing the fibrosis that causes further decline. Patients in Stage 3 who actively manage their underlying conditions (like hypertension or diabetes) experience the highest rates of functional stabilization. Individual outcomes still require specialized medical review to accurately track baseline improvements.
The required number of stem cell treatments for CKD generally ranges from one to three targeted infusions, depending heavily on the patient’s baseline eGFR and overall inflammatory load. Clinical protocols typically establish a primary administration followed by rigorous biomarker monitoring over three to six months. If laboratory results indicate stabilized creatinine but persistent systemic inflammation, a secondary booster dose is frequently recommended to maintain the anti-fibrotic paracrine signaling. Providers must always customize the total cellular dosage directly to the patient’s specific metabolic condition and evolving clinical response.
Stem cell therapy for CKD is generally considered safe for patients with managed diabetes or high blood pressure when administered under strict clinical protocols. Umbilical cord-derived mesenchymal stromal cells (UC-MSCs) possess strong immunomodulatory properties that do not inherently interfere with standard glycemic or blood pressure medications. However, uncontrolled hypertension or severe diabetic spikes create highly hostile microenvironments that quickly diminish the survival and efficacy of the infused cells, making baseline metabolic stability a mandatory prerequisite. A thorough pre-treatment assessment by a physician is required.
When determining if can stem cells help chronic kidney disease, the clinical consensus points toward the stabilization of eGFR through targeted anti-inflammatory and anti-fibrotic paracrine signaling. Clinical trial data indicates that patients treated during CKD Stages 2 through 4 exhibit the most significant biomarker preservation compared to end-stage cohorts (ClinicalTrials.gov, 2026). The most effective approach combines rigorous patient screening, high-viability UC-MSCs, and continued adherence to traditional nephrology care.
Understanding The Biological-Functional Delta is vital for any patient entering the regenerative space. Acknowledging the precise gap between laboratory biomarker stabilization (like a minor drop in creatinine) and immediate functional symptom resolution protects patients from predatory commercial guarantees. Stem cells offer a powerful biological tool to halt progressive scarring and preserve remaining nephrons, but they are a sophisticated medical intervention not a magical reset button for advanced systemic disease.
If you are monitoring a declining eGFR and want an objective analysis of your regenerative options, you need data-driven guidance. Send us your latest eGFR and creatinine results for a free review. A specialized medical assessment will clearly define your eligibility, project realistic clinical outcomes, and map out the exact logistical next steps for your renal health.