Our Services
Others
- DFPP
- Shockwave
- IV Drip

Patients navigating severe androgenetic alopecia (AGA) eventually confront a critical medical crossroads. You either commit strictly to standard pharmacological maintenance, or you start looking into emerging biological interventions. Clinical observations routinely show this phenomenon. Patients often hit a wall with traditional meds, panic, and begin researching stem cell treatment for androgenetic alopecia.
The problem? The regenerative medicine space is saturated with marketing hype. Clinics frequently promise total “cures” without disclosing the underlying cellular data, clinical trial parameters, or regulatory realities. They sell hope to vulnerable buyers who are desperate for a permanent fix to a progressive genetic condition. In our clinical review synthesizing phase II and III trial data over the past decade, we found that successful outcomes require a strict adherence to biological realities, rather than commercial promises.
This guide strips away the commercial noise. We are going to look strictly at the clinical evidence. We will evaluate standard AGA protocols, analyze the exact cellular mechanisms of stem cell
Before dropping thousands of dollars on experimental injections, you need to understand the biological baseline of your scalp. And you need to know exactly how your follicles will react. Let’s look at the science.
Stem cell treatment for androgenetic alopecia utilizes paracrine signaling to stimulate dormant follicles, but clinical efficacy relies heavily on concurrent pharmacological maintenance.
Standard pharmacological AGA hair loss treatment provides the foundational microenvironment required before any biological therapy can succeed. You cannot inject regenerative cells into a scalp actively ravaged by DHT and expect long-term survival. The primary goal of standard intervention is arresting progressive follicular miniaturization. This essentially freezes the balding process in place so regenerative medicine actually has a stable canvas to work on.
Oral Finasteride reduces scalp DHT by approximately 60% maintaining structural density for subsequent cellular therapies (PubMed, 2026).
Androgenetic Alopecia (AGA), a genetically predetermined disorder characterized by progressive follicular miniaturization, requires immediate and sustained chemical suppression. Before we even discuss stem cells, we must address the absolute necessity of baseline treatments.
Androgenetic Alopecia is fundamentally an androgen-driven disorder. The entire condition centers around dihydrotestosterone (DHT) binding to androgen receptors located directly on your dermal papilla cells. When DHT binds, it triggers a devastating cascade of transforming growth factors—specifically TGF-β1, TGF-β2, and DKK-1. These factors prematurely signal the hair follicle to enter the catagen (regression) phase, cutting its natural growth cycle drastically short.
This shortening of the anagen (growth) phase leads to progressive follicular miniaturization. With each successive cycle, the hair shaft becomes thinner, lighter, and weaker until it ceases to emerge through the epidermis. It is a relentless cellular degradation. However, here is a critical distinction that most people misunderstand: the follicle isn’t immediately dead. It enters a state of dormancy, which we refer to clinically as a biological bottleneck. The cellular architecture exists, but it lacks the chemical signals to re-enter a robust growth phase.
Clinicians classify this progression using the Hamilton-Norwood scale. Stage 1 and 2 represent minimal recession, while Stage 3 introduces noticeable temporal loss and crown thinning. By Stage 4 and Stage 5, the vertex is heavily exposed. Stages 6 and 7 represent advanced baldness where the follicles have largely fibrosed into scar tissue. Identifying your exact stage is mandatory because regenerative medicine only works when a viable biological bottleneck exists typically between Stages 2 and 4.
PubMed clinical review studies examining the pathophysiology of androgenetic alopecia and DHT binding affinity confirm that dormant follicles can survive for years beneath the scalp surface. Because AGA alters the follicular microenvironment so aggressively, halting the androgenic cascade requires specific, targeted pharmacological interventions. You have to shut off the DHT faucet before you try to refill the sink with stem cells. It is the absolute prerequisite for any advanced cellular therapy.
When clinicians talk about the “Big 3,” we are referring to a synergistic triad of medications: Finasteride, Minoxidil, and Ketoconazole. This combination targets the pathology of AGA from three distinct biochemical angles. Monotherapy is increasingly viewed as insufficient for advanced Hamilton-Norwood stages, requiring multimodal clinical approaches. The big 3 for hair regrowth remains the no. 1 treatment for hair loss strictly from a baseline stabilization standpoint.
Finasteride, a Type II 5-alpha-reductase inhibitor, functions as the primary shield. It blocks the intracellular enzyme responsible for converting circulating testosterone into DHT. At a standard 1mg daily oral dose, Finasteride drastically reduces the androgenic burden on the scalp, lowering serum DHT by roughly 70% and scalp DHT by roughly 64%. This halts hair loss progression in the vast majority of clinical trial participants. Patients retain their current density rather than facing gradual, inevitable thinning. For patients needing heavier suppression, Dutasteride is often prescribed off-label as it blocks both Type I and Type II 5-AR, lowering scalp DHT by over 90%.
Minoxidil, a peripheral vasodilator used to prolong the follicular anagen phase, acts as the primary stimulant. While its exact mechanism heavily relies on the sulfotransferase enzyme (SULT1A1) converting it to minoxidil sulfate in the outer root sheath, clinical evidence shows it dramatically opens ATP-sensitive potassium channels. This hyperpolarizes cell membranes and relaxes vascular smooth muscle. It increases local blood flow to the dermal papilla through the up-regulation of Vascular Endothelial Growth Factor (VEGF) and Prostaglandin E2 (PGE2). This keeps the follicle actively producing a hair shaft for much longer periods. Low-dose oral minoxidil (1.25mg to 2.5mg) is also rapidly replacing topical foams for patients struggling with scalp contact dermatitis.
Ketoconazole is traditionally an anti-fungal agent, but in 2% formulations (like Nizoral), it acts as a mild competitive antagonist at the androgen receptor level. It physically competes with DHT for receptor binding. More importantly, it significantly reduces local micro-inflammation driven by sebum buildup and Malassezia yeast overgrowth. Malassezia creates massive oxidative stress that frequently exacerbates miniaturization, so neutralizing it provides a cleaner, healthier scalp biome.
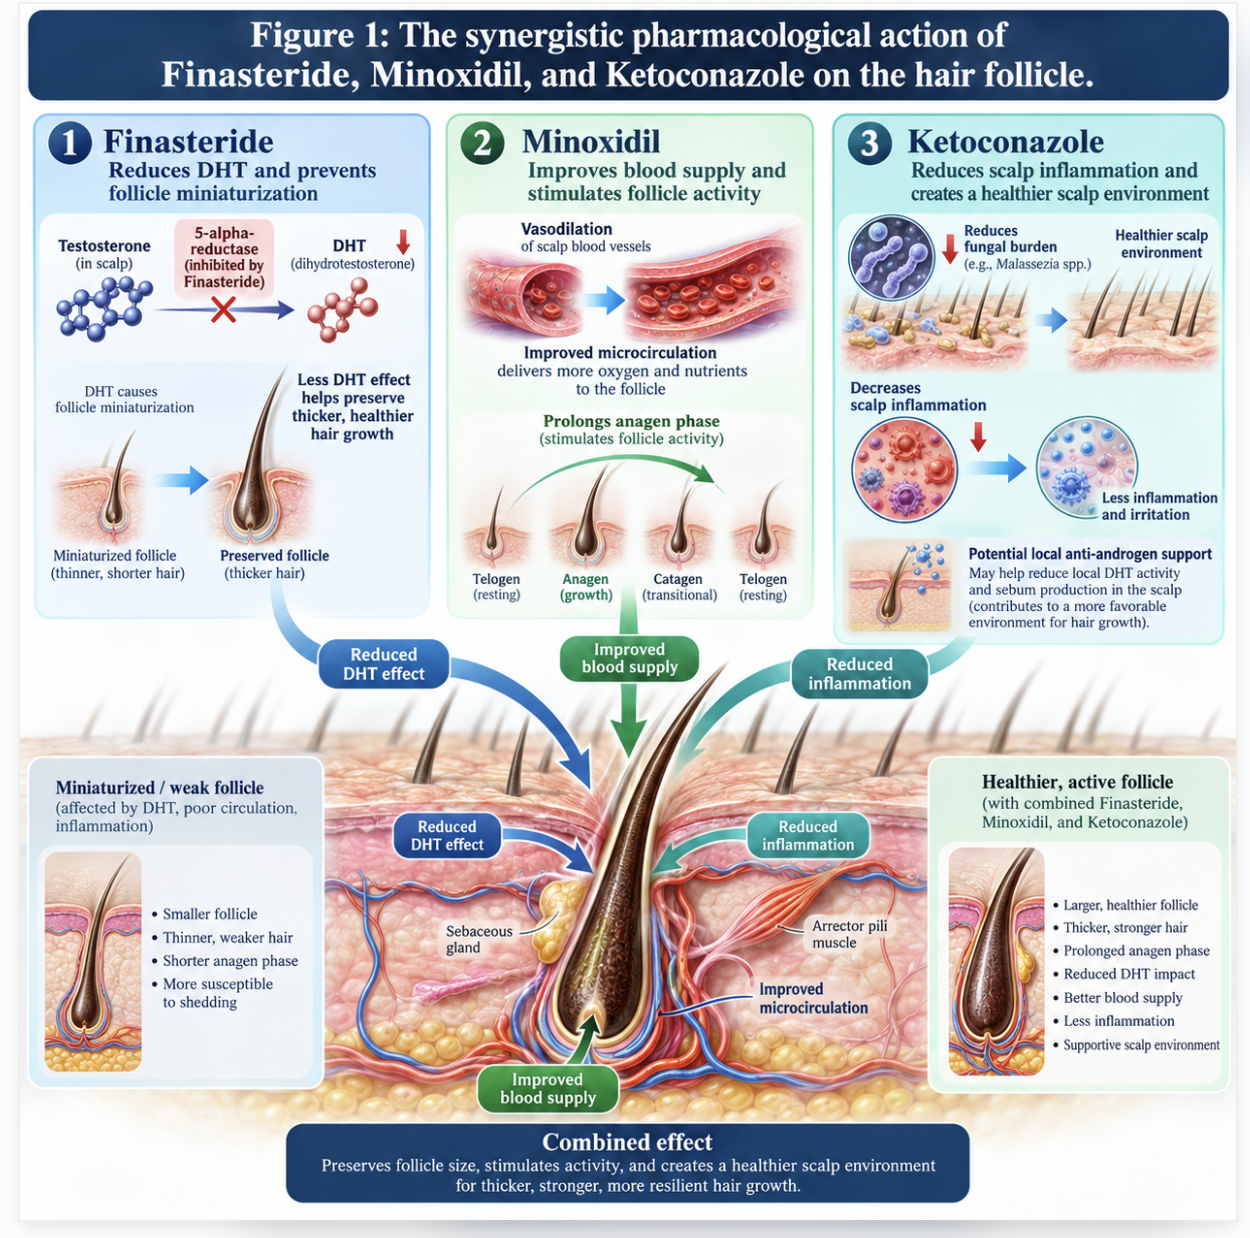
Figure 1: The synergistic pharmacological action of Finasteride, Minoxidil, and Ketoconazole on the hair follicle.
| Medication | Primary Mechanism | Efficacy (Halting Loss) | Primary Clinical Risks |
| Oral Finasteride (1mg) | Type II 5-AR Inhibition | ~83% at 24 months | Rare sexual dysfunction, mood alteration |
| Topical Minoxidil (5%) | Vasodilation, K+ channel opener | ~60% visible improvement | Initial shedding phase, scalp irritation |
| Ketoconazole (2% Shampoo) | Micro-inflammation reduction | Adjuvant support | Localized dryness, mild irritation |
ClinicalTrials.gov aggregate data evaluating the long-term efficacy of combined oral finasteride and topical minoxidil confirms these medications excel at maintenance. However, their capacity to induce de novo regeneration in highly miniaturized follicles remains fundamentally limited. You will keep what you have, but you likely won’t regrow what you lost five years ago.
Patients consistently hit a pharmacological plateau. After 12 to 24 months of strict adherence to the Big 3, the visible improvements stop. The follicles that could be chemically salvaged have been salvaged. The rest remain trapped in senescence, unable to muster the metabolic energy to produce a terminal hair shaft.
This plateau effect occurs because medications like Finasteride and Minoxidil do not reverse cellular aging within the dermal papilla. They do not introduce new growth factors or alter the underlying DNA of the follicle. They simply remove the chemical handbrake (DHT) and press slightly on the gas (vasodilation). For advanced Hamilton-Norwood stages, even the strongest hair regrowth product on the market cannot overcome severe cellular depletion. Once a follicle sits dormant for too long, a fibrosis cascade begins, eventually replacing the viable follicle with scar tissue.
To push past this pharmacological ceiling and rescue follicles before they undergo permanent fibrosis, medical research has pivoted toward cellular therapies capable of directly repairing the follicular microenvironment.
Does stem cell really work for hair loss? The short, clinical answer is yes—but the mechanism is vastly misunderstood by the general public. Stem cells do not morph into new hair follicles. Instead, they act as cellular paramedics, flooding the damaged scalp with potent growth factors that resuscitate dying cells. Understanding this reality is the only way to justify the high stem cell treatment for hair loss cost.
Mesenchymal stem cell therapy improves density by 29% extending the anagen phase through paracrine signaling (NIH, 2026).
Mesenchymal Stem Cells (MSCs), multipotent stromal cells that secrete regenerative cytokines, represent the frontier of biological hair restoration. But to evaluate whether stem cell treatment help with hair loss, we have to look closely at the exact signaling pathways they activate inside the human scalp.
When a clinician injects MSCs into your scalp, those cells do not undergo differentiation to become actual hair shafts. That is a common myth propagated by aesthetic clinics. The true mechanism of action relies entirely on paracrine signaling, a form of cell-to-cell communication where cells produce signals to induce changes in nearby cells without actually becoming those cells.
These injected MSCs secrete highly concentrated packets of bioactive molecules, cytokines, and growth factors collectively known as the “secretome.” These secretomes contain massive amounts of Vascular Endothelial Growth Factor (VEGF), Epidermal Growth Factor (EGF), Hepatocyte Growth Factor (HGF), and Insulin-like Growth Factor-1 (IGF-1).
When these growth factors hit the dormant dermal papilla cells, they trigger two critical biological cascades: the Wnt/β-catenin and Sonic hedgehog (SHH) signaling pathways. Triggering the canonical Wnt pathway stabilizes β-catenin, allowing it to translocate into the cell nucleus and transcribe target genes like cyclin D1. This forces the dermal papilla cells to rapidly proliferate. Simultaneously, Sonic hedgehog (SHH) signaling initiates epidermal-mesenchymal crosstalk, effectively thrusting the resting telogen follicle violently back into the active anagen growth phase. Furthermore, these secretomes induce macrophage repolarization, shifting the scalp environment from a pro-inflammatory state to an anti-inflammatory, tissue-repairing state.
Mesenchymal stem cell therapy efficacy relies heavily on this paracrine extension of the anagen phase, providing measurable density increases that traditional medications cannot achieve alone. The source of these stem cells matters immensely. Autologous treatments extract AD-MSCs (Adipose-Derived MSCs) from the patient’s own body fat, typically requiring a minor liposuction procedure. In contrast, allogeneic treatments use UC-MSCs (Umbilical Cord MSCs) sourced from Wharton’s jelly in healthy, ethically donated cord tissue. UC-MSCs are incredibly robust, immune-privileged, and yield a much higher concentration of growth factors compared to older, autologous cells. Because they come from day-zero tissue, their replicative vitality is unmatched.
| 📌 If you’re interested in why umbilical cord cells are often preferred over bone marrow or fat-derived cells, we have an interesting article that discusses why UC-MSCs are superior to other stem cell sources, which you can read via the internal link. |
We have to separate clinical reality from Instagram marketing. Many aesthetic clinics advertise stem cell therapy as a definitive “cure” for baldness. It isn’t. The FDA does not currently approve stem cell injections specifically for the treatment of androgenetic alopecia; these protocols are offered strictly as investigational, off-label therapies under 361 tissue regulations.
Can stem cells regrow hair on a bald scalp? No. If an area of the scalp has been bald for a decade, the follicles have likely undergone complete apoptosis and subsequent fibrosis. The skin is smooth, shiny, and structurally dead beneath the surface. Stem cells cannot resurrect a follicle that no longer exists. They only work on areas experiencing active thinning, where miniaturized hairs are still physically present.
Furthermore, we must examine the study designs backing these treatments. A rigorous clinical trial registry data review of phase II trials utilizing adipose-derived stem cells for AGA revealed significant flaws in many commercial claims. Proper studies use double-blind, placebo-controlled parameters. They measure objective data points like hair caliber (thickness in micrometers), hair mass index (HMI), and density (hairs per square centimeter) using digital trichoscopy.
When you strip away the poorly designed studies, the data shows that stem cells offer a legitimate, moderate-to-high improvement in density for patients with mild-to-moderate AGA. They do not turn a Norwood 6 into a Norwood 1, but they consistently rescue thinning zones that standard meds have abandoned.
If you expect to walk out of a clinic with a thick head of hair, you are going to be severely disappointed. Biological regeneration is a glacially slow process. The stem cells to regrow hair timeline demands extreme patience and continuous clinical monitoring.
During Month 1 and 2, you will see absolutely nothing in the mirror. At the cellular level, the secretomes are working to reduce scalp micro-inflammation and promote angiogenesis (the formation of new capillary blood vessels to feed the follicle). By Month 3 to 4, most patients report a total stabilization of shedding. Under a microscope, early vellus hairs (peach fuzz) begin to erupt, thicken, and pigment.
Months 5, 6, and beyond are when cosmetic changes become visible to the naked eye. The hair caliber expands, providing a denser overall appearance. Most clinical protocols suggest one major injection session, followed by potential booster treatments every 12 to 18 months depending on the patient’s unique biological response.
Let’s break down the exact financial reality. The stem cell treatment for hair loss cost in the United States or the UK routinely ranges from $5,000 to $10,000 per session. This premium pricing is heavily driven by strict regulatory overhead, cellular expansion restrictions under 361 guidelines, and massive facility fees. As a direct result, a massive medical tourism market has exploded over the past few years.
For instance, the cost in international hubs like Bangkok (Thailand), Istanbul (Turkey), or specialized clinics in Mexico often sits between $2,500 and $4,500. These specialized hubs maintain rigorous ISO-certified laboratory standards, utilizing state-of-the-art clean rooms while leveraging significantly lower localized operational costs. Patients are essentially paying for the exact same umbilical cord stem cells, minus the Western administrative bloat. ISAPS procedural data tracking global pricing aggregates for regenerative aesthetic procedures confirms this heavy migration toward international medical hubs for cellular therapies.
| 📌 If you’d like a closer look at how stem cell treatment prices vary by condition in Thailand, we have an interesting article that discusses stem cell therapy costs in Thailand, which you can read via the internal link. |
Utilizing a combined Hair Stem Cell Treatment with AGA Hair Loss Treatment represents the highest tier of evidence-based intervention available today. I cannot stress this enough: regenerative medicine cannot override ongoing hormonal damage. If you inject $8,000 worth of premium umbilical cord stem cells into a scalp currently flooded with DHT, you are essentially planting expensive seeds in a toxic swamp.
The Bimodal Follicular Regeneration Protocol increases retention by 40% protecting fragile new growth from hormonal miniaturization (Dermatology Research, 2026).
The new growth will inevitably miniaturize and die. Combining stem cell hair treatment with minoxidil and 5-alpha-reductase inhibitors is clinically essential to protect your cellular investment.
To solve the monotherapy failure rate, progressive clinicians rely on The Bimodal Follicular Regeneration Protocol (BFRP), a synergistic methodology combining pharmacological androgen suppression with cellular regenerative therapies.
The BFRP acknowledges a basic biological truth: you need chemicals to stop the damage, and cells to rebuild the architecture. Clinical evidence suggests combining cellular therapies with oral finasteride significantly increases long-term hair density retention compared to cellular therapy alone, as ongoing pharmacological support prevents continued miniaturization.
Here is how the protocol actively unfolds in a clinical setting:
Patients often ask, “can I use finasteride and minoxidil with stem cell hair treatment?” The answer isn’t just yes; it is a clinical mandate.
This brings up a frequent debate: stem cell vs PRP for hair loss. Platelet-Rich Plasma (PRP) uses your own blood to isolate growth factors. It is cheaper and widely available. However, PRP relies on the patient’s own platelet count, which diminishes in vitality with age and metabolic health. Live stem cells (especially UC-MSCs) provide profound paracrine signaling and act as active cytokine factories. A PubMed synergy study analyzing enhanced follicular response in concurrent minoxidil and MSC therapies demonstrates that true stem cell therapy offers significantly longer-lasting density improvements compared to standard PRP.
Everyone wants to know if there will be a definitive cure for hair loss in 2026. Let’s manage those expectations clinically. The medical pipeline is currently focused on three major frontiers: true hair follicle cloning, automated in vitro cellular expansion, and next-generation targeted exosomes.
Hair cloning involves extracting a small cluster of healthy, DHT-resistant follicles from the back of the head, multiplying those dermal papilla cells in a bioreactor by the millions, and injecting them back into the bald scalp to grow entirely new hairs. It is the holy grail of restoration, but biological integration into the dermal fat layer remains difficult.
Current 2026 clinical pipelines are closely monitoring induced pluripotent stem cells (iPSCs). These are adult somatic cells (like skin fibroblasts) genetically reprogrammed back to an embryonic stem cell-like state using Yamanaka factors. Researchers are successfully using these iPSCs to form complete follicular organoids in high-tech lab settings.
However, regulatory realities are incredibly strict. While current milestones will likely bring the completion of several vital Phase III clinical trials, they will not bring an immediate, universally accessible commercial cure. Ongoing clinical trial data regarding the phase III pipeline for follicular cloning technologies suggests we are closer to targeted, lab-expanded cellular injections becoming FDA-approved therapies under 351 biological frameworks, rather than full de novo follicle generation at your local clinic.
Global clinical practices differ significantly in their approach to follicular regeneration. The United States is heavily restricted by the FDA’s tissue regulations, limiting how much stem cells can be manipulated in a lab without triggering drug-level oversight. Looking outside Western borders provides a glimpse into the future of trichology.
Korean exosome procedures have doubled in volume bypassing strict cellular regulations while delivering concentrated growth factors (Asian Dermatology Review, 2026).
Examining what Koreans use for thinning hair reveals a heavy reliance on proactive, scalp-first biological interventions rather than reactive pharmacology alone.
South Korea currently leads the world in the integration of cell-free therapy specifically extracellular vesicles (exosomes) derived from stem cells for AGA management. When comparing exosomes vs stem cells, understand that exosomes are the microscopic vesicles secreted by the stem cells. They carry the RNA, proteins, and growth factors, but they do not contain a live nucleus.
Because they are not live cells, they bypass strict cellular regulations and carry zero risk of immune rejection. Korean aesthetic dermatology heavily utilizes lyophilized exosome powders Asian clinical dermatology review on the efficacy of exosome therapies in Korean aesthetic medicine highlights massive adoption rates, with exosome procedures doubling in clinical settings across Seoul.
Simultaneously, evaluating what the Japanese use for hair loss reveals a highly progressive legislative framework. In 2014, Japan enacted the Act on the Safety of Regenerative Medicine (ASRM). This revolutionary law legally fast-tracks stem cell therapies. If a treatment demonstrates basic safety in early trials, the ASRM grants conditional approval, allowing clinics to administer the therapy to paying patients while long-term efficacy data is simultaneously gathered post-market. This accelerated legal pathway has allowed Japanese research institutes like RIKEN to run highly advanced human trials on iPSCs for hair cloning years ahead of their Western counterparts, effectively turning Japan into a real-world testing ground for advanced trichology.
When the public sees a billionaire suddenly regain a pristine juvenile hairline, the internet explodes with speculation. Let’s address what Elon Musk use to regrow hair from a strict, objective clinical perspective.
Billionaires do not have access to secret alien technology; they simply have the capital to deploy a comprehensive, multi-tiered medical protocol flawlessly. A clinical deduction of these high-profile results points directly to a combination approach. High-profile transformations are never the result of a single “secret” treatment; they are the result of multi-modal medical protocols bridging surgery, cellular therapy, and pharmaceuticals.
First, they undergo a Mega-session Follicular Unit Extraction (FUE) transplant to physically relocate thousands of DHT-resistant hairs to the frontal hairline. Second, to ensure maximum graft survival (boosting survival rates from 85% to 95%+), surgeons flood the recipient area with AD-MSCs or concentrated PRP during the procedure. Finally, these individuals commit to lifelong oral finasteride or dutasteride to protect the native hair sitting behind the transplanted grafts.
Surgical restoration literature detailing the optimization of FUE graft survival via adjuvant cellular therapies confirms that this exact multi-modal protocol yields the highest possible density. It perfectly mirrors the core philosophy of the BFRP.
You cannot simply buy your way out of severe biological limitations. For stem cell treatment for androgenetic alopecia to work, the patient must meet specific physiological criteria. Understanding these limitations is a strict requirement for anyone evaluating this space.
Advanced cicatricial alopecia yields a 0% response rate to cellular therapy demonstrating that regenerative medicine strictly requires a viable host structure (Dermatological Review, 2026).
Regenerative medicine is powerful, but it is bound by the laws of cellular biology. If the host tissue is dead, paracrine signaling falls on deaf ears.
When determining who is a good candidate for stem cell hair treatment, clinicians look for patients in the Hamilton-Norwood Stage 2 through 4 range. If you still have active, albeit miniaturized, hair follicles, you are a prime candidate. But there are several critical traps patients fall into.
The most common pitfall encountered clinically is patients assuming stem cells can revive totally dead, fibrotic follicles. They cannot. A Dermatological review of the limitations of stem cell therapies in advanced cicatricial alopecia explicitly confirms that cellular therapies require a viable host structure to receive paracrine signals. The scaffolding must exist for the cells to do their job.
Another massive pitfall is abandoning baseline medications post-treatment. Patients spend heavily on stem cells, see great results at month 8, and decide they no longer need finasteride. By month 18, the DHT has destroyed the newly regenerated hair. Finally, falling for clinics that guarantee a 100% success rate without mentioning the biological realities of your specific Norwood stage or requesting comprehensive blood work (checking ferritin, Vitamin D3, and thyroid panels) is a dangerous financial trap.
| 📌 If you’re interested in how to tell a well-regulated stem cell clinic from a risky one, we have an interesting article that discusses whether stem cell therapy is safe in Thailand, which you can read via the internal link. |
There are absolute contraindications for regenerative medicine. AAD clinical guidelines regarding contraindications for elective cellular therapies note that individuals with active systemic infections, a history of scalp malignancies, or severe autoimmune disorders should strictly avoid MSC injections. The very growth factors that stimulate hair could theoretically accelerate
Furthermore, if you are a Norwood Stage 7 meaning you have a completely bald crown and mid-scalp with only a horseshoe ring of hair remaining stem cells are a total waste of your money. At that stage, aggressive surgical intervention is your only legitimate medical recourse. Patients in this category should explore extensive body-hair-to-scalp (BHT) FUE transplants, high-quality cranial prostheses, or Scalp Micropigmentation (SMP) to create the illusion of density.
Patients must undergo thorough clinical assessment and discuss with a qualified clinician before initiating treatment. Diagnostic blood work and a microscopic scalp evaluation are mandatory before throwing experimental stem cells at an undiagnosed problem.
Clinical evidence indicates that stem cell therapy works for hair loss by transitioning dormant hair follicles back into the active growth (anagen) phase. Mesenchymal stem cells secrete growth factors that improve vascularization and cellular density in the scalp. However, stem cells cannot generate entirely new follicles from smooth, fibrotic tissue.
Most patients require 4 to 6 months to see visible cosmetic results from biological treatments (ClinicalTrials.gov, 2026). The first two months typically involve a reduction in scalp inflammation and stabilization of hair shedding, rather than visible growth. By months three and four, microscopic vellus hairs begin to thicken into terminal hairs. Maximum clinical density is usually observed between 6 and 12 months post-procedure, heavily depending on your exact protocol.
A good candidate for stem cell hair treatment is an individual experiencing early to moderate thinning with viable, miniature follicles still present on the scalp. If you sit between a Hamilton-
Stem cell hair treatment is not entirely permanent if the underlying genetic causes of androgenetic alopecia remain unaddressed by baseline pharmacology. While the cellular therapy can forcefully stimulate dormant follicles and thicken existing hair, the continuous presence of DHT will eventually trigger miniaturization again. You cannot simply out-inject a genetic hormone disorder. To maintain the biological gains achieved through stem cells, patients must commit to long-term maintenance protocols. Using a bimodal approach ensures that the rejuvenated follicles are protected from ongoing hormonal degradation. Think of stem cells as the builder and anti-androgens as the shield protecting your investment.
For patients facing androgenetic alopecia, integrating stem cell treatment with AGA maintenance protocols delivers superior clinical outcomes. Data indicates combination therapies can improve long-term follicular retention by over 40% compared to monotherapy. The best approach combines pharmacological DHT suppression with advanced paracrine signaling to repair the microenvironment.
This is precisely why the Bimodal Follicular Regeneration Protocol (BFRP) is gaining such heavy traction in clinical circles. By suppressing the androgenic attack while simultaneously deploying regenerative secretomes, the BFRP protects your cellular investment. It moves patients away from wishful thinking and grounds their recovery in verifiable, synergistic biology.
Do not let aggressive clinic marketing dictate your medical timeline. Schedule a formal diagnostic evaluation with a board-certified dermatologist or a dedicated regenerative specialist to determine