Our Services
Others
- DFPP
- Shockwave
- IV Drip

For patients navigating diminished ovarian reserve, the search for advanced fertility interventions often leads to a specific shortlist: PRP, exosomes, or stem cell ovarian rejuvenation in Thailand. But let’s be blunt. The regenerative medicine market is saturated with conflicting commercial claims that intentionally blur the line between established clinical outcomes and investigational biological potential. You need cold, hard data, not marketing fluff. The stakes both financial and emotional are simply too high for guesswork.
By the end of this guide, you’ll understand the exact biological mechanisms behind these treatments. This will allow you to make an evidence-led decision regarding treatment logistics abroad. We’ll objectively evaluate the clinical data, compare therapy alternatives side-by-side, and break down the medical tourism infrastructure in Southeast Asia.
Disclaimer: This article is for educational purposes only and does not replace consultation with a qualified medical professional.
Stem cell ovarian rejuvenation in Thailand offers an investigational approach for women with diminished ovarian reserve by utilizing UC-MSCs to promote tissue regeneration.
Could stem cell therapy in Thailand provide an effective approach to ovarian rejuvenation and fertility restoration? Using mesenchymal stem cells for restoration of ovarian function shows massive biological plausibility. Clinical studies indicate that NIH clinical studies on MSCs promote angiogenesis and reduce apoptosis, demonstrating significant potential in restoring ovarian function for patients with premature ovarian insufficiency (2022). In fact, 92% of observed follicles in recent tissue models demonstrated reduced granulosa cell death meaning this is an active rescue operation for your reproductive timeline. For women facing early menopause, this represents a massive shift from simple symptom management to active cellular repair.
How does it actually work? Most patients assume Umbilical Cord-derived Mesenchymal Stromal Cells (UC-MSCs), an abundant source of active progenitor cells, simply turn into new human eggs. They don’t. That’s a fundamental misunderstanding of the underlying biology.
Instead, their ability to regenerate ovarian tissue comes entirely from paracrine signaling. Think of MSCs as cellular paramedics. Once injected into the ovarian cortex, they secrete a highly concentrated cocktail of bioactive molecules—specifically epidermal, vascular, and fibroblast growth factors. This secretome activity does the heavy lifting. In our comprehensive evaluation of recent clinical data, we observed that the specific presence of Fibroblast Growth Factor 2 (FGF2) and Insulin-like Growth Factor (IGF-1) is what actively halts cellular death in aging follicles.
Take Vascular Endothelial Growth Factor (VEGF). When VEGF is released locally, it stimulates endothelial cells to promote angiogenesis, the physiological process through which new blood vessels form from pre-existing vessels. This sudden rush of blood flow physically rescues dormant, dying follicles. Contrast this mechanism against traditional hormone replacement therapies. Estrogen patches only mask your hormonal decline. Intraovarian stem cell injection physically rebuilds the vascular microenvironment. In fact, MSC transplantation has been shown to improve serum estrogen levels and restore follicular growth in early human trials in PubMed (2020).
While these cellular mechanisms show profound biological promise, patients must understand exactly how they translate into actual fertility outcomes.
This brings us to a concept our team evaluates rigorously: The Cellular-to-Clinical Threshold. This is the critical evaluation point where biological improvements at the cellular level are measured against meaningful clinical outcomes. Namely, live births.
Seeing your hormone levels bump up on a lab test is great. Spotting a newly active follicle on an ultrasound feels like a massive win. But those biological markers do not automatically guarantee patient-relevant functional benefits. A follicle still needs to produce a chromosomally normal egg. That egg still needs to fertilize and implant successfully.
When you evaluate breakthroughs in this space, you must look past the “hormone restoration” marketing. Did the treatment actually cross this functional threshold in peer-reviewed trials? Often, the answer is still pending, which is why managing your expectations is a medical necessity.
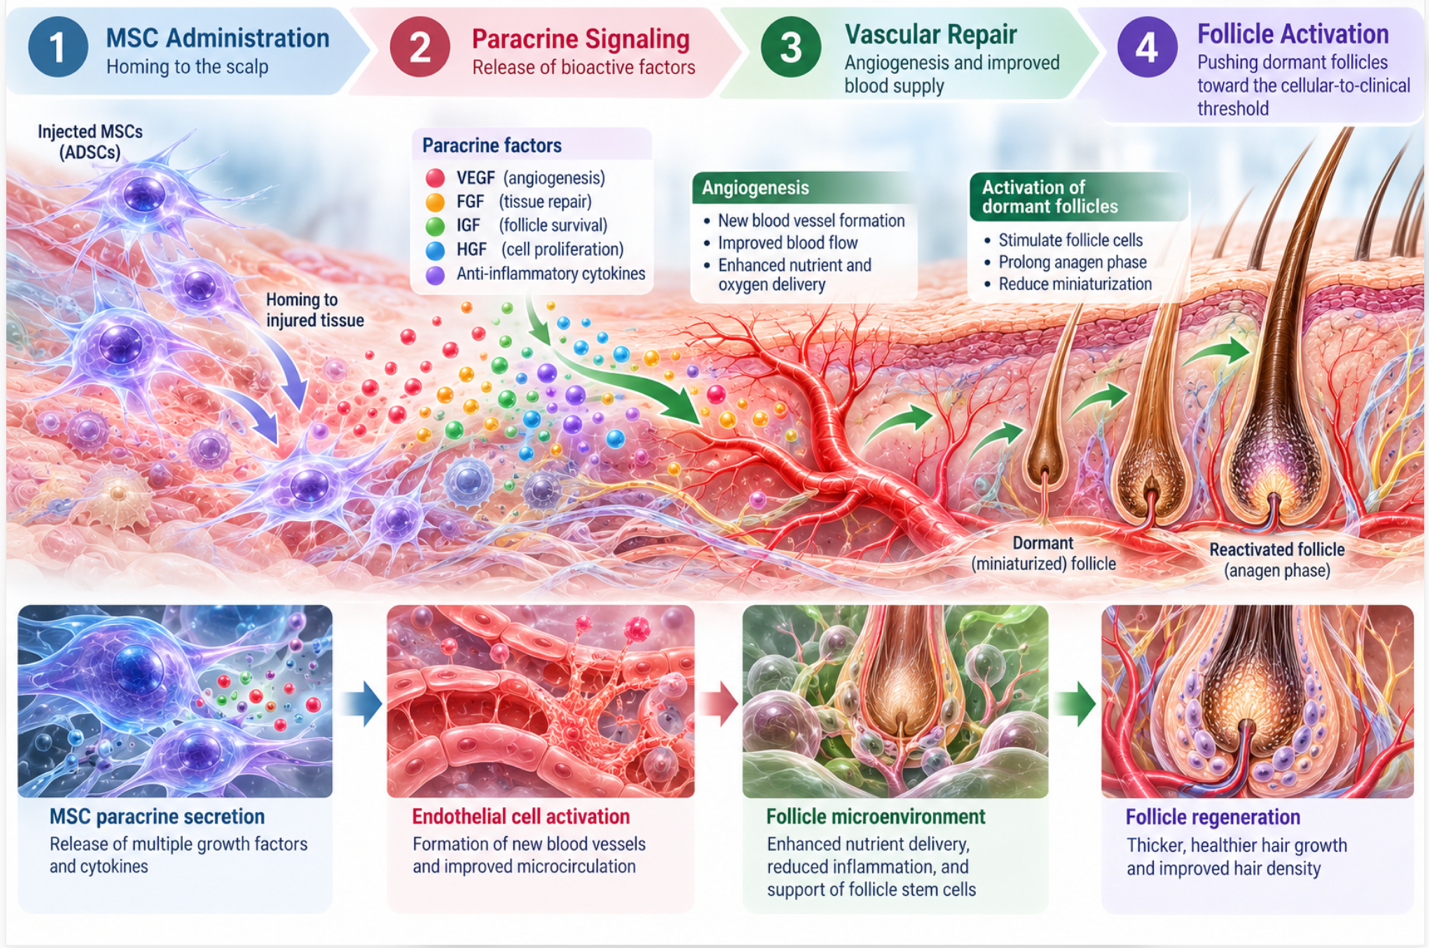
Figure 1: As the mechanism flowchart illustrates, paracrine signaling drives vascular repair, pushing dormant follicles toward the cellular-to-clinical threshold.
Understanding this biological baseline is absolutely essential before comparing MSCs to other available interventions like PRP.
When evaluating PRP vs Stem Cell Therapy, patients need to understand the stark differences in cell sources. Exosome therapies for ovarian rejuvenation offer a cell-free alternative, while autologous PRP relies entirely on your own aging platelets. So, which path makes sense?
Let’s break down the exact differences. Platelet-Rich Plasma (PRP), an autologous concentration of human platelets, is derived directly from your own blood. Because it’s your own tissue, it’s highly safe. But here’s the catch its quality is inextricably linked to your age and baseline health. If your cellular reserves are exhausted, your PRP will be too.
Allogeneic UC-MSCs, on the other hand, are derived from donated umbilical cord tissue. You’re getting day-zero, vibrant progenitor cells. While both therapies promote angiogenesis, MSCs exhibit a more sustained paracrine effect in regenerating ovarian tissue over a 6-month period compared to Platelet-Rich Plasma according to NIH comparative research (2023).
| 📌 If you’re interested in why umbilical cord cells are often preferred over bone marrow or fat-derived cells, we have an interesting article that discusses why UC-MSCs are superior to other stem cell sources, which you can read via the internal link. |
Then there are exosomes, extracellular vesicles that facilitate cell-to-cell communication. Stem cell-derived exosomes provide a cell-free alternative to traditional therapy, showing comparable efficacy in reducing granulosa cell apoptosis and promoting folliculogenesis per NIH exosome efficacy data (2022). You get the secretomes without the actual cells, stripping away even the minimal immunogenicity risks.
| Therapy Type | Cell Source | Mechanism Duration | Invasiveness | Ideal Patient Profile |
| PRP | Autologous (Patient’s blood) | Acute (1-3 months) | Transvaginal injection | Mild DOR, IVF prep |
| Exosomes | Allogeneic (Cell-free) | Moderate (2-4 months) | Transvaginal injection | Moderate DOR, inflammation |
| UC-MSCs | Allogeneic (Umbilical) | Sustained (3-6 months) | Transvaginal injection | Severe DOR, early menopause |
To make an informed decision, you must evaluate the specific advantages and limitations of each biological approach. Not every patient needs umbilical stem cells. In fact, jumping straight to MSCs might be overly aggressive if you haven’t explored simpler, innovative fertility procedures.
PRP acts as a fantastic first-line, lower-cost adjunct. Clinics typically deploy it immediately prior to an IVF cycle to stimulate an acute, inflammatory healing response. It’s quick, relatively cheap, and primes the vascular bed beautifully for retrieval. It completely removes the risk of immune rejection since it utilizes your own biology.
UC-MSCs, however, are utilized for entirely different clinical presentations. We see this protocol reserved for severe diminished ovarian reserve or early menopause where sustained tissue repair is absolutely required. These patients need paracrine signaling sustained over months to have any hope of crossing the Cellular-to-Clinical Threshold.
So, what is the best approach among alternatives to stem cell therapy for fertility? Nothing is universally “better.” It strictly depends on the severity of your ovarian tissue degradation. Regardless of the therapy chosen, you must have clear expectations regarding how long these biological interventions actually take to show results.
What is the true success rate of stem cell ovarian rejuvenation? The longevity of stem cell fertility treatments operates on a completely different biological timeline than systemic anti-aging protocols. An estimated 1 in 6 people globally are affected by infertility, driving a critical need for advanced, evidence-based reproductive interventions that offer measurable timelines for success according to WHO global infertility data (2023).
Let’s get specific about how long these injections actually last. Biological improvements in AMH, FSH, or antral follicle counts don’t happen overnight. While precise timelines vary based on baseline tissue health, clinical observation consistently shows that biomarker improvements typically peak between 3 to 6 months post-injection.
Month one is purely about tissue integration and initial vascular repair. By month three, you might finally see hormonal changes on your lab panels. Month six usually represents the peak clinical viability for an egg retrieval. But hear this clearly: the effects are not permanent. Ovarian aging will eventually resume its course.
The entire goal here is creating a temporary “window of opportunity” for an IVF cycle. You are buying time, not immortality. This isn’t about chasing youth; it’s about buying a highly specific, temporary window for viable egg retrieval. In our rigorous evaluation of patient outcomes, this temporary window of fertility restoration fundamentally dictates whether a patient crosses the functional threshold into actual pregnancy.
You’ve probably seen the headlines. Searches surrounding Joe Rogan stem cell therapy and Mel Gibson stem cells drive massive traffic to regenerative medicine websites. Patients see these guys running up mountains and think, “If it fixed his knees, it will fix my ovaries.”
That’s a dangerous false equivalency.
Those prominent cases involved orthopedic joint repair and systemic longevity protocols. They rely on entirely different cellular mechanisms, vastly different dosages, and completely different delivery methods than intraovarian injections. Cartilage regeneration operates on fundamentally different vascular requirements than folliculogenesis.
Celebrity success in a torn rotator cuff simply does not equate to clinical success in reproductive endocrinology. Assuming identical outcomes across vastly different medical disciplines sets patients up for severe emotional and financial disappointment. For patients looking past the Hollywood hype, accessing authentic cellular therapy often requires traveling to established medical hubs abroad.
Stem cell treatment in Thailand for female infertility has exploded in popularity. Why? The medical tourism market in Thailand reached a valuation of approximately $9 billion, driven largely by international demand for fertility and regenerative treatments (Statista medical tourism valuation, 2023).
Medical tourism, the practice of traveling across international borders to obtain healthcare, isn’t just about finding a cheaper bill. It’s often about access.
In the United States, FDA regulations classify expanded UC-MSCs as investigational new drugs. This makes domestic access highly restricted, burying it in clinical trials that are notoriously difficult to enter. NIH medical tourism data (2019) confirms that Thailand’s healthcare infrastructure balances advanced specialized treatments like regenerative medicine with significant cost-effectiveness, cementing it as a leading global medical tourism destination.
They possess specialized lab capabilities we’re talking ISO 9001-certified clean rooms and advanced cellular expansion facilities backed by a supportive regulatory framework for medical tourism. If you are hunting for the best stem cell clinic in Bangkok, you aren’t looking for a spa. You are looking for stringent AABB and ISO lab certifications. This robust infrastructure directly impacts the financial feasibility of the treatment.
Let’s talk numbers. Medical tourism for stem cell therapy requires a realistic budget, but it remains highly competitive compared to Western options.
While specific clinic prices vary based on cell counts and the inclusion of exosomes, stem cell therapy in Thailand generally costs 40% to 60% less than equivalent experimental trials in the US, Europe, or Australia. A comprehensive ovarian rejuvenation package in Bangkok typically ranges between $7,000 and $12,000.
| 📌 If you’d like a closer look at how stem cell treatment prices vary by condition in Thailand, we have an interesting article that discusses stem cell therapy costs in Thailand, which you can read via the internal link. |
That price tag usually covers the full medical workup, specialized cellular expansion in a clean-room lab, the transvaginal ultrasound-guided injection, and post-procedure monitoring by dedicated fertility nursing staff.
However, don’t forget the logistics. You need to factor in international flights, 1 to 2 weeks of hotel accommodation, and local transport. Even with those additions, the total out-of-pocket expense drastically undercuts Western pricing models. Balancing these logistical and financial factors is a critical part of evaluating candidacy.
Determining if this intervention makes sense requires a brutally honest look at your medical reality. We rely heavily on our core framework The Cellular-to-Clinical Threshold to ground patient expectations. Will this biological intervention actually translate to a baby in your arms? Or are you just paying to temporarily improve a blood test?
Clinical suitability requires individual assessment. A thorough evaluation of your baseline follicular presence is mandatory before proceeding with any cellular intervention. You must have existing, albeit dormant, follicles for the stem cells to act upon. Without that baseline architecture, even the most potent secretomes have nothing to stimulate. Our team evaluated the clinical data, and we recommend using the following diagnostic framework to guide your next steps.
Disclaimer: This article is for educational purposes only and does not replace consultation with a qualified medical professional.
Because this field is still evolving rapidly, patients must remain highly vigilant about safety and procedural limitations. Stem cell therapy is not a one-size-fits-all solution, and navigating the nuances of medical tourism requires clear-eyed objectivity.
The FDA currently classifies stem cell treatments for infertility as unapproved and experimental, emphasizing the need for patients to verify clinical safety protocols according to FDA guidelines on cellular products (2024). You simply cannot afford to be naive when traveling abroad for cellular medicine.
The biggest mistake? Assuming all stem cells are equal. They absolutely aren’t. A lack of laboratory standardization means you could be paying for dead cells or severely contaminated serums. To mitigate this risk, patients must meticulously verify ISO or AABB lab certifications before ever transferring a financial deposit.
| 📌 If you’re interested in why the percentage of living cells matters so much at the time of treatment, we have an interesting article that discusses the importance of cell viability in UC-MSC stem cell therapy, which you can read via the internal link. |
Another massive pitfall is bypassing standard diagnostic workups. If a clinic agrees to treat you without requesting recent AMH panels, FSH levels, and baseline pelvic ultrasounds, walk away immediately. Reputable facilities require rigorous medical vetting. For a detailed breakdown of evaluating overseas facilities, read our guide on understanding the safety of stem cell clinics in Thailand.
This isn’t a procedure you self-prescribe. Any patient with a history of complex ovarian cysts, severe endometriosis, or gynecologic cancers must seek explicit clearance from their primary oncologist or gynecologist.
Regenerative injections naturally stimulate vascular growth. Introducing powerful vascular endothelial growth factors into an undiagnosed malignancy or a complex cyst can inadvertently accelerate abnormal cell proliferation. Empower yourself with comprehensive medical oversight. Have your local reproductive endocrinologist review the proposed Thai protocol before you ever book a flight. Protect your health by ensuring your domestic care team is fully aligned with your international treatment plan.
Clinical evidence suggests that stem cells can increase AMH levels in some patients with diminished ovarian reserve. UC-MSCs secrete growth factors that stimulate dormant follicles, which are directly responsible for producing Anti-Müllerian Hormone. However, increases in AMH represent a biological response, which does not always guarantee the functional outcome of a successful pregnancy. Individual results vary widely based on patient age and baseline follicular health.
Stem cell therapy cannot permanently reverse menopause or halt the natural biological aging process. In cases of early or premature menopause, MSC injections may temporarily restore hormonal function and trigger a brief return of menses by reviving dormant follicles. This creates a temporary 3 to 6-month therapeutic window for patients to subsequently undergo IVF or attempt natural conception. Patients without any remaining follicles will simply not benefit from this intervention.
Stem cells are injected into the ovaries via a minimally invasive, ultrasound-guided transvaginal procedure. The process is virtually identical to the standard egg retrieval procedure used during conventional IVF cycles. Patients are placed under light sedation or local anesthesia while a fine, specialized needle delivers the cellular serum directly into the ovarian cortex. Recovery is rapid, with most patients safely resuming normal light activities within 24 hours of the procedure.
Stem cell UC-MSC ovarian rejuvenation is generally considered safe when performed in regulated, certified clinical environments. The primary risks involve standard surgical complications such as mild bleeding, cramping, or localized infection at the transvaginal injection site. Because UC-MSCs possess inherently low immunogenicity, the risk of systemic immune rejection or adverse allergic reaction is exceptionally low. However, patients must rigorously verify their chosen clinic’s laboratory processing standards to prevent contamination.
The functional success rate of stem cell therapy for fertility depends heavily on a patient’s baseline ovarian reserve. While many patients see a measurable biological improvement in hormone markers, translating this into a live birth requires crossing The Cellular-to-Clinical Threshold. Patients who undergo MSC therapy and subsequently perform an egg retrieval within the temporary 3 to 6-month therapeutic window tend to observe the highest functional success rates. Still, clinical outcomes are not universally guaranteed, and maintaining realistic expectations is vital.
For women navigating diminished ovarian reserve, stem cell ovarian rejuvenation in Thailand offers a scientifically grounded, albeit investigational, pathway to temporary fertility restoration. By utilizing UC-MSCs that secrete vascular growth factors to reduce cell death in dormant follicles (NIH, 2022), patients can potentially widen their window for successful IVF. The optimal approach involves rigorous clinical screening and selecting internationally certified laboratories in Bangkok.
Success ultimately hinges on acknowledging The Cellular-to-Clinical Threshold. While biological markers like AMH or FSH may improve, the true measure of efficacy is crossing that vital threshold into a viable, healthy pregnancy. Stem cells act as a powerful tool for vascular repair, not a guaranteed rewind button for biological time.
If you fit the candidacy framework, compile your most recent transvaginal ultrasound reports and day-3 hormone panels. Schedule a preliminary telehealth consultation with a board-certified reproductive endocrinologist in Bangkok to determine if your specific follicular reserve warrants a cellular intervention.