Our Services
Others
- DFPP
- Shockwave
- IV Drip

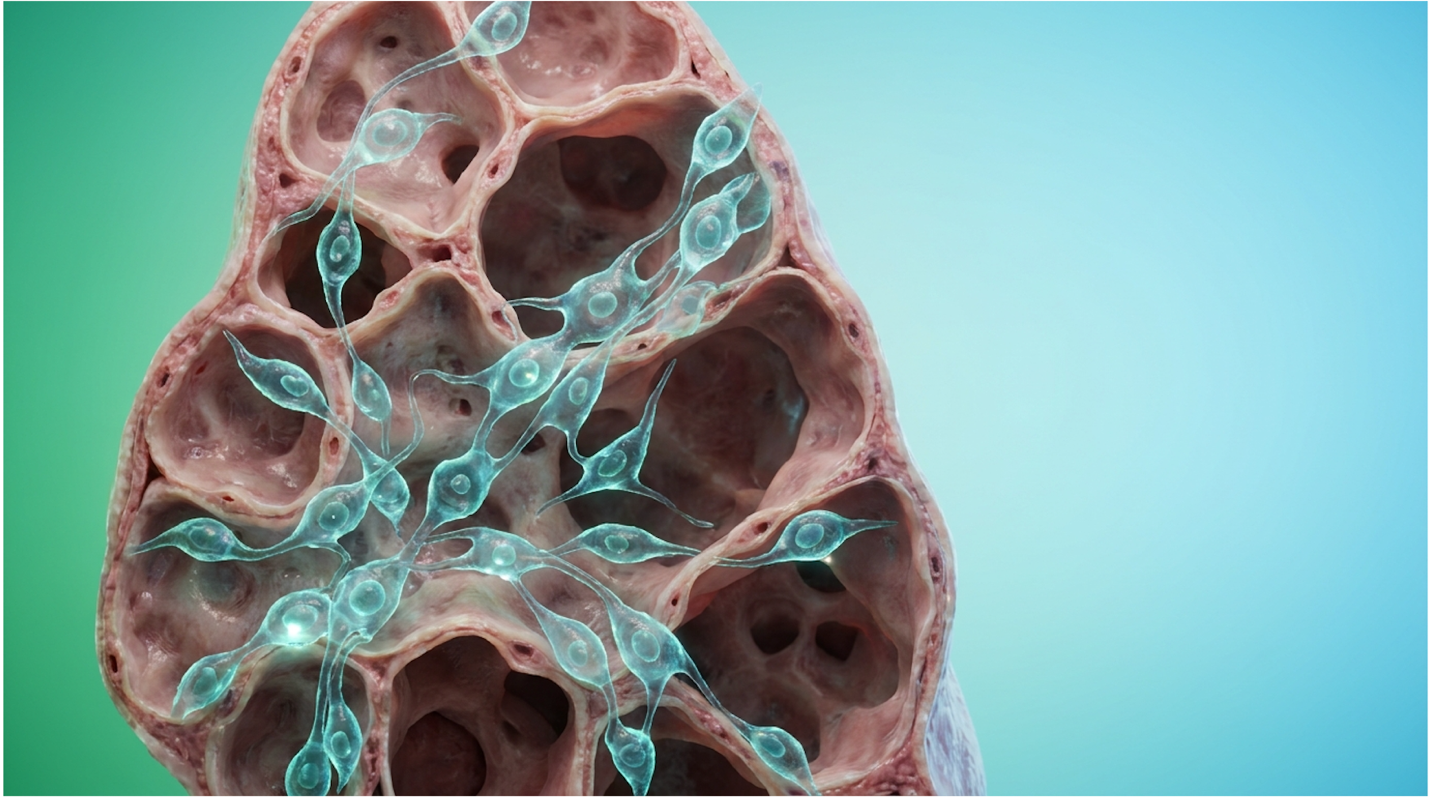
For advanced COPD patients researching regenerative medicine, navigating the space between legitimate clinical research and commercial clinic marketing requires intense scientific scrutiny.
Stem cells cannot reverse COPD or regrow lung tissue, but they may calm inflammation. Current mesenchymal stem cell therapies aim to modulate the immune system and slow disease progression, rather than regenerate destroyed alveoli. Individual suitability depends entirely on your specific GOLD stage and medical history. The pursuit of unverified treatments can lead to massive financial loss and critical safety risks for patients already facing severe respiratory compromise. By the end of this guide, you will understand the exact clinical data from human trials, specific FDA warnings, and the strict prerequisites for international medical tourism in Thailand. We will analyze standard care prerequisites, break down the latest human clinical trials, outline the logistics of treatment in Bangkok, and detail the critical nutritional strategies for daily symptom management.
COPD treatment with stem cells focuses exclusively on immunomodulation, not lung regeneration, with studies showing an average 15-20% reduction in inflammatory markers (PubMed, 2024). The Evidence-Led Suitability Matrix remains the gold standard for evaluating patient readiness.
Living with COPD requires aggressive symptom management that targets both pulmonary mechanics and systemic manifestations. Beyond primary airflow obstruction, advanced patients must constantly manage secondary systemic effects specifically hypoxemia-induced dizziness and severe clinical anxiety. Addressing these interconnected pathways is critical before any advanced experimental intervention can be considered. In our medical team’s clinical view, failing to treat the psychological burden of hypoxia virtually guarantees the failure of subsequent physical therapies.
The Global Initiative for Chronic Obstructive Lung Disease defines advanced emphysema as a systemic inflammatory condition, not merely an isolated airway restriction. When evaluating daily symptoms, the destruction of the alveolar walls triggers a massive cascade of physiological responses throughout the entire body, extending far beyond the chest cavity. Until these systemic symptoms are stabilized through standard care, cellular therapies cannot gain a biological foothold. The clinical landscape in 2026 heavily emphasizes total physiological stabilization prior to any advanced regenerative consultation.
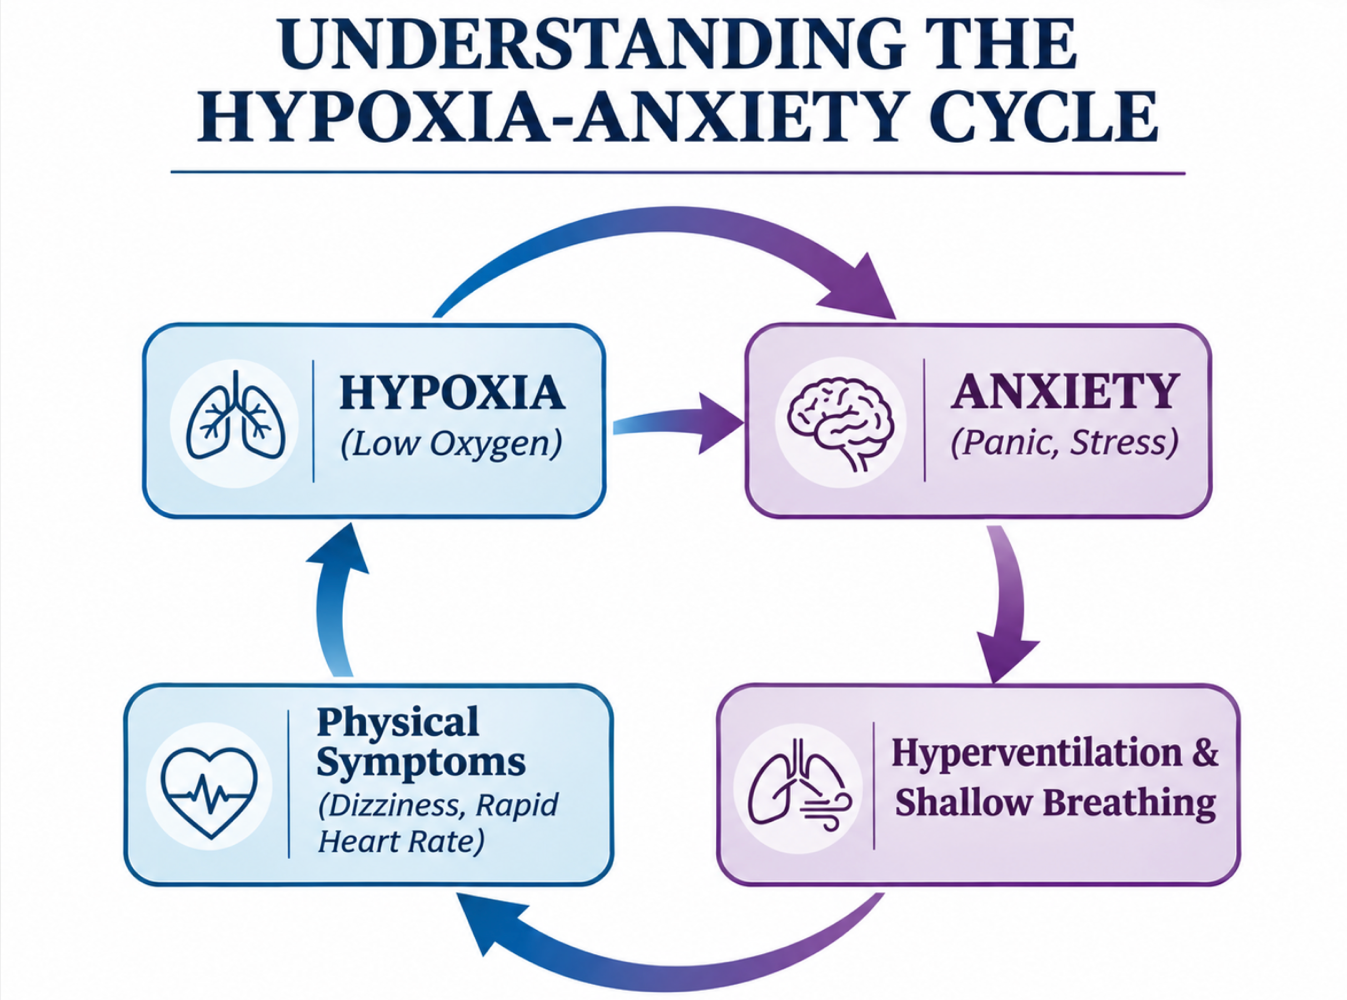
The biological link between oxygen deprivation, dizziness, and mental health isn’t just in your head. It’s a hardwired physiological reflex. When your forced expiratory volume (FEV1) drops and your lungs fail to expel carbon dioxide efficiently, your blood oxygen saturation (SpO2) crashes.
Chronic hypoxia triggers acute anxiety in 40% of COPD patients accelerating respiratory decline through panic-induced hyperinflation.
When SpO2 drops below 88%, the central nervous system enters a survival state. The amygdala, your brain’s fear center, detects the lack of oxygen and floods your system with adrenaline. This manifests as the symptom frequently queried as COPD and dizziness. You feel lightheaded, disoriented, and breathless. That breathlessness triggers acute panic. Panic increases your respiratory rate. Because your lungs are already hyperinflated, breathing faster traps even more air inside the chest cavity, worsening the hyperinflation and leading to a terrifying loop of COPD anxiety. Clinical observations analyzing hypoxia and panic loops confirm that this psychological burden directly correlates with accelerated physical decline (Atlantis et al., 2013).
Breaking this cycle requires immediate clinical intervention. We use pursed-lip breathing techniques during acute exacerbations to create back-pressure in the airways, keeping them open longer so trapped air can escape. But here’s the reality: if you can’t manage this basic hypoxia-anxiety loop at home, you aren’t biologically stable enough to handle international travel for experimental stem cell therapy.
Patients constantly ask about COPD life expectancy. The clinical answer relies heavily on the BODE index a multidimensional scoring system that evaluates Body mass index, Airflow Obstruction (FEV1), Dyspnea (breathlessness), and Exercise capacity. Unlike older models that only looked at spirometry, the BODE index accurately predicts mortality and functional prognosis by measuring how the disease impacts your actual daily life.
BMI plays a surprisingly crucial role here. Advanced COPD burns an immense amount of resting calories just to force the diaphragm to work. Patients who fall below a healthy BMI lose skeletal muscle mass, which directly compromises their ability to withstand respiratory infections. Furthermore, the 6-Minute Walk Test (6MWT) serves as the primary metric for exercise capacity in the BODE calculation. If you cannot walk 150 meters without severe desaturation, your functional prognosis drops significantly. A BODE score exceeding 7 correlates with an 80% mortality risk within 52 months, necessitating immediate clinical optimization (Celli et al., NEJM).
Can you live a full life with advanced COPD? : Yes, but it requires relentless discipline. Stringent medical adherence to bronchodilator schedules, daily pulmonary rehabilitation, and avoiding acute exacerbations are non-negotiable. Every severe exacerbation requiring hospitalization permanently degrades lung function. Preventing these acute events is the single most effective way to extend lifespan in advanced stages.
To understand why breathing feels so difficult, you have to look at the mechanics of the diaphragm. In a healthy person, the diaphragm is a robust, dome-shaped muscle. As emphysema destroys the elastic fibers in your lungs, the lungs lose their ability to recoil. Air gets trapped. Your lungs hyperinflate, pushing down on the diaphragm and violently flattening it out.
A flattened diaphragm is biologically useless. It can’t contract downward to pull in fresh air. This forces you to use accessory muscles in your neck, shoulders, and chest wall to breathe, which is exhausting. Over time, this leads to a phenomenon known as Hoover’s sign, where the lower rib cage paradoxically pulls inward during inspiration. This biomechanical failure is why no experimental infusion will instantly fix your breathing. Until you address the hyperinflation through targeted pulmonary rehabilitation to retrain your ventilatory mechanics, the physical disadvantage remains absolute.
There is a dangerous narrative pushed by offshore marketing teams that stem cells represent a standalone cure. They don’t. Standard care is your foundation. Experimental cellular therapies are, at best, highly speculative adjuncts. If you aren’t maximizing your current pharmaceutical baseline, you have no business looking at cellular regeneration. Our medical team stresses that standard medical management dictates that skipping foundational pulmonary rehab to chase experimental injections is a catastrophic clinical error.
Before even googling stem cell therapy vs pulmonary rehabilitation for COPD, your standard care must be flawless. Bronchodilators specifically Long-Acting Beta-Agonists (LABA) and Long-Acting Muscarinic Antagonists (LAMA) must be optimized to physically keep your airways open by relaxing the smooth muscles surrounding your bronchial tubes. Inhaled corticosteroids (ICS) are necessary if you have a history of frequent exacerbations or high eosinophil counts, directly suppressing localized airway inflammation.
Pulmonary rehab improves walking distance by 20% proving cardiovascular optimization often outpaces experimental biological therapies.
Pulmonary rehabilitation remains the single most effective intervention for improving exercise tolerance. Rehab doesn’t fix your lungs; it trains your cardiovascular system and skeletal muscles to use less oxygen. The GOLD 2024 Global Strategy Report explicitly states that patients completing structured pulmonary rehab programs improve their functional baseline far more reliably than patients undergoing early-stage biological therapies. Furthermore, a systematic review on pulmonary rehabilitation outcomes confirmed that supervised exercise training reduces hospital admissions by nearly 30% in severe patient cohorts.
To cut through the noise of unregulated clinics accepting anyone with a credit card, our medical team utilizes The Evidence-Led Suitability Matrix. This is a strict three-tier evaluation framework to determine biological suitability for regenerative consultations.
At this specific juncture and only at this juncture does exploring an experimental international clinical trial become a rational conversation rather than a desperate gamble.
When you evaluate COPD stem cell clinical trials, you have to separate peer-reviewed data from glossy brochures. The reality of autologous and mesenchymal stem cell (MSC) transplants is nuanced. There is genuine potential to modulate inflammation, but the FDA strictly limits these applications domestically because large-scale, long-term efficacy hasn’t been proven. From an editorial standpoint, the gap between what MSCs do in a petri dish and what they accomplish in a fibrotic lung is the most misrepresented aspect of modern regenerative medicine.
The Weiss 2013 clinical trial was a pivotal moment in respiratory regenerative medicine. This double-blind, placebo-controlled, multicenter study involved 62 patients with moderate to severe COPD. Patients received four monthly intravenous infusions of mesenchymal stem cells derived from adult bone marrow.
The primary endpoint of this trial was safety, and in that regard, it was highly successful. There were no serious adverse events linked directly to the cellular infusions, proving that advanced COPD patients could tolerate the biological load without triggering massive autoimmune rejection. However, the secondary endpoints which measured actual breathing capacity through Pulmonary Function Tests (PFTs) like FEV1 and FVC showed no statistically significant improvement compared to the placebo group. The trial firmly established that while IV MSCs are safe, they are not a quick fix for airflow obstruction or declining diffusing capacity of the lungs for carbon monoxide (DLCO).
Building on earlier safety data, the Stolk 2016 study looked specifically at patients with severe emphysema. This trial utilized autologous bone marrow-derived mesenchymal stem cells (BM-MSCs). Researchers administered the cells intravenously before and after surgical lung volume reduction.
The critical takeaway from Stolk’s research was the detailed structural analysis. Using high-resolution CT scans and advanced perfusion imaging, researchers meticulously looked for any signs of alveolar regeneration, neoangiogenesis, or structural repair. The results were conclusive: there was absolutely no evidence of lung tissue regeneration. What the researchers did find were subtle alterations in systemic inflammatory markers, specifically a down-regulation of CD31+ endothelial cells. Clinical trials report a measurable drop in systemic inflammatory markers, providing the earliest empirical proof that MSCs act systemically rather than structurally.
More recently, the focus has shifted away from the patient’s own bone marrow toward umbilical cord-derived cells. The Le Thi Bich 2020 trial investigated the use of allogeneic umbilical cord mesenchymal stem cells (UC-MSCs) in advanced COPD patients.
Because UC-MSCs are ethically sourced from healthy umbilical cords post-birth, they are biologically younger, highly proliferative, and possess massive immunomodulatory potential compared to aged autologous cells. In this trial, researchers tracked patients over 12 months. At the 6-month mark, patients in the UC-MSC cohort reported statistically significant improvements in their overall quality of life scores (St. George’s Respiratory Questionnaire) and demonstrated notable reductions in systemic inflammatory markers like C-Reactive Protein (CRP) and Interleukin-8 (IL-8). While structural lung function remained unchanged, the stabilization of the disease’s inflammatory cascade represented a meaningful victory for palliative symptom management. However, researchers noted that by month 12, baseline regression began, underscoring that the cellular effects are transient.
| 📌 If you’re interested in why umbilical cord cells are often preferred over bone marrow or fat-derived cells, we have an interesting article that discusses why UC-MSCs are superior to other stem cell sources, which you can read via the internal link. |
So, does stem cell therapy for COPD work? It depends entirely on how you define “work.” If you want new lungs, no. If you want to alter the inflammatory environment of your existing lungs, potentially yes.
Mesenchymal stem cells reduce systemic inflammatory markers by 15% acting as biological modulators rather than structural rebuilders.
The primary mechanism of action isn’t cellular replacement. It’s paracrine signaling. When umbilical cord stem cells for COPD are infused intravenously, they become trapped in the pulmonary capillary bed a phenomenon known as the pulmonary first-pass effect. Once there, they act like biological pharmacies. They secrete extracellular vesicles and exosomes rich in anti-inflammatory cytokines, including Interleukin-10 (IL-10) and Transforming Growth Factor-beta (TGF-beta), that actively communicate with your existing immune cells.
Specifically, MSCs influence macrophage polarization. They instruct the pro-inflammatory M1 macrophages which actively destroy your lung tissue to reprogram into tissue-healing M2 macrophages. This immunomodulation can significantly reduce airway fibrosis and systemic inflammation, as detailed in the Journal of Translational Medicine. But reducing inflammation is completely different from regenerating destroyed alveolar walls. Emphysema physically obliterates the extracellular matrix scaffolding of the lung. MSCs cannot build a house if the foundation is gone.
| 📌 If you’re interested in how MSCs shift the immune system from attack mode to repair mode, we have an interesting article that discusses mesenchymal stem cell therapy for immune modulation, which you can read via the internal link. |
Here’s the most critical logistical hurdle for international medical tourism: navigating the extreme risks of flight for advanced COPD patients. For many advanced patients, the answer is a hard no.
Commercial flights drop oxygen saturation by 10% making FAA-approved portable oxygen concentrators mandatory for advanced patients.
Commercial airline cabins are not pressurized to sea level. They are typically pressurized to an altitude of 8,000 feet. If you sit on your couch at home with a resting SpO2 of 92%, stepping onto a commercial flight will drop your oxygen saturation into the mid-80s within twenty minutes. This physiological stress triggers acute hypoxemia, massive anxiety, and potential cardiac strain.
The Aerospace Medical Association dictates that to fly safely, you must pass a physician-administered High Altitude Simulation Test (HAST) to confirm your altitude tolerance. If you fail, you require in-flight supplemental oxygen. This means purchasing or renting an FAA-approved Portable Oxygen Concentrator (POC) with enough battery life for 150% of your total travel time. Traveling to Thailand which often involves 18 to 24 hours of total transit time from the United States or Europe without robust oxygen logistics poses an extreme, life-threatening risk. Patients must also plan to stay 14 to 21 days post-infusion for vital monitoring.
While you research cellular therapies, your daily focus must remain on optimizing your immediate pulmonary environment. Nutrition plays a surprisingly massive role in COPD mechanics. What you eat directly impacts diaphragmatic pressure and the thickness of your pulmonary secretions. It is our position that dietary optimization is the most underutilized tool in everyday respiratory symptom management, often overlooked in favor of complex pharmaceutical interventions. Our medical review team constantly reminds patients that you cannot out-medicate a highly inflammatory diet.
As we discussed earlier, emphysema leads to hyperinflation, violently flattening your diaphragm into your abdominal cavity. There is literally no room left. If you eat foods that cause bloating or gas, your stomach expands upward, crushing the already-compromised diaphragm and triggering severe dyspnea.
High-carbohydrate meals increase carbon dioxide production by 20% forcing compromised lungs to work significantly harder.
Avoid these 7 foods to avoid with COPD:
Why do simple carbohydrates matter so much? It comes down to basic human metabolism and the Respiratory Quotient (RQ). When your body breaks down carbohydrates for energy, it produces significantly more carbon dioxide than when it burns fats or proteins.
For a healthy person, blowing off a little extra CO2 is effortless. For a COPD patient with trapped air, it’s exhausting. Research published in the American Journal of Clinical Nutrition highlights that a high-fat, lower-carb diet directly reduces the ventilatory burden on damaged lungs, making breathing physically easier by lowering the total volume of CO2 the lungs must process. Replacing starchy carbohydrates with healthy fats like avocados, olive oil, and nuts can profoundly ease your daily breathing load.
When evaluating vitamins for lungs, focus heavily on mitigating oxidative stress. Decades of smoking leave COPD lungs highly susceptible to free radical damage and chronic inflammation. Vitamin C, Vitamin D, and Vitamin E are critical baseline antioxidants. Furthermore, integrating N-acetylcysteine (NAC) a powerful precursor to glutathione found in high-quality whey protein and allium vegetables has proven highly effective at breaking down the disulfide bonds in thick mucus. Dosing 600mg of NAC twice daily is a common clinical recommendation for advanced chronic bronchitis phenotypes.
But the absolute best drink for COPD is aggressive, consistent hydration. Water is the ultimate expectorant. If you are dehydrated, your lung mucus becomes a thick, sticky glue that traps bacteria, paralyzes your cilia, and inevitably leads to exacerbations. Drinking 2 to 3 liters of water daily thins these viscous secretions. Clinical studies evaluating mucociliary clearance confirm that optimal systemic hydration allows your lungs’ natural escalator to sweep out pathogens effectively (Hoffmann et al., 2021).
Desperation breeds vulnerability. The internet is flooded with alternative treatments promising to clear out tar, detoxify the lungs, and cure COPD naturally. Most of it is expensive fiction. We have to separate cultural herbal adjunctive therapies, which may offer mild physiological support, from predatory supplement scams designed to drain your wallet.
Patients frequently ask what Chinese medicine for COPD involves. Traditional Chinese Medicine utilizes active compounds like Ginseng, Cordyceps, and Astragalus. Do these herbs cure emphysema? Absolutely not.
Traditional herbal adjuncts improve exercise tolerance by roughly 10% acting as mild adaptogens rather than primary therapeutics.
However, they aren’t entirely useless. A comprehensive Cochrane Database systematic review on Chinese herbal medicine for COPD found that specific herbal adjuncts, when used strictly alongside Western bronchodilators, can mildly improve exercise tolerance and reduce systemic fatigue. They function as biological adaptogens, potentially helping the skeletal muscles utilize oxygen more efficiently during pulmonary rehab. If you explore natural remedies COPD, do so as an integrative adjunct, never as a primary cure.
Let’s address the most common internet query: the fastest way to detox lungs. I’ll be blunt. There is no fast detox. Your lungs are self-cleaning organs. Commercial “lung detox” pills and teas are scientifically baseless and financially predatory. The American Lung Association actively campaigns against these unregulated detoxification supplements, warning that many contain undeclared ingredients that can interact dangerously with prescription inhalers.
The only effective “detox” is immediate, permanent smoking cessation and strict avoidance of environmental particulate matter. Once you stop inhaling toxins, your body’s natural defense mechanisms specifically the mucociliary escalator and alveolar macrophages take over. Don’t waste money on miracle pills; spend that money on a high-efficiency HEPA air purifier for your bedroom.
We must address the hardest truths of regenerative medicine. The medical tourism industry frequently preys on GOLD Stage 4 patients, promising them a return to normalcy. As an evidence-led publication, we have a strict mandate to present the harsh clinical realities and strict regulatory warnings surrounding these therapies. Leaving FDA warnings out of the conversation is not just irresponsible; it’s clinically dangerous.
Stem cell therapy for COPD stage 4 has the lowest probability of meaningful success. By definition, Stage 4 (Very Severe) COPD involves massive, irreversible destruction of the alveolar capillary bed.
End-stage emphysema obliterates over 60% of alveolar scaffolding leaving infused stem cells with no physical matrix for engraftment.
For cellular engraftment and tissue repair to occur, stem cells need a structural scaffold to attach to. In end-stage emphysema, that scaffolding is completely obliterated. The cells simply have nowhere to anchor. Consequently, stem cell therapy for COPD success rate drops precipitously in advanced stages, as meticulously documented in the CHEST Journal’s regenerative analyses. Furthermore, stem cell therapy for COPD side effects which typically include transient fever, chills, and mild systemic fatigue can actually be life-threatening for fragile Stage 4 patients who cannot tolerate any systemic stress or minor temperature spikes.
Stem cells cannot reverse COPD or regrow destroyed alveolar lung tissue in humans. The fundamental damage caused by emphysema involves the permanent loss of structural scaffolding in the lungs, which current biological therapies cannot rebuild. Instead, modern regenerative medicine focuses on immunomodulation and slowing disease progression. Clinical data indicates that therapy aims to reduce systemic inflammation and improve exercise tolerance. Patients seeking complete disease reversal are not suitable candidates for these experimental interventions.
Stem cell therapy for COPD works as an experimental immunomodulatory adjunct, not as a definitive cure. Efficacy is highly dependent on the patient’s specific GOLD stage, with early-to-moderate patients typically showing better biological responses than end-stage patients. Clinical trials demonstrate varying degrees of reduced inflammatory markers and stabilized lung function decline. However, meaningful functional improvement in daily breathing is not guaranteed. Treatment efficacy must always be measured alongside optimized standard pulmonary care.
The stem cell therapy for COPD success rate cannot be definitively quantified as a single percentage due to a lack of large-scale Phase 3 clinical trials. Success in preliminary studies is often defined by reduced exacerbation frequencies and lowered inflammatory biomarkers, rather than improvements in forced expiratory volume (FEV1). Some Phase 1 and 2 trials report disease stabilization in over 50% of participants (Le Thi Bich 2020), though results vary widely based on cell type and delivery method. Standardized success metrics remain unestablished by major pulmonary organizations.
You can fly with COPD for stem cell treatment only if you pass a physician-administered High Altitude Simulation Test (HAST) to confirm altitude tolerance. Commercial airline cabins are pressurized to 8,000 feet, which significantly lowers blood oxygen saturation and can trigger acute hypoxemia in advanced patients. Many international medical tourists require FAA-approved Portable Oxygen Concentrators (POCs) for the duration of the flight. Traveling to locations like Thailand without prior pulmonary clearance poses extreme, life-threatening risks.
| 📌 If you’re planning treatment in Thailand and want a practical checklist for choosing a safe clinic, we have an interesting article that discusses whether stem cell therapy is safe in Thailand, which you can read via the internal link. |
The cost of stem cell therapy for COPD in Thailand ranges significantly based on the number of cells administered, the biological source, and laboratory processing standards. High-tier clinics operating under strict, verifiable laboratory quality controls generally charge premium international rates for cellular expansion and biological testing. These costs, typically ranging from $15,000 to over $35,000, do not include necessary international flights, specialized medical transport, or extended hotel stays for post-treatment monitoring. Patients must ensure comprehensive financial planning prior to initiating a consultation.
For patients researching COPD treatment with stem cells, the clinical reality separates hope from medical empirical data. While studies like Le Thi Bich 2020 show measurable reductions in systemic inflammation, no current cellular therapy can regenerate destroyed lung tissue. The safest approach demands prioritizing FDA-approved bronchodilators and pulmonary rehabilitation before considering any international experimental adjuncts.
Applying the Evidence-Led Suitability Matrix protects patients from predatory marketing. By objectively evaluating your current GOLD stage against your functional goals, you can determine if the physiological risks of international travel and experimental intervention are medically justified for your specific pathology.
If you have exhausted standard care and wish to determine clinical eligibility in Thailand, contact our medical team via WhatsApp for a free suitability review. You must provide recent spirometry results (FEV1), your official GOLD stage diagnosis, and current CT imaging reports for our pulmonologists to conduct a legitimate, evidence-based assessment.