Our Services
Others
- DFPP
- Shockwave
- IV Drip

Patients evaluating structural deflation quickly discover the severe limitations of repeat synthetic injectables. Fillers are fantastic for minor touch-ups. But for lasting architectural repair? They fall short. If you’ve been chasing your youth with syringe after syringe of hyaluronic acid, you likely feel fatigued by the temporary, and often unnatural, results. Regenerative medicine points toward a more permanent biological solution: autologous tissue.
Standard fillers don’t address the underlying biological deterioration of your tissue. And if you’ve gone through rapid weight loss specifically with modern GLP-1 medications this hollowing accelerates drastically. It leaves the face looking skeletal rather than youthful. You aren’t just losing fat; you’re losing the very scaffolding that holds your face up.
This guide breaks down stem cell treatment for facial volume loss area by area, directly comparing it to fillers so you can determine your clinical suitability. We’ll analyze the raw science of stem cell-enriched fat grafting, look at area-specific outcomes, examine realistic graft survival rates, and honestly assess the critical limits of what added volume cannot lift.
Stem cell treatment for facial volume loss utilizes autologous fat grafting enriched with mesenchymal stem cells to biologically restore depleted structural zones.
Volume loss is not merely superficial skin wrinkling; it is driven by The Tri-Level Volume Loss Matrix: the simultaneous degradation of collagen, deflation of deep fat pads, and resorption of underlying facial bone. As skeletal support diminishes, fat compartments shift downward, creating the visible hollows and folds traditionally treated with temporary injectables. Facial aging is a three-dimensional deflation process; skeletal bone mass decreases by roughly 10% between ages 40 and 60, accelerating overlying fat pad displacement (Plastic and Reconstructive Surgery, 2019).
So, exactly why does the face lose volume with age? It starts deep at the skeletal level. The facial skeleton actively remodels over time. You specifically lose projection in the maxilla (the upper jaw) and the orbital rim surrounding your eyes. As the maxilla retreats, it fundamentally alters your dental arch support, pulling the midface inward. Think of it like the foundation of a house slowly shrinking beneath the siding. Clinical anatomical studies show this continuous bone remodeling drastically reduces the surface area available to support soft tissue.
Above this retreating bone sits your facial fat. These aren’t just random blobs of tissue; they are highly distinct anatomical compartments called malar fat pads and sub-orbicularis oculi fat. They don’t simply droop due to gravity. They physically atrophy. They lose cellular volume.
When this deep structural support collapses, the superficial skin the extracellular matrix caves inward. This causes the visible folds and hollows you see in the mirror. Contrast this severe three-dimensional deflation with the incredibly common, yet flawed, practice of just injecting superficial fillers. Filler masks the problem. It doesn’t restore structural integrity (Aesthetic Surgery Journal, 2021).
While chronological aging predictably degrades these layers, rapid systemic changes accelerate the process violently. Enter the era of GLP-1 weight loss medications like semaglutide and tirzepatide. Clinical communities define “Ozempic face” as aggressive, rapid depletion of facial adipose tissue following significant, medically induced weight loss.
Facial volume loss after weight loss treatment is disproportionately severe because you rapidly lose essential buccal and temporal fat. These are your facial structural anchors. When lipolysis (fat breakdown) occurs this rapidly, the overlying skin envelope simply cannot contract fast enough to match the volume reduction, leading to severe, gaunt hollowing.
Reversing this profound level of deflation requires more than a temporary gel. Patients presenting with this extreme hollowing require autologous fat transfer. Why? Because the sheer volume of synthetic filler needed to correct severe weight-loss hollowing inevitably leads to a bizarre, puffy result known as “pillow face.” You need biologically active tissue to replace what was lost, not just a space-occupying gel (Journal of Cosmetic Dermatology, 2024).
Stem cell-enriched fat grafting, formally known as cell-assisted lipotransfer (CAL), advances traditional fat transfer by fortifying harvested adipose tissue with a concentrated dose of the patient’s own multipotent cells. This stromal vascular fraction (SVF) prevents the rapid graft reabsorption that plagues standard fat transfer. Stem cell enrichment significantly improves facial fat graft retention; clinical data indicates that enriched grafts achieve survival rates of 70% to 80%, compared to 40% to 50% for standard fat transfer (Aesthetic Plastic Surgery, 2021).
The process of stem cell tissue regeneration relies entirely on your own biology. The first step involves micro-liposuction harvesting of fat from donor sites typically the abdomen or the flanks.
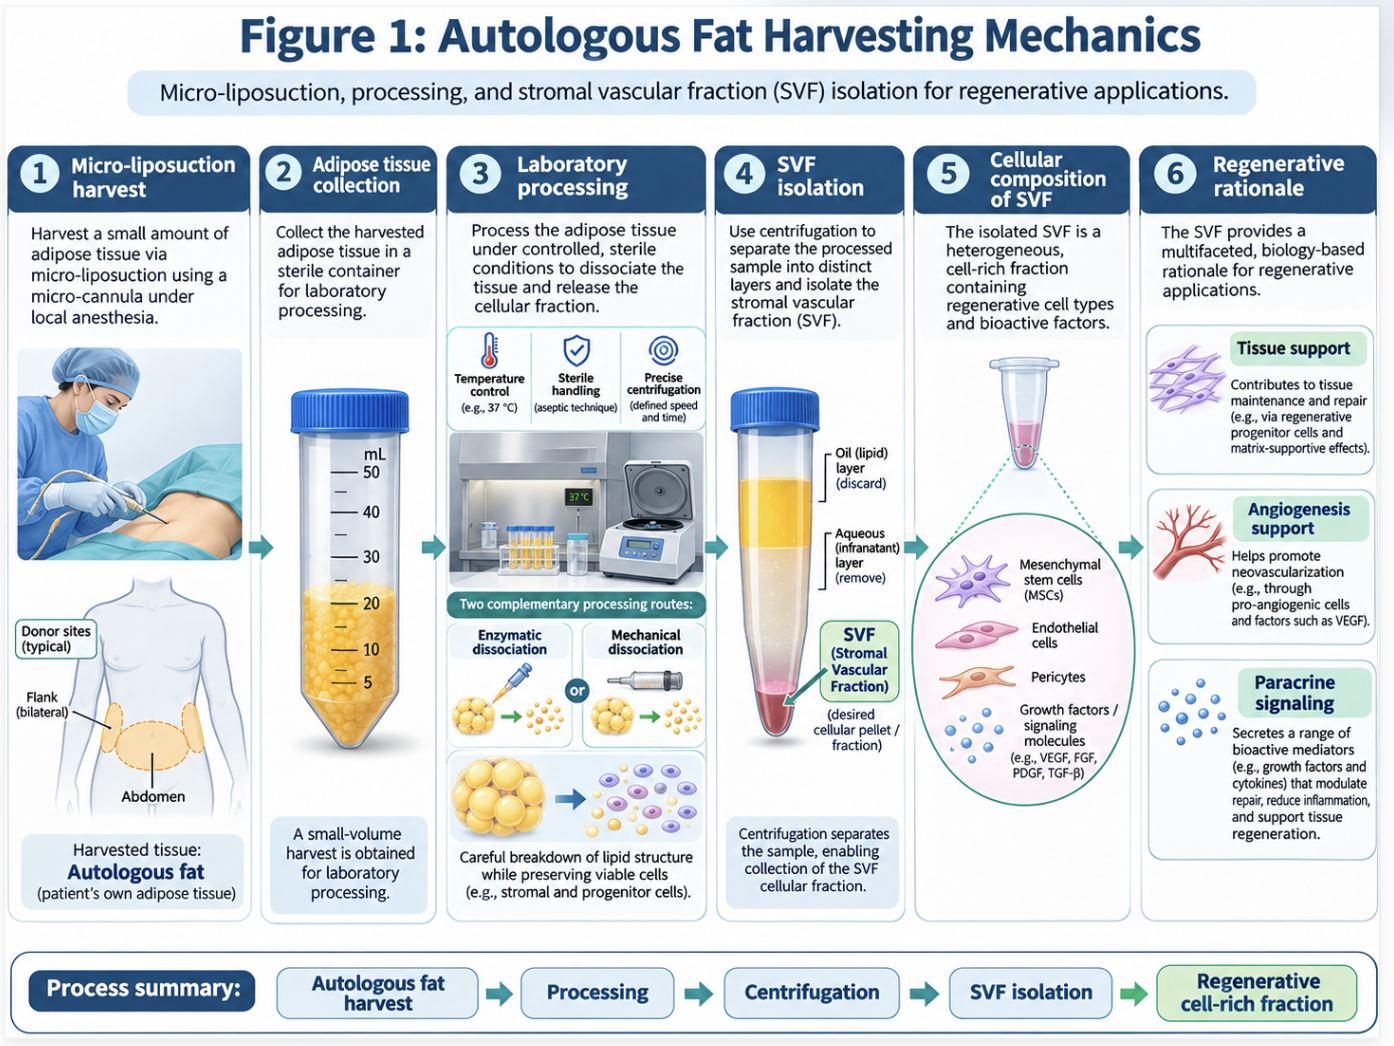
Once harvested, the clinician processes a portion of this fat enzymatically or mechanically. The laboratory phase requires strict temperature control and precise centrifugation to break down the lipid membrane without damaging the delicate stem cells inside. This isolates the Stromal Vascular Fraction (SVF). SVF is liquid gold. It’s packed with mesenchymal stem cells (MSCs), endothelial cells, and potent growth factors (Stem Cell Research & Therapy, 2021).
| 📌 If you’re interested in why the percentage of living cells matters so much at the time of treatment, we have an interesting article that discusses the importance of cell viability in UC-MSC stem cell therapy, which you can read via the internal link. |
This highly concentrated SVF is then recombined with the remaining purified fat before the surgeon injects it into your face. Contrast this autologous approach using your own body’s tissue with synthetic hyaluronic acid fillers. There is zero risk of allergic rejection. It permanently integrates into your facial structure. And because it’s living tissue, it behaves naturally with facial movement, unlike stiff gels that can migrate over time.
Beyond simply surviving as a biological filler, these cells actively change the aging environment of your face. Mesenchymal stem cells utilize paracrine signaling. They secrete bioactive molecules, including critical epidermal and vascular growth factors. When introduced to the aging face, these cells often recognize an ischemic (low-oxygen) environment and respond by building a fresh microvascular network.
These signals wake up your quiescent dermal fibroblasts, triggering neocollagenesis. Rebuilding collagen with stem cells isn’t a marketing myth; it’s documented synthesis of new type I and type III collagen, along with fresh elastin fibers (Dermatologic Surgery, 2020).
Furthermore, this creates a profound epigenetic shift. The cellular secretomes from these youthful stem cells promote the repair of senescent (aging) tissues and modulate local immune responses to reduce inflammation. They literally improve the overlying skin texture and hydration from the inside out. Fillers only stretch the skin outward. Enriched fat grafting improves the biological quality of the skin itself. You aren’t merely filling a void; you are actively reversing localized tissue decay.
| 📌 If you’re interested in how MSCs calm overactive immune cells throughout the body, we have an interesting article that discusses mesenchymal stem cell therapy for immune modulation, which you can read via the internal link. |
Not all facial regions respond identically to volume restoration. Because facial fat transfer relies on local blood supply to survive, highly mobile areas retain less volume than fixed zones. Evaluating stem cell treatment for facial volume loss against traditional dermal fillers requires a precise, area-by-area anatomical assessment.
The tear trough is notoriously unforgiving. Standard hyaluronic acid fillers often cause the Tyndall effect a bluish tint under the thin skin or chronic edema (swelling) because HA is highly hydrophilic. It holds water and creates morning puffiness that patients despise. Stem cell under eye treatment using micro-fat or nano-fat provides a permanent, natural-looking correction. It doesn’t hold excess fluid, and there’s absolutely no Tyndall effect. Plus, the stem cells thicken the overlying skin, effectively hiding the dark vascular structures underneath.
But if you’re wondering about fat transfer under eyes and the risk of lumps, the science is clear. Macro-fat will look lumpy. Precision nano-fat grafting which completely emulsifies the fat into a smooth cellular matrix devoid of bulky adipocytes is strictly required for the periorbital area to ensure a perfectly smooth outcome (Ophthalmic Plastic and Reconstructive Surgery, 2022). Clinical data shows that when nano-fat is properly processed, complication rates related to contour irregularities drop to nearly zero in this delicate zone.
Temporal hollowing creates a skeletal, “peanut-head” appearance. We see this constantly in older adults and GLP-1 weight loss patients. It’s a dead giveaway of structural aging that shadows the upper face and makes the brow look heavy. Using standard fillers for temple hollowing treatment requires massive volumes often two to four heavy syringes per side. This makes temporary fillers wildly cost-prohibitive for a result that simply fades away in 12 to 18 months.
Stem cell-enriched fat is objectively the superior choice here. The temporal fossa boasts an incredibly rich vascular supply. This leads to exceptionally high graft survival rates, often exceeding 85% with CAL techniques. It provides permanent, structural widening of the upper third of the face, restoring the youthful inverted triangle shape effortlessly. Because the temples don’t move aggressively like the mouth, the fat stays exactly where the surgeon places it, integrating seamlessly with the underlying temporalis muscle fascia.
Deflation of the deep malar fat pads severely flattens the midface, creating the illusion that the whole face is melting downward. When clinicians attempt to fix this with massive amounts of filler, the product often drifts or looks overly pillowy when the patient smiles a very common phenomenon known as “filler fatigue.” Fat grafting for sunken cheeks excels precisely where these gels fail. The malar region is a remarkably stable anatomical zone with dense vascularity.
It serves as the absolute optimal recipient site for fat transfer (Facial Plastic Surgery Clinics, 2018). Because the cheek moves less aggressively than the lower face, it yields the highest retention rates of grafted fat. Stem cells permanently restore the apex of the cheek, lifting the midface naturally without the artificial stiffness of heavy dermal fillers. You get real tissue regeneration that mimics the exact fat pads you had in your twenties, maintaining natural facial expressions without distortion.
The nasolabial folds (smile lines) deepen primarily due to descending cheek fat, not necessarily because the fold itself lost intrinsic volume. It’s largely a shadowing effect caused by heavy, drooping tissue above it. Here’s the clinical reality: fat grafting directly into the nasolabial fold has a notoriously lower survival rate.
Why? The constant movement of the sphincter muscles around the mouth literally prevents the fragile graft from establishing a vascular blood supply. The movement starves the graft before it can survive. When weighing fillers or fat transfer for nasolabial folds, stiff structural fillers are often much more predictable. A better approach for stem cell treatment for nasolabial folds is actually treating the cheeks to lift the heavy tissue off the fold, rather than chasing the line directly with fat. Injecting high volumes of fat directly into these highly mobile creases usually results in rapid reabsorption.
We must immediately address the pervasive myth of the “liquid facelift” or volumetric lifting. Adding volume does not magically shrink redundant skin. A stem cell treatment for sagging jawline issues can effectively camouflage minor pre-jowl sulcus hollowing, helping to temporarily blend the jawline border. But it cannot lift severely sagging jowls or lax neck skin. Gravity wins that battle every single time (Plastic and Reconstructive Surgery, 2020).
If a provider attempts to fix severe jowling by pumping heavy volume into a sagging jawline, it inevitably results in a heavier, wider lower face often making the patient look overweight rather than youthful. For significant structural laxity, excisional surgery like a deep-plane facelift is absolutely mandatory. Regenerative medicine is a brilliant adjunct to improve skin quality and replace lost deep volume, but it should never be presented as a viable replacement for excisional lifting when severe skin redundancy is the primary issue.
Patients transitioning from temporary fillers to autologous fat transfer must violently adjust their expectations regarding recovery timelines. Unlike hyaluronic acid, which provides instant, finalized results before slowly degrading, stem cell-enriched fat grafting involves real surgical downtime. It requires a months-long stabilization process as the tissue establishes an independent blood supply. Following facial fat grafting, patients should expect significant edema for 10 to 14 days, with final volume retention stabilizing at 3 to 6 months post-procedure (Journal of Plastic, Reconstructive & Aesthetic Surgery, 2021).
Let’s talk numbers. A percentage of transferred fat will inevitably die and be reabsorbed by your body. That is a biological fact.
So, how much facial fat transfer survives? Standard fat transfer survival rates hover around 40% to 60%. However, stem cell-enrichment (CAL) reliably pushes those survival rates to 70% to 80% (Aesthetic Surgery Journal, 2021). The SVF promotes rapid angiogenesis the formation of new blood vessels that feed the graft, ensuring long-term cellular viability.
You must understand the timeline. The volume you see at week two is mostly swelling. The true, permanent biological result isn’t finalized until months three to six. Don’t panic when the initial swelling subsides; the surviving stem cells are actively integrating into the host tissue architecture.
When we discuss facial fat grafting recovery and swelling, we dispense with the marketing promises of “lunchtime procedures.”
You are looking at significant social downtime of 7 to 14 days. This is due to intense edema (swelling) and potential bruising at both the donor and recipient sites. Surgeons intentionally utilize “overcorrection.” They inject slightly more fat than you actually need, anticipating the natural reabsorption rate. You will look overly swollen and puffy for the first few weeks.
Crucially, you must not compress the face or undergo aggressive facial massages during this early vascularization phase. Pressure physically kills the fragile graft before it connects to your blood supply. Protect the investment by sleeping elevated at a 45-degree angle, avoiding restrictive masks, and skipping ice packs that inappropriately constrict vital blood flow to the new graft.
Fat transfer under the eyes will not look lumpy if the surgeon utilizes purified nano-fat grafting. Standard macro-fat particles are too large for the delicate, thin skin of the periorbital region and can create visible irregularities. By emulsifying the tissue into nano-fat, clinicians isolate the regenerative stem cells and cellular matrix without bulky adipocytes. This technique smoothly corrects hollowing and dark circles. Patients must verify their provider specializes in periorbital nano-fat protocols to ensure smooth outcomes.
Stem cells can significantly improve dark circles caused by tissue thinning and vascular transparency. Mesenchymal stem cells in the grafted fat trigger localized neocollagenesis, thickening the dermal layer of the lower eyelid. This biological thickening effectively masks the underlying dark venous structures that cause the discoloration. While it corrects structural dark circles, it is less effective for hyperpigmentation caused by genetics or sun damage. A clinical assessment is necessary to determine the exact etiology of the dark circles before treatment.
Facial fat transfer is considered a permanent volumetric correction, as the surviving fat cells integrate completely into the facial tissue. Once the grafted fat establishes a blood supply typically within three to six months it behaves like native fat for the rest of the patient’s life. Stem cell enrichment increases the percentage of cells that survive this initial phase to roughly 80% (Aesthetic Surgery Journal, 2021). However, these permanent cells will still naturally shrink or expand in response to future systemic weight fluctuations and chronological aging.
For adults addressing severe structural deflation, stem cell treatment for facial volume loss provides a permanent, autologous alternative to temporary fillers, with enriched grafts demonstrating up to 80% long-term survival (Plastic and Reconstructive Surgery, 2021). The most effective approach requires a precise area-by-area assessment, prioritizing the cheeks and temples for fat grafting while recognizing the limitations of volume in the highly mobile lower face.
Success depends heavily on understanding The Tri-Level Volume Loss Matrix. Because rapid GLP-1 weight loss and chronological aging degrade bone, deplete fat pads, and thin the collagen matrix simultaneously, masking the issue with superficial filler is chemically inefficient. You need structural, biologically active tissue to replace what was physically lost.
Take action today by booking a consultation with a board-certified regenerative aesthetic specialist. They will evaluate your distinct facial fat pads and determine your exact clinical suitability for cell-assisted lipotransfer. A thorough medical evaluation ensures your treatment plan matches your anatomical reality.
| 📌 If you’re planning treatment in Thailand and want a practical checklist for choosing a safe clinic, we have an interesting article that discusses whether stem cell therapy is safe in Thailand, which you can read via the internal link. |
This article is for educational purposes only and does not replace consultation with a qualified medical professional.