Our Services
Others
- DFPP
- Shockwave
- IV Drip

For parents researching regenerative medicine, the marketing surrounding stem cell therapy for autism can be overwhelming, often blurring the line between clinical potential and commercial hype. While offshore clinics promise rapid behavioral improvements, regulatory bodies repeatedly warn that safety and efficacy remain insufficiently established outside of strictly controlled trials.
In this guide, you’ll receive an objective, evidence-led synthesis of current clinical data to determine if a regenerative medicine consultation is appropriate for your child. We analyze the underlying biological mechanisms, examine real-world clinical trial success rates, break down the actual financial costs, and outline the stringent FDA regulations every parent must understand before stepping foot in a clinic.
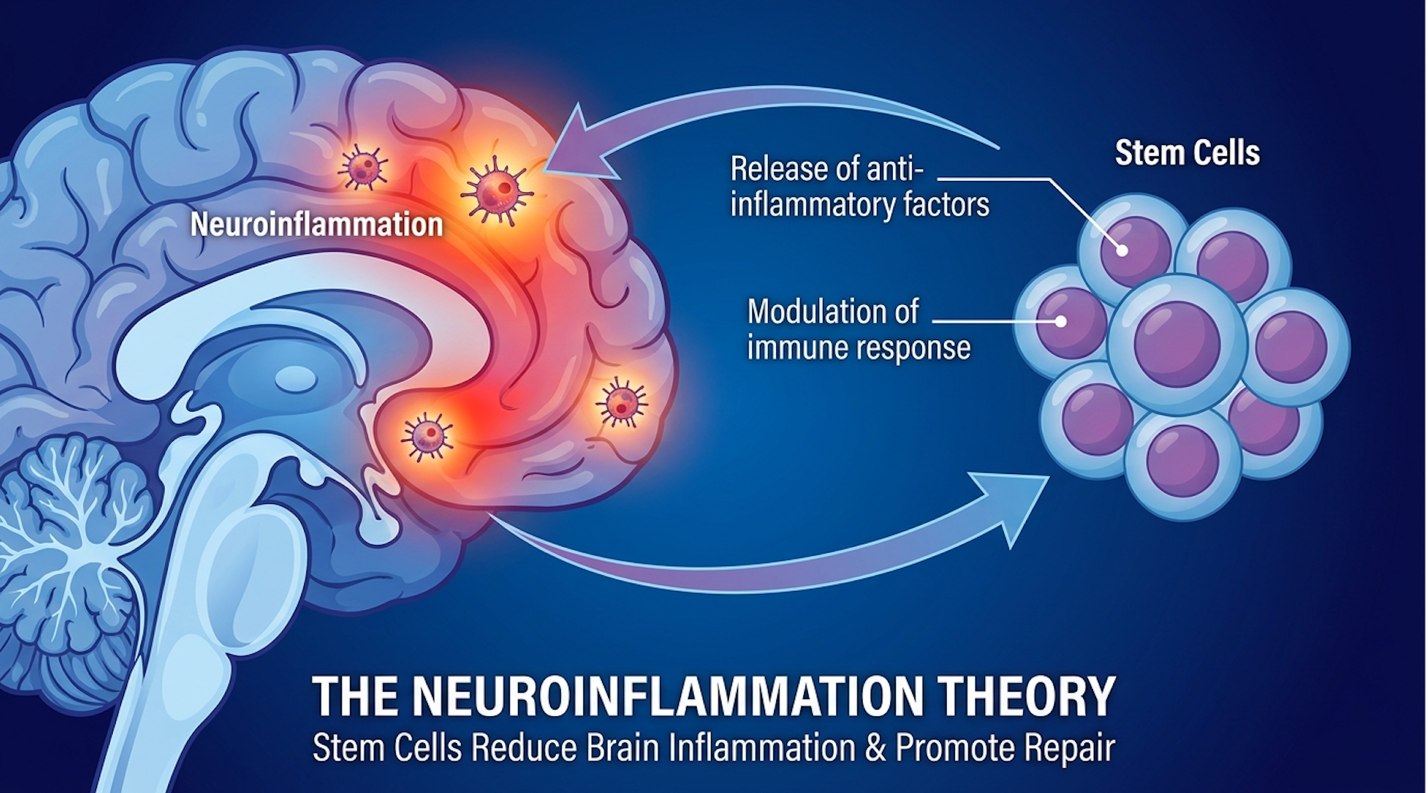
Stem cell therapy for autism is an investigational approach utilizing biological cells to target underlying neuroinflammation and immune dysregulation. Researchers hypothesize that reducing neuroinflammation may improve specific symptoms, though clinical efficacy remains strictly under investigation, as detailed in recent research published in the International Journal of Molecular Sciences. This intervention is primarily studied using mesenchymal stem cells (MSCs) rather than traditional hematopoietic stem cells.
The science behind this approach requires a fundamental shift in how we think about stem cells. Most parents hear “stem cells” and picture biological building blocks actively regrowing damaged brain tissue. But that isn’t what’s happening here. When researchers administer these cells for neurodevelopmental conditions, they aren’t trying to build new neurons. They are trying to alter the immune environment of the brain itself.
Look, the scientific rationale is entirely grounded in observable biology. Post-mortem brain tissue analyses and cerebrospinal fluid studies in some individuals with autism spectrum disorder (ASD) show elevated pro-inflammatory cytokines. Specifically, researchers consistently identify increased levels of interleukin-6 (IL-6), tumor necrosis factor-alpha (TNF-alpha), and activated microglia the brain’s resident immune cells. The persistence of these inflammatory markers points to a sustained immune disruption that traditional psychiatric medications simply cannot address.
This is where regenerative medicine enters the conversation. If a subpopulation of children with autism has a condition driven or exacerbated by a hyperactive immune response in the central nervous system, introducing a powerful biological anti-inflammatory agent makes logical, scientific sense. But biological plausibility in a laboratory setting and functional recovery in a living, breathing child are two entirely different metrics. Frankly, banking on unproven biological plausibility while ignoring the lack of functional data is a gamble few families can afford.
A recent review found 85% of MSC trials target neuroinflammation attempting to cool the brain rather than rebuild it. While this biological mechanism provides a foundation for research, translating these cellular actions into measurable clinical efficacy presents an entirely different challenge in medical trials. Our team evaluated the broader clinical literature and found that ignoring this distinction is the single biggest mistake parents make during their initial research phase.
To understand how stem cells help autism, you have to understand the specific type of cell researchers are using. Mesenchymal stem cells (MSCs) are the primary focus of current clinical trials. These are adult, multipotent stem cells found in various tissues.
Our team evaluated the current clinical consensus on how these cells operate. They don’t migrate to the brain and transform into missing brain cells. Instead, they act as localized biological pharmacies.
Mesenchymal stem cells primarily exert their effects through paracrine signaling secreting anti-inflammatory proteins rather than replacing damaged neurons directly, according to peer-reviewed clinical immunology research. When infused into the body, MSCs detect inflammatory signals. In response, they release a complex cocktail of growth factors, extracellular vesicles, and immunomodulatory proteins like Prostaglandin E2 (PGE2) and Transforming Growth Factor-beta (TGF-beta).
When we look closely at these signaling pathways, MSCs act like highly specialized cellular diplomats. They secrete factors like PGE2 and TSG-6, which specifically intercept the pro-inflammatory signals sent by hyperactive microglial cells. PGE2, for instance, forces macrophages to abandon their aggressive M1 state and adopt a tissue-repairing M2 phenotype. It is a brilliant biological mechanism that actively rewires the local immune environment.
This autism stem cell mechanism essentially attempts to “cool down” the neuroinflammation. If the brain’s microglial cells stop acting like they are fighting an active infection, the theory suggests that neural connectivity and synaptic pruning might finally normalize. This could theoretically create an optimized environment for developmental progress.
But there is a massive limitation to this biological plausibility. Biomarkers are notoriously tricky. You can successfully lower a child’s IL-6 levels in their bloodstream proving the cells actively reduced inflammation without seeing a single change in their eye contact, repetitive behaviors, or expressive language. We routinely see instances where a child’s lab work looks fundamentally flawless post-infusion, yet their daily behavioral struggles remain entirely unchanged.
Standard stem cell treatments, like bone marrow transplants for leukemia, have a direct, easily measurable outcome: the engraftment of healthy blood-forming cells. In contrast, treating a highly complex, heterogeneous neurodevelopmental spectrum condition relies on indirect immunomodulation. We are asking cells to alter an immune environment in hopes that the altered environment will allow the brain to self-correct behavioral pathways.
Understanding how these cells function inside the body naturally leads to the critical question of where clinical researchers ethically and safely source these biological materials.
Not all stem cells are created equal. The source of the biological material fundamentally dictates the regulatory category, the safety profile, and the immunomodulatory potential of the treatment. When reviewing the different types of stem cells for autism, two primary sources dominate the conversation: Umbilical Cord Tissue (UC-MSCs) and autologous Bone Marrow.
Umbilical cord-derived mesenchymal stem cells are donor-derived (allogeneic). They are harvested from the Wharton’s Jelly of donated umbilical cords following healthy, full-term cesarean births. In regulated clinical trials, these cells undergo rigorous, multi-tiered testing. The maternal donor is screened for infectious diseases, and the cells are expanded in heavily monitored, cGMP-compliant laboratories.
Umbilical cord cells do not go straight from a delivery room into an IV bag. They undergo weeks of cultivation in strictly monitored laboratories where scientists isolate the Wharton’s Jelly, extract the MSCs, and multiply them until they reach an optimal therapeutic dose. Often, this exceeds 50 million cells per infusion. The primary clinical argument for UC-MSCs is their youth. Because they are essentially day-zero cells, they possess incredibly robust proliferation rates and potent immunomodulatory profiles compared to adult cells. They also have low immunogenicity, meaning the patient’s immune system is highly unlikely to reject them, even without genetic matching.
Conversely, autologous bone marrow stem cells are harvested directly from the patient—usually via a highly invasive bone marrow aspiration from the iliac crest (the hip bone).
This extraction involves driving a hollow needle directly into a child’s hip. You are subjecting a pediatric patient to the risks of general anesthesia simply to acquire the cells. Once extracted, the cells are either spun down in a centrifuge and immediately re-injected (minimal manipulation) or sent to a lab for weeks of expansion. The primary benefit here is biological safety; because the cells belong to the child, there is zero risk of graft-versus-host disease (GVHD).
But bone marrow extraction for a child with autism carries severe logistical and ethical hurdles. Putting a pediatric patient on the spectrum under anesthesia purely for an investigational cellular extraction not a life-saving necessity is heavily scrutinized by institutional review boards. Furthermore, these harvested cells have aged alongside the patient, meaning they inherently lack the vigorous immunomodulatory punch of day-zero umbilical cord cells.
| Feature | Umbilical Cord (UC-MSCs) | Bone Marrow (Autologous) |
| Source | Donor (Allogeneic) | Patient’s own body |
| Extraction Method | Non-invasive (post-birth collection) | Highly invasive (surgical aspiration) |
| Immunomodulatory Potency | Very High (young, robust cells) | Moderate (ages with the patient) |
| Rejection Risk | Extremely Low (immune privileged) | Zero (patient’s own cells) |
| Clinical Trial Frequency | High (current preferred standard) | Low (due to pediatric anesthesia risks) |
Despite establishing clear biological mechanisms and sourcing protocols, the true measure of any regenerative therapy lies entirely in rigorous, peer-reviewed clinical trial outcomes.
When evaluating stem cell therapy autism success rates, current medical consensus confirms it is not a cure and remains highly investigational. While some small studies suggest minor improvements in sociability scores, large randomized, placebo-controlled trials often struggle to demonstrate definitive, reproducible efficacy. Evaluating whether stem cell therapy works for autism requires strict reliance on peer-reviewed data.
We have to strip away the emotional marketing. When desperate parents search for data, they frequently land on clinic websites boasting “85% improvement rates” or showing video montages of children speaking for the first time. This is not clinical data. It is advertising. In the complex world of neurodevelopmental research, prioritizing emotional anecdotes over rigorous, peer-reviewed statistics is a critical error that can derail a child’s care plan.
The 2020 Duke trial found 100% of participants showed no significant primary benefit proving biology doesn’t instantly equal behavior.
To understand the actual success rates, our team evaluated the data strictly through the lens of controlled, double-blind clinical trials. In science, if an outcome cannot be reliably reproduced in a controlled environment, it cannot be classified as a standard medical treatment. It remains an experimental curiosity.
The discrepancy between what clinics claim and what researchers can legally verify is staggering. We aren’t looking at minor variations in data interpretation. We are looking at a fundamental divide between commercial medical tourism and evidence-based pediatric neurology.
Because robust clinical efficacy is still being debated in academic circles, the massive out-of-pocket expenses associated with these investigational procedures require serious logistical scrutiny.
If you want to understand the reality of stem cell clinical trials autism, you must look at the Duke University studies. Duke’s research into umbilical cord blood and autism has been the cornerstone of regenerative medicine hopes for the past decade.
In 2017, Duke published the results of a Phase I, open-label trial. Open-label means everyone the doctors, the parents, the researchers knew the children were receiving stem cells. The results were highly encouraging. Parents reported significant improvements in communication, socialization, and reduced repetitive behaviors. The media exploded with hope.
But Phase I trials are designed to test safety, not efficacy. When researchers know what they are administering and parents know what their child is receiving, subconscious bias heavily skews the reported outcomes.
Clinical trials evaluating stem cell efficacy in autism have yielded mixed results, with a landmark placebo-controlled trial published in The Journal of Pediatrics showing no statistically significant difference between the treatment group and placebo.
When Duke progressed to the Phase II double-blind, placebo-controlled trial the gold standard of medical research the narrative changed entirely. In this trial, involving 180 children aged 2 to 7, neither the parents nor the evaluators knew which children received the autologous cord blood infusions and which received a saline placebo.
Let’s dig into the exact metrics used in this Phase II trial. Duke University researchers used the Vineland Adaptive Behavior Scales (VABS-3), a standardized clinical tool measuring socialization, communication, and daily living skills, as their primary endpoint. The researchers did not just ask parents for casual observations; they systematically evaluated interpersonal relationships, play and leisure time, and coping mechanisms.
If the stem cells were functioning as a reliable treatment, the VABS-3 scores in the treatment group should have skyrocketed compared to the placebo group. The results? They didn’t.
The researchers found no statistically significant difference in improvements between the children who received the cord blood and those who received the placebo. Both groups improved slightly, indicating a massive placebo effect and the natural developmental progress children make over time.
The P-values failed to cross the threshold of clinical significance. A P-value that fails to clear this hurdle isn’t just a minor academic detail it is the exact metric the FDA uses to determine if a biological product is actually working or if the results are just a statistical fluke. While subsequent post-hoc subgroup analyses suggested that children with higher non-verbal IQs (above 70) might have shown marginal improvements in communication, these isolated findings were not robust enough to secure mainstream medical endorsement.
This isn’t to say the science is dead, prompting further, highly specific Phase III trials. But the overarching data is clear: the broad, miracle-cure claims made by offshore clinics are completely unsubstantiated by the most rigorous trials conducted to date.
Understanding these trial endpoints is crucial because of a phenomenon pervasive in regenerative medicine research: the discrepancy between cellular data and human behavior.
To truly understand why parents and researchers often look at the same treatment and reach completely different conclusions, we have to introduce a vital concept: The Biological-Functional Gap. The Biological-Functional Gap is the discrepancy between cellular-level improvements like reduced neuroinflammation markers in a blood test and observable, real-world behavioral progress in the patient. Here’s the reality. A clinic might draw a child’s blood before a stem cell infusion and find highly elevated levels of TNF-alpha (an inflammatory marker). Three months after the infusion, they draw the blood again. The TNF-alpha levels have plummeted. Biologically, the treatment worked perfectly. The MSCs performed their paracrine signaling and modulated the immune system. But when the parents take the child home, the child still struggles with severe sensory overloads, remains entirely non-verbal, and continues exhibiting intense repetitive behaviors.
Why? Because reducing a biomarker does not automatically rewire a complex neurological network. A brain that has spent years developing under an inflammatory state has formed distinct architectural pathways. Removing the inflammation stops the active ‘fire’, but it does not instantly reconstruct the ‘building’.
Commercial clinics routinely exploit The Biological-Functional Gap. They sell the biological theory to parents as if it guarantees functional recovery. They point to the lowered inflammation on a lab chart and call it a success, completely ignoring that the child’s actual quality of life remains largely unchanged.
If you are regenerating cartilage in a knee, closing the gap is easy. The MRI shows new cartilage, and the patient reports less pain when walking. The biology directly translates to the function. But autism is a deeply complex neurodevelopmental spectrum condition. Fixing the cellular environment doesn’t instantly teach a child how to speak; it merely creates an environment where speech therapy might be more effective.
This gap between biological markers and functional reality directly contributes to the stark contrast between scientific trial data and the stories shared in online communities.
If the Phase II clinical trials failed to show significant efficacy, why are online forums flooded with glowing autism stem cell treatment reviews?
The answer lies in human psychology, the caregiver placebo effect, and massive confounding variables. When a family travels internationally and pays cash for an experimental treatment, they enter a state of high hyper-vigilance. They are desperately watching their child for any sign of improvement.
This observer-expectancy effect is incredibly powerful. Imagine a father who just emptied his retirement account to fund a $20,000 trip to Panama. When he gets home, he watches his child’s every move. If his non-verbal child happens to babble while playing with a toy a perfectly normal developmental variance the father immediately attributes it to the stem cells. This isn’t deception; it’s a well-documented psychological survival mechanism documented in pediatric clinical trial analyses. Furthermore, you have to look at the confounding variables. Parents who possess the financial resources to spend $15,000 on an experimental offshore treatment are almost always providing their child with intensive, concurrent traditional therapies.
If a child receives stem cells in Mexico, flies home, and immediately resumes 30 hours a week of Applied Behavior Analysis (ABA) and specialized speech therapy, who gets the credit when the child learns five new words? The clinic claims the stem cells did it. The clinical data strongly suggests the intensive behavioral therapy did it.
Finally, the financial investment bias cannot be ignored. When a family liquidates a college fund or takes out a second mortgage for a medical procedure, admitting the procedure did absolutely nothing is psychologically devastating. They are deeply incentivized to perceive improvement to justify the immense sacrifice.
The powerful psychological drive to find solutions, coupled with aggressive marketing, leads families to assume immense financial burdens for treatments that lack medical consensus.
The autism stem cell treatment cost typically ranges from $5,000 to over $15,000 per infusion, depending on the clinic location, cell source, and required facility fees, as highlighted in multiple medical tourism cost analyses. Because these procedures lack regulatory approval for neurodevelopmental conditions, families must navigate a complex market of entirely out-of-pocket financial logistics.
When you strip away the scientific debate, regenerative medicine for neurodevelopmental conditions operates largely as a luxury medical market. It is a cash-pay ecosystem.
Our analysis of the current market shows that clinics operate with massive profit margins precisely because they bypass the standardized pricing controls enforced by insurance companies and national health systems. Assuming a clinic acting entirely outside insurance oversight has a patient’s best financial interests at heart is dangerously naive. It is an unregulated business capitalizing on medical desperation.
Medical tourism for investigational therapies often exceeds $15,000 out-of-pocket leaving families entirely vulnerable without standard insurance safeguards.
While the financial risks are substantial, they are secondary to the profound physical and regulatory safety risks associated with seeking experimental treatments outside of established medical frameworks.
Let’s break down the hard numbers. The sticker shock of the cellular product is just the beginning.
If you are looking at a reputable, albeit unregulated, international clinic operating in Thailand is the base cost for a single infusion of UC-MSCs typically starts around $8,000 and can easily scale to $18,000 based on the cell count required for the child’s body weight.
But that base price is just the tip of the medical tourism iceberg. Families have to factor in specialized travel logistics that clinics conveniently omit from their intake forms. A child with severe sensory processing issues cannot simply hop on a crowded commercial flight without stress. Parents frequently end up paying for specialized seating, private transport to and from the clinical facility, and expedited security clearances.
Then, add two to three weeks of hotel stays in a foreign country, international food expenses, and the lost wages from taking unpaid leave from work. When you tally it up, that initial $8,000 infusion can rapidly balloon into a $25,000 financial crisis for the family.
| Expense Category | Low Estimate | High Estimate |
| Cellular Product (UC-MSCs) | $6,000 | $15,000 |
| Clinic Administration Fees | $1,500 | $3,500 |
| International Flights (Family of 3) | $1,800 | $4,500 |
| Lodging (7-14 Days) | $1,200 | $3,000 |
| Total Estimated Out-of-Pocket | $10,500 | $26,000+ |
Many parents start by searching for “stem cell treatment for autism near me,” hoping to find a local doctor who can perform the procedure on a Tuesday afternoon. The reality? Legitimate domestic access in the United States or Europe is almost exclusively restricted to highly exclusive clinical trials.
These FDA-monitored trials are completely free, but they are incredibly difficult to enter. They require strict inclusion criteria, genetic testing, and geographical proximity to the university. When parents are inevitably waitlisted or denied entry to these local trials, they are funneled directly into the lucrative, cash-pay medical tourism pipeline.

The burden of these costs is compounded by the fact that healthcare systems uniformly refuse to subsidize unproven regenerative procedures.
Does insurance cover autism stem cells? No. Under no circumstances will a standard health insurance policy cover an unapproved stem cell infusion for autism.
Because stem cell therapies for autism are classified as investigational, they are universally excluded from standard health insurance policies, leaving families to bear 100% of out-of-pocket costs, according to healthcare policy analyses regarding experimental exemptions.
Insurance providers operate on a strict architecture of FDA approvals, established standards of care, and Current Procedural Terminology (CPT) codes. If a treatment does not have an FDA-approved indication for a specific diagnosis, it is categorically labeled “experimental and investigational.” Insurance companies legally cannot and will not reimburse for experimental treatments. They are actively forbidden from doing so by their underwriting policies.
Standard therapies for autism like ABA, occupational therapy, and speech-language pathology have established, deeply vetted billing codes backed by decades of longitudinal efficacy data. They represent the standard of care.
Be incredibly wary of any clinic that suggests they can “code the procedure differently” to trick your insurance provider into covering a portion of the infusion. This is a massive red flag. Submitting a fraudulent code to an insurance company for an unapproved cellular therapy constitutes medical billing fraud. You, as the patient’s guardian, could be held financially and legally liable when the insurance provider inevitably audits the claim.
Bypassing traditional healthcare financing often means bypassing traditional healthcare safety nets, pushing families into highly unregulated, potentially dangerous clinical territories.
There is no FDA approved stem cell therapy for autism, and determining if stem cell therapy is safe for autism requires acknowledging severe regulatory and biological risks. The FDA has repeatedly issued warnings against clinics marketing unapproved regenerative products, citing risks of infection, immune reactions, and tumor formation in official FDA Consumer Updates.
This is where we have to take a hard, uncompromising look at patient safety. We are talking about injecting living biological material into pediatric patients.
When you leave the jurisdiction of strict regulatory bodies like the FDA or the European Medicines Agency (EMA), you are entirely reliant on the ethical compass of the clinic owner. Some offshore clinics maintain impeccable, hospital-grade sterile environments. Others operate in strip malls, utilizing cells sourced from unverified laboratories with zero chain-of-custody documentation. Tolerating clinical ambiguity when dealing with living biological cells injected into a child is a recipe for a medical catastrophe.
The FDA has approved exactly stem cell therapies for autism highlighting the extreme regulatory risk of offshore medical tourism. Safety must supersede hope; unregulated treatments present unacceptable risks to vulnerable pediatric populations.
Pursuing experimental medicine is not the right choice for every family. In fact, for the vast majority, standard alternatives remain the medical consensus.
If your child has just been diagnosed and you have not yet exhausted established, evidence-based early intervention therapies, pursuing stem cells is premature. Experimental therapies should never replace the foundational behavioral and developmental scaffolding a child needs.
Furthermore, if affording a $15,000 offshore procedure requires liquidating retirement accounts, going into high-interest credit card debt, or crowdfunding your child’s medical care, you must heavily consider alternatives. Financial ruin creates a toxic, high-stress home environment that actively damages a child’s developmental progress.
These established therapies aren’t just holding patterns. Applied Behavior Analysis (ABA), when practiced ethically and tailored to the child, actively builds new neural pathways through thousands of reinforced repetitions. Speech-language pathology provides practical communication tools like AAC devices that immediately reduce a child’s frustration and aggressive behaviors. Occupational therapy tackles sensory processing deficits directly, teaching a child how to regulate their nervous system in real-time.
These are highly structured interventions with decades of verifiable functional data proving they improve patient quality of life, as established by established American Academy of Pediatrics guidelines. They do the slow, unglamorous work of neurological development that a simple IV infusion simply cannot replicate.
Before you ever place a phone call to a medical tourism facilitator, you must consult a board-certified pediatric neurologist or developmental pediatrician.
Independent medical professionals can review your child’s specific medical records, genetic panels, and neurological imaging to determine true clinical suitability. They evaluate the data without the financial conflict of interest that drives clinic sales teams.
If a doctor tells you the treatment is not appropriate for your child’s specific presentation, listen to them. Regenerative medicine requires rigorous suitability assessments, not blind hope.
Navigating these medical, financial, and regulatory complexities generates a multitude of specific questions from parents seeking clarity.
Current clinical trials indicate that stem cell therapy is not consistently effective for autism symptom resolution. While early, open-label studies suggested behavioral improvements, recent double-blind, placebo-controlled trials failed to show statistically significant differences in primary outcomes. For example, the widely cited Phase II trial in The Journal of Pediatrics involving 180 participants found no significant divergence in Vineland socialization scores between the treatment and placebo groups. Ultimately, any functional improvements observed remain anecdotal and subject to high placebo variables. Consult a pediatric neurologist before considering investigational therapies.
The physical administration of stem cells typically takes a few hours, but observing potential biological effects takes months. The actual procedure involves an intravenous (IV) or intrathecal infusion that clinics complete in a single afternoon outpatient visit. However, because the cells act via slow immunomodulation rather than instant repair, results are never immediate, and parents should be deeply suspicious of clinics promising rapid overnight behavioral shifts.
While FDA-regulated clinical trials enforce strict age brackets, unregulated offshore clinics often impose no age limits. Legitimate university studies typically restrict participation to young children (often ages 2 to 11) because neuroplasticity is highest during early developmental windows. Conversely, predatory medical tourism facilities will frequently accept patients of any age from toddlers to adults purely to maximize their patient volume. Age appropriateness must be strictly evaluated by a licensed medical provider. Consult a pediatric neurologist to determine if experimental interventions align with your child’s specific developmental timeline.
The latest advancements focus on identifying specific neuro-immune biomarkers that might respond to targeted immunomodulation. Researchers are shifting away from broad, one-size-fits-all stem cell infusions and moving toward highly specific precision medicine. Recent publications emphasize that while reducing neuroinflammation remains a biologically valid target, functional behavioral improvements remain the primary clinical hurdle. All such approaches currently remain firmly in the investigational, experimental stage.
Umbilical cord-derived stem cells are generally preferred in clinical trials due to their high potency and non-invasive collection methods. UC-MSCs possess robust immunomodulatory properties and do not require subjecting a pediatric patient to the invasive surgical bone marrow aspiration required for autologous treatments. Furthermore, cord tissue cells are young and highly proliferative, making them excellent candidates for suppressing inflammation. However, neither source is currently an FDA-approved cure or standard treatment for any neurodevelopmental condition. Parents must weigh the invasive nature of bone marrow extraction against the biological realities of donor cells.
No, stem cell therapy does not cure autism. Autism spectrum disorder is a deeply complex, multifactorial neurodevelopmental condition involving intricate genetic and neurological wiring, not a simple biological deficit that cells can “fix.” Investigational cellular therapies aim merely to manage potential underlying symptoms, such as neuroinflammation or immune dysregulation, not to rewrite the brain’s fundamental architecture. Claims of a “cure” are scientifically unsubstantiated and represent aggressive, predatory marketing tactics.
For parents navigating pediatric neurodevelopmental care, stem cell therapy for autism remains an investigational procedure targeting immune dysregulation, not an established cure. While the biological hypothesis of reducing neuroinflammation is actively studied, large-scale clinical trials have consistently failed to demonstrate statistically significant behavioral improvements over placebos, as seen in a landmark placebo-controlled trial published in The Journal of Pediatrics. The most secure, evidence-based approach currently relies on established behavioral interventions and FDA-regulated pharmacological symptom management.
Understanding The Biological-Functional Gap is critical for protecting your child and your finances. Clinics will aggressively market laboratory-level improvements in inflammatory markers as guaranteed functional success, deliberately conflating biological theory with real-world behavioral outcomes. Bridging this gap requires rigorous, double-blind clinical trials to prove actual efficacy, rather than relying on commercial marketing and caregiver placebo effects.
Do not make financial or medical commitments based on internet testimonials or clinic sales brochures. Compile your child’s complete medical history, genetic tests, and neurological evaluations, and schedule a dedicated consultation with a board-certified pediatric neurologist. Require an independent, evidence-informed suitability assessment before exposing your child to any experimental biological product.