Our Services
Others
- DFPP
- Shockwave
- IV Drip

From a clinical perspective, the medical team considers this patient’s condition to be a complex multilevel spinal disorder rather than a single-disc problem or isolated source of back pain. His medical history suggests a combination of previous spinal fusion, degenerative disc and facet-joint disease, neural foraminal narrowing, nerve-root compression, radiating pain, bilateral foot drop, and prolonged dependence on opioid pain medication.
These findings should be assessed not only from an anatomical perspective, but also according to their impact on the patient’s neurological function, mobility, sleep, work, independence, and quality of life. Because the patient wishes to preserve mobility and potentially return to activities such as surfing, skiing, and snowboarding, the medical team recommends that treatment planning focus on both structural stability and long-term functional recovery.
Recommended Review of Imaging and Neurological Status The available imaging indicates multilevel degenerative disease involving the lumbar spine. The preoperative lumbar MRI demonstrated facet arthropathy, neural foraminal narrowing, an L3–L4 disc bulge, and a central L4–L5 disc protrusion with annular fissuring. At L4–L5, moderate bilateral neural foraminal narrowing was present with involvement of the L4 nerve roots. Postoperative changes were also noted at L5–S1, together with mild vertebral displacement at several levels.
Thoracic imaging demonstrated the previous T9–T11 fusion and mild multilevel degeneration, without significant thoracic cord compression at that time.
However, imaging findings should always be correlated with the patient’s neurological and functional condition. MRI and CT can identify structural pathology, but they do not fully demonstrate the severity of pain, walking limitations, sleep disturbance, weakness, or loss of independence.
For this reason, the medical team recommends ongoing assessment of:
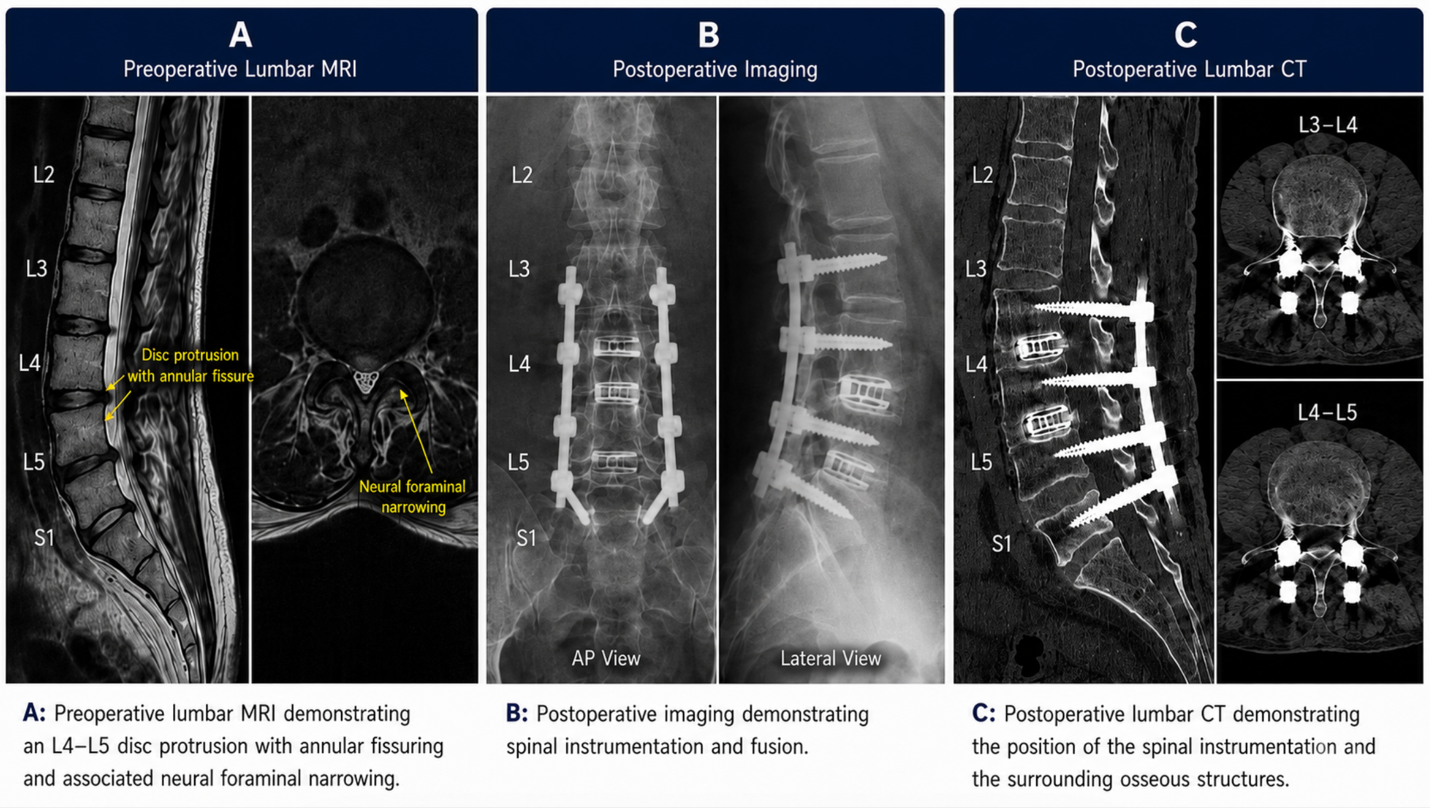
Figure 1: Composite lumbar imaging demonstrating the patient’s preoperative and postoperative findings.A: Preoperative lumbar MRI showing an L4–L5 disc protrusion with annular fissuring and associated neural foraminal narrowing.B: Postoperative imaging demonstrating spinal instrumentation and fusion.C: Postoperative lumbar CT showing the position of the spinal implants in relation to the surrounding bony structures.
When Surgical Management Should Take Priority In this case, the medical team recommends distinguishing clearly between biological symptoms such as inflammation and pain, and structural neurological problems caused by mechanical nerve compression or spinal instability.
When a patient develops progressive neurological deficits such as worsening radiculopathy, persistent nerve-root compression, spinal deformity, significant stenosis, or bilateral foot drop, supportive regenerative treatment alone is unlikely to be sufficient.
The decompression, instrumentation, and fusion performed at L3–L5 appear to have been appropriate for addressing the mechanical component of the condition.
This distinction is essential because cell therapy cannot:
Therefore, progressive neurological impairment should always prompt surgical or neurosurgical review before considering regenerative supportive care.
Recommended Postoperative Assessment
Before considering any postoperative regenerative treatment, the medical team recommends confirming that the patient has recovered sufficiently from surgery. Postoperative imaging demonstrated instrumentation and fusion at L3–L5 together with the previous L5–S1 fusion. Although no clear central spinal-canal stenosis was identified, assessment of some neural foramina was limited by metallic artefact.
The presence of a postoperative subcutaneous haematoma should also be considered before proceeding with elective injections or regenerative therapy.
The medical team therefore recommends reviewing:
Regenerative treatment should only be considered when the postoperative condition is clinically stable.
Recommended Role of Cell Therapy
For this patient, the medical team positions cell therapy as an adjunctive biological support option rather than a substitute for surgery. Cell therapies are being investigated for their ability to release cytokines, growth factors, extracellular vesicles, and other signalling molecules that may influence inflammatory activity and the local tissue environment.
The proposed goals of cell therapy would be to:
It should be explained clearly that cell therapy cannot guarantee restoration of chronic nerve damage or bilateral foot drop and should not be described as rebuilding the entire spinal disc or reversing established spinal fusion.
Recommended Treatment Strategy
The medical team recommends a staged treatment approach rather than relying on a single modality.
Stage 1: Structural and Neurological Assessment Before treatment, review:
Stage 2: Targeted Supportive Regenerative Treatment If the patient is medically stable and there is no indication for further urgent structural intervention, a supportive regenerative programme may be considered. Potential components may include:
The exact route, dose, and location should be determined according to imaging findings, examination, previous surgery, and procedural safety.
Stage 3: Rehabilitation The regenerative programme should be combined with structured rehabilitation. The medical team recommends particular attention to:
Patients with bilateral foot drop may also require orthotic assessment, such as ankle-foot orthoses, depending on the degree of weakness.
Recommended Outcome Monitoring The effectiveness of supportive treatment should not be judged by subjective impressions alone.
The medical team recommends establishing baseline measurements before treatment and reassessing at 1, 3, 6, and 12 months.
Important outcome measures include:
This is particularly important because there is currently insufficient structured follow-up information to determine how much improvement can specifically be attributed to cell therapy.
Recommendation Regarding Pain Medication Given the history of long-term opioid use, the medical team also recommends coordinated pain-management review.
Any reduction in opioid medication should be supervised rather than performed abruptly. The goal should be to improve function and reduce reliance on medication when clinically appropriate, while maintaining adequate pain control.
A multidisciplinary pain-management approach may include:
Return to Sport and Higher-Level Activity The patient’s goal of returning to surfing, skiing, and snowboarding should be approached progressively.
The medical team does not recommend return to high-impact or high-risk activity until the patient demonstrates:
Return to sport should therefore be based on functional milestones rather than time alone.
Overall Clinical Recommendation The medical team’s overall recommendation is to manage this patient through a combined structural, neurological, biological, and rehabilitation strategy.
The main priorities should be:
In this setting, cell therapy may have a role in supporting the biological environment surrounding affected tissues and complementing rehabilitation, but it should not be expected to replace decompression surgery, correct spinal hardware, reverse established structural degeneration, or guarantee recovery of chronically damaged nerves.
The most appropriate approach is therefore: Structural assessment → neurological review → surgical management when required → supportive regenerative treatment when appropriate → structured rehabilitation → long-term outcome monitoring.
This provides the patient with a realistic, medically responsible treatment pathway while keeping the goals focused on mobility, neurological preservation, pain control, functional recovery, and quality of life.