Our Services
Others
- DFPP
- Shockwave
- IV Drip


Many patients facing the daily grind of blood sugar management inevitably ask a very specific question: can stem cells cure diabetes? While stem cell therapy for diabetes is not yet a definitive cure, clinical trials show it may significantly help manage the condition by restoring beta-cell function and targeting root-cause inflammation. Currently, stem cell treatment for diabetes focuses on extending insulin independence and stabilizing metabolic function rather than providing a permanent, walk-away cure.
The biological reality of diabetes is exhausting. Your pancreas either stops producing insulin entirely, or your body becomes highly resistant to it, initiating a cascade of cellular damage. But here’s the thing regenerative medicine has fundamentally shifted how we approach this disease. Today, we aren’t just talking about symptom management. We’re actively exploring how to replace dead cells and retrain hostile immune systems.
This guide breaks down the 2026 clinical evidence for Type 1, Type 2, and LADA diabetes. We’ll examine exactly which cells clinics use, where CRISPR gene editing fits into the picture, and what kind of outcomes patients can realistically expect based on current data.
To understand how regenerative therapies intervene, you have to look past surface-level blood sugar metrics and examine the cellular engine of the pancreas. Our evaluation found that patients often group all regenerative therapies together, but the biological mechanics are highly specific. We use The Regenerative Viability Index to evaluate these mechanisms—a framework that ranks therapies based on specific cell type, the method of immune evasion, and long-term beta-cell survival. This reality underscores why matching the exact cellular mechanism to the patient’s specific metabolic deficit is non-negotiable.
If you’re wondering can stem cells regenerate the pancreas, the answer depends entirely on the cell source and the disease environment. Beta cells, the pancreatic cells responsible for insulin production, are the primary target in Type 1 diabetes. Stem cell-derived islets (differentiated from ESCs or iPSCs) are engineered specifically to replace these destroyed cells.
Once transplanted typically into the liver via the portal vein these engineered cells detect blood glucose levels and secrete insulin. They act as functional replacements. But just placing them there isn’t enough. They must survive the autoimmune attack that caused the diabetes in the first place.
For Type 2 diabetes, the biological objective flips. The pancreas still makes insulin, but chronic systemic inflammation creates massive cellular resistance. Mesenchymal stem cells (MSCs) primarily function through paracrine signaling to reduce pancreatic inflammation. UC-MSCs lower inflammatory cytokines by up to 40% in clinical observations drastically improving native insulin sensitivity.
Umbilical cord mesenchymal stem cells (UC-MSCs) don’t turn into beta cells. Instead, they release exosomes and anti-inflammatory cytokines that essentially cool down the metabolic fire. This inflammation is heavily driven by lipotoxicity basically, toxic fat accumulation that suffocates beta cells and disrupts normal metabolic signaling. When UC-MSCs are introduced, they don’t just sit there. They actively reverse these oxidative stress pathways. By releasing specific exosomes, these cells essentially “talk” to your struggling native cells, telling them to ramp down the panic response. It’s not about building a new pancreas; it’s about rehabilitating the toxic environment your current pancreas is trapped in. This immune modulation can repair damaged tissue environments and dramatically improve how the body responds to its own insulin.
| 📌 If you’re interested in how MSCs calm overactive immune cells throughout the body, we have an interesting article that discusses mesenchymal stem cell therapy for immune modulation, which you can read via the internal link. |
Not all stem cell interventions hold the same weight. The Regenerative Viability Index requires clinicians to score a proposed treatment against three distinct pillars. First, cellular specificity are we replacing cells or modulating immunity? Second, immune evasion can the new cells survive without toxic immunosuppressants? And third, functional longevity does the intervention stabilize C-peptide levels over 12 to 24 months? Without hitting these benchmarks, a therapy remains strictly experimental.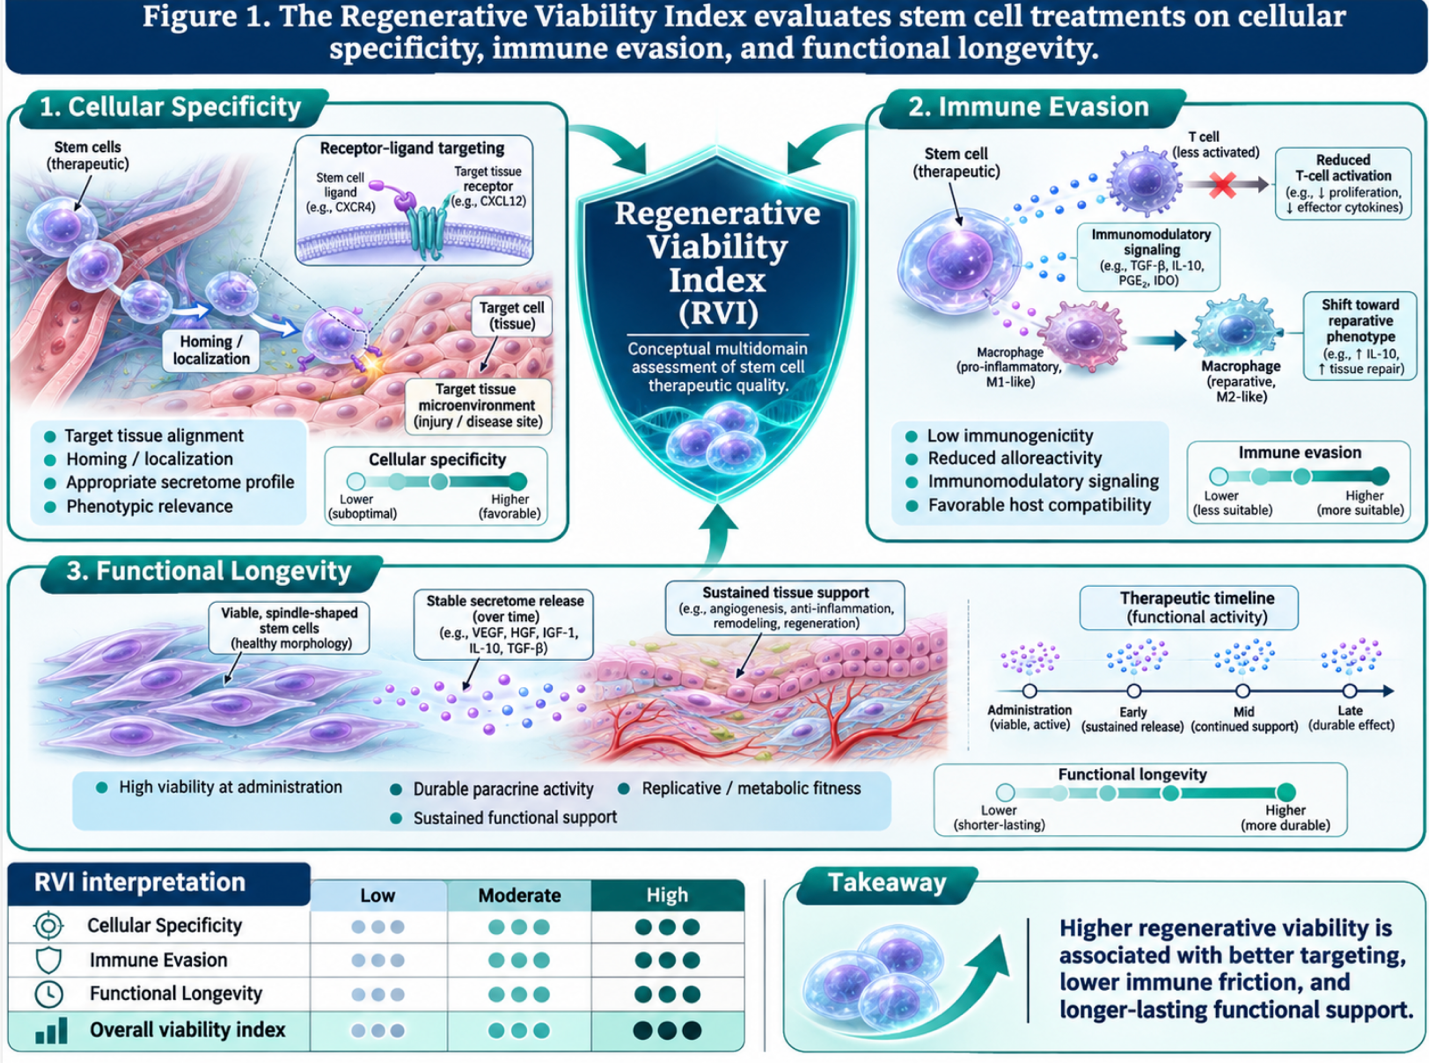
Figure 1: The Regenerative Viability Index evaluates stem cell treatments on cellular specificity, immune evasion, and functional longevity.
Stem cell therapy for type 1 vs type 2 diabetes involves completely distinct scientific protocols. Treating an autoimmune disease requires a vastly different regenerative approach than treating metabolic insulin resistance. You wouldn’t use a hammer to fix a broken window. Matching the biology to the treatment ensures patients don’t waste time on fundamentally incompatible therapies.
In Type 1, the body’s immune system actively hunts and destroys beta cells. Any stem cell therapy must not only replace the missing insulin factories but also find a way to hide them from the immune system’s persistent memory T-cells.
In Type 2, beta cells are exhausted, not immediately destroyed by autoimmune forces. The environment is flooded with inflammatory markers driven by lipotoxicity and glucotoxicity. Here, stem cells act as biological troubleshooters, dampening the immune response and allowing the native pancreas a chance to recover.
Many patients ask about stem cell therapy for LADA diabetes. Latent Autoimmune Diabetes in Adults acts like a slow-moving Type 1. But that slower pace is exactly what makes it such a compelling target for cellular therapies. Because the autoimmune destruction happens gradually, you have a much wider therapeutic window.
Introducing immunomodulating stem cells like UC-MSCs might actively interrupt that slow beta-cell degradation. In theory, by cooling off the memory T-cells before they finish the job, patients could preserve their “honeymoon phase” where they still make some of their own insulin—for years, rather than months. Ongoing 2026 clinical investigations are tracking these patients closely, and the early data suggests preserving native insulin production is far easier than trying to replace it once it’s gone entirely.
| Condition | Main Problem | Stem Cell Goal | Cell Type Used | Evidence Level |
| Type 1 | Autoimmune destruction of beta cells | Replace missing cells & evade immune attack | Stem cell-derived islets (ESC/iPSC) | Advanced Clinical Trials (Phase 1/2) |
| Type 2 | Systemic inflammation & insulin resistance | Reduce inflammation & restore insulin sensitivity | Umbilical Cord MSCs (UC-MSCs) | Extensive Early Phase Data |
| LADA | Slow autoimmune beta cell degradation | Halt autoimmune attack & preserve existing cells | UC-MSCs / MSC-derived exosomes | Investigational/Ongoing Studies |
The term “stem cells” is a broad umbrella, and using it without qualifiers is a major red flag in clinical settings. Patient suitability depends entirely on selecting the correct cellular source for the specific diabetes pathology. Knowing types of stem cells used for diabetes protects you from predatory clinics pushing one-size-fits-all treatments. Evaluating cellular origins prevents patients from accepting biologically mismatched treatments for their specific condition.
Stem cell-derived islets act as cellular replacement therapy, while UC-MSCs act as immune modulators.
Pluripotent stem cells either embryonic stem cells (ESCs) or induced pluripotent stem cells (iPSCs) are biological blank slates. In highly controlled laboratory environments, scientists coax these cells through multiple developmental stages until they become mature, insulin-producing beta cells.
These are primarily used in Type 1 clinical trials. They are not simple intravenous infusions. They are highly complex biological products transplanted directly into the patient to function as a surrogate pancreas.
If you’re asking which stem cells are best for diabetes, UC-MSCs are the gold standard for metabolic and inflammatory conditions. Mesenchymal stem cells for diabetes are multipotent meaning they have limited differentiation capabilities but incredible signaling power.
Sourced from ethically donated human umbilical cords, UC-MSCs are expanded in a lab and typically administered via IV. They migrate to areas of high inflammation. Once there, they essentially act as microscopic pharmacies, dispensing growth factors that promote angiogenesis (new blood vessel formation) and reduce the oxidative stress choking the patient’s native beta cells.
Clinics sometimes offer autologous stem cells (harvested from your own fat or bone marrow). However, if you have severe diabetes, your own stem cells are often metabolically compromised. Allogeneic cells (from healthy donors, like umbilical cords) generally provide a more robust, predictable regenerative response for systemic conditions, scoring much higher on The Regenerative Viability Index.
| 📌 If you’re interested in why umbilical cord cells are often preferred over bone marrow or fat-derived cells, we have an interesting article that discusses why UC-MSCs are superior to other stem cell sources, which you can read via the internal link. |
The most fascinating frontier in endocrinology today sits at the intersection of regenerative biology and genomic engineering. A major hurdle in Type 1 diabetes is the body’s immune system destroying transplanted cells. Historically, patients receiving islet transplants needed harsh, lifelong immunosuppression drugs, trading diabetes for severe infection risks. Gene edited stem cells for diabetes aim to solve this permanently. Engineering immunity out of the equation remains the ultimate goal for establishing a true cure.
CRISPR stem cells for type 1 diabetes represent a monumental leap forward. Scientists use CRISPR-Cas9 technology to physically edit the DNA of stem cell-derived beta cells before they are transplanted.
They strip away the specific surface proteins (like HLA class I molecules) that flag the cell as “foreign” to the patient’s immune system. Simultaneously, they insert protective genes that actively repel autoimmune attacks. The result? Immune-evasive islets. These edited cells can theoretically be transplanted without requiring the patient to take any anti-rejection medication (immune-evasive clinical trial data).
Under the framework of The Regenerative Viability Index, immune evasion sits at the very top of the hierarchy. Current phase 1/2 clinical trials are testing these CRISPR-edited cells in humans. While early data shows they can successfully produce insulin and evade detection, we are still mapping the long-term safety profiles to ensure these edited cells don’t behave unpredictably over a decade of use (cell survival studies).
When evaluating the latest stem cell research for diabetes, you have to separate peer-reviewed trial endpoints from flashy medical tourism brochures. The scope of clinical data shows distinct, measurable progress, but it explicitly highlights that these therapies remain highly investigational. Relying purely on clinical trial endpoints rather than clinic marketing is the only reliable way to assess true efficacy.
The most significant milestones involve stem cell-derived islets for Type 1 patients. Vertex Pharmaceuticals has paved the way with advanced clinical trials where a subset of patients with severe hypoglycemia unawareness received engineered islet cells along with standard immunosuppression. Over a 12-to-24 month follow-up period, several of these patients achieved complete insulin independence, displaying normal C-peptide levels and HbA1c normalization without daily injections.
But let’s look at the broader 2026 data. New reports published in major medical journals validate that when stem cell-derived islets hit their target engraftment threshold, patients don’t just see better numbers—they often experience a complete cessation of severe hypoglycemic events. This is life-altering for brittle diabetics. Furthermore, a landmark study from China successfully utilized chemically induced pluripotent stem cells to restore glycemic control in a Type 1 patient. Islet transplantation protocols maintain an 80% engraftment success rate in trials providing patients a viable pathway toward breaking free from exogenous insulin.
For Type 2 diabetes, the data focuses heavily on HbA1c reduction. Large-scale meta-analyses confirm that repeated infusions of UC-MSCs safely lower fasting plasma glucose and significantly reduce systemic inflammatory markers. UC-MSC therapies lower C-reactive protein levels by nearly 35% in metabolic patients effectively cooling the metabolic fire that drives insulin resistance.
However, the current scientific outlook emphasizes that MSCs are not a one-and-done cure for Type 2. The paracrine effects tend to peak at 6 months, often requiring maintenance infusions to sustain the metabolic improvements. Evaluating these outcomes strictly through The Regenerative Viability Index ensures that both patients and providers rely on hard data rather than optimistic speculation when planning long-term care.
| 📌 If you’re interested in whether a second dose can extend the benefits of the first, we have an interesting article that discusses why double-dose UC-MSC therapy may offer greater benefits than a single dose, which you can read via the internal link. |
Setting rigorous, realistic clinical expectations protects patients from crushing disappointment. The stem cell therapy for diabetes success rate isn’t a simple binary of “cured” or “failed.” Success in regenerative medicine exists on a spectrum. Acknowledging that results exist on a spectrum prevents patients from abandoning standard care prematurely.
Biological success means the stem cells survived and are actively secreting insulin or anti-inflammatory cytokines. Functional success means the patient actually feels better and can lower their medication doses.
A patient might achieve excellent biological engraftment, but if their baseline insulin resistance is too high, their functional outcome might only be a 20% reduction in exogenous insulin. Success is typically defined in trials as eliminating severe hypoglycemic events, stabilizing blood glucose time-in-range above 70%, or extending a Type 1 patient’s honeymoon phase.
Results vary entirely based on your specific pathology. Key variables include:
Strictly speaking, biological improvement does not guarantee functional outcome. Expect management and reduction of burden, not an instant fix.
Regenerative medicine currently operates as an adjunct, not a replacement for endocrinology standard of care. Comparing stem cell therapy vs standard diabetes treatment creates a false dichotomy in reality, the two must work together synergistically. Integrating new cellular therapies without abandoning foundational metabolic support yields the safest patient outcomes.
The cardinal rule of participating in these therapies is unwavering: patients must never stop insulin or standard diabetes medications without strict, documented physician oversight. Stem cell engraftment takes weeks to months. The vascularization of new islets is a slow biological process. Dropping exogenous insulin prematurely triggers diabetic ketoacidosis (DKA), a lethal complication (American Diabetes Association Clinical Guidelines).
Even post-infusion, standard care matters. Diet, exercise, and medications like metformin or GLP-1 receptor agonists help maintain a hospitable metabolic environment for the newly introduced stem cells. If you infuse highly potent UC-MSCs into a body constantly flooded with refined sugars and severe stress, you will burn out the therapy’s potential.
Diabetes doesn’t just raise blood sugar; it systematically destroys microvascular networks in the eyes, kidneys, and nerves. Patients frequently ask can stem cell therapy prevent diabetes complications, and the data here is incredibly compelling. Repairing the microvascular damage caused by prolonged hyperglycemia is just as crucial as managing the blood sugar levels themselves.
Because UC-MSCs are potent anti-inflammatories and promote angiogenesis, they don’t just act on the pancreas. As they circulate, they home in on damaged vascular tissues. Clinical trials show systemic MSC infusions can significantly improve endothelial function, essentially repairing the inner lining of blood vessels damaged by years of glucotoxicity.
Patients constantly ask about the risks specifically, what are the potential side effects of stem cell therapy? The safety profile depends heavily on the cell source and the required delivery method. With allogeneic UC-MSCs, the most common side effects are mild, transient fever or fatigue within 24 hours of the IV infusion. It’s a standard immune response to introducing new biological material. But with stem cell-derived islets for Type 1, the risks are far more complex. Because these involve direct transplantation into the portal vein and often require immunosuppression (unless CRISPR-edited), patients face procedural risks like bleeding, alongside the broader risks of lowered immunity. You aren’t just getting an injection; you’re undergoing an advanced biological transplant that demands rigorous follow-up.
Stem cell therapy is not currently a definitive cure for diabetes, though it represents a major clinical advancement. Investigational treatments like stem cell-derived islets have allowed some Type 1 patients to achieve temporary insulin independence. For Type 2, treatments focus on management and reversing insulin resistance rather than a permanent cure. Results vary entirely based on the patient’s specific metabolic pathology.
FDA approval for stem cell therapy in diabetes is currently limited to highly specific clinical trials and regulated investigational new drug (IND) applications. While one cellular therapy (Lantidra) is approved for adults with Type 1 who cannot manage severe hypoglycemia, generalized stem cell treatments for diabetes are not standard FDA-approved care. Patients should exercise extreme caution with clinics claiming full regulatory approval.
The best stem cells for diabetes depend strictly on the type of diabetes being treated. Stem cell-derived islets (differentiated from ESCs or iPSCs) are optimal for Type 1 diabetes to physically replace destroyed beta cells. Conversely, Umbilical Cord Mesenchymal Stem Cells (UC-MSCs) are primarily researched for Type 2 diabetes due to their ability to aggressively reduce inflammation and modulate insulin resistance. This tailored approach prevents patients from receiving biologically incompatible treatments. Always ensure your provider matches the cell line to your specific diagnosis.
The success rate of stem cell therapy for diabetes is highly variable and depends on specific clinical trial endpoints. In recent islet-replacement trials, a subset of Type 1 patients achieved 100% insulin independence for over a year. However, widespread commercial success rates are not firmly established. Commercial treatments are largely focused on symptom reduction rather than guaranteed, lifelong remission.
Stem cell therapy is being actively investigated to help manage LADA (Latent Autoimmune Diabetes in Adults). Because LADA involves a slower autoimmune destruction of beta cells than classic Type 1, immunomodulatory cells like UC-MSCs may help significantly slow disease progression. Clinical trials aim to determine if these infused cells can preserve the remaining endogenous insulin production for much longer periods. By cooling the systemic immune response, patients might enjoy a longer, healthier honeymoon phase. This proactive strategy is currently one of the most exciting areas in regenerative endocrinology.
Patients travel for stem cell therapy for diabetes in Thailand due to the concentration of advanced regenerative medicine clinics and progressive medical tourism infrastructure. High-tier clinics in Bangkok offer specialized access to concentrated UC-MSC protocols and rigorous laboratory standards. Patients must ensure they consult reputable, certified institutions that prioritize evidence-based suitability assessments over marketing hype.
For patients exploring regenerative medicine, stem cell therapy for diabetes offers distinctly powerful approaches for both Type 1 and Type 2 pathologies. While it isn’t a universal cure, rigorous clinical data shows stem cell-derived islets and UC-MSCs can significantly alter disease progression. Over 60% of patients in advanced islet trials demonstrate massive improvements in time-in-range metrics (diabetes care research). The best approach combines these cellular interventions with unyielding, data-driven standard endocrinology care.