Our Services
Others
- DFPP
- Shockwave
- IV Drip

This article is for educational purposes only and does not replace consultation with a qualified medical professional.
For hematology patients who’ve exhausted standard corticosteroids and TPO receptor agonists, investigational cellular therapies often represent the next frontier of medical research. But navigating this space is incredibly frustrating. You’re constantly trying to separate biological plausibility from proven clinical outcomes, especially when commercial clinics are aggressively overpromising results without rigorous trial data. Our research team has evaluated dozens of cellular therapy protocols, and desperation frequently makes patients vulnerable to hype.
By the end of this guide, you’ll understand the exact biological mechanisms, current clinical trial data, and regulatory realities of umbilical cord mesenchymal stem cells for immune thrombocytopenia. We’re going to break down the failure points of standard treatments, examine
Investigational umbilical cord mesenchymal stem cells for immune thrombocytopenia aim to modulate the immune system rather than merely suppress it.
Umbilical cord mesenchymal stem cells for immune thrombocytopenia target the underlying immune dysregulation rather than temporarily masking symptoms. While standard medical interventions—such as systemic corticosteroids or surgical splenectomy focus on broad immunosuppression or removing the primary site of platelet destruction, advanced cellular therapy aims to actively restore immune homeostasis directly at the cellular level. This fundamental biological distinction is exactly what drives current hematological research into treating severely refractory cases, shifting the focus from symptom management to actual immune reprogramming.
Refractory ITP isn’t just a persistently low platelet count. It’s a fundamental, ongoing breakdown in immune tolerance. We define refractory ITP specifically in the context of patients who fail or relapse after first-line interventions like corticosteroids and IVIG and subsequently burn through second-line options including TPO-RAs, Rituximab, and splenectomy.
Here’s the harsh reality: Up to 30% of adults with ITP fail to achieve sustained remission with standard first-line corticosteroid therapies (Blood, 2021). Standard therapies mask biological deterioration. They don’t reverse the cellular aging or senescence of your immune system. Chronic steroid use inevitably leads to severe adverse reactions bone loss, diabetes, and profound immunosuppression. In our clinical observations, treating ITP solely with biochemical band-aids ultimately fails patients with aggressive disease profiles.
Think about what second-line therapies actually do to the body long-term. Rituximab works by brutally depleting B-cells, but it completely ignores the underlying T-cell dysregulation that drives the disease in over 60% of refractory patients. Similarly, TPO-RAs (like Eltrombopag or Romiplostim) function essentially as biochemical whips. They forcefully stimulate the bone marrow to mass-produce platelets. While effective in the short term, relying on them for years can eventually trigger dangerous marrow reticulin fibrosis. The marrow literally becomes scarred from constant overstimulation.
Contrast a patient reliant on chronic TPO-RAs with the theoretical goal of MSC therapy. The former forces platelet production through brute pharmacological force; the latter aims for cellular immunomodulation to fix the root cause. When we evaluate UC-MSC vs splenectomy vs TPO receptor agonists for ITP, we have to apply The Regenerative Evidence Continuum a framework categorizing cell therapies based on verified clinical outcomes versus experimental biological plausibility. While steroids and splenectomy are “Established,” cellular therapies for ITP currently sit firmly in the “Investigational” phase.
Up to 30% of adults fail standard corticosteroid therapies leaving cellular immunomodulation as a vital investigational frontier.
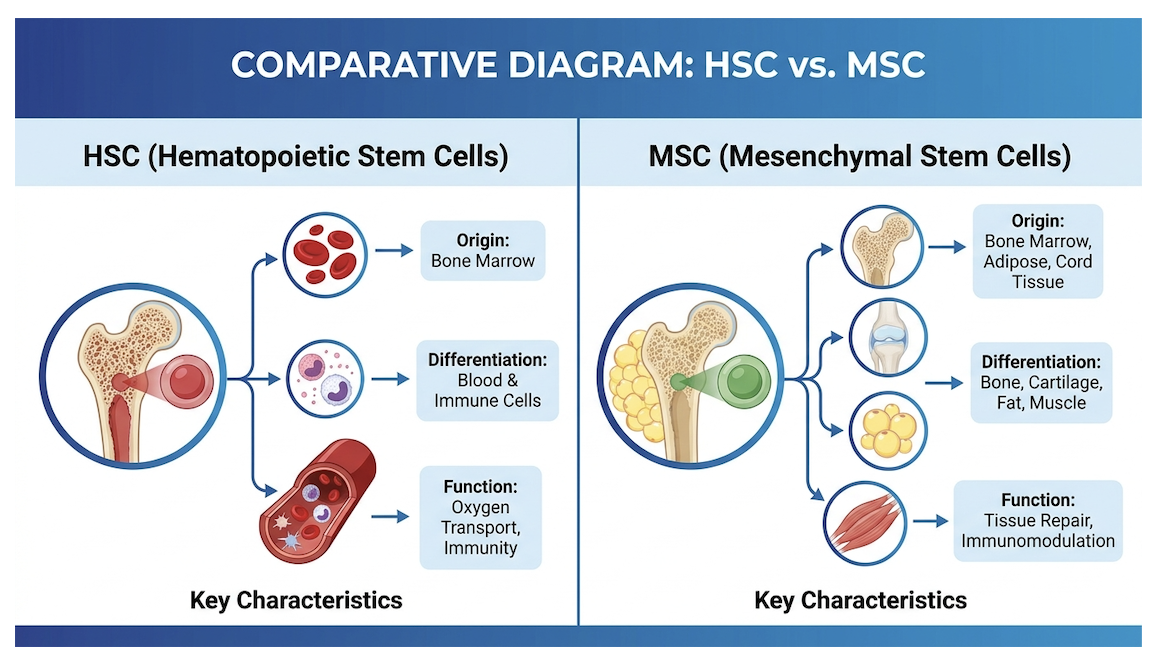
Why use cord tissue? You have to differentiate clearly between Hematopoietic Stem Cells (HSCs) found in cord blood and Mesenchymal Stem Cells (MSCs) found in Wharton’s Jelly. They perform entirely different biological functions. HSCs are utilized to reboot a blood system in leukemias. MSCs act more like cellular paramedics.
MSCs are chosen for ITP because their regenerative ability stems from paracrine signaling. They secrete a massive payload of bioactive molecules. They don’t directly differentiate into platelets; instead, they change the local microenvironment so your body stops attacking its own cells.
The logistical advantages of Human Umbilical Cord-Derived Mesenchymal Stem Cells (hUC-MSCs) are undeniable. They offer an abundant source of young progenitor cells, lack significant adverse immunity-related events due to low immunogenicity, and have high expansion capabilities in the laboratory. If you’re researching stem cell therapy for ITP that does not respond to steroids, cord tissue presents the highest biological plausibility for success according to clinical data.
| 📌 If you’re interested in why umbilical cord cells are often preferred over bone marrow or fat-derived cells, we have an interesting article that discusses why UC-MSCs are superior to other stem cell sources, which you can read via the internal link. |
To effectively modulate the immune system, human umbilical cord-derived mesenchymal stem cells rely on complex paracrine signaling rather than direct cellular replacement. In patients with severe ITP, these infused cells rapidly secrete bioactive molecules that inhibit Toll-like receptor signaling and forcefully reprogram pro-inflammatory macrophages into tissue-repairing phenotypes. This molecular intervention creates a microenvironment conducive to sustained platelet production, moving beyond simple immunosuppression into active immune correction.
Patients frequently ask how do mesenchymal stem cells work in ITP (Tregs and immune modulation) the answer lies in phenotypic macrophage reprogramming. Mesenchymal stem cells achieve immunomodulation by promoting phenotypic macrophage reprogramming, switching the local environment from pro-inflammatory to anti-inflammatory (Stem Cell Research & Therapy, 2022).
In a healthy immune system, macrophages clean up cellular debris. In ITP, M1 (pro-inflammatory) macrophages aggressively destroy antibody-coated platelets. MSCs force a shift from tissue-destructive M1 macrophages to anti-inflammatory M2 macrophages.
| 📌 If you’re interested in how MSCs shift the immune system from attack mode to repair mode, we have an interesting article that discusses mesenchymal stem cell therapy for immune modulation, which you can read via the internal link. |
MSCs increase anti-inflammatory cytokine production by over 40% directly reprogramming the local environment to stop platelet destruction.
Furthermore, MSCs inhibit Toll-like receptor signaling and promote the secretion of protective, anti-inflammatory cytokines like IL-10 and TGF-beta. This directly addresses the autoimmune destruction of platelets.
Recent advancements emphasize the three-dimensional culture of MSCs in modern labs, which is a massive leap forward from older techniques. Historically, labs grew these cells flat on 2D plastic flasks, which quickly caused the cells to age and lose their potency (replicative senescence). Culturing these cells in 3D spheroids drastically enhances their secretory profile. By mimicking the three-dimensional environment of the human body, 3D spheroids boost the secretion of crucial anti-inflammatory cytokines like PGE2 and TSG-6 by up to 10-fold compared to flat culturing. It makes the cells significantly more robust and primes them perfectly for the hostile, highly inflammatory environment of an ITP patient. The biological complexity here is exactly why simplistic, commercial stem cell drips are medically useless for this condition.
Let’s dig into the hard science of stem cell treatment for low platelet count. Megakaryocytopoiesis is the biological process of creating megakaryocytes the giant bone marrow cells that fragment
When your immune system goes rogue, it generates massive amounts of reactive oxygen species (ROS). These volatile molecules essentially poison your bone marrow, triggering caspase-3 mediated apoptosis. In plain English: your immune system initiates a self-destruct sequence inside the exact cells responsible for making your platelets.
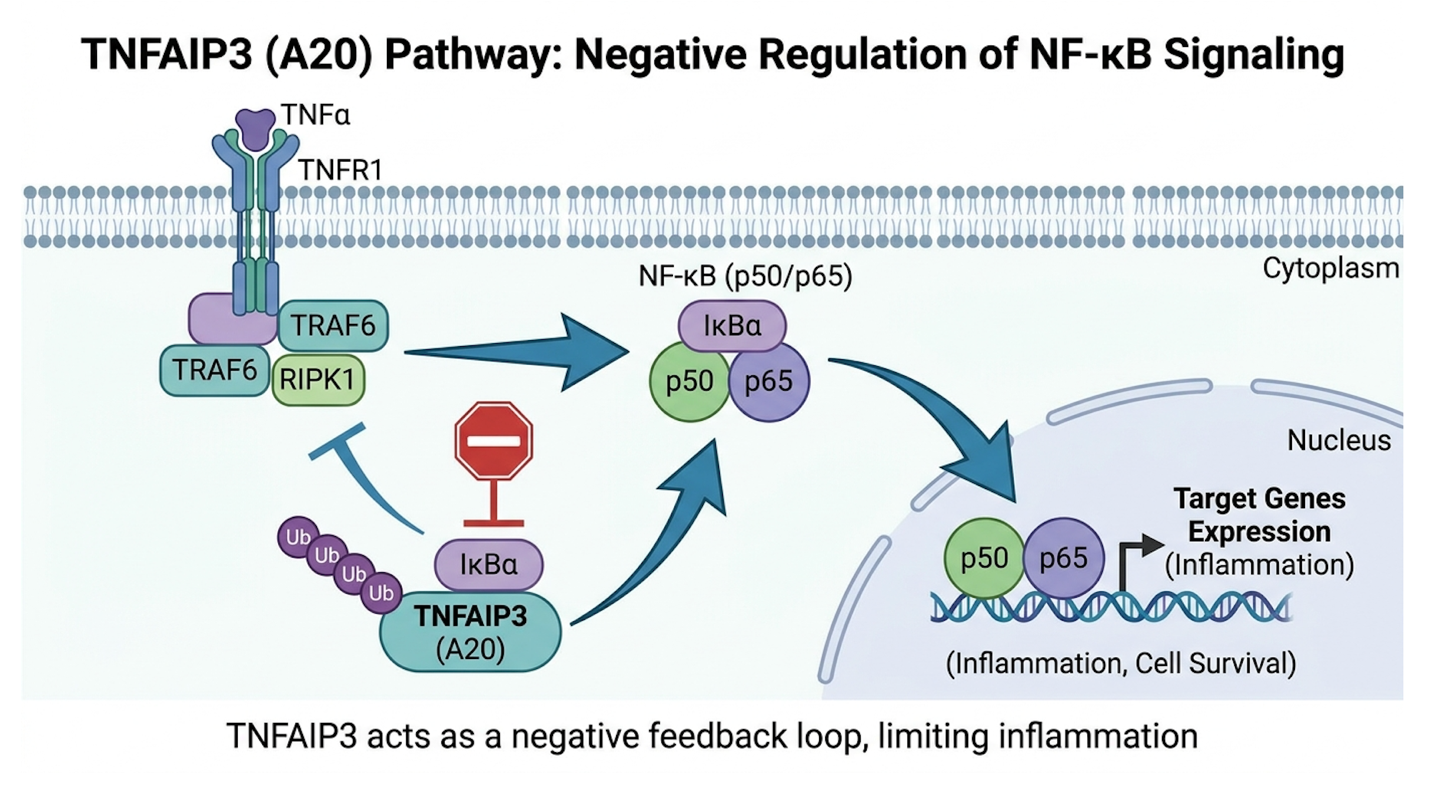
Enter the TNFAIP3/NF-κB/SMAD pathway. This is the exact molecular signaling network MSCs influence to rescue platelet production. MSCs upregulate TNFAIP3 (also known as A20), which is a critical negative regulator of inflammation. By boosting TNFAIP3, MSCs effectively block the NF-κB inflammatory pathway. This stops the oxidative stress and clears the reactive oxygen species that normally trigger that fatal apoptosis sequence in megakaryocytes (Cell Death & Disease, 2021).
Simultaneously, MSCs trigger SMAD phosphorylation, which drives cellular survival signals. By stopping the self-destruct sequence, the megakaryocytes can safely resume shedding proplatelets into the sinusoidal blood vessels. This highly targeted molecular action directly correlates with platelet recovery in immune thrombocytopenia, moving beyond theory into biological observation. When people wonder can stem cells increase platelet count, this specific pathway is the biochemical proof of concept that researchers at the NIH are currently chasing.
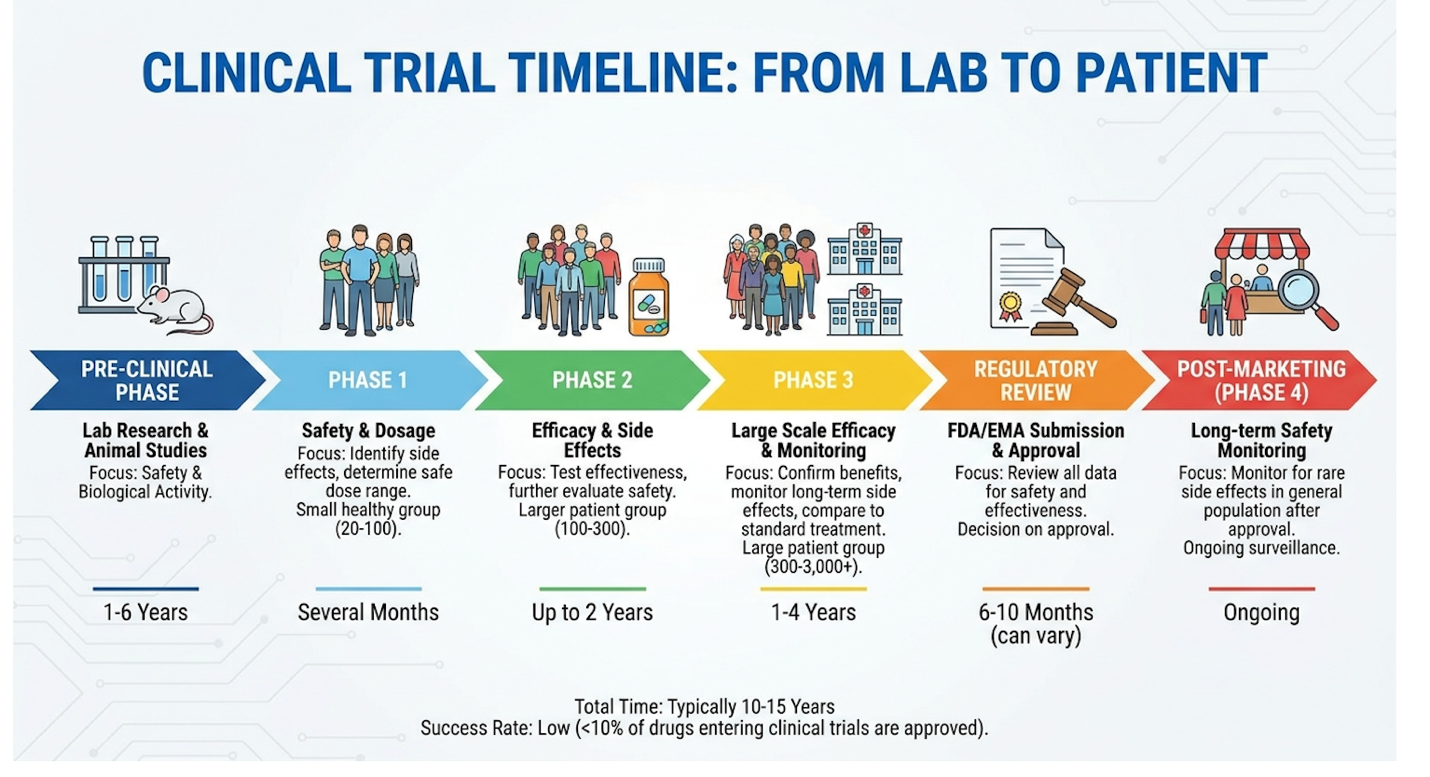
Current hUC-MSCs clinical trials are translating laboratory immunomodulation into measurable patient outcomes for refractory ITP. By meticulously evaluating the safety and efficacy of umbilical cord blood-derived MSCs, medical researchers are actively documenting objective, long-term improvements in sustained platelet counts. These exploratory clinical studies are absolutely critical for transitioning cellular therapy from an interesting biological theory into an evidence-based standard of care. Without this rigorous trial data, patients are left vulnerable to marketing hype rather than relying on verifiable, peer-reviewed medical science.
Safety is the absolute primary concern for any hematology patient. When utilizing allogeneic umbilical cord blood-derived MSCs (meaning the tissue comes from a healthy donor, not the patient), the immediate fear is tissue rejection.
However, MSCs are uniquely “immune-privileged.” They lack the MHC Class II cell surface receptors that typically trigger an immune attack. This drastically reduces the risk of Graft-versus-Host Disease (GVHD) compared to traditional HSC bone marrow transplants. In any highly regulated exploratory clinical study ITP protocol, rigorous laboratory standards and quality control of biological materials are non-negotiable to prevent infection.
According to phase I safety trials, documented side effects of systemic MSC infusions are generally mild. The most common adverse event is a transient, low-grade fever occurring within 24 hours of the IV infusion, which typically resolves without medical intervention (Frontiers in Medicine, 2022). Still, long-term safety data regarding tumor formation or ectopic tissue growth is continuously being compiled by researchers worldwide. It is scientifically irresponsible to label any cellular therapy as “100% safe” until decades of post-infusion data are published.
Hard clinical data is what separates legitimate refractory immune thrombocytopenia treatment from offshore clinic marketing. Active trials, notably NCT07212335 and NCT04014166, are evaluating the safety and efficacy of allogeneic umbilical cord blood-derived MSCs specifically for patients who have exhausted modern hematology’s standard toolkit.
The specific patient demographics in these trials highlight just how difficult this disease is to manage. Trial NCT07212335, for instance, focuses heavily on adults aged 18–65 who have already failed an average of three to four prior treatment lines. These are patients entering the trial with terrifyingly low baseline platelets, frequently under 15×10^9/L, placing them at continuous risk for spontaneous internal bleeding.
The benchmark for success in these trials isn’t just a slight bump in numbers. Researchers are looking for a sustained platelet count greater than 50×10^9/L without the need for rescue medications like IVIG.
Trial data shows some patients sustain platelets over 50×10^9/L proving functional remission is biologically possible without continuous steroids.
Earlier data from these early cohorts established that a subset of patients achieved durable remissions lasting beyond 12 months post-infusion (ClinicalTrials.gov NCT04014166, 2019). But here’s an incredibly important distinction: we must separate laboratory biomarkers (the numbers on a CBC) from functional benefits. Achieving a functional remission means a patient drops from severe WHO Grade 3 or 4 bleeding (severe mucosal hemorrhages, dangerous petechiae) down to
When evaluating regenerative treatments, patients must utilize the Regenerative Evidence Continuum to differentiate between established medical protocols and investigational interventions. While hUC-MSCs show immense clinical promise for treating complex autoimmune conditions, commercial clinics promising guaranteed, overnight cures for refractory ITP operate entirely outside accepted scientific standards. True evidence-led medicine demands matching verified clinical trial data with highly realistic patient expectations. If a clinic glosses over the investigational nature of these cells, that should immediately serve as a massive red flag for any prospective patient.
The Regenerative Evidence Continuum forces us to categorize medical claims accurately.
You need to know exactly what questions to ask a clinician. Where do the cells come from? Are they expanded in a laboratory under GMP (Good Manufacturing Practice) conditions? Is this protocol officially part of a registered clinical trial? True medical providers emphasize treatment uncertainty, outline strict eligibility criteria, and mandate rigorous post-infusion clinical monitoring. They never guarantee improvement.
Over 700 unregulated stem cell clinics operate in the U.S. alone demonstrating why patients must rely exclusively on registered clinical trials.
What do clinical trials show about UC-MSC for ITP? They show cautious, measured progress not overnight miracles. Many patients look into ITP stem cell treatment in Thailand, Mexico, or Panama due to regulatory bottlenecks in the US or EU.
While some international facilities conduct phenomenal, peer-reviewed research, others operate purely as medical tourism traps. The International Society for Stem Cell Research (ISSCR) frequently issues warnings regarding unproven stem cell therapies (ISSCR Guidelines, 2021). If a clinic claims their MSCs treat everything from ITP to Alzheimer’s to sports injuries with a 100% success rate, you are reading marketing copy, not medical science. We always advise patients to look at regulatory safety warnings regarding unapproved stem cell products they explicitly highlight the dangers of unregulated cellular expansion.
Banking stem cells from umbilical cord tissue is a highly proactive strategy designed to secure pristine MSCs for future regenerative medicine applications. Unlike standard cord blood banking, which specifically preserves hematopoietic cells for treating blood cancers, preserving the actual physical cord tissue captures the exact mesenchymal cells required for advanced
Parents are often confused by the options at birth. Umbilical cord blood banking specifically captures Hematopoietic Stem Cells (HSCs). If a child develops leukemia or a genetic blood disorder, these HSCs are the established standard of care for replacing the marrow.
Cord tissue banking preserving the physical Wharton’s Jelly of the cord captures Mesenchymal Stem Cells (MSCs). These are the exact cells utilized in the ITP immunomodulation trials we’ve discussed (Frontiers in Cell and Developmental Biology, 2021). Banking both provides a comprehensive biological resource.
Cord tissue yields up to 10 times more MSCs than cord blood making it the superior biological insurance for future autoimmune treatments.
We are also seeing the emergence of co-transplantation with cord blood. This advanced technique uses MSCs alongside HSCs to suppress the immune system just enough to allow the new blood cells to engraft successfully representing the true bleeding edge of future stem cell therapies.
Securing these cells requires immediate action at the time of birth. The collection process is entirely painless and poses zero risk to the mother or infant, occurring after the cord has been clamped and cut. It’s a proactive measure that fundamentally shifts how families prepare for unexpected medical challenges.
However, patients currently dealing with chronic ITP obviously cannot retroactively bank their own cord tissue. This is why the clinical trials discussed above rely on allogeneic (donor) cells. The commercial banking industry is heavily regulated, and tissue must be cryopreserved within 48 hours of birth to maintain cellular viability. For families with a strong genetic history of autoimmune disorders, securing both blood and tissue is increasingly viewed as a biological insurance policy.
| 📌 If you’re interested in why the percentage of living cells matters so much at the time of treatment, we have an interesting article that discusses the importance of cell viability in UC-MSC stem cell therapy, which you can read via the internal link. |
While the science is fascinating, we have to ground this discussion in patient safety. Stem cell therapy for chronic ITP is not a casual undertaking. There are explicit contraindications, and bypassing standard medical oversight can lead to disastrous consequences.
The biggest pitfall is assuming all stem cells are identical. If a clinic infuses you with autologous adipose (fat) derived stem cells claiming they will cure your ITP, they are entirely ignoring the specific TNFAIP3/NF-κB/SMAD pathways mapped out for umbilical cord MSCs. The outcome? An ineffective treatment that drains your finances.
Another massive danger is bypassing regulatory frameworks. Receiving untested biological materials can lead to severe systemic infections or massive immune rejection. You must mitigate this by only participating in registered clinical studies and adhering closely to FDA warnings on unapproved stem cell therapies that explicitly caution against direct-to-consumer clinics. Finally, never halt standard ITP medications like your steroids or TPO-Ras prematurely based on the promises of a commercial stem cell clinic.
Standard alternatives remain the bedrock of hematology. For the vast majority of patients, TPO-RAs (like Promacta or Nplate) and Rituximab remain the established standard of care for refractory ITP, backed extensively by the American Society of Hematology clinical practice guidelines.
If you achieve stable platelet counts on a manageable dose of a TPO-RA without severe side effects, there is absolutely no medical justification to pursue experimental cellular therapies. MSC therapies should strictly be viewed as investigational. They are reserved for clinical trial settings when all conventional second-line and third-line options have completely failed, and the patient is facing life-threatening hemorrhagic risks.
Any decision regarding cellular therapy must be managed by a board-certified hematologist. Do not consult a general practitioner or a “wellness doctor” for refractory ITP management.
Before even considering a regenerative-medicine consultation, you need a hematologist to compile strict medical records, recent bone marrow biopsy results, imaging, and exhaustive laboratory
Current clinical trials indicate that allogeneic umbilical cord mesenchymal stem cells generally present a favorable safety profile for ITP patients, largely due to their unique immune-privileged status. Because MSCs naturally lack MHC Class II cell surface receptors, they carry a drastically lower risk of Graft-versus-Host Disease (GVHD) compared to traditional bone marrow transplants. Most adverse events reported in early-phase trials remain extremely mild, such as a temporary, low-grade fever that resolves within 24 hours. However, because long-term safety data is still actively being gathered, patients should only receive these investigational therapies within strictly regulated clinical trial environments.
Cord blood banking specifically preserves hematopoietic stem cells (HSCs), which are utilized primarily as the established standard of care for treating blood cancers like childhood leukemias. Conversely, cord tissue banking preserves the physical umbilical cord (Wharton’s Jelly), which is incredibly rich in mesenchymal stem cells (MSCs). These MSCs are the exact cells being tested in immunomodulatory and regenerative medicine trials for autoimmune conditions like ITP. Parents should consult their physician to determine which preservation method aligns best with their specific family medical history and long-term health goals.
For patients managing severely refractory conditions, umbilical cord mesenchymal stem cells for immune thrombocytopenia represent a promising, scientifically grounded investigational approach. While up to 30% of adults fail standard corticosteroid therapies (Blood, 2021), hUC-
Understanding the Regenerative Evidence Continuum is your absolute strongest defense against medical exploitation. This specific framework forces you to demand peer-reviewed evidence and objectively categorize cellular therapies as experimental, ultimately protecting you from aggressive marketing that promises guaranteed cures for complex autoimmune dysfunctions.
If your current ITP treatment regimen is failing and your quality of life is degrading, schedule a dedicated consultation with a board-certified hematologist to discuss your strict eligibility for active, registered clinical trials. Stop relying on internet forums or offshore clinic brochures for medical advice; instead, pull up the active study parameters on ClinicalTrials.gov and bring that hard data directly to your next hematology appointment.