Our Services
Others
- DFPP
- Shockwave
- IV Drip

Patients researching a stem cell transplant for autoimmune disease quickly encounter two completely different protocols. There’s intensive, hospital-based HSCT, which relies on chemotherapy. Then there’s clinic-based MSC therapy, a milder, immunomodulatory approach. Neither is a guaranteed cure.
Navigating these options without understanding the distinct biological mechanisms immune reset versus immune calming can lead to mismatched expectations and unrecognized risks. It’s a high-stakes decision.
In this guide, you’ll learn the exact procedural, safety, and evidence differences between HSCT and MSC therapy. We break down the clinical processes, condition-specific evidence, and how to determine which approach actually aligns with your diagnosis.
Autoimmune disease pathology presents a severe clinical challenge because the human immune system actively adapts to evade targeted pharmaceutical interventions. When rheumatologists prescribe standard biologics or broad immunosuppressants, the body frequently develops biological workarounds. This creates a refractory state where the disease simply ignores the drugs and continues damaging tissues. Isolated symptom management fails when the underlying biological machinery continues generating autoreactive cells.
Patients require a systemic biological intervention to alter this trajectory, rather than just masking the resulting inflammation.
“Standard disease-modifying drugs fail to halt progression in up to 30% of severe autoimmune cases (NIH, 2026) forcing patients to seek systemic cellular interventions.”
Your immune memory is stubborn. T-cells and B-cells catalog threats, and in autoimmune disease, they’ve erroneously cataloged your own tissues as the enemy. Standard drugs suppress this activity, but they don’t erase the memory.
Once you stop the medication, the attack resumes. Peer-reviewed rheumatology research demonstrates that simply suppressing the immune system long-term leads to diminishing returns and accumulating side effects. This biological reality is exactly why patients eventually explore stem cell protocols. They aren’t just looking for temporary symptom relief; they want to fundamentally alter the behavior of their immune system.
Autologous Hematopoietic Stem Cell Transplantation (AHSCT) is aggressive. It isn’t a simple IV drip of healing cells. First, doctors harvest your own blood-forming (hematopoietic) stem cells through a process called apheresis, collecting millions of progenitor cells over several days. Then comes the brutal part: the conditioning regimen.
You undergo high-dose chemotherapy to intentionally destroy your malfunctioning immune system. This ablates the autoreactive cells attacking your body. Many clinics gloss over this step, but it’s the core of the procedure. HSCT is not just a stem cell infusion; it is a high-dose chemotherapy treatment followed by a stem cell rescue, according to FDA guidelines noting the crucial distinction between blood-forming cell transplants and unapproved therapies (2026). The stem cells don’t fight the disease the chemotherapy does.
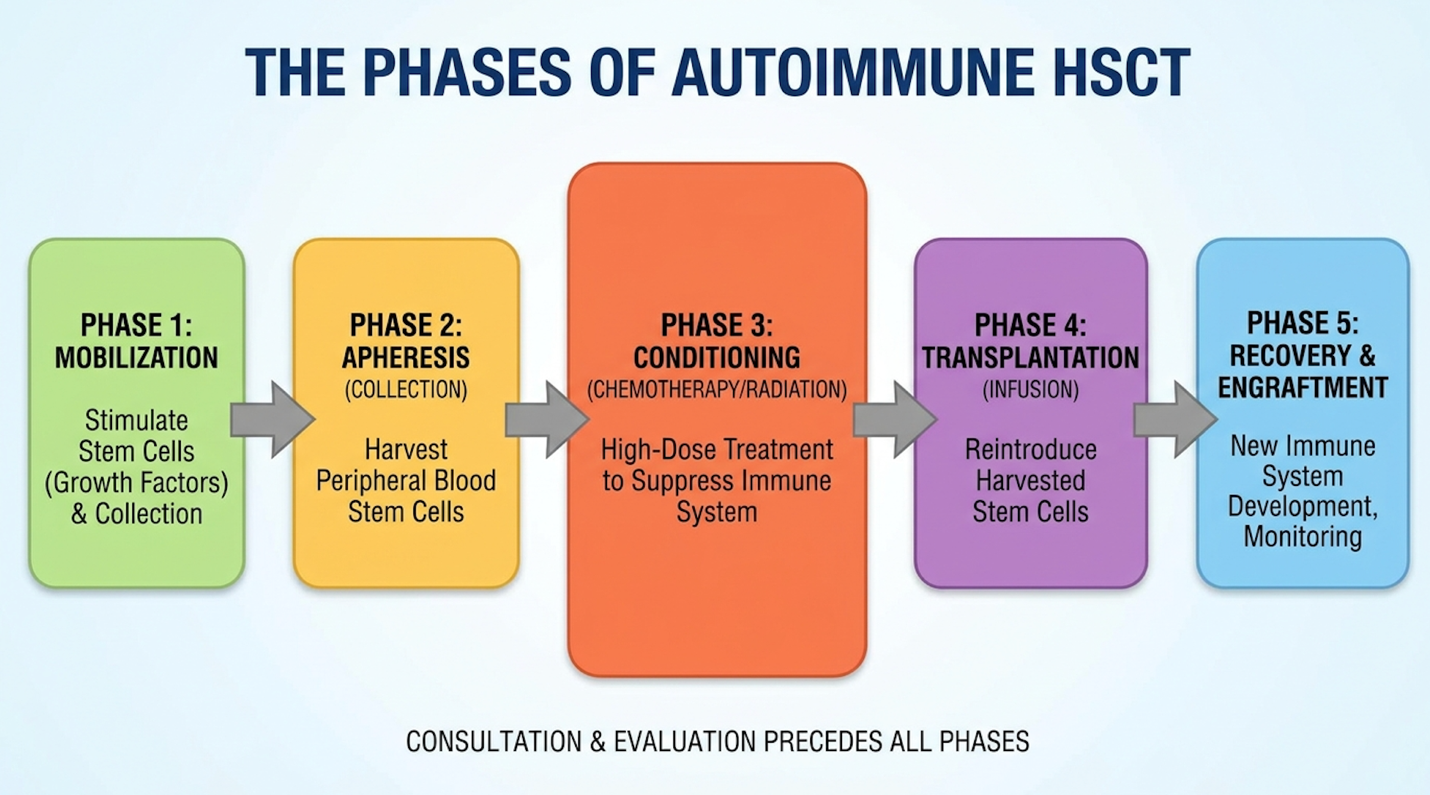
Once the chemotherapy wipes out your immune defenses, your body requires immediate rescue. Doctors re-infuse your previously harvested stem cells, a process outlined in standard National Cancer Institute guidelines. These naive, unprogrammed cells migrate to your bone marrow and begin generating a brand-new immune system from scratch.
The recovery is intense. You’ll spend weeks in a hospital isolation ward because you essentially have zero immune function. You’re extremely vulnerable to opportunistic infections during this window. This complete destruction and rebuilding process is what clinicians mean when they discuss an autoimmune stem cell treatment step-by-step. It’s a profound physiological trauma designed to force a biological reboot.
Yes, but the term “reset” technically only applies to HSCT. When patients ask if stem cells can truly reset the immune system, they are specifically referring to this aggressive eradication of old immune memory.
By destroying the existing T and B cells and growing new ones, HSCT provides a clean slate. The new immune system doesn’t “remember” to attack your nervous system or joints. It’s a genuine systemic reset, though it comes at the cost of immense physical toll, as documented in clinical immunology studies. We call this the Immune Reset vs Calming Framework, and it’s the fundamental baseline for understanding stem cell protocols.
Conversely, immune calming achieved through MSC therapy doesn’t destroy anything. Instead of wiping the hard drive, it installs a software patch.
| 📌 If you’re interested in how MSCs shift the immune system from attack mode to repair mode, we have an interesting article that discusses mesenchymal stem cell therapy for immune modulation, which you can read via the internal link. |
Mesenchymal stem cells alter the behavior of your existing immune cells through complex stem cell immune signaling. Stem cell regulatory research shows they suppress the overactive attackers and boost regulatory cells without requiring toxic conditioning. It’s a modulation strategy, not a reset. Understanding this distinct biological difference prevents massive misunderstandings about what a cellular procedure actually entails and the risks involved.
Mesenchymal stem cells (MSCs) operate entirely differently from blood-forming hematopoietic cells. MSC therapy does not use chemotherapy. Instead, it involves infusing these specialized cells—often derived from ethical umbilical cord tissue to calm systemic inflammation.
| 📌 If you’re interested in why umbilical cord cells are often preferred over bone marrow or fat-derived cells, we have an interesting article that discusses why UC-MSCs are superior to other stem cell sources, which you can read via the internal link. |
They work primarily through paracrine signaling. The cells act like microscopic pharmacies, secreting cytokines and growth factors that directly inhibit T-cell proliferation while promoting regulatory T cells (Tregs). PubMed clinical reviews demonstrate mesenchymal stem cells creating an immunomodulatory effect by inhibiting T-cell proliferation. They don’t replace your immune system; they actively negotiate with it to stand down. For a deeper scientific breakdown, review our UC-MSC autoimmune science guide.
Because there’s no immune ablation, the delivery is straightforward. It’s usually administered via intravenous infusion in a clinical setting over a few hours.
Patients frequently ask about the difference between stem cell transplant and stem cell therapy. A transplant (HSCT) uses your own cells to rescue you from chemotherapy. A therapy (MSC) uses donor mesenchymal stem cells to reduce inflammation natively, a mechanism currently being evaluated in ongoing clinical trial reviews. It’s a vastly gentler approach, making it accessible to those who couldn’t survive high-dose chemo.
When evaluating HSCT vs mesenchymal stem cells for autoimmune disease, you’re really calculating risk tolerance against disease severity.
HSCT offers a proven track record of halting aggressive disease, but it demands you endure chemotherapy and hospital isolation. MSC therapy offers a gentle safety profile with minimal downtime, but its long-term efficacy is still heavily investigational. You have to choose your biological baseline: do you need to burn the forest down to stop the spread, or can you manage it by aggressively fighting the flames?
| Feature | HSCT (Immune Reset) | MSC Therapy (Immune Calming) |
| Primary Goal | Eradicate and rebuild immune system | Suppress inflammation and modulate immune response |
| Chemotherapy Required? | Yes (High-dose conditioning) | No |
| Typical Setting | Hospital hematology-oncology ward | Specialized outpatient clinic |
| Major Risks | High toxicity, severe infection, 1-2% mortality | Low acute risk; long-term efficacy unproven |
| Evidence Level | High (Standard of care for specific MS cases) | Investigational (Ongoing clinical trials) |
| Where Offered | Major research hospitals | International stem cell clinics |
Looking at the clinical hematology parameters, HSCT’s evidence base is undeniably stronger for specific conditions, but the collateral damage is fierce. MSC therapy sidesteps the danger, yet lacks the decades of longitudinal data that hospitals demand for investigational cellular protocols.
When people ask which autoimmune diseases can be treated with stem cells, relapsing-remitting multiple sclerosis (MS) leads the conversation. This is where HSCT shines brightest.
For highly active MS that ignores standard drugs, a stem cell transplant for autoimmune disease can dramatically alter the patient’s trajectory. Clinical data from NIH Central records reports up to 70% to 80% treatment-free clinical remission in relapsing-remitting MS (2026 updates). Furthermore, NIAID funded trials are demonstrating superiority over standard disease-modifying drugs. It stops new inflammatory lesions dead in their tracks. Our clinical team continually evaluates these emerging protocols, and we’ve observed that matching the precise disease state to the correct cellular mechanism is the single most critical factor for success.
While HSCT for multiple sclerosis has the strongest backing, researchers are aggressively tracking other conditions. The evidence varies wildly depending on the pathology.
For severe systemic sclerosis (scleroderma), HSCT has demonstrated clear survival benefits over standard immunosuppression regimens, actively halting skin thickening and preserving lung function. However, the toxicity during conditioning remains a massive barrier. Read our Systemic Sclerosis research breakdown.
In systemic lupus erythematosus (SLE), both HSCT and MSCs are showing significant promise for treatment-resistant patients facing imminent organ failure. Recent 2026 clinical data suggests MSCs can safely reduce proteinuria in lupus nephritis without the dangers of chemo. See our Lupus stem cell evidence guide.
For Crohn’s disease, MSCs are actively used to treat complex perianal fistulas. They show high closure rates where repeated surgeries fail, according to the Crohn’s and Colitis Foundation. Dive into our Crohn’s fistula applications overview.
Rheumatoid arthritis (RA) sees mixed results in clinical settings. While localized joint inflammation often decreases rapidly following MSC infusions, long-term systemic disease modification requires far more rigorous, large-scale data before it becomes a standard of care. Check our RA joint therapies page for the latest clinical trial outcomes.
Finally, for Type 1 Diabetes, MSC therapy is actively being studied for beta-cell preservation to delay insulin dependence in newly diagnosed patients. It is absolutely not a cure, and it will not reverse long-standing diabetes. Researchers are focused on extending the ‘honeymoon phase’ of the disease rather than replacing daily insulin. See our Type 1 Diabetes investigations.
Stem cell therapies are never first-line treatments. They are reserved exclusively for patients who have failed conventional therapies.
So, who actually qualifies for HSCT for autoimmune disease? Generally, doctors look for younger patients with a shorter disease duration who are experiencing aggressive inflammatory activity despite trying top-tier biologics. You must have adequate organ function specifically heart, lung, and kidney health to survive the chemotherapy conditioning phase outlined by EBMT clinical guidelines. If your body can’t handle the chemo, you simply aren’t a candidate for HSCT.
Conversely, who should stay away? Patients with severe, irreversible organ damage face unacceptably high mortality risks. Advanced age and a high baseline infection risk are major contraindications recognized in clinical rheumatology standards.
Additionally, if your disease is in a “burned-out” phase meaning the active inflammation has stopped, but you’re left with permanent nerve or tissue damage HSCT won’t help. Stem cells don’t regenerate dead nerves. They stop active fires. If you fall into these high-risk categories, the conversation must pivot away from aggressive hospital protocols immediately.
Medical research is rapidly moving beyond blunt-force immune resets. The current debate around CAR-T vs stem cell transplant for autoimmune disease highlights this dramatic shift in treatment philosophy.
Traditionally used for blood cancers, CAR-T cell therapy is now being heavily investigated for conditions like severe lupus. Instead of wiping out the entire immune system with chemotherapy like HSCT does, CAR-T involves engineering your T-cells in a lab to selectively hunt down and destroy only the misbehaving autoreactive B-cells. National Institutes of Health updates report incredible early remission data using this highly targeted approach. Our clinical team closely monitors these CAR-T advancements, recognizing them as the probable future of autoimmune care.
This represents a massive leap in precision targeting. Initial CAR-T trials show profound drug-free remission in small lupus cohorts (Nature, 2026) signaling a potential end to broad immune ablation. It’s the next logical evolution beyond the collateral damage of a stem cell transplant for autoimmune disease.
While still highly experimental and carrying its own neurotoxicity risks documented in recent clinical hematology reviews, CAR-T may eventually offer the deep remission of HSCT without the danger of high-dose chemo. For patients researching the cutting edge of cellular biology, explore our guide on targeted NK cellular therapies to see how precision immunology is reshaping treatment timelines.
HSCT is typically performed off-label or under clinical trial protocols for autoimmune diseases in most countries. While fully approved as a standard of care for specific blood cancers like leukemia, its autoimmune applications remain investigational in the US. However, some European nations now endorse it for severe, rapidly progressing MS. Access usually requires failing multiple FDA-approved biologics first, demonstrating a truly refractory disease state.
A stem cell transplant and stem cell therapy are biologically distinct medical procedures. A transplant (HSCT) uses high-dose chemotherapy to destroy the immune system, relying on your own stem cells solely for rescue. Alternatively, stem cell therapy (MSC) uses donor cells to reduce systemic inflammation without any chemotherapy. Understanding this difference is absolutely crucial for accurately assessing your personal risk tolerance.
A stem cell transplant does not technically cure MS, but it can induce long-term, treatment-free remission. Published clinical data shows that disease progression often halts completely in properly selected patients, preventing new neurological lesions for years. However, clinical relapse remains a documented possibility over a ten-year horizon, making ongoing neurological monitoring essential. It is an aggressive disease-modifying intervention, not a guaranteed permanent cure.
Many patients successfully stop standard disease-modifying drugs after a successful HSCT procedure. Because the autoreactive immune memory is theoretically wiped clean by the chemotherapy, daily immunosuppression often becomes unnecessary for several years. However, you must strictly manage any medication tapering with your treating neurologist. Premature or unmonitored cessation can trigger severe flare-ups, so medical supervision remains critical during your recovery window.
Recovery from an HSCT procedure for autoimmune disease typically requires a 3 to 4 week hospital stay. This is followed by 3 to 6 months of intense at-home recovery while your body heals from the chemotherapy. Because the conditioning ablates your immune system, you remain highly susceptible to dangerous infections during this fragile window. Full immune system reconstitution—where your blood counts normalize entirely—can take up to a year or more, making this a grueling medical marathon rather than a quick fix.
MSC therapy carries a significantly lower immediate risk profile than HSCT because it completely avoids toxic chemotherapy conditioning. You bypass the immediate dangers of sepsis, hair loss, and acute organ toxicity associated with complete immune ablation. However, while acute safety is exceptionally high, long-term efficacy data for MSCs is still being established compared to the decades of HSCT research available today. Ultimately, it effectively trades immediate physical safety for long-term clinical uncertainty, which patients must carefully weigh.
| 📌 If you’re planning treatment in Thailand and want a practical checklist for choosing a safe clinic, we have an interesting article that discusses whether stem cell therapy is safe in Thailand, which you can read via the internal link. |
For advanced patients, a stem cell transplant for autoimmune disease offers profound disease-modifying potential. Published research confirms that HSCT achieves up to 80% clinical remission in relapsing MS, though it carries a steep 1-2% mortality risk. The best approach demands rigorously matching your disease severity with your physiological ability to withstand either an aggressive hospital chemotherapy protocol or a milder, clinic-based cellular infusion.
This requires applying the Immune Reset vs. Calming Framework to your specific diagnosis. If your body cannot handle the toxicity of an immune reset, the calming mechanism of MSCs provides a viable, safer alternative. You have to weigh the proven long-term ablation data of a hospital transplant against the gentle, yet investigational, safety profile of clinical immunomodulation.
Not sure which option fits you? Send your diagnosis and medicines list for an honest doctor review to determine if clinical stem cell protocols align with your specific autoimmune profile.