Our Services
Others
- DFPP
- Shockwave
- IV Drip

If your AMH is low or IVF has produced few eggs, you have probably seen adverts for new fertility treatments for low ovarian reserve: stem cells, PRP, “ovarian activation” and even lab-grown eggs. Some are being tested in women today. Others exist only in mice or in a dish. This guide puts them side by side, with an honest label on each, so you can tell what is real now and what is still years away.
Stem cell (UC-MSC) and PRP injections: small human studies. In vitro activation (IVA): research centres only. Exosomes and artificial ovaries: animal studies. Lab-grown eggs: lab only. IVF with your own or donor eggs remains the standard treatment.
You are born with all the eggs you will ever have. That supply falls with age, and for some women it falls early because of genetics, autoimmune disease, surgery, chemotherapy or unknown causes. When the ovaries stop working normally before 40, doctors call it premature ovarian insufficiency (POI).
Standard care today is straightforward. Doctors try IVF with adjusted stimulation to collect as many of your own eggs as possible. If that is unlikely to work, IVF with donor eggs has the highest chance of pregnancy. Women with POI also usually need hormone therapy to protect bone and heart health (ESHRE/ASRM POI guideline, 2024).
Everything else on this page is an add-on being studied, not a replacement for that care.
Here are the experimental fertility treatments you are most likely to hear about, ordered from most to least tested in women.
| Treatment | How it works | Evidence level | Available to patients today? |
| UC-MSC stem cells | Donor cells injected into the ovary or given by IV release signals that may support remaining follicles | Small human studies | Yes, at some clinics, as an experimental option |
| PRP (platelet-rich plasma) | Your own blood, concentrated and injected into the ovary | Small human studies; mixed randomized trials | Yes, at many fertility clinics |
| In vitro activation (IVA) | Ovarian tissue is removed, treated in the lab to wake dormant follicles, then put back | Small human case series | Research centres only |
| Exosomes | Tiny packets released by stem cells, given without the cells themselves | Animal studies | Not as a proven treatment |
| Artificial ovary | A scaffold holding follicles, implanted to restore function | Animal studies | No |
| Lab-grown eggs (IVG) | Eggs made from a person’s own skin or blood cells | Lab only | No |
Umbilical cord mesenchymal stem cells (UC-MSCs) are donated cells that release signals which may reduce inflammation and support the follicles a woman still has. In a 2018 study of women with ovarian failure, UC-MSCs placed on a collagen scaffold were linked to follicle growth and some pregnancies (Ding et al., Science China Life Sciences). Studies so far are small and mostly without control groups. For the procedure, results and who may be a candidate, read stem cell therapy for ovarian rejuvenation.
| 📌 If you’re interested in why umbilical cord cells are often preferred over bone marrow or fat-derived cells, we have an interesting article that discusses why UC-MSCs are superior to other stem cell sources, which you can read via the internal link. |
In vitro activation (IVA) for ovarian insufficiency was developed by Professor Kazuhiro Kawamura’s team in Japan. Most follicles in the ovary are asleep. IVA tries to wake the few that remain.
It works in two steps. First, a surgeon removes a piece of ovarian tissue by keyhole surgery. In the lab, the tissue is cut into small fragments and treated with substances that switch on a growth signal inside follicles. The fragments are then placed back near the ovary, and the woman goes through IVF to collect any eggs that grow (Kawamura et al., 2016).
Results show both promise and limits. A review of 51 women with POI treated with IVA found follicle growth in about 3 in 10, and 4 pregnancies in total (Fabregues et al., Journal of Ovarian Research, 2018). It only helps women who still have some sleeping follicles.
| IVA | UC-MSC stem cells | |
| What is done | Your own ovarian tissue is removed, treated and replaced | Donor cells are injected into the ovary or given by IV |
| Surgery | Yes, usually two keyhole operations | No open surgery; a needle procedure or drip |
| How it may work | Directly switches on dormant follicles | Signals that may improve the ovarian environment |
| Where offered | A few specialist research centres | Some regenerative clinics, as an experimental option |
Only in a small number of specialist centres, mostly in Japan and a few other countries, often within research programmes. It is not a routine treatment, and it is not offered at Vega. If you are interested, ask a reproductive endocrinologist about current ovarian rejuvenation clinical trials.
Exosomes are tiny packets that stem cells release, carrying proteins and genetic messages. The idea behind stem cell exosomes for ovarian function is to deliver those signals without giving the cells themselves, which may be easier to standardise and store.
Not yet shown in women. A 2024 analysis of 29 animal studies found that stem cell exosomes improved follicle counts, hormones and pregnancy in rodents with ovarian failure (Rajai Firouzabadi et al., Journal of Ovarian Research). Human trials are only starting. Products sold as “exosome therapy” vary widely, and many are not tested for what they contain.
An artificial ovary is a scaffold, like a tiny sponge, that holds follicles and is placed in the body to take over the work of a failing ovary. In 2017, Northwestern University researchers 3D-printed a gelatin scaffold, filled it with mouse follicles, and implanted it in mice whose ovaries had been removed. Some of the mice became pregnant and gave birth naturally (Medical News Today summary).
The hope is to help women who lost ovarian function after cancer treatment, using follicles frozen before treatment. Human versions face big hurdles: keeping follicles alive, growing blood vessels into the scaffold, and making it last for years. This is still animal research.
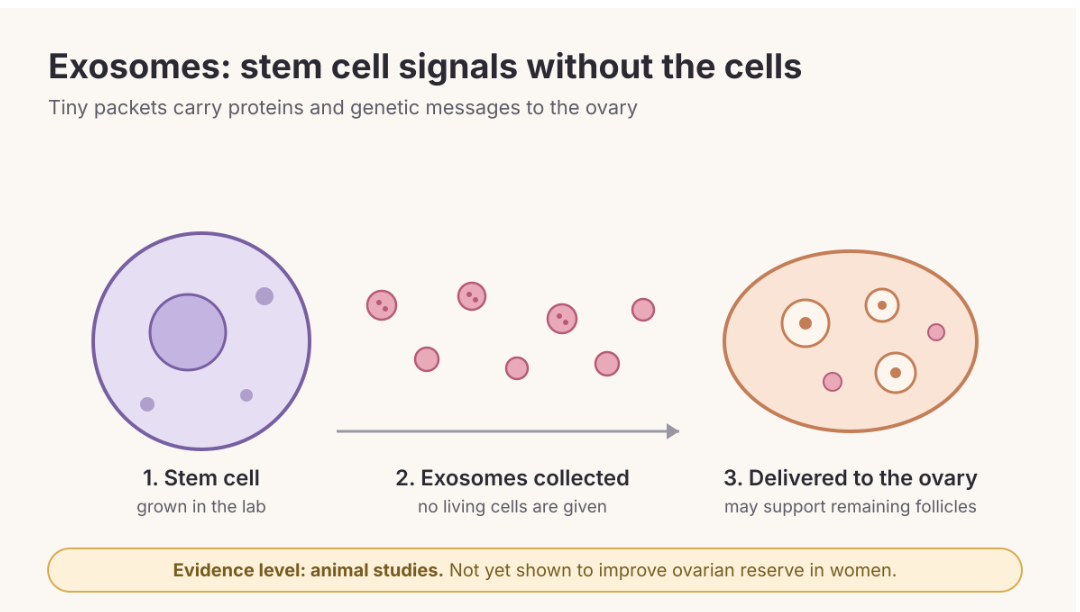
Figure 1. How stem cell exosomes may work: tiny packets released by lab-grown stem cells carry signals to the ovary without giving living cells. Evidence so far comes from animal studies only.
Lab-grown eggs from stem cells, known as in vitro gametogenesis (IVG), would turn a woman’s own skin or blood cells into stem cells, and then into eggs. It has already produced healthy baby mice. In humans, labs in Japan have grown early egg precursor cells but not mature eggs (Murase et al., Nature, 2024).
No. In 2025, one leading researcher, Professor Katsuhiko Hayashi, estimated that viable human lab-grown eggs or sperm may be several years away, and safety would then need to be proven (Guardian report via Bioethics.com). Lab-grown eggs are also not legal for fertility treatment in many countries, including the UK. Any clinic offering them today is not being truthful.
None yet. No new option has been shown in large, well-controlled trials to raise live birth rates for women with low ovarian reserve. Here is where each one sits on the evidence ladder, from closest to proven to furthest away:
The international guideline on premature ovarian insufficiency treats these approaches as research topics, not routine care (ESHRE/ASRM, 2024).
No, At best, stem cells may support the ovary so that IVF has more to work with. The usual order is: an assessment of your hormones and IVF history, then a doctor’s honest view of your chances with your own eggs. If you choose a stem cell approach, it is typically done a few months before a further IVF cycle, so any change can be measured.
| 📌 If you’re interested in whether a second dose can extend the benefits of the first, we have an interesting article that discusses why double-dose UC-MSC therapy may offer greater benefits than a single dose, which you can read via the internal link. |
Donor eggs remain the most reliable route to pregnancy for many women with very low reserve. Choosing an experimental option should not delay that decision for too long, especially after 40.
Whichever option you consider, and whichever clinic, ask these six questions. A trustworthy clinic will answer each one clearly and in writing.
Be wary of any clinic that promises pregnancy, quotes success rates without published data, or tells you to stop seeing your fertility specialist.
| 📌 If you’re planning treatment in Thailand and want a practical checklist for choosing a safe clinic, we have an interesting article that discusses whether stem cell therapy is safe in Thailand, which you can read via the internal link. |
A clinical trial is often the safest way to try a new option, because the treatment is closely monitored and results are published. You can search for ovarian rejuvenation clinical trials on ClinicalTrials.gov using terms such as “premature ovarian insufficiency” or “poor ovarian response”. Ask your fertility doctor to help you check whether you meet the entry criteria.
At Vega Stem Cell Clinic in Bangkok, Thailand, we offer UC-MSC therapy for selected women with low ovarian reserve as an experimental, supportive option. We do not offer IVA, exosome products or lab-grown eggs.
For what to expect, see stem cell ovarian rejuvenation in Thailand.
The newest options being tested in women are UC-MSC stem cells, PRP and in vitro activation. Exosomes, artificial ovaries and lab-grown eggs are still in animal or lab research.
No treatment available today has been shown to create new eggs. The options being studied aim to support or wake follicles that are already there.
PRP and UC-MSC stem cells have the most human data, but both still need larger controlled trials. IVA has live births, but only at a few research centres.
Yes. Most are used before an IVF cycle, with the aim of collecting more or better eggs. They do not replace IVF.
Some studies include women with POI, and a few pregnancies have been reported. Results are less likely when very few follicles remain, so a doctor’s assessment matters.
Short-term side effects reported in studies are usually mild, such as pain at the injection site. Long-term safety is not fully known, which is why careful screening, lab testing and follow-up are essential.
There is no fixed rule, but because egg supply falls with age, many doctors suggest setting a clear time limit, such as one or two cycles, before reviewing other options.
Not sure which option, if any, fits your situation? Send us your AMH and FSH results, recent ultrasound reports and IVF history. A Vega doctor in Bangkok, Thailand, will review them free of charge and give you an honest opinion: whether a UC-MSC approach may help, or whether IVF, donor eggs or a clinical trial is the better next step.