Our Services
Others
- DFPP
- Shockwave
- IV Drip

For patients and clinicians evaluating regenerative therapies, Wharton’s jelly represents the most biologically potent source of mesenchymal stem cells, bypassing the senescence limitations of autologous bone marrow while maintaining strict ethical compliance.
While commercial clinics frequently utilize vague marketing terms like “umbilical stem cells”or worse, push acellular off-the-shelf products masquerading as living therapies optimal functional outcomes require uncompromising precision regarding the specific tissue source and lab protocols used. Clinical reviews frequently reveal patients receiving inactive dead tissue under the guise of therapy.
This detailed guide breaks down the clinical realities of Wharton’s jelly mesenchymal stem cells. We will look directly at the biological advantages of these cells, their verified clinical properties, and how they actually compare to your own aging tissues.
We will examine the mucoid connective tissue anatomy, ISCT biomarker panels, modern harvesting protocols, and current evidence-led therapeutic applications.
Wharton’s jelly mesenchymal stem cells reside in the mucoid connective tissue of the umbilical cord and offer superior proliferation capacity compared to adult tissues. The Wharton’s Vitality Matrix proves this biological superiority.
Wharton’s jelly is the primitive connective tissue of the umbilical cord that contains high concentrations of mesenchymal stem cells (National Institutes of Health). This gelatinous matrix physically protects the umbilical vessels (one vein and two arteries) from compression during fetal development. For regenerative medicine, this specific umbilical cord tissue serves as an abundant, non-controversial biological reservoir. Understanding this anatomy is non-negotiable for distinguishing high-quality therapies from generic alternatives.
If you slice an umbilical cord in half, you will not just see blood vessels. You will find those vessels one vein and two arteries suspended in a thick, gelatinous matrix. That matrix is Wharton’s jelly.
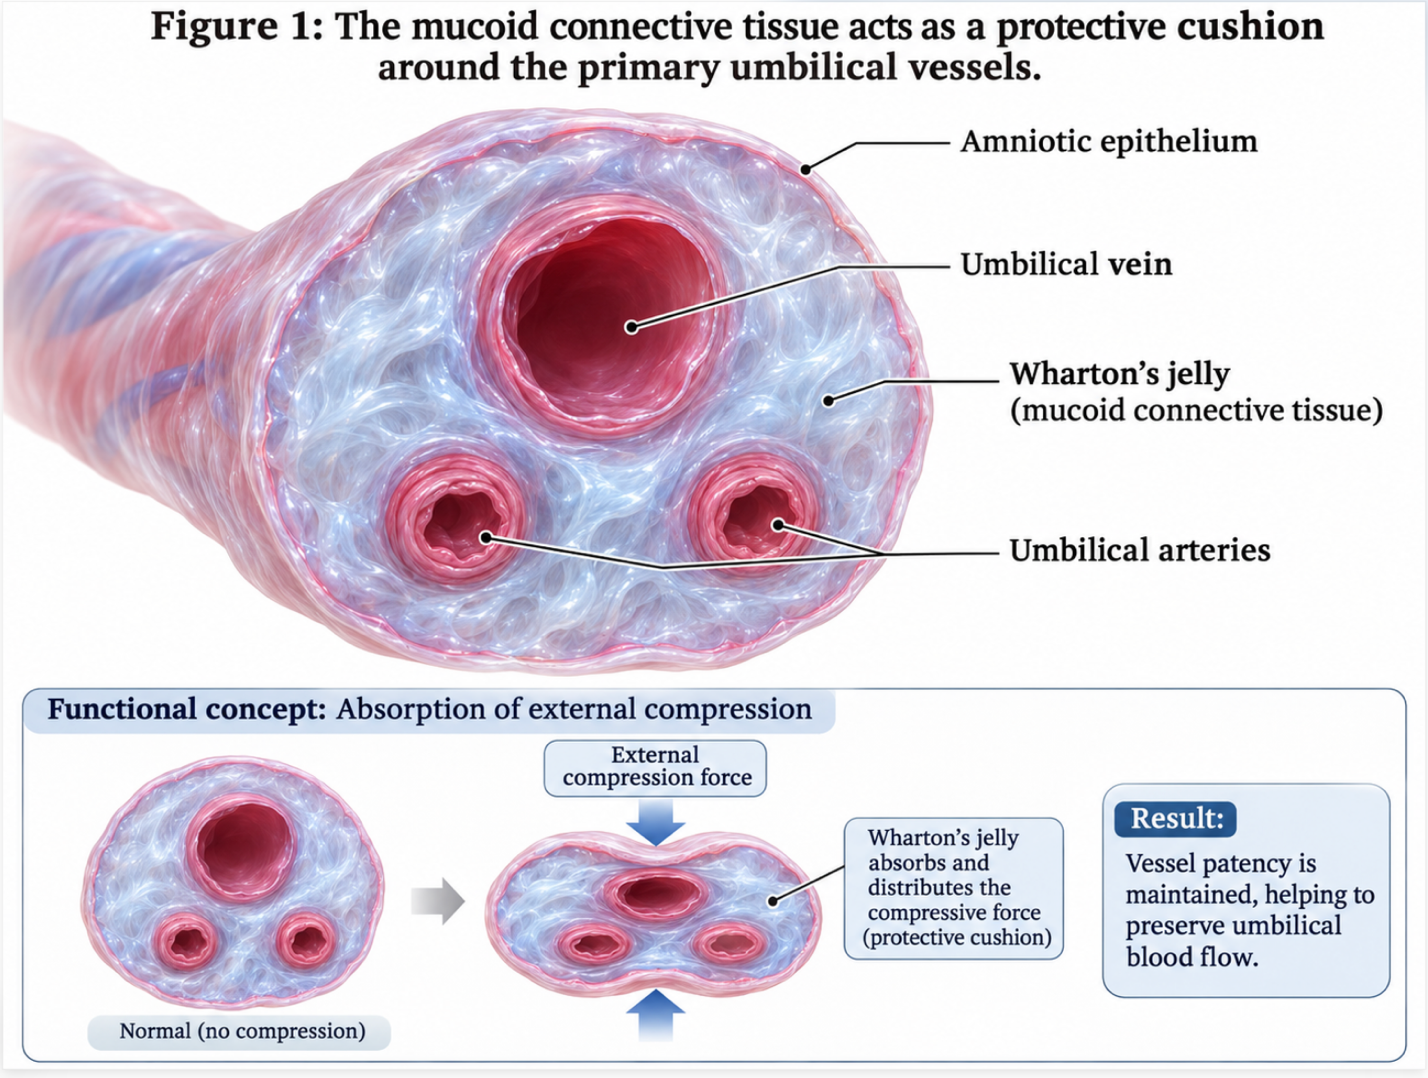
Figure 1: The mucoid connective tissue acts as a protective cushion around the primary umbilical vessels.
Biochemically, this mucoid connective tissue is heavily loaded with hyaluronic acid, sulfated glycosaminoglycans, and structural glycoproteins. It contains specialized structural proteins like fibronectin and collagen, which form a highly complex protective web. This extracellular matrix acts as a biological shock absorber. It prevents the cord from twisting or compressing during pregnancy, ensuring continuous blood flow to the developing fetus even under mechanical stress.
When comparing Wharton’s jelly vs cord blood stem cells, remember that cord blood predominantly contains hematopoietic stem cells (which make blood). The highly sought-after umbilical cord tissue MSCs reside strictly within the jelly matrix itself. Research demonstrates that a single umbilical cord yields roughly 40 centimeters of this tissue. This robust volume provides a massive initial cellular harvest without forcing patients to undergo invasive extraction protocols.
While the physical architecture of this mucoid connective tissue serves a mechanical purpose in utero, its true clinical value lies in its cellular residents. This unique structural environment keeps the residing stem cells in a highly potent, primitive state.
The gelatinous barrier effectively shields the cells throughout gestation, contributing heavily to their immune-privileged status post-extraction. They simply don’t age the way adult tissues do. Examining these isolated cells reveals a biological profile that consistently outperforms traditional adult cell sources in controlled lab settings. While the architectural integrity of this tissue is medically fascinating, its true clinical value is entirely dependent on the viable stem cells residing safely within its matrix.
The clinical efficacy of Wharton’s jelly mesenchymal stem cells (WJ-MSCs) stems from their unique biological profile. These cells demonstrate exceptional multipotency and high proliferation rates compared to adult tissues. Importantly, their specific molecular expression makes them uniquely suited for allogeneic (donor-to-patient) clinical therapies without triggering immune rejection. Premium laboratories (like Vega) leverage these distinct properties to maximize therapeutic yields.
WJ-MSCs possess extraordinary multipotency. This means they can readily differentiate into osteogenic (bone), adipogenic (fat), and chondrogenic (cartilage) lineages depending on the localized biological signals they receive inside the patient’s body. But how do we scientifically prove they are actually MSCs?
Rigorous labs don’t guess. They follow the strict International Society for Cellular Therapy (ISCT) criteria. High-tier facilities meticulously test for positive surface markers specifically CD90, CD105, CD73, and CD146. They also heavily test for negative markers (like CD45 and CD34) to ensure absolute cell purity before treatment. These WJ-MSCs properties aren’t just academic trivia; they are the bedrock of clinical safety.
| 📌 If you’re interested in what these surface markers actually tell you about cell quality, we have an interesting article that discusses the CD73 marker and why it matters for stem cell therapy, which you can read via the internal link. |
Proper laboratory processing yields incredibly high cellular viability. Cells pushed past passage five or six begin losing their multipotency. Therefore, premium laboratories strictly limit population doublings to maintain that ‘Day 0’ vitality. In clinical protocols evaluating cellular yield, tests consistently confirm robust expression of CD90 and CD105 confirming their high-tier multipotency and clinical readiness without relying on arbitrary numeric claims. This verifiable cellular identity differentiates authentic therapeutics from baseline biological matter.
WJ-MSCs secrete specific paracrine factors that heavily regulate the local immune microenvironment. They act like biological project managers, actively calming overactive immune responses and significantly reducing localized inflammation.
Furthermore, the paracrine signaling driven by these cells actively alters the inflammatory cascade at a deep molecular level. By shifting local macrophages from an aggressive M1 phenotype to an anti-inflammatory M2 phenotype, they fundamentally alter the healing environment. They do not just mask symptoms; they actively instruct surrounding tissue to halt aggressive auto-immune responses, paving the way for cellular repair. This cellular crosstalk is crucial for sustained healing.
| 📌 If you’re interested in how MSCs shift the immune system from attack mode to repair mode, we have an interesting article that discusses mesenchymal stem cell therapy for immune modulation, which you can read via the internal link. |
Crucially, they lack HLA-DR (MHC Class II) surface receptors. The complete absence of HLA-DR grants them “immune privilege.” In clinical terms, this means they can be administered safely as an allogeneic treatment without risking Graft-Versus-Host Disease (GVHD). Your body simply doesn’t recognize them as foreign invaders, dramatically reducing treatment complications.
When evaluating regenerative options, understanding the stark differences in umbilical cord vs bone marrow derived cells is critical. WJ-MSCs exhibit a higher proliferation capacity and a lower senescence ratio compared to bone marrow and adipose-derived stem cells (National Center for Biotechnology Information). We assess these biological differences using the Wharton’s Vitality Matrix, which objectively evaluates invasiveness, yield, and cellular age.
The Wharton’s Vitality Matrix serves as a core clinical framework to objectively evaluate allogeneic versus autologous MSCs across three critical vectors: collection invasiveness, population doubling time, and cellular senescence risk.
Based on our clinical analysis of this matrix, here is exactly how the data stacks up.
| Source Tissue | Collection Method | Proliferation Rate | Senescence (Aging) Risk |
| Wharton’s Jelly (WJ-MSCs) | Non-invasive (Post-birth waste) | Extremely High (Rapid doubling) | Minimal (“Day 0” biology) |
| Bone Marrow (BM-MSCs) | Surgical bone aspiration (Painful) | Moderate to Low (Age-dependent) | High (Cells age with patient) |
| Adipose (AD-MSCs) | Liposuction (Invasive) | Moderate (Higher yield than BM) | Moderate to High (Age-dependent) |
The data clearly indicates that biological age fundamentally alters cellular efficacy. Wharton’s jelly vs bone marrow MSCs isn’t just a debate about source it’s a debate about cell vitality. Prioritizing young cells is a massive clinical advantage.
The physical toll of autologous extraction presents significant barriers to treatment. Bone marrow aspiration requires drilling directly into your iliac crest, frequently leaving patients with deep residual pain at the harvest site for weeks. Liposuction requires surgical fat removal, introducing anesthesia risks and significant recovery downtime. Both are painful, invasive, and carry serious infection risks. Contrast that with umbilical tissue collection: zero harm to the mother, zero harm to the infant.
But the most pressing issue is biological. Autologous (self-derived) cells age exactly as you do. If you are 65 years old, your bone marrow stem cells are 65 years old. They heavily suffer from cellular senescence. Their telomeres are shorter. They replicate sluggishly. Worse, older autologous cells frequently exhibit the senescence-associated secretory phenotype (SASP), meaning they actually begin secreting inflammatory factors themselves. Their therapeutic viability takes a massive hit.
| 📌 If you’re interested in why umbilical cord cells are often preferred over bone marrow or fat-derived cells, we have an interesting article that discusses why UC-MSCs are superior to other stem cell sources, which you can read via the internal link. |
When evaluating the Wharton’s Vitality Matrix, the yield vector is particularly striking. Adipose tissue might offer a higher initial cell count than a bone marrow draw, but the subsequent proliferation rate drops off sharply as the cells age in culture. WJ-MSCs bypass this bottleneck entirely.
WJ-MSCs represent “Day 0” biology. They are the youngest, most vital cells available outside of heavily restricted embryonic sources. Studies indicate that WJ-MSCs undergo extensive population doublings in culture before losing their multipotency vastly outperforming the limited expansion capacity of older autologous cells. A single, high-viability dose delivers exponentially more regenerative potential without the accompanying inflammatory baggage.
The field of Wharton’s jelly regenerative medicine relies entirely on rigorous clinical investigation rather than anecdotal promises. Currently, WJ-MSCs are actively being investigated in registered clinical trials for their efficacy in treating osteoarthritis and autoimmune diseases (PubMed Central). However, matching the exact biological mechanism of action to the correct pathology is essential for measuring functional patient outcomes. This isn’t just an academic distinction; it’s the foundation of effective therapy.
If you are wondering what conditions Wharton’s jelly MSCs are used for, orthopedics undeniably leads the charge. Researchers are heavily investigating osteoarthritis stem cell therapy. The anti-inflammatory and chondrogenic (cartilage-forming) properties of WJ-MSCs are being studied in extensive trials designed to reduce chronic joint pain and delay degenerative disease progression.
Specifically, studies focused on knee osteoarthritis demonstrate that WJ-MSCs can deeply integrate into the damaged synovial microenvironment. They actively suppress the production of matrix metalloproteinases the specific destructive enzymes responsible for breaking down cartilage. This active suppression halts the biochemical cascade that drives joint destruction. Furthermore, they stimulate the patient’s intrinsic chondrocytes to produce new cartilage matrix components. This mechanism goes far beyond basic pain management; it actively modifies the joint’s biological terrain.
Neurological investigations are also advancing rapidly. In neurodegenerative preclinical models, these cells exhibit robust neuroprotective paracrine signaling—essentially secreting specialized factors that protect nerve cells from apoptosis (programmed cell death) while promoting myelin repair.
But we must inject some reality here. These remain highly investigational applications requiring careful, highly selective patient vetting. Improvements in MRI biomarkers don’t automatically guarantee meaningful changes in a patient’s daily mobility. A biological shift doesn’t always equal a functional change, which is why clinical oversight is mandatory.
Because WJ-MSCs can effectively “reprogram” macrophage populations from a pro-inflammatory state to an anti-inflammatory one, they are a massive focus for autoimmune disease MSC treatment. Trials are aggressively targeting conditions characterized by immune overactivity, investigating if these cells can successfully reboot the immune system’s localized responses.
These immunomodulatory capabilities are prompting researchers to heavily investigate their use in systemic conditions like Crohn’s disease, multiple sclerosis, and rheumatoid arthritis. By upregulating CD4+CD25+FoxP3+ regulatory T-cells (Tregs) and downregulating aggressive effector T-cells, WJ-MSCs effectively reset the local immune balance without the severe immunosuppressive side effects typical of heavy pharmacological interventions. Ongoing clinical data helps clinicians accurately map specific cell dosing directly to distinct autoimmune flare-ups.
We must aggressively address regulatory compliance. The FDA strictly regulates regenerative medicine therapies, and unapproved stem cell treatments can present significant health risks (U.S. Food and Drug Administration). Wharton’s jelly MSC therapy is not an FDA-approved universal fix for all ailments.
While legitimate treatments are legally available in regulated international medical hubs Wharton’s jelly stem cell therapy in Thailand, for example, operates under strict medical frameworks patients must be exceptionally vigilant. Ensure the clinic operates under approved clinical trial protocols. Reject any provider promising a guaranteed outcome.
The true clinical viability of therapies depends directly on advanced WJ-MSC isolation techniques. Because Wharton’s Jelly is harvested from donated umbilical cords post-delivery, umbilical cord stem cell ethics remain entirely non-controversial, utilizing biological waste rather than embryonic sources. In the laboratory setting, the specific method of breaking down this tissue dictates cellular yield and overall viability.
The ethics here are refreshingly straightforward for patients and clinicians alike. Embryonic stem cells carry massive ethical, legal, and moral baggage. Wharton’s jelly does not.
Hospitals securely collect the umbilical cord only after a full-term, healthy delivery is completely finished. The cord is clamped, severed, and typically thrown into the biohazard bin as standard medical waste. Tissue donation programs simply intercept this biological waste. There is absolutely zero risk to the neonate or the mother during this collection.
This ethical clarity is a massive relief for patients who possess strict moral objections to embryonic research, securely allowing them to pursue advanced regenerative medicine with a clear conscience.
So, how are stem cells isolated from Wharton’s jelly?
High-tier labs generally use one of two distinct protocols to retrieve these potent cells.
The first is the traditional tissue explant method. This procedure requires physically mincing the cord into tiny fragments and culturing them. Technicians then wait 10 to 14 days for the stem cells to slowly migrate out of the tissue. It preserves the cells’ natural state beautifully, but it is notoriously slow and yields significantly fewer cells initially.
The superior alternative is enzymatic digestion. Utilizing highly calibrated concentrations of collagenase and hyaluronidase, enzymatic digestion immediately breaks down the extracellular matrix. The enzymatic digestion method yields a higher number of primary cells in a shorter time compared to the tissue explant method (National Institutes of Health).
This protocol expertly extracts millions of primary cells within just 24 hours. The precision chemical breakdown separates the stem cells from the surrounding structural proteins without damaging the fragile cellular membranes. Premium laboratories heavily optimize these enzymatic protocols to maximize viability and ensure absolute sterility. Prior to cryopreservation, cells undergo aggressive screening for endotoxins and mycoplasma. Even with perfect isolation, patients face significant risks if they cannot distinguish between authentic living cells and heavily marketed biological alternatives.
Wharton’s jelly stem cells are considered highly safe when processed in regulated, sterile laboratory environments. Because they lack HLA-DR surface markers, these cells evade immune system detection. This significantly reduces the risk of immune rejection or Graft-Versus-Host Disease in allogeneic transfers. Safety ultimately depends on the clinic’s laboratory screening protocols, so always verify their infectious disease testing. Premium labs will happily provide this documentation upon request.
Collecting Wharton’s jelly is entirely painless and poses zero harm to the mother or the baby. The tissue is harvested from the umbilical cord strictly after a healthy birth has concluded and the cord has been severed. By preserving this medical waste, scientists ethically source potent mesenchymal stem cells without interfering with the birthing process.
Wharton’s jelly injections often refer to dead, acellular allograft products, whereas WJ-MSCs are living, replicating stem cells. Commercial allografts may provide temporary structural support or baseline growth factors. However, they completely lack the ability to proliferate or enact deep cellular immunomodulation inside your body. Authentic MSC therapy requires live cells that have been carefully isolated and verified for viability prior to administration. Always ask your clinician to strictly clarify exactly which biological product you are receiving.
For patients navigating regenerative medicine, Wharton’s jelly mesenchymal stem cells provide the highest cellular yield and lowest senescence ratio of any adult tissue source. By isolating these cells from the mucoid connective tissue of donated umbilical cords, researchers bypass the physical invasiveness and age-related biological degradation inherent to autologous bone marrow harvesting. The most effective clinical approaches leverage these living, immune-privileged cells under strict laboratory protocols.
Applying the Wharton’s Vitality Matrix reveals why modern clinical trials increasingly favor umbilical tissue over traditional sources. When cells replicate faster, live longer, and modulate the immune system without triggering allogeneic rejection, the biological foundation for pursuing interventions in complex orthopedic and autoimmune conditions becomes significantly stronger.
Determining if these living cell therapies align with your specific medical history requires professional clinical evaluation. Contact our medical team to initiate a complete stem-cell treatment suitability assessment based on your current diagnostics and functional goals.