Our Services
Others
- DFPP
- Shockwave
- IV Drip

For women facing a diagnosis of diminished ovarian reserve, the biological clock feels less like a metaphor and more like a strict deadline. Traditional IVF often hits a wall when viable eggs drop to critical levels, forcing many to consider donor eggs before they are ready. The prospect of closing the door on natural conception is devastating, leading many to search for experimental regenerative solutions.
By the end of this guide, you will understand exactly how stem cell therapy for ovarian rejuvenation operates at a biological level, so you can make safe, evidence-based decisions about your fertility journey. We will examine the clinical science, eligibility requirements, honest success rates, and actual procedural safety.
This article is for educational purposes only and does not replace consultation with a qualified medical professional.
Stem cell therapy for ovarian rejuvenation aims to restore fertility by utilizing mesenchymal stem cells to awaken dormant follicles in the ovaries, though it remains an investigational procedure.
Stem cell therapy for ovarian rejuvenation is an investigational medical procedure designed to restore reproductive function by injecting mesenchymal stem cells into the ovaries. Researchers at Stanford Medicine report that these cells secrete paracrine factors to reduce localized inflammation and stimulate blood vessel growth (Stanford Medicine, 2026). This improved microenvironment may help awaken dormant follicles in women facing fertility challenges.
To grasp the specifics of stem cells for fertility, we must first define the broader medical category. Ovarian rejuvenation serves as an umbrella term for various medical procedures aimed at restoring hormone production and egg retrieval capabilities in aging or failing ovaries.
The most common misconception surrounding what is ovarian rejuvenation involves the creation of new eggs. The scientific reality dictates that women are born with a finite number of eggs stored within their ovarian tissue. Throughout a woman’s life, these eggs deplete naturally. Ovarian rejuvenation cannot manufacture new eggs out of nothing. Instead, the procedure aims to awaken “dormant” or sleeping follicles that have stopped responding to the body’s natural hormones.
These dormant follicles represent a trapped potential. When standard In Vitro Fertilization (IVF) stimulation medications fail to prompt these follicles to grow, physicians look for ways to alter the local environment of the ovary itself. Stem cells for fertility represent the most advanced, experimental tier within this category of regenerative medicine.
Consider a scenario where a patient consistently produces only one or zero mature eggs during multiple IVF cycles despite receiving maximum medication doses. This patient might explore rejuvenation therapies to fundamentally improve how their ovarian tissue responds to stimulation. By attempting to heal the surrounding cellular environment, the goal is to coax out the few remaining viable eggs that standard protocols leave behind. Understanding this broad goal is only the first step; the specific cellular mechanics dictate potential success.
The core of this therapy relies on Mesenchymal Stem Cells (MSCs). Mesenchymal stem cells are a specialized type of adult stem cell found throughout the human body, most commonly harvested from bone marrow, adipose (fat) tissue, or umbilical cord tissue. Unlike embryonic stem cells, adult MSCs are utilized primarily for their regenerative and anti-inflammatory properties.
The biological mechanism of action is highly specific. When injected into the ovary, these cells do not magically transform into human eggs. Rather, they function as microscopic cellular factories. They secrete what scientists call “paracrine factors” a complex soup of chemical signals, proteins, and growth factors. These chemical signals communicate directly with the damaged or aging cells within the ovarian tissue.
These paracrine factors accomplish two critical tasks. First, they dramatically reduce localized tissue inflammation, which often inhibits healthy follicle development in older ovaries. Second, they stimulate angiogenesis, which is the growth of new, healthy blood vessels. Better blood flow means more nutrients and oxygen are delivered to the struggling, dormant follicles.
Think of a failing ovary like dry, depleted soil. Pumping it full of expensive IVF hormones is like throwing water on hard clay; it simply runs off without absorbing. The stem cells act as a vital nutrient infusion that conditions the soil, softening it and restoring its nutrient network so the existing seeds (dormant follicles) can finally grow. This robust tissue regeneration mechanism is precisely what separates stem cell therapy from older interventions.
Before stem cells gained prominence in fertility research, Platelet-Rich Plasma (PRP) was the primary regenerative option. PRP is a process that isolates platelets from a patient’s own blood and injects those concentrated platelets directly into the ovaries to deliver localized growth factors.
While both treatments aim to improve the ovarian microenvironment, they operate on entirely different biological timelines and depths. According to clinical comparisons published in Nature Scientific Reports, PRP provides a relatively short-term burst of localized growth factors. The platelets release their proteins quickly, offering a temporary spike in ovarian support. Stem cells, however, offer a deeper, more sustained structural tissue regeneration potential.
Mesenchymal stem cells can actively adapt to the specific inflammatory environment they encounter within the ovary. Once injected, they survive in the tissue for an extended period, continuing to secrete repair factors and continuously modulating the immune response over weeks or months. PRP is a static dose of proteins, whereas stem cells behave as dynamic, living therapeutic agents.
Because of this profound difference in capability, the clinical applications diverge. A patient might try PRP for a mild, temporary boost before an IVF cycle. However, severe ovarian aging, intense tissue scarring, or significant premature failure might require the deep structural regeneration targeted by stem cell therapy.
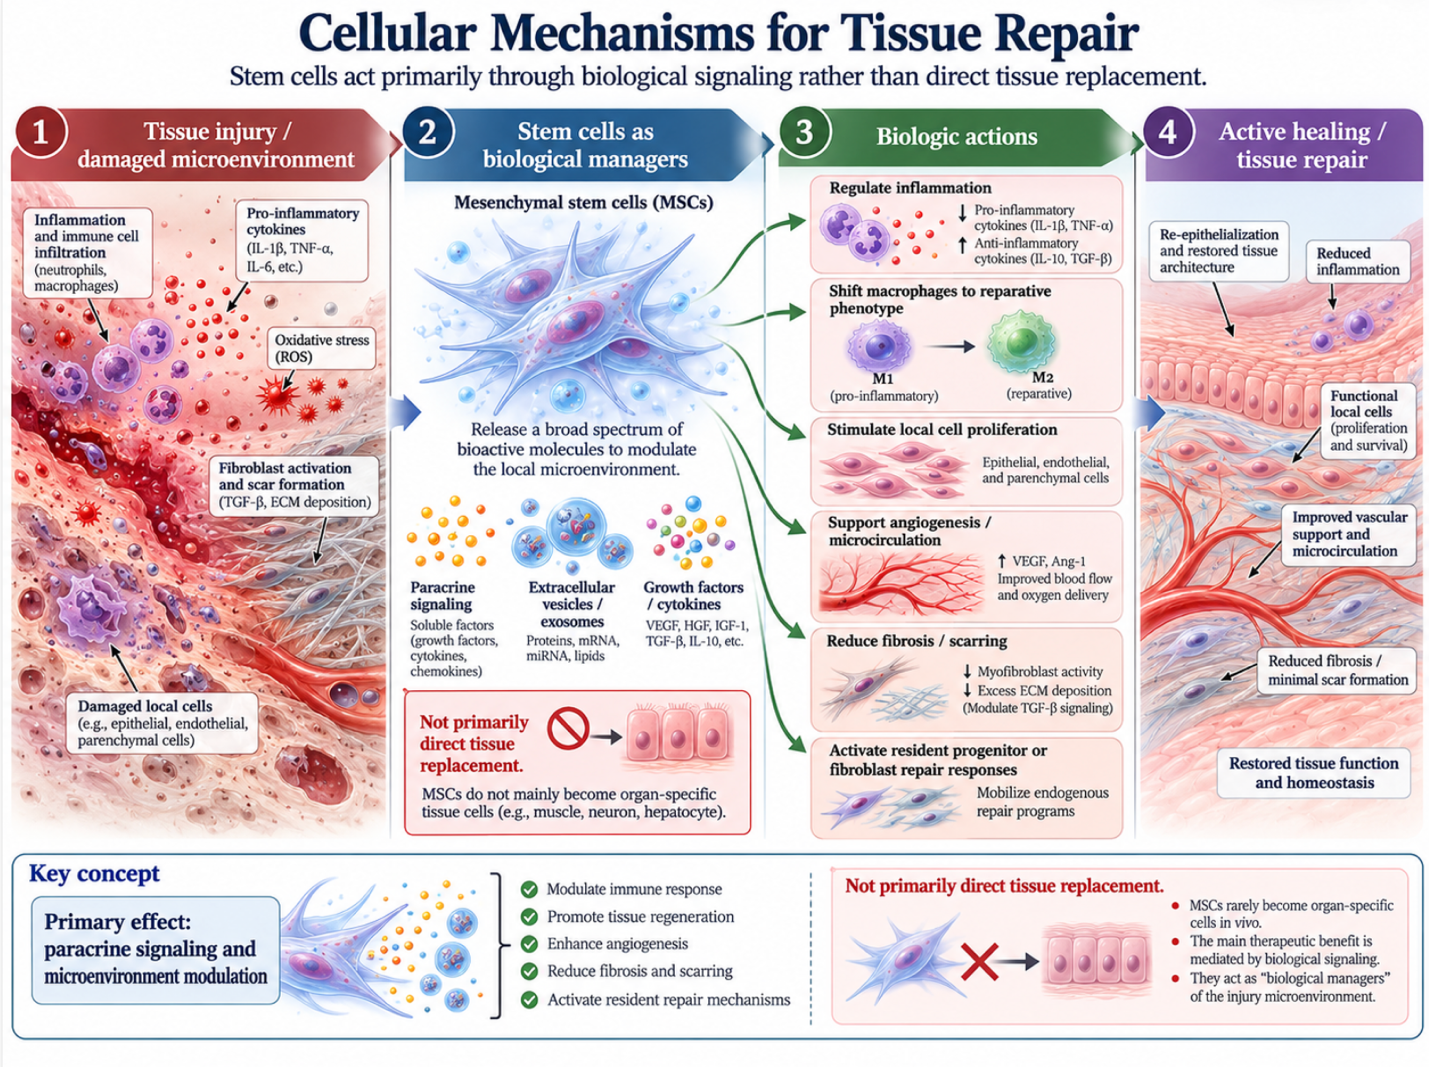
Figure 1: Stem cells provide dynamic, ongoing tissue repair compared to the static protein delivery of PRP injections.
Because these treatments operate differently at the cellular level, they are not universally effective. Identifying the ideal candidate based on exact medical diagnosis is the most critical step.
Determining who is a candidate for ovarian rejuvenation depends entirely on clinical diagnosis rather than age alone. Medical experts emphasize that because women with diminished ovarian reserve have critically low numbers of viable eggs, standard IVF treatments often fail (Johns Hopkins Medicine, 2026). Consequently, clinical trials currently restrict stem cell therapies to specific pathological diagnoses rather than general age-related infertility.
Diminished Ovarian Reserve (DOR) is a medical diagnosis indicating that a woman has a significantly lower number of eggs than expected for her age. Standard IVF relies heavily on high egg yields. The process assumes a doctor can retrieve ten to fifteen eggs, fertilize them all, and rely on statistical attrition to result in one or two genetically normal embryos.
Because DOR patients start with very few follicles, they struggle profoundly with standard IVF protocols. High doses of stimulation medications often fail to recruit more than one or two eggs, making the expensive IVF process statistically heartbreaking. Clinical realities detailed by Johns Hopkins Medicine demonstrate that because these women have critically low numbers of viable eggs, standard treatments may fail, driving the urgent need for regenerative research.
For patients using stem cells for diminished ovarian reserve, the therapeutic goal is highly targeted. The stem cells aim to rescue the few remaining dormant follicles to improve the yield in a subsequent IVF cycle. The treatment is rarely intended to guarantee a spontaneous natural pregnancy, though this occasionally occurs.
Managing expectations for DOR patients is paramount. A DOR patient should never expect stem cell therapy to jump their retrieval numbers from one egg to fifteen. A highly successful functional outcome for a DOR patient might be retrieving three to four healthy eggs instead of one, providing just enough embryos to achieve a healthy pregnancy. While DOR involves a low egg count, Premature Ovarian Failure represents an even more severe clinical challenge.
Premature Ovarian Failure (POF), also known formally in the medical community as Premature Ovarian Insufficiency (POI), is defined by the loss of normal ovarian function before the age of 40. Women with POF experience a cessation of regular menstrual cycles, plummeting estrogen levels, and a near-total absence of responding follicles years or decades earlier than natural menopause.
Because of the severity of this diagnosis, women with POF are the primary candidates for ongoing, rigorous clinical trials. Multiple active studies listed on ClinicalTrials.gov confirm that researchers are actively recruiting women specifically with POI to test the efficacy of autologous (self-donated) mesenchymal stem cell injections.
The emotional vulnerability associated with POF cannot be overstated. These patients are frequently told by primary care physicians that donor eggs are their singular, non-negotiable option for family building. This devastating news makes POF patients highly susceptible to aggressive marketing from commercial clinics promising miraculous cures through ovarian rejuvenation for POF.
Patients with POF must approach stem cell therapy as a strict, investigational Hail Mary. The clinical objective is to attempt to briefly restore hormonal function and ovarian micro-environments just long enough to retrieve a single biological egg. It is a highly experimental pathway that requires intense medical supervision and significant financial investment.
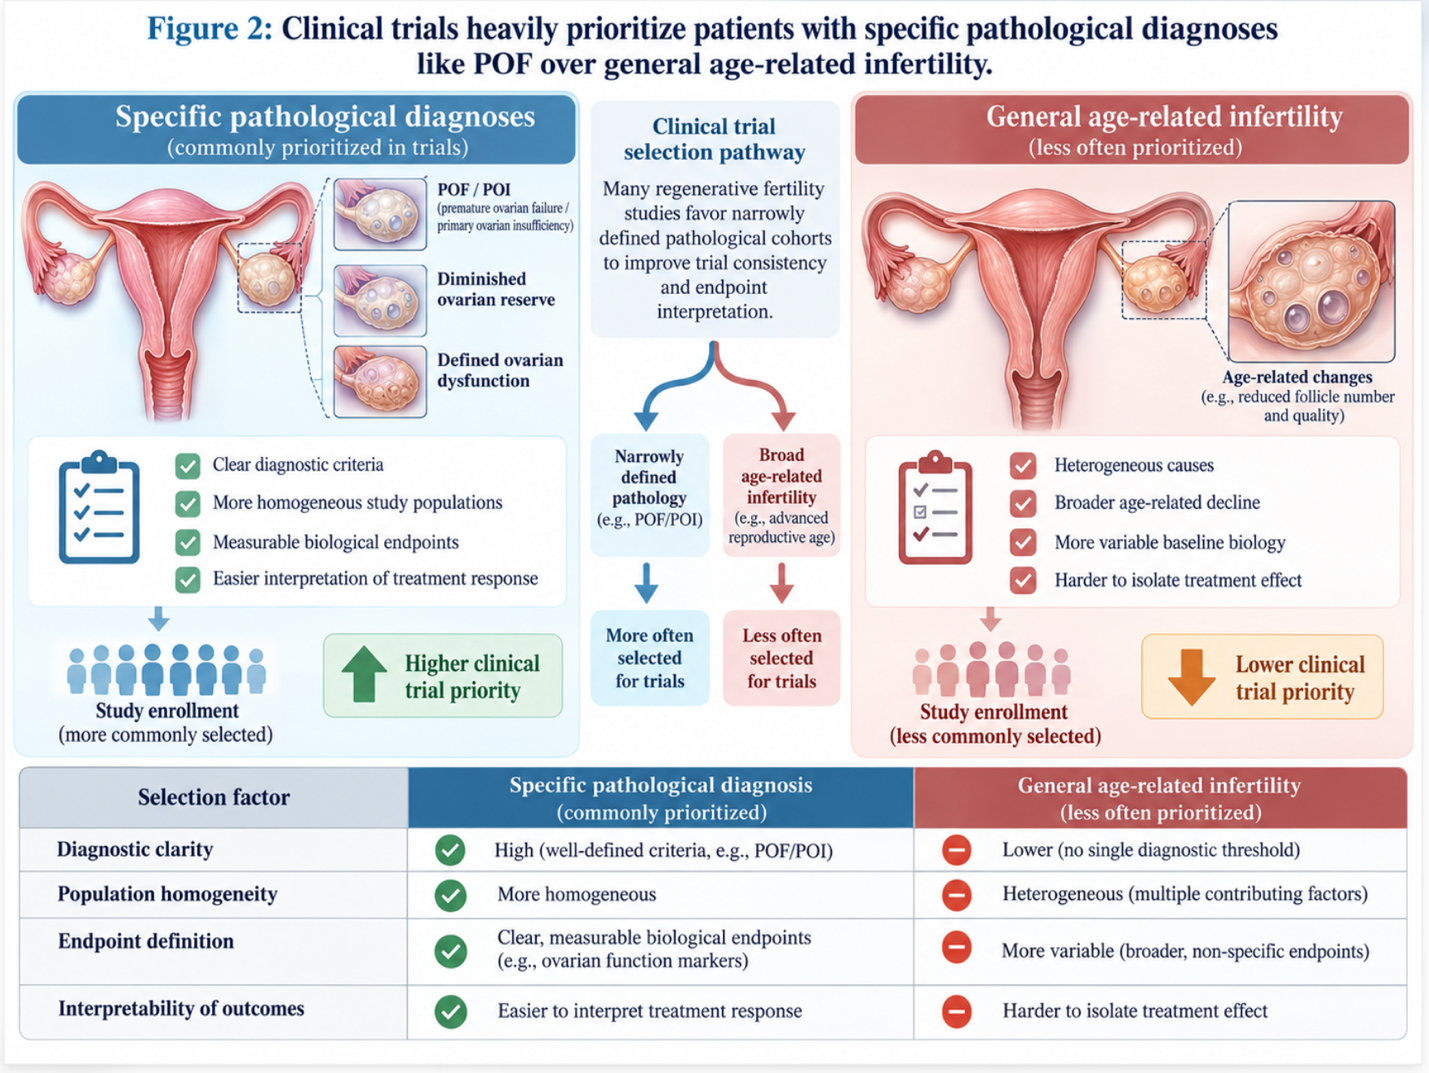
Figure 2: Clinical trials heavily prioritize patients with specific pathological diagnoses like POF over general age-related infertility.
The discussion of POF naturally leads to the most common question surrounding severe age-related infertility: the concept of reversing menopause.
A pervasive and dangerous myth surrounding regenerative medicine is the concept of menopause reversal. To be unequivocally clear: stem cell therapy menopause treatments cannot permanently reverse natural menopause or stop the biological clock.
Medical science delineates a stark difference between natural, age-appropriate menopause and early menopause caused by pathological conditions like POF. Natural menopause occurs when the ovarian reserve is completely and permanently depleted the biological vault is entirely empty. In cases of natural menopause, stem cells have no dormant follicles left to awaken.
While some experimental therapies have shown a temporary resumption of menses (menstrual periods) or short-term hormonal improvements in post-menopausal women, this does not equal viable fertility. A temporary spike in estrogen or a resumed period does not mean the patient has healthy, genetically normal eggs capable of resulting in a live birth.
Any commercial clinic promising to permanently reverse menopause using stem cell therapy is operating far outside the bounds of established medical science. This critical distinction between a temporary hormonal shift and a successful pregnancy forms the basis of how patients must evaluate the clinical data presented by fertility centers.
When patients ask, “does ovarian rejuvenation work?“, the answer depends heavily on how success is measured. A 2026 systematic review concluded that while mesenchymal stem cells show promise in awakening dormant follicles, human live birth success rates remain largely experimental (PubMed, 2026). Patients must evaluate these therapies through rigorous, peer-reviewed data rather than marketing claims.
Because stem cell ovarian rejuvenation is an investigational procedure, there is no universally accepted stem cell ovarian rejuvenation success rate. The medical community lacks decades of massive, multi-center, double-blind randomized controlled trials required to establish a standard-of-care statistical baseline.
Many commercial clinics proudly tout high success rates on their websites, claiming a “70% improvement” or “high success.” However, these figures almost universally represent small, uncontrolled patient groups. Furthermore, the definition of “improvement” in these marketing materials is frequently obscured.
A generalized patient outcome in current clinical trials reveals a nuanced reality. A specific subset of women may experience resumed menstrual cycles or improved hormone profiles (lowered FSH, higher AMH) for a window of three to six months following the injection. However, only a significantly smaller fraction of those women go on to achieve a natural pregnancy or a successful IVF retrieval directly attributable to the therapy.
Patients must aggressively question the data presented to them. Readers should explicitly ask clinics for data specifically on live birth rates for women in their exact age and diagnosis bracket. General “pregnancy success stories” can be misleading, as pregnancies in advanced maternal age or severe DOR profiles often end in early miscarriage. To truly understand these statistics, patients must learn how to separate cellular changes from actual babies.
To navigate the confusing landscape of clinical data, patients should apply The Functional vs. Biological Fertility Framework. This framework is a critical evaluative tool designed to help patients interpret clinical claims by strictly separating biological improvements from functional benefits.
Biological Improvements are laboratory results. These include lowered Follicle Stimulating Hormone (FSH), increased Anti-Mullerian Hormone (AMH), or the temporary resumption of menstrual bleeding. Commercial clinics heavily rely on these metrics. If a stem cell injection causes a patient’s FSH to drop from an unhealthy 40 to a healthier 15, the clinic legally labels the procedure a “biological success.”
Functional Benefits, however, represent the actual goal of the fertility patient. A functional benefit is the retrieval of genetically normal eggs, the achievement of a viable clinical pregnancy, and ultimately, the delivery of a healthy baby. A lowered FSH number is meaningless to a patient if it does not result in a child.
If a clinic boasts a 60% success rate based purely on biological improvements, but only a 5% success rate regarding functional benefits (live births), the patient must carefully weigh the high financial cost against the functional reality. The Functional vs. Biological Fertility Framework protects vulnerable patients from investing thousands of dollars into a treatment that only provides a temporary better blood test result. This framework provides the exact lens needed to interpret the data coming out of ongoing scientific research.
The hard scientific data surrounding this therapy is highly promising in laboratory settings but complex in human application. Data from the National Center for Biotechnology Information confirms that stem cell therapy can successfully restore estrogen levels and promote follicular development in animal models. However, widespread, reliable human application remains under intensive study.
Furthermore, systematic reviews published via PubMed emphasize a critical divide. Mesenchymal stem cells definitively show promise in altering the ovarian microenvironment and awakening dormant follicles. Yet, human live birth success rates remain largely experimental, with high variance based on the patient’s individual immune response.
The theoretical science is sound, and animal models demonstrate remarkable regenerative capabilities. But human ovaries present incredibly complex immunological environments that medical science is still mastering. Translating a successful mouse study into a successful human pregnancy requires years of careful protocol refinement.
Patients must contrast this cautious medical reality with the aggressive marketing of ovarian rejuvenation pregnancy success stories seen on social media platforms. Anecdotal success stories do not equal scientific consensus. Trusting peer-reviewed data over social media testimonials ensures patients make decisions based on reality.
Transparent risk assessment is a mandatory component of evaluating investigational medicine. The immediate side effects of ovarian stem cell therapy are generally mild but require monitoring. Short-term effects include mild pelvic cramping, localized pelvic pain, light vaginal spotting, and distinct soreness at the harvesting site (whether the hip or the abdomen).
Patients must also recognize the slight risk of infection or internal bleeding inherent to any needle-based surgical procedure. Puncturing the vaginal wall and the ovarian capsule always carries a baseline risk of introducing bacteria, which is why prophylactic antibiotics are often prescribed.
The long-term unknowns present a more complex challenge. Because this therapy is investigational, decade-long longitudinal studies regarding permanent ovarian tissue changes or potential cancer risks are still pending. Stem cells promote cellular growth and blood vessel formation; ensuring they do not inadvertently stimulate abnormal cellular growth over a ten-year period is a primary focus of ongoing safety trials.
The U.S. Food and Drug Administration strictly warns against unregulated commercial clinics offering stem cell therapies without an approved IND application. The FDA cites severe risks associated with unapproved treatments, including dangerous site reactions, severe infections, or unregulated cellular multiplication. Ensuring you are treated at an FDA-compliant clinic is paramount, which leads to the complex landscape of finding and affording a reputable provider.
Stem cell therapy for ovaries works by injecting regenerative cells directly into the ovarian tissue to improve the local microenvironment. These cells secrete specialized proteins and paracrine factors that reduce inflammation and stimulate new blood vessel formation. This increased blood flow delivers vital nutrients to the damaged tissue, conditioning the ovary for better function. In clinical trials, this specific biological process has shown the ability to awaken dormant follicles in women with diminished ovarian reserve. However, functional results vary significantly based on the patient’s exact diagnosis and cellular response.
Stem cells cannot create new eggs from scratch within the human ovary. Women are born with a finite, predetermined number of eggs that naturally deplete throughout their lifetime. The therapeutic goal of stem cell injection is strictly to awaken and support existing dormant follicles that have stopped responding to natural hormones. Stem cells act as a repair mechanism for the surrounding tissue rather than a manufacturing center for new genetic material.
Stem cell therapy for premature ovarian failure is currently the primary focus of multiple high-level clinical trials. Because patients with POF lose ovarian function before age 40, they represent the ideal pathological candidates for testing regenerative interventions. However, the treatment remains strictly investigational and is not yet considered a standard-of-care medical cure. Patients with POF should only pursue this therapy within the safety parameters of an FDA-monitored clinical trial.
Health insurance does not cover ovarian rejuvenation because the procedure is universally classified as experimental and investigational by regulatory bodies. Patients must prepare to pay entirely out of pocket for the consultation, harvesting, processing, and injection phases. These out-of-pocket expenses typically range from $5,000 to $15,000 or more in the United States. This financial burden is completely separate from the costs of any subsequent IVF cycles required to retrieve the eggs.
For women facing diminished ovarian reserve, stem cell therapy for ovarian rejuvenation offers an investigational approach to awakening dormant follicles. While systematic reviews from 2026 show promise for biological improvements in the ovarian microenvironment, live birth rates remain largely experimental. The safest approach combines consulting a board-certified reproductive endocrinologist, insisting on FDA-compliant clinical trials, and maintaining highly realistic expectations regarding actual pregnancy outcomes.
When evaluating your options, rely heavily on The Functional vs. Biological Fertility Framework. True clinical success is measured by healthy pregnancies and live births, not just temporary hormone spikes or resumed periods. Applying this framework protects you from misleading clinic marketing and ensures your financial and emotional investments are grounded in functional medical reality.
As a clear next step, gather your complete medical records, including your most recent hormone panels for FSH and AMH, and previous IVF stimulation records. Schedule a second-opinion consultation with a verified, board-certified fertility specialist at a university-affiliated research hospital to determine if your specific diagnosis makes you a viable candidate for ongoing clinical trials.