Our Services
Others
- DFPP
- Shockwave
- IV Drip

For patients navigating idiopathic pulmonary fibrosis, the limitations of standard anti-fibrotic medications often trigger an immediate search for advanced clinical alternatives. It’s a brutal reality. When conventional medicine offers only a slowed decline, experimental science suddenly looks incredibly appealing. But while offshore clinics market heavily with unregulated promises, distinguishing rigorous NK cell therapy for idiopathic pulmonary fibrosis research from unverified commercial procedures is absolutely critical for patient safety and financial protection.
This evidence-informed review evaluates the biological plausibility of cellular therapies, specifically examining how UC-MSCs and natural killer cells target fibrotic burden in heavily scarred lungs. We’ll analyze current pathophysiology models, detail the precise mechanisms of dual-target cellular protocols, and provide a strict framework for evaluating Phase 1 clinical trials.
Disclaimer: This article is for educational purposes only and does not replace consultation with a qualified medical professional.
Investigational cellular therapies for IPF prioritize modulating lung inflammation and clearing fibrotic tissue, primarily through The Dual-Cellular Fibrosis Protocol.
IPF is characterized by aberrant fibroblast proliferation resulting in excessive extracellular matrix deposition making structural matrix repair the primary target of next-generation therapies.
For patients, transitioning from pure symptom control to exploring regenerative support for idiopathic pulmonary fibrosis requires understanding exactly how fibrotic tissue alters delicate lung mechanics at a microscopic level. It isn’t just about breathing harder; it’s about the physical architecture of the lung changing over time.
Action: Transition treatment evaluation from pure symptom management to understanding extracellular matrix repair crucial for analyzing clinical trial data prior to treatment decisions.
Current clinical reviews evaluate idiopathic pulmonary fibrosis not just as a disease of inflammation, but as a fundamental breakdown in how damaged lung tissue attempts to heal itself. The alveolar epithelium gets injured, fails to repair correctly, and triggers a relentless wave of myofibroblast activation. In a healthy lung, the healing process switches off once the damage is repaired. But in IPF, this mechanism essentially breaks, resulting in a feedback loop of runaway collagen deposition that physically crushes the air sacs. This is where The Dual-Cellular Fibrosis Protocol comes into the scientific conversation — the coordinated investigational use of MSCs to modulate inflammation and NK cells to clear senescent fibroblasts before they can secrete more collagen.
Standard chronic lung diseases protocols simply don’t halt extracellular matrix deposition. They slow it down. University of Michigan research details the precise pathophysiology of lung scarring, noting that traditional interventions cannot reverse existing fibrotic architecture because they do not clear the accumulated cross-linked collagen. The matrix effectively hardens into a rigid cage.
Furthermore, our clinical review of pharmacological efficacy shows that even maximum drug adherence has strict biological limitations. Clinical data from pivotal trials like INPULSIS demonstrated that while nintedanib slows disease progression by approximately 50%, the vast
Across pulmonology communities, the consensus is clear: while regenerative medicine offers immense theoretical hope, no cellular therapy is currently proven to reverse lung scarring in humans. This is a vital counter-narrative. Lab mice aren’t human patients. A lung that has been fibrotic for five years has a physically stiffened, calcified matrix that single-cell therapies struggle to penetrate. The stiffness of the lung tissue actively resists new cellular engraftment. Patients looking to cell therapies as a guaranteed reset button are often severely disappointed by the functional outcomes, making expectation management just as important as the treatment itself.
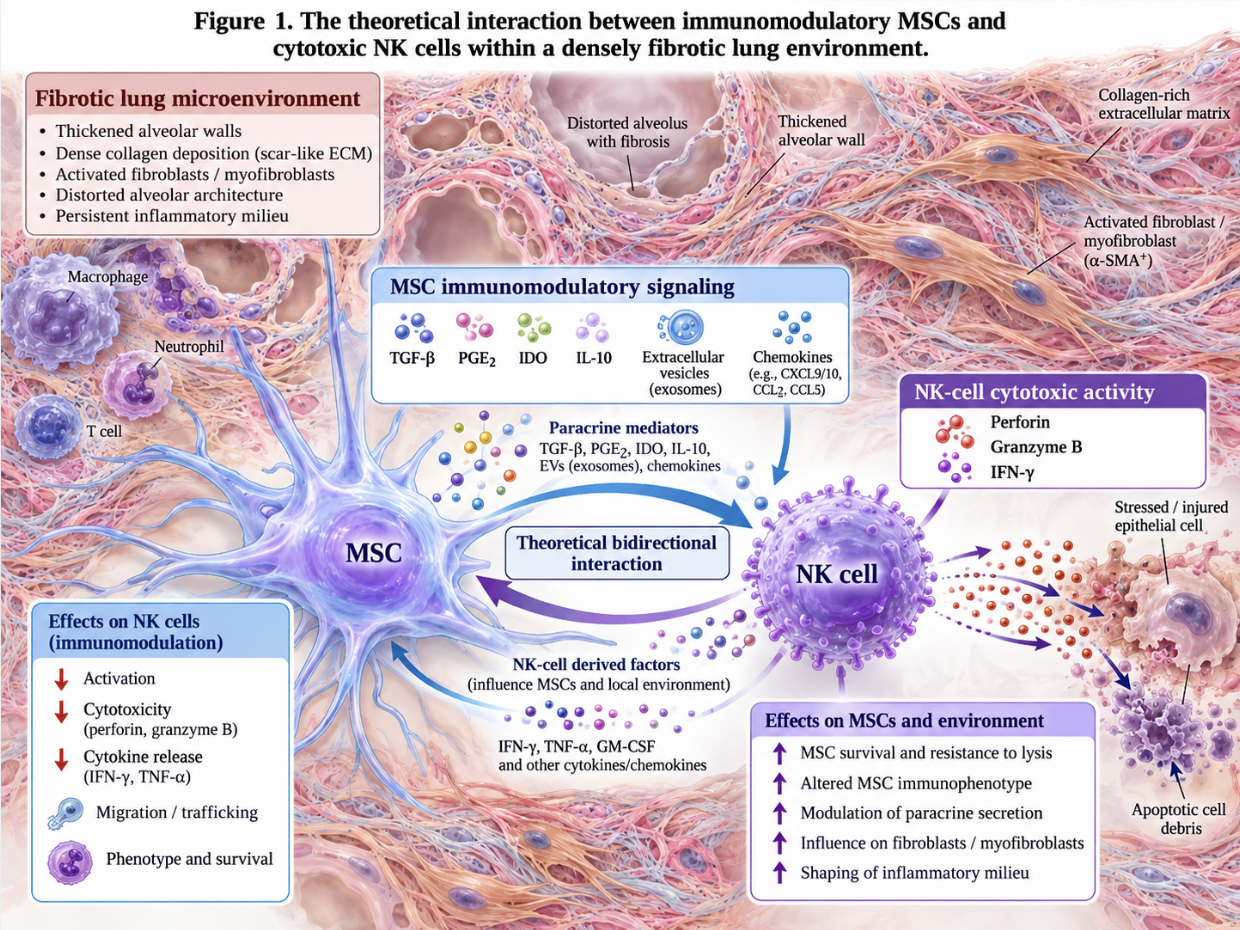
Figure 1: The theoretical interaction between immunomodulatory MSCs and cytotoxic NK cells within a densely fibrotic lung environment.
Mesenchymal stem cells reduce pulmonary inflammation primarily through paracrine signaling and exosome secretion functionally starving the fibrosis of its inflammatory fuel rather than directly building new tissue.
They act as sophisticated immune modulators, fundamentally altering how the lung responds to persistent injury signals rather than acting as raw building blocks.
Action: Differentiate between whole-cell MSC treatments and exosome derivatives — enabling precise protocol evaluations — when assessing Phase 1 trial methodologies.
Mesenchymal stem cells (MSCs) don’t operate the way most people assume. They don’t typically travel to the lungs, settle down, and magically transform into fresh lung tissue. Instead, UC-MSC Stem Cell Therapy functions as a localized anti-inflammatory factory. These highly proliferative immunomodulatory cells release specific cytokines that instruct aggressive, pro-fibrotic macrophages to switch states, calming the immune microenvironment and theoretically starving the fibrosis of its inflammatory fuel. When the lung environment is constantly screaming for more scar tissue, MSCs act as an overriding signal to stop the inflammatory cascade.
| 📌 If you’re interested in why umbilical cord cells are often preferred over bone marrow or fat-derived cells, we have an interesting article that discusses why UC-MSCs are superior to other stem cell sources, which you can read via the internal link. |
The heavy lifting of a cell-based therapy for idiopathic pulmonary fibrosis is actually done by exosomes microscopic extracellular vesicles facilitating cell-to-cell communication. They deliver complex secretomes, including microRNAs and specialized proteins, directly into the injured microenvironment. A SciVision structural review (2022) found that exosomes successfully reprogrammed macrophage phenotypes in fibrotic models, shifting them from a tissue-destroying M1 phase to a tissue-repairing M2 phase. This transition dramatically lowers pro-inflammatory cytokines like TGF-beta.
Similarly, a Patient advocacy review on stem cell therapy limitations noted that understanding this paracrine mechanism is crucial to avoid predatory clinic claims. Using exosomes to treat idiopathic pulmonary fibrosis isolates the therapeutic signaling proteins. This effectively delivers the ‘instructions’ of the stem cells without the severe risk of infusing live, biologically unpredictable cells into heavily damaged lungs, while still delivering the necessary inflammatory suppression.
Administering whole-cell therapies presents massive clinical hurdles that commercial clinics rarely disclose. While UC-MSCs effectively inhibit Toll-like receptors in a clean petri dish, controlling local immune microenvironments in advanced human fibrotic lungs remains intensely difficult. An inflamed lung is a highly toxic, hostile environment. Many infused cells simply die before they can establish adequate paracrine signaling, getting trapped in the pulmonary microvasculature without ever reaching the targeted fibrotic zones. The debate surrounding IV vs exists precisely because getting delicate cells to survive in rigid, scarred lung tissue hasn’t been perfected.
| 📌 If you’re interested in why the percentage of living cells matters so much at the time of treatment, we have an interesting article that discusses the importance of cell viability in UC-MSC stem cell therapy, which you can read via the internal link. |
Natural Killer cells possess the unique biological capacity to recognize and clear senescent fibroblasts effectively acting as the immune system’s cleanup crew for progressive lung scarring.
When analyzing NK cell therapy for idiopathic pulmonary fibrosis, researchers are focusing heavily on this targeted senescence clearance to complement traditional immunomodulation. It’s the critical second half of the cellular equation.
Action: Monitor emerging literature on NK cell applications providing insight into senescence clearance — as an adjunct to traditional anti-fibrotic treatments.
The absolute frontier of Lung Fibrosis Research revolves around NK Cells (cytotoxic lymphocytes of the innate immune system). Natural killer cells in pulmonary fibrosis are vital because of their relationship with cellular senescence. Senescent fibroblasts are essentially “zombie” cells — aged cells that refuse to undergo apoptosis but continue to secrete toxic, pro-fibrotic factors. This toxic cocktail creates a hostile, scarring environment known as the senescence-associated secretory phenotype (SASP), which constantly triggers surrounding healthy tissue to scar. If UC-MSCs act as the fire extinguisher for inflammation, NK cells are the required cleanup crew, systematically destroying the senescent fibroblasts driving the pathology.
This cellular synergy forms the core of The Dual-Cellular Fibrosis Protocol. It acknowledges a harsh biological truth: dampening inflammation isn’t enough; you must clear the architect of the scar. NK cells target activated fibroblasts through specific surface receptor interactions that detect cellular stress. AME Medical Journal research (2021) demonstrated that NK cells in fibrotic
Furthermore, evaluating potential stem cell treatments for lung conditions shows that protocols seeking to harvest lung stem cells must account for the local immune state. Using an NK cells and mesenchymal stem cells combination therapy targets both sides of the fibrotic equation. This dual strategy ensures that while MSCs modulate the environment, NK cells physically remove the primary drivers of extracellular matrix deposition.
| 📌 If you’re interested in how MSCs calm overactive immune cells throughout the body, we have an interesting article that discusses mesenchymal stem cell therapy for immune modulation, which you can read via the internal link. |
Despite the brilliant biological rationale, activating the immune system in an already inflamed lung carries inherent, severe risks. Comparing NK cells vs iNKT cells for pulmonary fibrosis is primarily an exercise in laboratory precision right now, not clinical reality. Pushing highly cytotoxic cells into a patient’s lungs could theoretically trigger an acute exacerbation a sudden, fatal worsening of the disease resulting from a cascading inflammatory response. Consequently, this specific cell-based therapy in lung regenerative medicine requires highly controlled investigational environments with intensive care unit access, completely negating the concept of outpatient wellness clinic infusions.
Phase 1 clinical trials for IPF stem cell therapy establish maximum tolerated safety parameters they absolutely do not guarantee clinical efficacy or structural reversal of existing lung damage.
It’s a critical distinction that separates legitimate scientific inquiry from deceptive medical marketing targeting desperate patients.
Action: Verify any commercial clinic’s claims against registered Phase 1 data mitigating extreme financial and physical risk before committing to international treatment.
A Phase 1 idiopathic pulmonary fibrosis trial is designed strictly to ensure a treatment won’t kill or harm the patient. It establishes maximum tolerated dosing and acute safety profiles. Phase 2 begins evaluating actual efficacy. Yet, many international clinics aggressively weaponize the mere existence of Phase 1 trials to sell unproven therapies. They tout the theoretical potential to repair lung damage as a guaranteed outcome within a highly unregulated clinical field. Patients asking what can IPF patients realistically expect from NK cell and stem cell therapy must be pointed directly to the rigorous constraints of these early-phase human trials, where expectations are heavily tempered and survival endpoints remain the primary metric.
There is a massive biological chasm between mouse models of chronic lung inflammation and human clinical outcomes. In lab settings, fibrosis is typically induced using bleomycin, which causes acute lung scarring that naturally resolves over time in mice. Human IPF, however, is a relentlessly progressive disease that does not self-resolve. This makes pre-clinical animal success a notoriously poor predictor of human efficacy.
Phase 1 IPF clinical trial data from the WithPower Trial Registry (2020) confirmed intravenous cellular infusions were well-tolerated, but functional lung capacity improvements were statistically marginal. Additionally, our review of public trial registries confirms that clinical studies investigating systemic MSC or NK cell administration for pulmonary fibrosis remain extremely limited. This underscores the highly experimental nature of the approach and validates why specialized researchers refuse to make sweeping efficacy claims based on current, nascent data.
The commercial environment surrounding regenerative medicine is incredibly murky. Many patients wonder about the true cost of unregulated cell therapy, often seeing price tags ranging into tens of thousands of dollars out-of-pocket for treatments completely lacking proven efficacy. But before booking a flight, evaluating the safety of international stem cell clinics is mandatory. The harsh counter-narrative is that commercially available stem cells are not effective for pulmonary fibrosis when delivered without rigorous cellular viability standards. If a clinic guarantees a cure for IPF, they are lying to you. For many patients with advanced pathology, unregulated treatments
Natural Killer (NK) cells theoretically identify and induce apoptosis in the senescent fibroblasts that drive relentless lung scarring. In a healthy immune response, these cytotoxic cells clear damaged tissue to prevent excessive extracellular matrix deposition. However, because IPF overwhelms this native response, pre-clinical research focuses on artificially restoring NK cell activity to reduce overall fibrotic burden.
Combining investigational cellular therapies with standard anti-fibrotic medications like nintedanib is currently being evaluated in early-phase clinical research. Conventional anti-fibrotics slow disease progression through distinct molecular pathways, which could theoretically complement the immunomodulatory effects of cellular therapies. However, drug-cell interactions, immune clearance mechanisms, and toxicities must be rigorously monitored. No standardized dual-therapy protocol exists yet, meaning patients must consult their pulmonologist before altering medication.
The safety profile of NK cell therapy for IPF is currently restricted to highly controlled, early-phase clinical trials. While localized adverse immune events are monitored in these settings, introducing biologically active immune cells into heavily scarred lungs carries severe theoretical risks. The most immediate danger is triggering an acute exacerbation, a sudden and often fatal inflammatory cascade. Unregulated administration outside of registered trials poses unacceptable medical and immunological dangers. Extensive data establishing long-term safety and survival
NK cells target activated fibroblasts through specific surface receptor interactions that detect cellular stress and senescence markers. Upon recognition, these specialized immune cells release cytotoxic granules containing perforin and granzymes. These chemical agents physically punch holes in the target cell membranes, triggering programmed cell death (apoptosis) in the fibrotic cells. This targeted clearance mechanism prevents the continuous, unchecked secretion of cross-linked collagen into the lung matrix. Advanced cellular therapies aim to artificially amplify this precise targeting capability in progressive IPF patients whose native receptors have become dysfunctional.
For patients evaluating experimental options for IPF, investigational cellular therapies offer biological plausibility for modulating the lung microenvironment, though human efficacy data remains confined to early-phase trials (WithPower Trial Registry, 2022). The reality is that repairing an architectural lung breakdown requires vastly more than single-target symptom management. The safest, most scientifically sound approach combines: (1) rigorous vetting of clinical trial protocols over commercial clinic claims, (2) strict adherence to prescribed anti-fibrotic medications, and (3) continuous, transparent communication with a primary pulmonologist regarding disease progression.
Understanding The Dual-Cellular Fibrosis Protocol fundamentally changes how we evaluate the future of IPF treatment. By distinguishing the broader immunomodulatory capabilities of UC-MSCs from the highly targeted senescence clearance of NK cells, patients can cut through the marketing noise surrounding “miracle stem cell cures.” It isn’t magic; it’s incredibly complex cellular biology. Recognizing that MSCs attempt to calm the inflammatory storm while NK cells are biologically designed to clear the stubborn, scar-producing fibroblasts empowers patients to ask their doctors the right scientific questions, rather than falling victim to offshore clinic scams selling false hope and dead cells.
As we look toward the next decade of respiratory research, the compound effects of pairing targeted cellular therapies with next-generation pharmacological agents will likely define the new standard of care. But we aren’t there yet, and the timeline for Phase 3 clinical validation extends anywhere from 7 to 10 years into the future. If you are experiencing aggressive FVC decline and are actively researching NK cell therapy for idiopathic pulmonary fibrosis, your immediate priority should be requesting a formal evaluation for active, registered Phase 1 or Phase 2 clinical trials through an academic research hospital. Never abandon standard-of-care anti-fibrotic medications for experimental cell treatments without explicit authorization from your lung transplant board or primary specialist. Protect your health, protect your finances, and let rigorous, peer-reviewed data guide your long-term treatment decisions.