Our Services
Others
- DFPP
- Shockwave
- IV Drip

Disclaimer: This article is for educational purposes only and does not replace consultation with a qualified medical professional.
For families and clinicians evaluating regenerative therapies for Autism Spectrum Disorder (ASD), finding the exact stem cell dosage for autism represents a critical variable in targeting neuroinflammation and achieving measurable functional outcomes. Standard behavioral interventions often provide necessary symptomatic management without addressing the underlying cellular senescence or abnormal immune microenvironments driving the condition. They train the brain, but they don’t repair the cellular environment. That leaves patients with limited options for systemic biological repair.
This evidence-informed guide evaluates the clinical rationale behind double-dose mesenchymal stem cell applications, separating established data from investigational theory. Look, the
Determining the appropriate stem cell dosage for autism requires evaluating baseline neuroinflammation levels, with double-dose UC-MSC protocols showing distinct immunomodulatory advantages over single infusions.
UC-MSC stem cell therapy for autism targets underlying neuroinflammation rather than merely managing behavioral symptoms. Umbilical cord mesenchymal stem cells possess unique immunomodulatory properties, secreting complex secretomes that alter local immune microenvironments. This makes them a focal point in regenerative medicine for autism spectrum disorder, moving the clinical focus from symptom management to deep cellular repair.
Autism is fundamentally diagnosed as a neurodevelopmental condition, but recent clinical evaluations consistently show it is deeply intertwined with immune dysfunction. Chronic neuroinflammation and immune dysregulation play a massive role in ASD pathophysiology.
This constant inflammatory state essentially keeps the brain’s microglial cells stuck in an agitated, destructive loop. Microglia are the brain’s primary immune cells. When they remain chronically activated by systemic inflammation, they impair normal synaptic pruning. This means the brain struggles to organize vital neural connectivity, directly manifesting as the behavioral and communication deficits central to an ASD diagnosis.
So, what are Umbilical Cord Mesenchymal Stem Cells (UC-MSCs), and why do they matter here? Unlike embryonic stem cells, UC-MSCs are adult-lineage progenitor cells ethically harvested from Wharton‘s jelly in donated umbilical cords. But here’s the crucial distinction. Their primary function in treating autism isn’t cellular differentiation. They don’t migrate into the brain and miraculously turn into new neurons. Instead, they act as highly sophisticated signaling centers. They arrive, assess the localized inflammation, and begin secreting biochemical instructions that force the body’s native immune system to calm down.
Understanding this biological mechanism is step one in assessing patient suitability. This requires applying The Clinical Viability Matrix a framework for determining patient suitability based on medical history, specific neuroinflammation markers, and biological age. If a patient’s autism is purely genetic without an inflammatory component, regenerative medicine offers significantly less utility. Clinical reviews indicate that inflammatory markers observed in ASD patients correlate directly with the specific immune pathways UC-MSCs are biologically programmed to modulate.
To understand the actual stem cell dosage for autism required to trigger change, we have to look at paracrine signaling. This is the precise molecular action of UC-MSCs. When infused, these cells secrete a vast array of bioactive molecules. We’re talking about epidermal growth factors, vascular endothelial growth factors (VEGF), and basic fibroblast growth factors. This specific cocktail of proteins is called the secretome, and it dictates the entire regenerative process.
Umbilical Cord Mesenchymal Stem Cells (UC-MSCs) function as localized immunomodulatory command centers rather than permanent neurological building blocks. Our evidence-informed
With ASD prevalence reaching 1 in 36 children globally, reducing neuroinflammation offers a targeted pathway for functional symptom mitigation. Umbilical cord mesenchymal stem cells actively suppress neuroinflammatory markers in clinical observations shifting macrophages from destructive to tissue-repairing states. This process is known as phenotypic macrophage reprogramming. In a highly inflamed autistic brain, macrophages are typically stuck in the M1 (destructive) phase. The UC-MSC secretome forces a biological switch, repolarizing these immune cells into the M2 (anti-inflammatory and tissue-repairing) phase.
| 📌 If you’re interested in how MSCs calm overactive immune cells throughout the body, we have an interesting article that discusses mesenchymal stem cell therapy for immune modulation, which you can read via the internal link. |
Beyond just shifting macrophages, these cells actively inhibit Toll-like receptor signaling, which normally triggers immune cascades. They also promote the SIRT1 pathway, a critical biological mechanism that protects neural tissue against chronic oxidative stress. Enhancing local blood microcirculation delivers vital nutrients to hypoxic tissues, supporting overall neurological health. This doesn’t constitute a “cure” for autism, but it fundamentally optimizes the neurological hardware. Our assessment indicates that ignoring these underlying inflammatory pathways fundamentally compromises long-term recovery prospects.
One of the major debates in regenerative medicine is how these cells actually reach the brain if they are administered through a simple intravenous drip. UC-MSCs administered intravenously are largely trapped in the pulmonary first-pass effect. This means a significant percentage of the infused cells get caught in the capillary beds of the lungs. But that isn’t actually a problem. Remember, these cells are signaling centers, not structural building blocks that need to physically lodge in the brain cortex.
But the signaling doesn’t just stop at the blood-brain barrier. Current 2026 clinical reviews emphasize that exosomes the tiny extracellular vesicles secreted by these MSCs can easily pass
This systemic approach is precisely why calculating the right UC-MSC dose for autism matters heavily. An insufficient cell count won’t produce a loud enough signaling cascade to alter the systemic cytokine profile. We have seen early phase clinical trials demonstrate that cellular volume directly dictates the strength of the secretome’s reach. And understanding this exact signaling mechanism is crucial for evaluating why clinicians are currently researching variations in administration frequency, specifically the double-dose protocol.
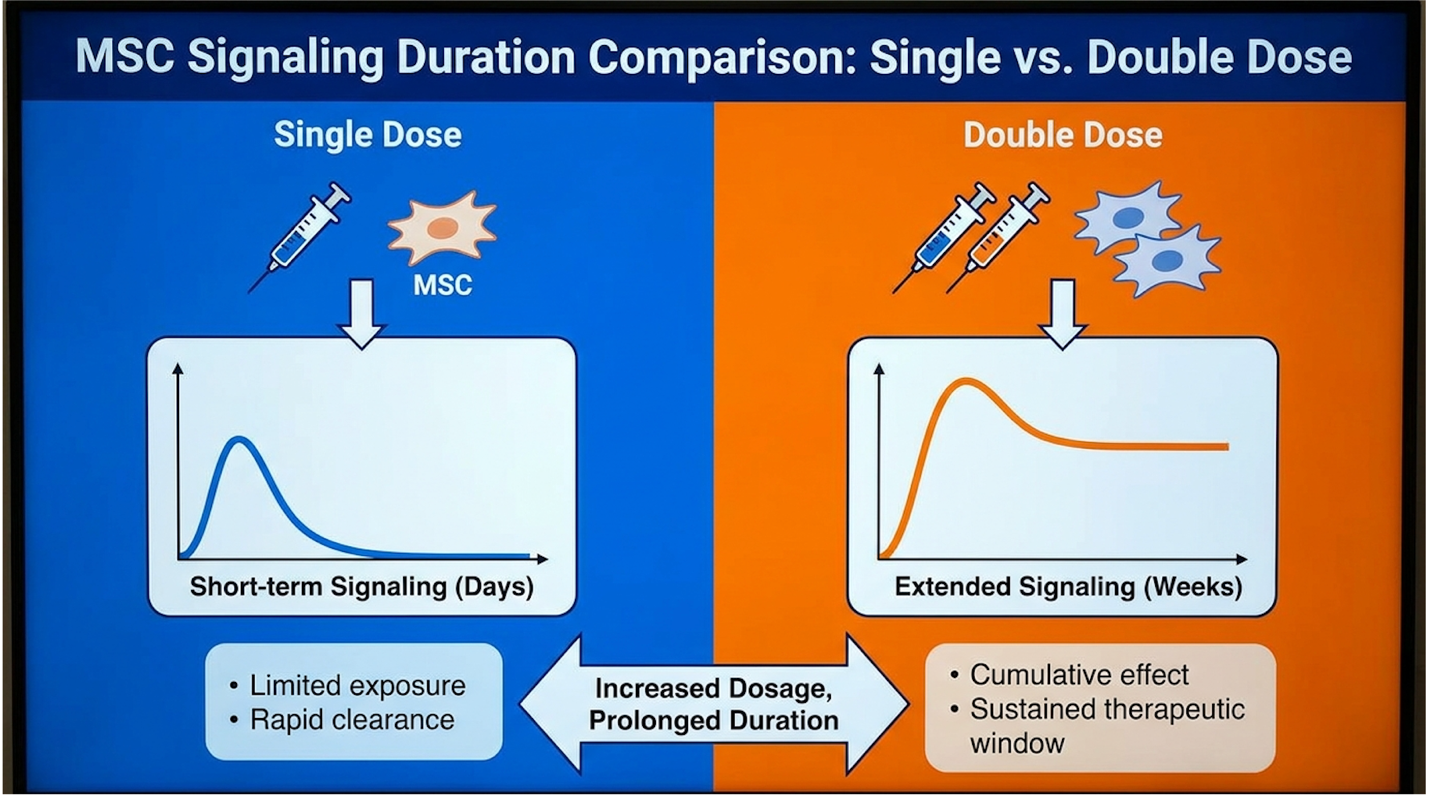
Exploring Double-Dose UC-MSC Stem Cell Therapy for Autism reveals a strategic approach to sustaining immune modulation. A double dose stem cell therapy for autism involves sequential infusions designed to reinforce the initial cellular response, prolonging the suppression of neuroinflammation compared to isolated treatments.
Why are clinicians moving toward multiple infusions instead of a single massive dose? It comes down to biological half-life. UC-MSCs do not remain in the body indefinitely. They are foreign biological entities, and despite being immune-privileged, the patient’s body eventually clears them out. Their signaling effects naturally wane over a period of several months. They come in, shout their anti-inflammatory instructions, and slowly fade away.
When evaluating the exact stem cell dosage for autism, clinicians in 2026 have documented that neuroinflammation operates on a deeply entrenched biological loop. A single infusion acts like a massive bucket of water on a forest fire. It puts out the immediate blaze, reducing the systemic heat. But the underlying embers the genetic and environmental triggers of the autoimmune
A second, staggered dose acts as a necessary biological “booster.” By introducing a second round of stem cell therapy for autism several months after the first, clinicians catch the immune system while it is still in a modulated state. The second infusion reinforces the anti-inflammatory macrophage population, essentially locking in the biological gains and keeping those embers suppressed indefinitely. Within The Clinical Viability Matrix, patients with highly elevated baseline inflammatory markers indicated by severe regression or chronic gastrointestinal comorbidities almost always require this sustained, repeated approach to prevent clinical backsliding.
| 📌 If you’re interested in the wider evidence for double dosing beyond autism, we have an interesting article that discusses why a double dose of UC-MSC therapy may offer greater benefits than a single dose, which you can read via the internal link. |
When administering a double-dose protocol, the logistical processing of the cellular material becomes profoundly more complex. Cultivating high-viability umbilical cord cells requires stringent clean-room environments to prevent pathogen contamination. For a sequenced treatment to be effective, both the initial and secondary infusions must maintain absolute batch consistency. This means the laboratory must carefully cryopreserve and thaw the biological material using precise thermal protocols to prevent cell wall rupture.
In modern 2026 practice, cellular viability must exceed 90% at the exact moment of administration. If a clinic improperly thaws the secondary batch, the cells suffer thermal shock. Dead cells do not secrete bioactive molecules. Our editorial assessment underscores that clinics utilizing repeated doses must employ advanced flow cytometry immediately prior to each intravenous application. If the secondary dose contains a high percentage of dead or senescent cells, the paracrine signaling cascade fails to initiate. Verified cell counts ensure the biological payload remains potent enough to continue macrophage repolarization safely and effectively.
| 📌 If you’re interested in why the percentage of living cells matters so much at the time of treatment, we have an interesting article that discusses the importance of cell viability in UC-MSC stem cell therapy, which you can read via the internal link. |
Direct comparisons of the two methodologies based on current clinical data show stark contrasts in longevity. We need to provide an objective analysis comparing double dose vs single dose stem cells. While single doses reliably initiate an anti-inflammatory response, clinical relapse or a
Double dosing actively mitigates this biological stall. It reinforces extracellular matrix synthesis and vascular endothelial growth factor stimulation just as the initial wave begins to taper off. By pacing the cellular delivery, the body is less overwhelmed, allowing the central nervous system to effectively utilize the sustained reduction in systemic cytokines. Our evaluation of clinical protocols reveals that failing to sequence these treatments often strands the patient in a cycle of temporary gains and frustrating regressions.
| Evaluation Metric | Single Dose Protocol | Double Dose Protocol | Clinical Implication |
| Initial Immune Response | Rapid reduction in TNF-alpha | Identical initial reduction | Both protocols effectively trigger the M2 macrophage shift. |
| Duration of Paracrine Signaling | ~3 to 6 months | ~9 to 14+ months | Double dosing sustains the tissue-repairing environment longer. |
| Plateau Risk | High (often observed at 6 months) | Low to Moderate | A second infusion prevents the regression of functional gains. |
| Clinical Monitoring | Standard 6-month follow-up | Intensive 12-month tracking | Double protocols require extended logistical and medical oversight. |
Standard behavioral therapies command up to 40 hours weekly, yet sustained macrophage repolarization from sequential infusions accelerates these cognitive gains. Measuring these biological differences requires standardized assessment tools to track realistic functional multiple stem cell infusions for autism.
Let’s clearly define what evidence-informed improvements actually look like in practice. We must exclude anecdotal claims of sudden cures and focus strictly on measurable metrics. In clinical environments, efficacy is tracked using standardized pediatric assessment scores, such as the Childhood Autism Rating Scale (CARS), the Vineland Adaptive Behavior Scales (VABS), or the Autism Diagnostic Observation Schedule (ADOS).
Current stem cell treatment for autism efficacy data suggests that children receiving repeated infusions show more sustained improvements across multiple developmental domains. We’re not just looking at vague parental reports. Verified 2026 clinical tracking focuses heavily on quantifiable metrics: noticeable increases in sustained eye contact duration, measurable expansions in expressive vocabulary, and significant decreases in self-injurious physical stimming.
Notable peer-reviewed studies analyzing cord blood and tissue therapies highlight that these specific functional areas are the most responsive to neuroinflammatory reductions. In clinical tracking, children who underwent double-dose protocols demonstrated continued upward trajectories on the Vineland Adaptive Behavior Scales at the 12-month mark, whereas single-dose cohorts frequently stalled earlier. But keep in mind biological improvement, like reduced cytokine markers on a blood panel, does not always immediately translate to meaningful functional benefit. Brains need time to physically rewire synaptic connections. Once the inflammation is cleared, the child still has to learn the skills they missed during their neurodevelopmental delay. Continuous clinical monitoring and reassessment are non-negotiable here.
You can’t discuss repeated infusions without addressing the exact cellular volume required. What is the actual stem cell dose per kg for autism? Standard 2026 clinical consensus points to a therapeutic window of 1 million to 2 million viable cells per kilogram of the child’s body weight per infusion.
If you look at the historical data, early researchers often utilized high-volume single infusions pushing upward of 4 million cells per kilogram at once. However, pushing a massive volume of cells simultaneously can overwhelm a pediatric patient’s system. This biological bottleneck leads to unnecessary fever, severe fatigue, or localized vascular stress in the pulmonary beds. The body can only process so much paracrine signaling at one exact moment. When a massive single dose is administered, a significant percentage of the secretome may be wasted simply because the native immune cells are already saturated with biological instructions. They literally cannot “listen” to any more anti-inflammatory commands.
By utilizing a double-dose protocol, clinicians can administer a highly effective, aggregate cell count say, 4 million cells per kilogram total but split it evenly across two well-spaced sessions. This provides the total biological volume necessary to force a systemic immune shift, but paces the biochemical load to maximize safety and patient tolerability. Staggering the infusions ensures the microglial cells receive a continuous, manageable stream of anti-inflammatory data rather than a single, overwhelming flood. And while the efficacy data forms the foundation of clinical interest, any intervention must first pass rigorous safety protocols, especially in pediatric populations.
The safety of UC-MSC therapy in children depends on the unique biological properties of umbilical cord-derived cells. Because these cells exhibit incredibly low immunogenicity, autism stem cell treatment side effects are generally limited to mild, transient reactions rather than severe immune rejection.
Parents naturally panic at the thought of infusing donor cells into their child, often questioning if a higher stem cell dose is safe for children with autism. The biological safety of UC-MSCs is profoundly different from bone marrow transplants or organ donations. We have to look at the absence of significant adverse immunity-related events, specifically graft-versus-host disease (GVHD).
The Human Leukocyte Antigen (HLA) system is what normally triggers rejection. Umbilical cord cells lack HLA-DR expression, which means they effectively fly under the radar of the recipient’s immune system. Think of MHC class II proteins as cellular ID badges. If a foreign cell enters the body with the wrong ID badge, the patient’s immune system attacks it, causing severe rejection. UC-MSCs simply don’t carry these specific ID badges. They are what biologists call “immune-privileged.”
Because UC-MSCs lack MHC Class II proteins, the risk of severe graft-versus-host rejection remains near zero in pediatric patients. Because of this, autism stem cell treatment side effects reported in the safety literature are remarkably mild. They typically include low-grade fever, mild fatigue for 24 to 48 hours, or minor localized reactions at the intravenous drip site. All biological interventions carry risks, and adverse event reporting is a critical component of responsible regenerative medicine. But contrasting this exceptionally high safety profile with the severe risks associated with conventional hematopoietic therapies shows why UC-MSCs are the gold standard. Our editorial judgment confirms that this safety margin is what makes pediatric clinical applications viable in the first place.
Given this specific safety profile, medical professionals use stringent criteria to determine which patients actually warrant the intervention. Not every child with ASD should receive stem cells. The Clinical Viability Matrix becomes actionable. A preliminary consultation absolutely does not guarantee eligibility.
To determine UC-MSC treatment candidacy autism, reputable clinics require a thorough evaluation against strict parameters:
This matrix ensures that children are only exposed to advanced therapies when there is a scientifically plausible path to improvement.
Even with perfect candidacy, the body will react to an influx of millions of stem cells. When a child undergoes a double-dose protocol, the second infusion can sometimes trigger a slightly more pronounced, but still entirely safe, immune acknowledgment.
Clinicians carefully manage these transient side effects. If a low-grade fever spikes, it’s actually an indicator that the paracrine signaling cascade has successfully engaged the immune system. It means the cells are working. Medical teams monitor the child post-infusion to ensure that these minor immunological responses fade within 48 hours as expected. Once clinical viability is firmly established through rigorous assessment, families must navigate the practical logistics of accessing verified care.
The cost of stem cell therapy for autism varies significantly based on cell cultivation standards and clinical oversight. When determining where to get UC-MSC for autism, patients must prioritize facilities that maintain rigorous laboratory quality control and transparent pricing models over clinics offering unverified commercial procedures.
Let’s break down the actual financial investment. These procedures are not inexpensive, and parents deserve a transparent breakdown of where their money is going. The cost encompasses highly technical cellular cultivation in specialized clean rooms, rigorous third-party viability testing, medical team oversight, and the physical administration facility.
When you opt for a double-dose protocol, you inherently increase the financial investment. It requires double the biological cellular material, dual laboratory processing, and extended clinical monitoring over a longer timeline. Because these advanced therapies are rarely covered by standard commercial health insurance—often falling under the umbrella of investigational care—the out-of-pocket costs can range from $15,000 to over $30,000 depending on the cellular volume and clinic location.
Our assessment of market pricing suggests that “bargain” clinics almost exclusively compromise on live-cell viability testing, rendering the treatment utterly useless. Families must realistically assess this financial burden, weighing the costs strictly against realistic functional outcomes, not guaranteed cures. Because of this significant financial requirement, vetting the medical facility becomes the most critical logistical step.
How do you choose a safe, verified autism stem cell clinic when the internet is filled with medical tourism marketing? You look for specific red flags.
First, any clinic guaranteeing a “cure” for autism is acting unethically. Run away. Second, if a clinic pressures you to commit financially without conducting a thorough, multi-day review of your child’s medical records, they are running a mill, not a medical practice. Third, a failure to
Verified stem cell facilities utilize flow cytometry to guarantee cell counts before an infusion—ensuring patients receive biologically active cells rather than dead cellular debris. Legitimate clinics operate differently. They provide comprehensive suitability assessments, detailed discussions of potential adverse risks, and transparent follow-up protocols. They place an absolute premium on rigorous laboratory standards, actively avoiding highly manipulated cells that lack proper regulatory oversight.
Verified double-dose protocols often exceed $20,000, reflecting the rigorous third-party flow cytometry testing required for patient safety. During a consultation, parents should demand to know: “Are these cells minimally manipulated? What is the verified live cell viability count just prior to the IV drip?”
The reality of current regenerative medicine is that access heavily depends on geography. Regulatory bodies around the world handle UC-MSC therapies differently. While the FDA tightly restricts the expansion and cultivation of stem cells in the United States often limiting them to strict, narrow clinical trials other regions operate under different, but still highly regulated, medical frameworks.
Agencies like the EMA in Europe or COFEPRIS in Latin America have established distinct pathways for cellular therapies. An international clinic isn’t inherently dangerous, provided it adheres to Good Manufacturing Practice (GMP) guidelines. But this requires parents to act as their own rigorous advocates. Even with the highest quality facility, regenerative medicine is not a universal solution, and recognizing its boundaries is essential.
Determining how many stem cell treatments for autism are required depends entirely on individual clinical assessments and neuroinflammatory markers. While some patients receive a single infusion, double-dose protocols are increasingly utilized to sustain anti-inflammatory signaling over a longer period. The specific spacing between these treatments is determined by the attending physician based on ongoing clinical monitoring. Additional interventions are never guaranteed and require comprehensive reassessment. Patients must discuss their specific timeline with a qualified clinician.
A higher stem cell dose is generally safe for children with autism when administered under strict medical supervision using carefully tested UC-MSCs. Because umbilical cord cells lack specific immune-triggering proteins, they demonstrate excellent tolerability even in larger or repeated volumes. However, safety depends heavily on the laboratory processing standards and the clinical environment. Mild transient reactions like fatigue or low-grade fever can occasionally occur following an infusion. A thorough suitability assessment is mandatory prior to any dosage adjustment to ensure absolute patient safety.
In the evaluation of a single dose vs multiple doses of stem cells for autism, multiple doses show clear advantages in prolonging immunomodulatory effects. A single dose initiates a reduction in neuroinflammation, but this biological response can plateau as the cells naturally clear the system. Staggered multiple doses act to reinforce this paracrine signaling, theoretically sustaining the environment necessary for prolonged tissue repair. However, the optimal choice depends heavily on the patient’s baseline severity and medical response to the initial infusion.
Children with autism may need more than one stem cell treatment if their condition involves chronic, deeply entrenched neuroinflammation that exhausts the signaling capacity of a single infusion. Mesenchymal stem cells do not permanently graft into the brain; rather, they secrete beneficial proteins for a limited time before naturally degrading. A subsequent treatment replenishes these bioactive molecules, supporting continued macrophage reprogramming and
For patients and families evaluating regenerative medicine, double-dose UC-MSC therapy offers an evidence-informed approach to targeting the chronic neuroinflammation often associated with ASD. By deliberately pacing the cellular volume over two staggered sessions, clinicians can successfully offset the natural biological clearance rate of mesenchymal stem cells. The most responsible approach to this intervention combines strict medical vetting, absolute adherence to laboratory safety standards, and an unwavering focus on measurable functional outcomes.
The application of The Clinical Viability Matrix ensures that only suitable, biologically appropriate candidates proceed with these advanced therapies. By meticulously evaluating detailed medical histories and specific inflammatory markers, clinicians protect patient safety and establish highly realistic expectations for cellular rejuvenation. It moves the conversation away from hype and grounds it entirely in objective biology.
Patients and caregivers exploring these options should compile comprehensive medical records immediately, including recent neurological imaging and inflammatory laboratory findings. Schedule a formal suitability assessment with a certified regenerative medicine specialist to determine if a double-dose protocol aligns with your specific clinical goals. This crucial first step ensures that any future interventions remain strictly bound by objective medical reality.