Our Services
Others
- DFPP
- Shockwave
- IV Drip

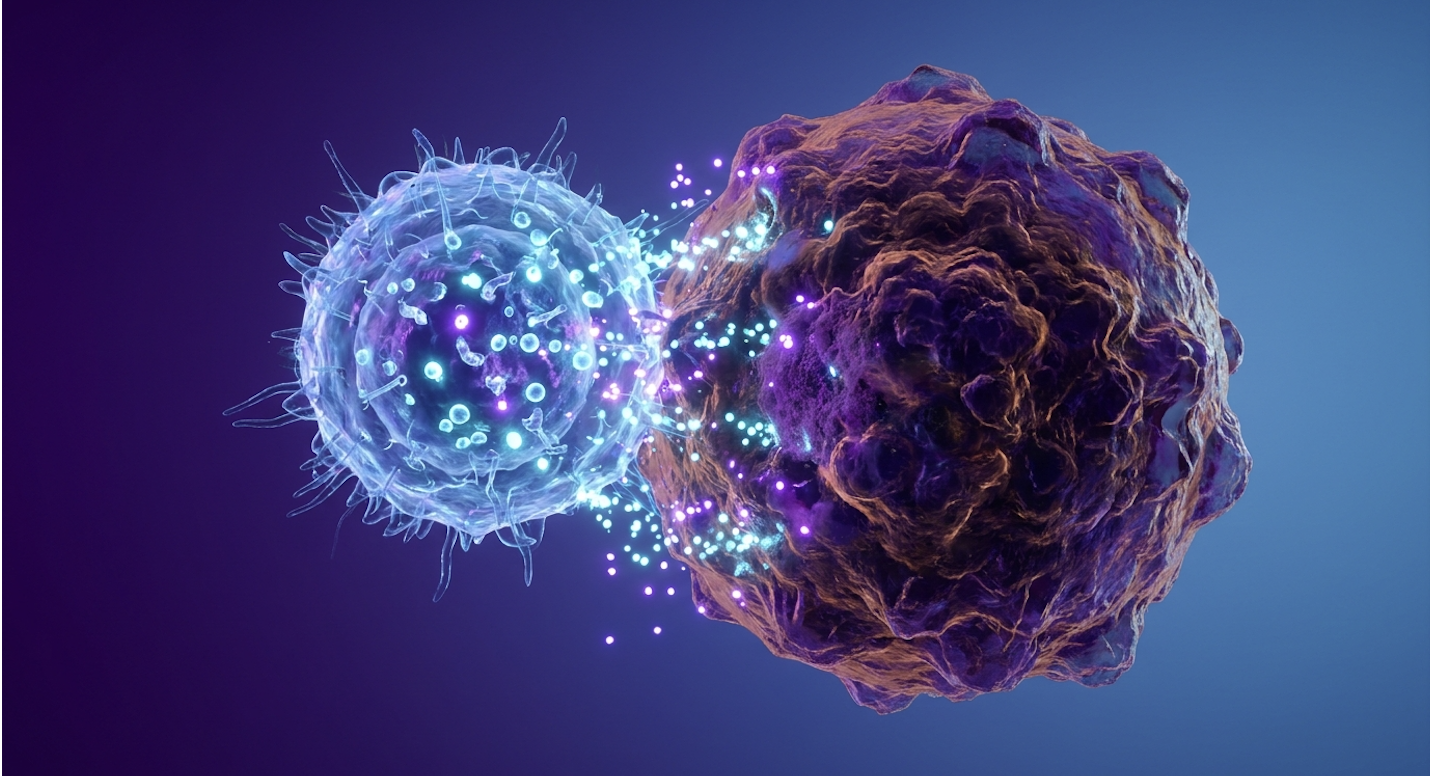
NK cell therapy for cancer utilizes the innate immune system to identify and induce apoptosis in malignant cells without requiring prior antigen exposure. It acts as a frontline defense, destroying tumor cells that evade standard T-cell recognition, and is typically integrated alongside conventional oncology treatments.
Navigating advanced oncology options is incredibly overwhelming. There’s an enormous amount of noise out there clinics selling false hope, misrepresenting early-phase trials, and pushing experimental procedures as guaranteed cures. Patients often get lost in the complex jargon when they just want to know what actually works. Look, we need to be strictly honest about the biology here. This guide maps the realistic, clinical step-by-step journey of NK therapy. We’re going to break down the exact physical process, analyze the evidence for specific cancer applications, and explain precisely how this cellular therapy integrates with standard chemotherapy.
NK cell therapy for cancer utilizes the innate immune system to identify and induce apoptosis in malignant cells without requiring prior antigen exposure.
NK cells cancer treatment hinges on a beautifully brutal biological mechanism. Natural Killer (NK) cells the cytotoxic lymphocytes of your innate immune system constantly patrol your bloodstream, inspecting cellular surfaces for signs of stress, viral infection, or malignant transformation. They don’t need to be “taught” what a cancer cell looks like beforehand.
How do NK cells recognize cancer cells when other immune defenses fail? It comes down to a molecular identification system. Healthy cells display Major Histocompatibility Complex (MHC) class I molecules on their surfaces, essentially presenting a biochemical ID badge that tells the immune system, “I belong here, don’t attack.”
But cancer cells are deceptive. To evade destruction by T-cells, many tumors intentionally downregulate or hide these MHC class I molecules. While this trick successfully blinds T-cells to the tumor’s presence, it triggers an immediate alarm for NK cells. NK cells detect malignant cells by identifying the absence of MHC class I molecules, triggering the release of perforin and granzymes to induce tumor cell death (Frontiers in Immunology, 2022). This is clinically referred to as the “missing self” hypothesis. When NK cell inhibitory receptors fail to find MHC class I, activating receptors like NKG2D lock onto stress ligands expressed by the tumor, authorizing a lethal strike. It’s a highly efficient biological fail-safe. If you want a deeper dive into the foundational biology, review our dedicated literature covering NK cell therapy for cancer in our foundational archives.
Once the NK cell confirms the target is malignant, the biochemical execution is swift. The NK cell forms an immunological synapse a tight physical seal with the cancer cell. It then deploys secretory lysosomes containing two critical proteins: perforin and granzymes.
Perforin acts exactly like a microscopic drill, polymerizing to punch physical pores directly through the cancer cell’s protective membrane. Through these newly created channels, granzymes (highly toxic enzymes) flood into the tumor cell. These enzymes immediately dismantle the cancer cell’s internal structure and activate a cascade that forces the cell to undergo apoptosis, or programmed cell death (Cellular & Molecular Immunology, 2023). The tumor essentially dismantles itself from the inside out, after which the NK cell detaches and moves on to hunt its next target.
The Integrated NK Cell Treatment Pathway is a highly controlled clinical process that translates innate biological mechanisms into a targeted oncological intervention. We aren’t just relying on the body’s natural reserves. How does NK cell therapy work in a clinical setting? It relies on either extracting and expanding the patient’s own cells or sourcing them from healthy donors to achieve massive therapeutic cell counts before reinfusion.
Understanding the NK cell therapy process step by step helps strip away the mystery and anxiety surrounding cellular medicine. It’s a highly regulated, multi-week protocol.
A crucial clinical distinction must be made regarding where these cells originate. The choice between autologous vs allogeneic NK cell therapy dictates the logistical complexity, rejection risks, and overall efficacy of the treatment.
Autologous therapy uses the patient’s own cells. While this eliminates any risk of immune rejection, it carries a massive inherent biological flaw: a cancer patient’s immune system is often profoundly exhausted by the disease and previous chemotherapy. Their NK cells might lack the vigor required to mount a meaningful attack.
Conversely, allogeneic therapy utilizes cells from a healthy, thoroughly screened donor—often sourced from peripheral blood or umbilical cord blood. Donor cells are biologically fresh, highly aggressive, and lack the exhaustion markers seen in patient-derived cells. Remarkably, unlike donor T-cells, allogeneic NK cells rarely cause Graft-Versus-Host Disease (GVHD), making them incredibly valuable for “off-the-shelf” clinical applications (OncoTargets and Therapy, 2020).
| 📌 If you’re interested in why umbilical cord cells are often preferred over bone marrow or fat-derived cells, we have an interesting article that discusses why UC-MSCs are superior to other stem cell sources, which you can read via the internal link. |
Understanding cell sourcing is critical, as the choice directly impacts how effectively the therapy targets specific malignancies.
How long does this entire process take? The complete clinical protocol typically spans two to three weeks from initial cell collection to the final infusion. After the leukapheresis blood draw, the laboratory isolation and expansion phase requires 10 to 14 days to reach therapeutic cell counts (Cytotherapy, 2022). Once ready, the outpatient intravenous reinfusion takes just a few hours. Post-treatment, patients remain closely monitored for immediate biological responses before continuing their standard oncology follow-ups.
Let’s address the reality of what this therapy can actually do today. While NK cells possess the biological capability to target virtually any malignancy, clinical efficacy varies drastically depending on the tumor type, the surrounding microenvironment, and whether the cancer is liquid (blood) or solid.
When it comes to NK cell therapy for leukemia, the clinical data is highly encouraging. Blood cancers are uniquely vulnerable to intravenous cellular therapies. Because leukemic cells circulate freely in the bloodstream and bone marrow, infused NK cells can physically bump into them with ease there are no physical tumor walls to penetrate. In everyday clinical practice, this means intravenous delivery works exactly as intended, immediately putting the therapeutic cells in direct contact with the malignancy.
Clinical data demonstrates over 30% complete remission rates for haploidentical NK cell therapy in specific high-risk leukemia patients proving its efficacy as a biological intervention (Blood, 2005). Multiple phase I and phase II clinical trials have shown that partially matched donor NK cell infusions can induce complete remissions in high-risk Acute Myeloid Leukemia (AML) patients, particularly when administered after traditional chemotherapy has reduced the overall tumor burden (The Lancet Oncology, 2020). Lymphomas and multiple myeloma are also primary targets in current hematological research, showing significant responsiveness to engineered NK variants.
Solid tumors represent a completely different, vastly more difficult battlefield. Unlike blood cancers, solid masses develop complex microenvironments with erratic blood vessels, making it physically difficult for immune cells to even arrive at the site.
Research into NK cell therapy for lung cancer is heavily focused on overcoming the suppressive environment of the pulmonary tumor beds. Non-small cell lung cancer (NSCLC) actively secretes factors that paralyze incoming immune cells. Current clinical trials are testing whether combining NK infusions with immune checkpoint inhibitors (like Keytruda) can keep the NK cells aggressive once they reach the lung tissue (Journal of Thoracic Oncology, 2023).
For patients exploring NK cell therapy for breast cancer, the data is highly nuanced. Triple-negative breast cancer (TNBC) which lacks standard targeted therapy options is a major focus of ongoing NK trials. In recent clinical setups, combining NK cells with targeted antibodies has shown promise in bypassing standard resistance mechanisms. Researchers are actively engineering CAR-NK cells (Chimeric Antigen Receptor NK cells) to specifically hunt HER2-positive breast cancer cells, attempting to replicate the success of targeted antibody drugs but with a living cellular weapon.
NK cell therapy for pancreatic cancer remains one of the most frustrating frontiers in modern oncology. We have to be extremely honest about this difficulty. Pancreatic adenocarcinomas surround themselves with a dense, scar-like tissue called a desmoplastic stroma. This fibrotic wall physically blocks immune cells from ever reaching the malignant core. Infusing billions of NK cells won’t help if they literally cannot touch the tumor. Current investigational protocols are combining NK cells with stroma-degrading drugs, attempting to breach the fortress wall before the cellular infantry arrives. Because solid tumors present such formidable barriers, NK cell therapy is rarely utilized in isolation.
There is a dangerous misconception in alternative medicine circles that natural cellular therapies should entirely replace standard oncology. That is clinically false. NK cell therapy with chemotherapy is the standard investigational protocol precisely because the two approaches are profoundly synergistic. Chemo isn’t the enemy here it’s the setup.
The most effective clinical protocols utilize NK therapy as a complementary adjunct to standard care. Before a patient receives an infusion of donor NK cells, oncologists typically administer a mild chemotherapy regimen often fludarabine and cyclophosphamide. This process, known as lymphodepletion, temporarily suppresses the patient’s existing regulatory T-cells (which normally suppress immune responses) and physically clears space in the bone marrow for the new NK cells to expand (Journal for ImmunoTherapy of Cancer, 2021).
Furthermore, many traditional chemotherapies actually stress cancer cells without killing them immediately. This cellular stress forces the tumor to upregulate stress-induced ligands on its surface. By turning up the volume on these biological distress signals, chemotherapy makes the surviving cancer cells massively more visible to the infused NK cells. If you want to understand the broader systemic impacts of these protocols, exploring the advantages of NK cell therapy reveals how this combined approach minimizes disease relapse. Some advanced protocols also incorporate mesenchymal stem cells to modulate the immune response; you can review our laboratory processing details on UC-MSCs and NK Cells Synergy to understand how cellular therapies interact.
| 📌 If you’re interested in how MSCs calm overactive immune cells throughout the body, we have an interesting article that discusses mesenchymal stem cell therapy for immune modulation, which you can read via the internal link. |
Administering NK cells at the precise moment is critical for maximum efficacy. Oncologists carefully time infusions to follow lymphodepleting chemotherapy regimens to ensure the immune environment is perfectly primed. This pre-conditioning window creates a favorable cytokine environment for the incoming NK cells to thrive. A comprehensive review published in immunology literature (Frontiers in Immunology, 2022) confirmed that patients receiving properly timed lymphodepletion experienced significantly higher in vivo expansion and persistence of donor NK cells compared to those who skipped pre-conditioning entirely. Even with optimized pre-conditioning and chemotherapy synergy, malignancies employ sophisticated defenses to survive.
To demonstrate real clinical authority, we must acknowledge the limitations. How do cancer cells escape NK cells? They don’t just passively wait to be destroyed. Malignant tumors are highly adaptive, evolving sophisticated mechanisms to blind, exhaust, and repel cellular therapies.
Solid tumors survive by engineering a highly toxic neighborhood known as the tumor microenvironment (TME). Within this space, cancer cells secrete intense immunosuppressive chemicals, most notably Transforming Growth Factor-beta (TGF-beta). When an activated NK cell enters a TGF-beta-rich environment, its metabolic engines are forcibly shut down. It loses its ability to secrete perforin and granzymes, rendering it harmlessly paralyzed right next to the cancer it was meant to kill (Nature Reviews Immunology, 2018).
Additionally, dense fibrotic tissue surrounding solid tumors creates a physical fortress. This formidable biological barrier prevents immune cells from reaching the malignant core, which is why treating solid tumors is vastly more complex than blood cancers.
Cancer cells don’t just hide; they actively deploy countermeasures. One of the most frustrating biological defenses is ligand shedding. Malignant cells can literally detach stress ligands (like MICA and MICB) from their surfaces, releasing them directly into the bloodstream. When circulating NK cells encounter these floating biochemical decoys, they prematurely fire their cytotoxic payloads into empty space, exhausting their reserves before they ever reach the actual tumor mass (Nature Communications, 2021). Understanding these escape mechanisms is precisely why patient selection and rigorous clinical evaluation are paramount.
Determining who is a candidate for NK cell therapy requires far more than a simple desire for alternative treatments. It demands a rigorous, evidence-based oncological review to ensure the treatment is biologically appropriate.
Candidacy is established through an exhaustive medical review of recent PET/CT imaging, detailed pathology reports, complete blood counts, and a comprehensive history of prior treatments. The clinical team must evaluate the tumor burden, the specific genetic markers of the malignancy, and the patient’s overall biological resilience (Journal of Translational Medicine, 2022). For deeper insights into how patient blood samples are analyzed to determine baseline immune competence, review our laboratory processing details.
Can NK cell therapy be used for stage 4 cancer? For advanced metastatic disease, cellular therapy is not classified as a definitive cure, but it is frequently explored within clinical trials or specialized compassionate use programs. In these severe cases, it serves as an adjunctive biological intervention to potentially slow disease progression and stabilize a profoundly compromised immune system. According to recent clinical trial analyses (Clinical Cancer Research, 2023), late-stage patients require exhaustive baseline immune profiling to determine if an allogeneic NK cell transfer remains a viable intervention alongside ongoing palliative care. While identifying candidacy is the first step, patient safety remains the ultimate clinical priority.
While cellular immunotherapies represent a massive leap forward, they are powerful biological interventions that require strict medical oversight and realistic expectations.
Patients can still experience infusion reactions, temporary fever, fatigue, and localized inflammation following treatment. It is vital to explicitly state that for many solid tumors, NK cell therapy remains strictly an investigational application rather than a primary standard of care. Readers must familiarize themselves with Vega Stem Cell’s established cellular therapy safety standards before proceeding. A consultation does not guarantee eligibility, treatment administration, or clinical improvement.
| 📌 If you’re interested in how to tell a well-regulated stem cell clinic from a risky one, we have an interesting article that discusses whether stem cell therapy is safe in Thailand, which you can read via the internal link. |
Is NK cell therapy safer than CAR-T therapy? Clinical data overwhelmingly suggests that NK cell therapy presents a fundamentally safer profile than traditional CAR-T interventions. Because NK cells naturally secrete a different, far less inflammatory array of cytokines, they rarely trigger life-threatening Cytokine Release Syndrome (CRS) or severe neurotoxicity the hallmark dangers of CAR-T protocols (Blood Advances, 2021). Additionally, because donor NK cells do not rely on the same recognition pathways as T-cells, allogeneic therapies carry a remarkably low risk of Graft-Versus-Host Disease (GVHD), allowing for much safer “off-the-shelf” donor treatments.
Natural Killer (NK) cells recognize cancer cells by detecting the absence of specific surface proteins called MHC class I molecules. Healthy cells display these molecules to signal they are normal, but tumors often hide them to evade T-cells. When an NK cell encounters a cell missing this “self” marker, its activating receptors trigger an immediate destructive response. This unique biological mechanism allows NK cells to attack malignancies without requiring prior exposure to the cancer antigen.
Cancer cells escape NK cells by creating a highly immunosuppressive tumor microenvironment that chemically deactivates immune responses. Tumors secrete inhibitory factors like TGF-beta, which physically exhaust and paralyze incoming NK cells before they can attack. Additionally, tumors can shed decoys into the bloodstream that trick NK cells into firing their weapons prematurely. Researchers are actively developing engineered CAR-NK therapies designed specifically to overcome these evasive barriers.
While there is no strict universal age limit, clinical suitability is determined by biological resilience rather than chronological age. Oncologists heavily evaluate liver and kidney function, cardiovascular health, and previous treatment toxicity. Many patients in their 70s successfully undergo therapy if their baseline organ function remains strong enough to tolerate the required lymphodepleting chemotherapy regimens (Journal of Geriatric Oncology, 2022).
Currently, NK cell therapy is not FDA approved as a standard first-line treatment for all cancers. While it is available through highly regulated clinical trials and specific expanded access programs, it remains an investigational protocol for most solid tumors (FDA Clinical Guidance, 2023). Patients must consult with their oncology team to access these therapies through authorized research pathways.
Yes, through a highly controlled process called cryopreservation, NK cells can be frozen and stored for future use. Healthy donor cells (allogeneic) are frequently cryopreserved to create “off-the-shelf” treatments that are immediately available when a patient requires rapid intervention. Clinical data indicates that utilizing specific cryoprotectants allows these cells to retain over 80% of their cytotoxic viability upon thawing (Cytotherapy, 2023).
For patients navigating advanced oncology care, NK cell therapy offers a targeted biological approach that identifies and destroys malignancies utilizing the immune system’s innate mechanisms. While strongest clinical evidence exists for hematological cancers like leukemia, ongoing trials are rapidly expanding applications for solid tumors. The most effective clinical pathways integrate this cellular therapy directly with standard chemotherapy regimens rather than acting as a standalone replacement.
Successfully navigating The Integrated NK Cell Treatment Pathway requires separating proven biological improvement from investigational hype. Finding reliable, clinical-grade oncology options is incredibly stressful, but relying on a standardized, evidence-informed pathway ensures that cellular interventions are applied safely and logically.
If you are exploring cellular immunotherapy options, your next step is a rigorous medical review. Request a suitability assessment with Vega Stem Cell via WhatsApp, email, or our secure booking form on the contact page to speak with our clinical team. Please ensure you gather your most recent PET/CT imaging, bloodwork, and complete pathology reports prior to your consultation to allow for an accurate, honest evaluation of your case.